








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.

You’ve done everything the box said. The cream went on, it stayed on for the full time, you washed the bedding at a temperature that worried your machine — and a week later you find a live louse walking across your child’s parting. Now you are standing in front of two options wondering whether the second one will work any better than the first.
That is the situation most people are in when they search permethrin vs ivermectin, and it deserves a better answer than a list of features. By the end of this guide you will know what genuinely separates these two treatments, which one suits which situation, and — the part that turns out to matter most — why a failure with one is a real reason to switch to the other rather than repeat the same thing harder.
There is also a number in the research that surprises almost everyone who assumes one of these drugs is simply better. We will come to it.
- By four weeks, the cure rates are much closer than the internet suggests — the real decision happens elsewhere.
- They attack completely different targets in the parasite’s nervous system, which is exactly why switching after a failure makes sense.
- Age limits differ, and for young children that difference alone can settle the choice.
- One of them is ahead in the first week and the other catches up — knowing which prevents a lot of premature panic.
- The most common reason treatment “fails” has nothing to do with which drug you picked.
Permethrin vs Ivermectin: The Short Answer
Because you are probably mid-infestation and short on patience, here is the decision rule up front.
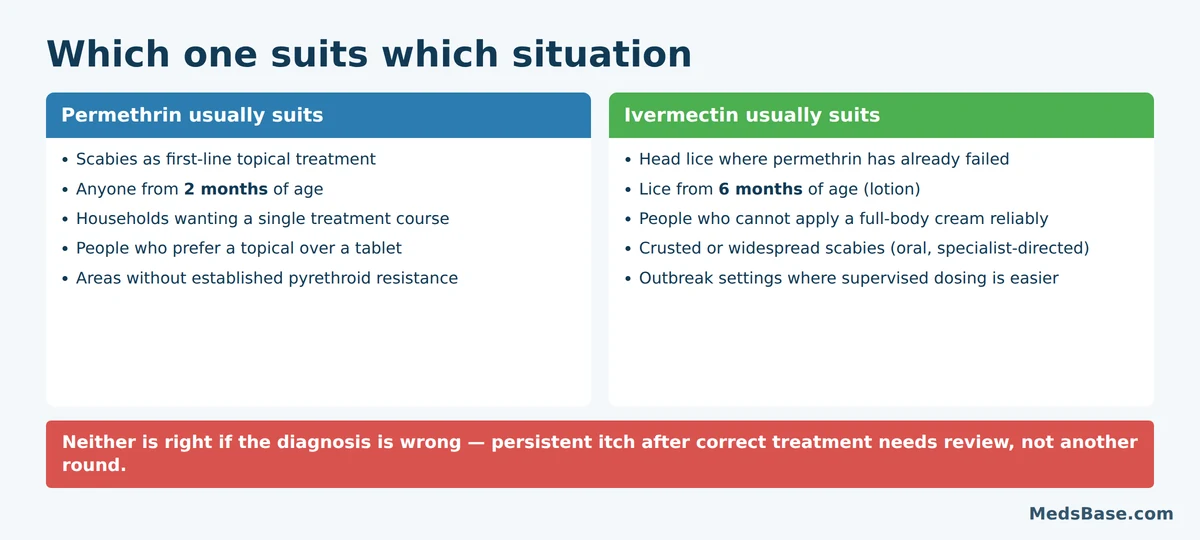
- Scabies, first treatment, no complications permethrin cream is the standard first-line topical choice.
- Head lice, first treatment permethrin is the usual starting point where pyrethroid resistance is not established locally.
- Head lice, permethrin already tried properly and failed switch to ivermectin lotion rather than repeating permethrin.
- Anyone under 6 months permethrin is the option with the lower age threshold; ivermectin lotion starts at 6 months.
- Crusted or widespread scabies, or an institutional outbreak oral ivermectin, often combined with topical treatment, under medical direction.
- Whole household affected treat everyone at the same time regardless of which drug you choose. This matters more than the choice itself.
The rest of this guide explains why each of those holds, because knowing the reasoning is what lets you adapt when your situation does not match the list exactly.
How Each One Actually Kills the Parasite
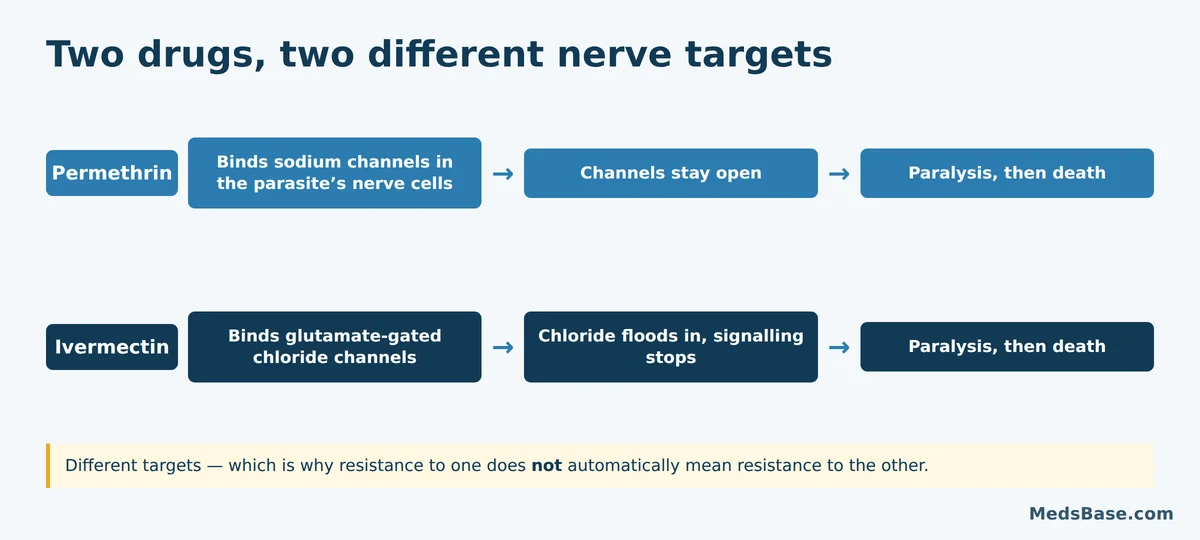
Here is where permethrin vs ivermectin gets interesting, and it is directly relevant to your decision rather than just biology trivia.
Permethrin is a synthetic pyrethroid. It binds to sodium channels in the parasite’s nerve cells and jams them open. Sodium keeps flooding in, the nerve fires uncontrollably, and the insect or mite is paralysed and dies. Think of it as taping down a light switch — the circuit can never reset.
Ivermectin goes after a different door entirely. It binds glutamate-gated chloride channels, which are found in invertebrate nerve and muscle cells but not in the equivalent form in humans. Chloride floods in, the cell becomes unable to fire at all, and the parasite is paralysed. That selectivity is why ivermectin has a good safety record in humans despite being potent against parasites.
Two different molecular targets means resistance to one does not automatically confer resistance to the other — which is the single most useful fact in this entire comparison.
That matters because pyrethroid resistance in head lice is widespread and well documented. Populations of lice carrying knockdown-resistance mutations have spread globally over decades of permethrin use. If the lice in your local area carry those mutations, permethrin can be applied perfectly and still fail — not because you did anything wrong, but because the drug’s target has changed shape.
Ivermectin’s target has not been under the same selection pressure for anything like as long, which is why it works in populations where permethrin has stopped working. Switching molecular targets after a failure is a strategy, not a guess.
Head Lice Treatment: Which One and When
In head lice treatment, permethrin is typically the starting point, and ivermectin lotion is the strong second line — with an important nuance about what “second line” means here.
Permethrin lotion is applied to damp, shampooed hair — no conditioner, because it interferes with the lotion — left on for 10 minutes, then rinsed. MedlinePlus drug information for permethrin is explicit about the follow-up rule: if live lice are seen 7 days or more after the first treatment, a second application is needed. Permethrin has limited effect on eggs, so the second application catches whatever hatched after the first.
Ivermectin lotion works differently in practice. It is applied to dry hair for 10 minutes, then rinsed with water only — and MedlinePlus drug information for topical ivermectin notes it is usually a single treatment, not to be repeated without advice. It is approved from 6 months of age.
That single-application property is genuinely useful with a squirming five-year-old, and it is the practical reason many families prefer it after a first failure.
One practical note that applies whichever you pick: nit combing with a fine-toothed comb over the following days is worth doing regardless. It removes dead lice and eggs, and — more usefully — it is how you find out whether the treatment worked, rather than guessing from itch alone.
Scabies: Which One and When
Scabies flips the default in the permethrin vs ivermectin decision. Here permethrin 5% cream is the standard first-line topical treatment, and oral ivermectin is the main alternative.
Permethrin cream is applied from the neck down over the entire body — including between fingers and toes and in all skin folds — left on for 8 to 14 hours, then washed off. For infants and adults over 65, the scalp, hairline, temples and forehead are included too. If live mites are seen 14 days or more after treatment, a second application is indicated.
Oral ivermectin is taken as tablets dosed by body weight, usually as two doses about a week apart. That second dose is not optional in most protocols: ivermectin does not reliably kill mite eggs, so the repeat catches the newly hatched generation. If you go this route, how ivermectin is dosed by body weight covers the arithmetic, and the full guide to using ivermectin for scabies covers timing and safety in detail.
When oral ivermectin is clearly preferred: crusted (Norwegian) scabies, where mite burden is enormous and cream cannot penetrate reliably; institutional outbreaks where supervising a swallowed tablet is far more practical than supervising whole-body cream application on dozens of people; and anyone who cannot apply a full-body cream properly — limited mobility, dexterity problems, or living alone without help.
The most important thing about scabies is not the drug choice at all. NHS guidance on scabies makes the point plainly: everyone in the household should be treated at the same time, even those with no symptoms, because it takes weeks for symptoms to appear after infestation. Treating one person and waiting to see who itches next is how households end up in a months-long cycle.
Expect the itch to continue for two to four weeks after successful treatment. That is an immune reaction to dead mites and their debris, not treatment failure. Assuming it means the drug failed leads people into unnecessary repeat treatments and skin irritation.
Permethrin vs Ivermectin on Application, Age Limits and Repeat Doses
The practical differences that separate permethrin vs ivermectin day to day, side by side.
| Permethrin | Ivermectin | |
|---|---|---|
| Forms | 5% cream (scabies), lotion (lice) | Lotion (lice), tablets (scabies) |
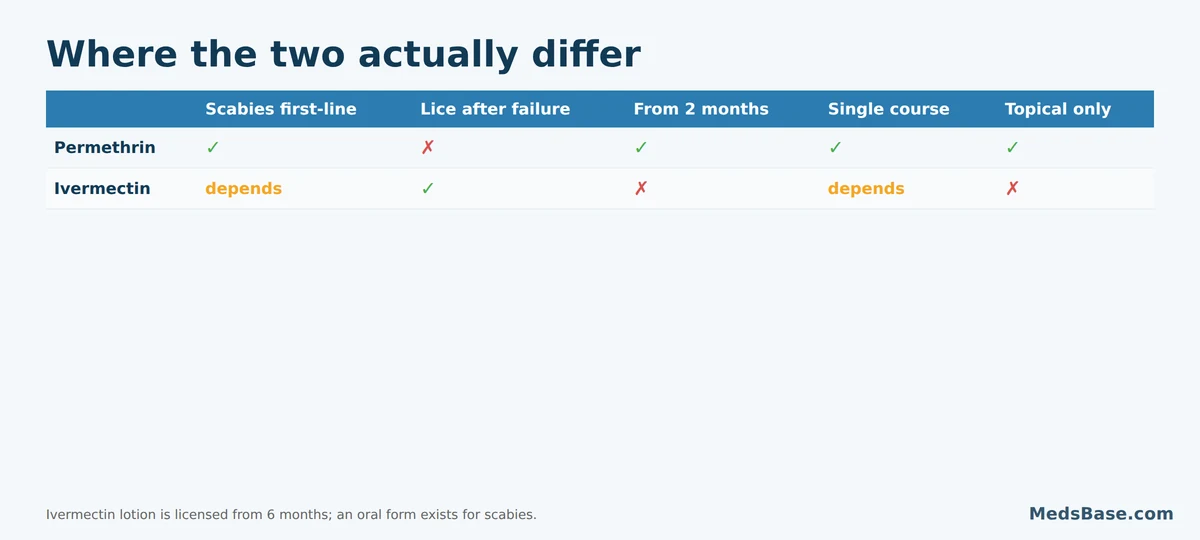
| Minimum age | From 2 months | Lotion from 6 months; tablets by weight, specialist advice in small children |
| Contact time | Cream 8–14 hours; lotion 10 minutes | Lotion 10 minutes; tablets swallowed |
| Hair state for application | Damp, shampooed, no conditioner | Dry hair |
| Repeat needed | Lice: repeat at 7 days if live lice seen. Scabies: repeat at 14 days if live mites seen | Lotion: usually single application. Tablets: commonly two doses a week apart |
| In pregnancy | Generally the preferred topical option | Discuss with a clinician first |
| Main practical drawback | Whole-body application is a chore; resistance is common in lice | Fewer options in the very young; oral form needs weight-based dosing |
The age threshold does real work in a decision. If you are treating an infant under 6 months, permethrin is the option with the established lower limit, and that alone often settles it.
MedsBase stocks both arms of this comparison — Perlice Cream (permethrin) and Ivrea Shampoo (ivermectin) — and no prescription is needed to order from MedsBase.com. Which one belongs in your basket depends on the decision rule above, not on which is stronger, because as the next section shows, “stronger” is not really what the evidence found.
What the Research Says About Permethrin vs Ivermectin
Here is the number that surprises people.
| Study | Year | Design | Finding |
|---|---|---|---|
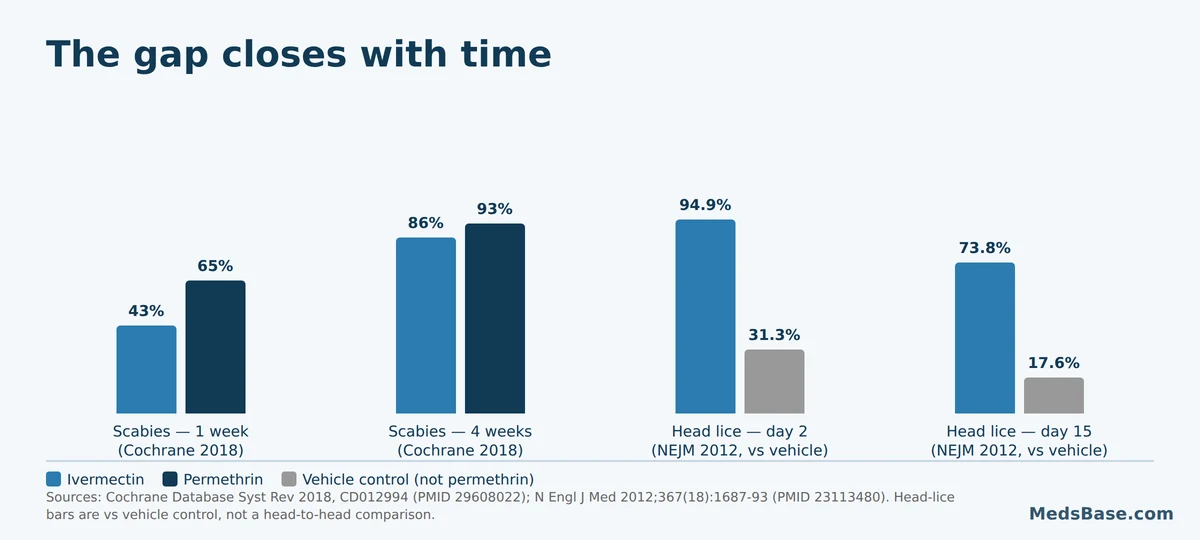
| Cochrane review, ivermectin and permethrin for scabies | 2018 | Systematic review, 15 studies, 1,896 participants | At 1 week, oral ivermectin cleared ~43% vs permethrin ~65%. At 4 weeks, ~86% vs ~93% — little or no difference (low-certainty evidence). No withdrawals due to adverse events in either group (moderate certainty) |
| Topical 0.5% ivermectin lotion for head lice | 2012 | Two randomised double-blind trials vs vehicle control, single 10-minute application, no nit combing | Louse-free: day 2 94.9% vs 31.3%; day 8 85.2% vs 20.8%; day 15 73.8% vs 17.6% (all P<0.001) |
| Oral ivermectin vs malathion lotion, difficult-to-treat lice | 2010 | Randomised controlled trial, 812 patients from 376 households | Oral ivermectin given twice at a 7-day interval had superior efficacy to topical 0.5% malathion in infestations that had already failed treatment |
The headline finding is the Cochrane one, because it is the only genuinely head-to-head evidence of the two drugs at scale. A Cochrane review compared them directly across 15 studies and 1,896 participants, and the result is more useful than a winner: at one week permethrin was clearly ahead, and by four weeks the gap had mostly closed.
That single result reframes the whole question. If you judge these drugs at day seven, permethrin looks substantially better. If you judge at four weeks — which is when it actually matters, because that is when you find out whether the infestation is gone — they are close. The Cochrane authors rated the certainty of that evidence as low, and the honest reading is that neither drug is decisively superior for ordinary scabies.
What this means for you: stop trying to pick the more powerful drug, because on this evidence there isn’t one. Pick the one that fits your parasite, your age group, your resistance situation and your ability to apply it properly.
For head lice, trials of the 0.5% lotion tested ivermectin against a vehicle control rather than against permethrin, so they establish that it works well from a single application — 73.8% still louse-free at day 15 without any nit combing — rather than that it beats permethrin head to head. That distinction is worth being clear about, because plenty of pages present those figures as though they were a comparison. They are not.
Where the evidence gets genuinely directional is in treatment failure. In infestations that had already resisted treatment, oral ivermectin outperformed a topical alternative in a randomised trial of 812 patients across 376 households. The comparator there was malathion rather than permethrin, so it is not a direct answer to this article’s question — but it supports the underlying principle that when a topical approach has failed, changing tack is more productive than repeating it.
Permethrin vs Ivermectin: The Side-by-Side Comparison
| Situation | Better fit | Why |
|---|---|---|
| Scabies, first treatment, otherwise healthy adult | Permethrin cream | Standard first-line topical; faster early clearance |
| Scabies, cannot apply cream reliably | Oral ivermectin | A swallowed tablet does not depend on application technique |
| Crusted or widespread scabies | Oral ivermectin, often with topical | Cream cannot penetrate heavy crusting alone |
| Head lice, first treatment, no local resistance | Permethrin lotion | Widely available, well established, low cost |
| Head lice after a properly applied permethrin failure | Ivermectin lotion | Different molecular target; usually a single application |
| Infant under 6 months | Permethrin | Lower established age threshold |
| Pregnancy | Permethrin (topical) | Generally the preferred topical option; discuss ivermectin first |
| Institutional outbreak | Oral ivermectin | Supervised dosing is far more practical at scale |
Which one fits which situation? If you are treating scabies for the first time in an otherwise healthy person who can apply a cream properly, permethrin is the sensible default and the evidence supports it. If you are treating head lice that have already survived a correct permethrin application, ivermectin is the logical switch and repeating permethrin is not. If age, pregnancy or application difficulty is the constraint, that constraint should decide — because on cure rates alone, at four weeks, you are choosing between two similar outcomes.
When Treatment Fails — and What to Do Next
This resolves the last open loop: the most common reason treatment appears to fail has nothing to do with the permethrin vs ivermectin choice at all.
In rough order of frequency:
- The itch is normal post-treatment itch. After scabies treatment, itching commonly continues for two to four weeks as your immune system reacts to dead mites. This is the single most common false alarm. Persistent itch alone is not evidence of failure.
- The household was not treated together. One untreated family member reinfests everyone. This causes more apparent treatment failures than drug resistance does.
- Application was incomplete. Missing the webbing between fingers, under nails, the buttock crease, or stopping at the wrists. With lice: using conditioner before permethrin lotion, or not using enough product to saturate the hair.
- The repeat dose was skipped. Neither drug reliably kills eggs. Skipping the second application or second tablet dose leaves the next generation to hatch.
- Genuine resistance. Real and common for pyrethroids in head lice — but it belongs after the four checks above, not before them.
- The diagnosis was wrong. Eczema, contact dermatitis and other itchy conditions get mistaken for scabies. No antiparasitic will help, and repeated treatment makes the skin worse.
Mistakes to avoid: repeating the same treatment a third time without changing anything; treating one person in a household; applying a repeat dose earlier than directed in the hope of speeding things up; using a veterinary formulation; and assuming continued itch means continued infestation. If you have completed a correct course, treated the household, and still have live parasites, that is the point to seek assessment rather than buy a third product.
- The full guide to using ivermectin for scabies — timing, dosing and safety in depth.
- What side effects to expect from ivermectin — the common, the rare and what needs attention.
- How ivermectin is dosed by body weight — for the oral form, where the arithmetic matters.
Frequently Asked Questions
Q: Which is better for scabies, permethrin or ivermectin?
A: On permethrin vs ivermectin for a first, uncomplicated case, permethrin cream is the standard first-line topical choice, and a Cochrane review of 15 studies found it cleared scabies faster in the first week — roughly 65% versus 43% at seven days. By four weeks the difference had largely closed, at about 93% versus 86%, rated as low-certainty evidence. Oral ivermectin is preferred for crusted or widespread scabies, institutional outbreaks, and anyone who cannot apply a full-body cream reliably.
Q: Can you use permethrin and ivermectin together?
A: Combined treatment is used in specific situations — most notably crusted scabies, where oral ivermectin is commonly given alongside topical treatment because the mite burden is very high and cream alone cannot penetrate thick crusting. This is a clinician-directed approach rather than something to attempt independently. For ordinary scabies or head lice, there is no established benefit to using both at once, and it increases skin irritation without improving cure rates.
Q: Why did permethrin not work for my lice?
A: Three likely explanations, in order. Pyrethroid resistance is widespread in head lice populations, so permethrin can be applied perfectly and still fail. Application error is common — using conditioner beforehand, or not using enough product to saturate the hair, both reduce effectiveness. And the second application at seven days is frequently skipped, which lets newly hatched lice re-establish. If application was correct and the repeat was done, resistance is the likely answer and switching to ivermectin is more sensible than trying permethrin again.
Q: How long does permethrin take to work?
A: It begins killing lice and mites within minutes of contact, but that is not the same as the infestation being resolved. For lice, check for live lice at seven days; a second application is indicated if any are found. For scabies, check at 14 days and repeat if live mites are seen. The itch of scabies typically continues for two to four weeks after successful treatment, so how you feel is a poor guide — look for live parasites instead.
Q: Is ivermectin safe for children?
A: Ivermectin lotion for head lice is approved from 6 months of age, and children aged 12 and under will need an adult to apply it. Oral ivermectin for scabies is dosed by body weight, and its use in very small children is generally a matter for medical advice rather than self-treatment. If you are treating an infant under 6 months, permethrin has the lower established age threshold at 2 months, which usually makes it the appropriate option.
Q: Do you need to repeat scabies treatment?
A: Usually yes, and this is where treatment most often goes wrong. Neither drug reliably kills mite eggs, so a single dose can leave the next generation to hatch. With permethrin cream, a second application is indicated if live mites are seen 14 days or more after the first. With oral ivermectin, two doses about a week apart is the common protocol. Skipping the repeat is one of the most frequent reasons an otherwise correct treatment fails.
Q: Does everyone in the house need treating?
A: For scabies, yes — everyone in the household should be treated at the same time, including people with no symptoms. Scabies can take several weeks to produce symptoms after infestation, so someone who feels fine today may already be carrying mites. Treating people one at a time as they start itching is how households end up in a months-long reinfestation cycle. For head lice, check everyone and treat those who actually have live lice.
Q: Is a shampoo or lotion better than a cream?
A: They serve different jobs rather than competing, which is why format matters as much as the permethrin vs ivermectin choice. Lotions and shampoo-style products are formulated for the scalp and hair, where head lice live, and use short 10-minute contact times. Creams are formulated for whole-body application against scabies mites, which burrow into skin across the body, and need 8 to 14 hours of contact. Using a scalp product for scabies, or a body cream for lice, means the treatment is not designed for where the parasite actually is.
The Bottom Line
On permethrin vs ivermectin, the honest verdict is that neither is decisively stronger — and that is genuinely good news, because it means you can choose on the factors you can actually assess. The best head-to-head evidence available found permethrin ahead at one week and the two drugs close by four weeks. Everything useful in this decision sits elsewhere: which parasite, what age, whether permethrin has already failed locally or personally, and whether you can realistically apply a whole-body cream for eight hours.
The one action worth taking before you buy anything: confirm whether this is a first treatment or a repeat after failure. If it is a first attempt, permethrin is a reasonable default for both lice and scabies. If a correct permethrin course has already failed, switch molecular targets rather than repeating — that is the single most useful principle on this page. And whichever you choose, treat the household together, because that decision matters more than the drug does.
If you have worked out which one your situation calls for, you can compare Perlice Cream (permethrin) and Ivrea Shampoo (ivermectin) side by side.
Wondering what to expect once you start? What side effects to expect from ivermectin covers the common and the rare. And if you arrived here because a routine blood test flagged something else entirely, how to lower uric acid without guesswork sorts out what diet realistically achieves.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.