








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
leptin hormone weight loss drugs — Leptin Hormone Weight Loss Drugs: 8 Proven Insights About the Comeback Hormone. Read on for an evidence-backed guide covering everything you need to know.

In 1994, scientists discovered a hormone that made obese mice thin within weeks. Thirty years later, that same hormone — leptin — is staging a comeback that could change how we think about leptin hormone weight loss drugs forever. You have probably heard the GLP-1 success stories. You have almost certainly heard the side-effect horror stories too — the nausea, the vomiting, the muscle loss that leaves people looking gaunt rather than healthy. What if there were a partner drug that could boost the weight loss, protect your muscle, and dial down the misery? That is the promise researchers are chasing right now with leptin hormone weight loss drugs. And the science, buried for decades, is suddenly looking very interesting again.
The story of leptin hormone weight loss drugs spans thirty years of soaring hopes, humbling failures, and a quiet revival that most people missed. If you quit a GLP-1 drug because the side effects were unbearable, or because the weight came roaring back the moment you stopped, this article is for you. What you are about to read could reshape how you think about the next generation of obesity treatment.
Key Takeaways
- Leptin was discovered in 1994 and made obese mice thin in weeks — but the first wave of leptin hormone weight loss drugs failed spectacularly in humans because most people with obesity are leptin-resistant, not leptin-deficient.
- 2026 marks a dramatic reversal. Scientists now believe leptin hormone weight loss drugs work best as partners to GLP-1 agonists — not replacements. The combination targets both short-term appetite and long-term weight stability.
- Muscle preservation is the headline feature. Unlike GLP-1s, which can cause significant lean tissue loss, early research suggests leptin hormone weight loss drugs help your body burn fat while holding onto muscle.
- Side effects may be milder. Because leptin acts through a different brain pathway than GLP-1s, researchers expect less nausea — potentially solving the #1 reason patients quit.
- Natural support works right now. While the drug pipeline matures, you can support healthy leptin levels today through sleep, exercise, and dietary choices — no prescription needed.
- Timeline to market: most candidates in the pipeline are in preclinical or early-phase trials. Real-world availability for leptin hormone weight loss drugs is likely 3–7 years away, though metreleptin is already FDA-approved for a rare condition.
Table of Contents
- What Are Leptin Hormone Weight Loss Drugs?
- How Does Leptin Work for Weight Loss?
- Why Did Early Leptin Hormone Weight Loss Drugs Fail?
- The 2026 Comeback: Leptin Hormone Weight Loss Drugs as GLP-1 Partners
- Leptin Hormone Weight Loss Drugs: What’s in the Pipeline?
- Safety & Side Effects of Leptin Hormone Weight Loss Drugs
- What Does the Research Say About Leptin Hormone Weight Loss Drugs?
- How to Support Healthy Leptin Levels Naturally
- Frequently Asked Questions About Leptin Hormone Weight Loss Drugs
- The Bottom Line on Leptin Hormone Weight Loss Drugs
Leptin Hormone Weight Loss Drugs: 8 Proven Insights About the Comeback Hormone
What Are Leptin Hormone Weight Loss Drugs?
Leptin hormone weight loss drugs are pharmaceutical compounds that target the body’s leptin signaling system — the hormonal pathway your fat cells use to tell your brain how much energy you have stored. In the simplest terms: leptin is your body’s fuel gauge. When fat stores are full, your fat cells release leptin into your bloodstream. That leptin travels to your hypothalamus and delivers a clear message: “We have enough energy. You can stop eating now and burn some stored fuel.”
When the system works, you feel full after a reasonable meal and your metabolism hums along at a healthy clip. When it breaks — and it breaks in most people carrying extra weight — the fuel gauge reads empty no matter how much fat you have stored. Your brain, starved of the leptin signal, thinks you are in a famine. It dials up hunger, slows your metabolism, and fights every attempt you make to lose weight.
Leptin hormone weight loss drugs aim to fix that broken signal. The earliest approach was simple: inject synthetic leptin and let the body respond. That worked — but only in the tiny fraction of people who actually lack leptin. For everyone else, scientists needed a smarter strategy. Today’s leptin hormone weight loss drugs are designed to restore leptin sensitivity, combine leptin with other metabolic signals, or neutralize the excess leptin that fuels resistance. It is a fundamentally different approach than the one that failed in the 1990s.
How Does Leptin Work for Weight Loss?

To understand leptin hormone weight loss drugs, you first need to understand the hormone itself. Leptin is a peptide hormone — a chain of 167 amino acids — produced primarily by your white adipose tissue. That is the scientific name for the fat cells sitting under your skin and around your organs. The more fat tissue you carry, the more leptin your cells pump out. It sounds backwards, but that is exactly how the system is designed: high leptin levels are supposed to mean “stop eating, you have plenty of reserves.”
Here is what happens in a healthy leptin system, step by step:
Step 1 — Fat cells release leptin. After you eat and your fat stores expand, adipocytes secrete leptin into your bloodstream in proportion to your total body fat.
Step 2 — Leptin crosses the blood-brain barrier. The hormone travels to your brain and passes through a specialized transport system at the blood-brain barrier to reach the hypothalamus.
Step 3 — Leptin binds to receptors in the arcuate nucleus. Inside the hypothalamus, leptin docks onto LEPR-B receptors on two competing sets of neurons: POMC neurons (which suppress appetite) and AgRP/NPY neurons (which drive hunger). Leptin activates the “stop eating” POMC pathway and silences the “keep eating” AgRP/NPY pathway.
Step 4 — Appetite drops, energy expenditure rises. With POMC firing and AgRP quiet, your brain reduces food intake and increases sympathetic nervous system activity, which ramps up metabolism and fat burning.
Step 5 — The thyroid and reproductive systems get involved. Leptin also signals the thyroid to produce T3/T4 hormones (metabolism regulators) and tells the reproductive system that energy stores are sufficient for normal function — which is why very low body fat can stop menstrual cycles.
Think of it like a thermostat. Your body has a “set point” weight it defends. When your weight drops below that set point, leptin falls, hunger rises, and your metabolism slows to pull you back up. When weight climbs above the set point, leptin rises to push it back down. The problem — and the reason leptin hormone weight loss drugs are needed — is that in obesity, the thermostat is broken. Leptin is sky-high, but the brain cannot hear it.
Research Spotlight: The 1994 Discovery That Started It All
In December 1994, Jeffrey Friedman and his team at Rockefeller University published a paper in Nature that would reshape obesity science forever. They identified the ob gene in mice — a gene that, when mutated, produced massively obese animals. The ob gene coded for a hormone nobody had seen before. Friedman named it leptin, from the Greek word leptos, meaning “thin.”
When Friedman’s team injected synthetic leptin into ob/ob mice — animals genetically unable to produce the hormone — the results were stunning. The mice lost 30% of their body weight in two weeks. They ate less, moved more, and their metabolism roared back to life. The photos from that study, showing a plump mouse next to its lean, leptin-treated sibling, made front pages worldwide. Amgen licensed the discovery for $20 million. A cure for obesity seemed imminent.
It was not. But the discovery laid the foundation for every leptin hormone weight loss drug in development today. Read the original 1994 Nature paper.
Why Did Early Leptin Hormone Weight Loss Drugs Fail?
The early leptin hormone weight loss drugs failed for a reason that seems obvious in hindsight but blindsided researchers in the late 1990s. The ob/ob mice lacked leptin entirely. Their obesity was a deficiency disease — like scurvy or rickets — and replacing the missing hormone fixed the problem. Human obesity turned out to be almost the exact opposite.
When researchers measured leptin levels in people with obesity, they found something unexpected: leptin was not low. It was extremely high. The more body fat a person carried, the more leptin circulated in their bloodstream. Their brains were drowning in the hormone — and ignoring it completely. Scientists named this phenomenon leptin resistance.
Fewer than 10% of people with obesity have a genuine leptin deficiency. The other 90%+ produce plenty of leptin — their brains simply refuse to respond to it. Injecting more leptin into a leptin-resistant person is like shouting into a megaphone at someone wearing noise-cancelling headphones. The signal is there. The receiver is not listening.
This explains why Amgen’s clinical trials of recombinant leptin in the late 1990s produced such disappointing results. Some participants lost a few pounds. Many lost nothing. The spectacular weight loss seen in mice did not translate. By the early 2000s, the pharmaceutical industry had largely walked away from leptin hormone weight loss drugs. The hormone was written off as a dead end.
One exception survived. In 2014, the FDA approved metreleptin (brand name Myalept) for a condition called generalized lipodystrophy — a rare disorder where patients are born with almost no fat tissue and therefore cannot produce leptin. For these patients — roughly 1 in 10 million for the congenital form, and up to 1 in 10,000 for all forms combined — metreleptin is life-changing. It restores normal appetite, reverses insulin resistance, and reduces liver fat. Learn more about lipodystrophy prevalence. But for the other 99.99% of people struggling with weight, metreleptin offered nothing.
That was the state of leptin hormone weight loss drugs for nearly two decades: one approved drug for an ultra-rare disease, and a graveyard of failed obesity trials. Nobody was paying attention when the comeback started.
The 2026 Comeback: Leptin Hormone Weight Loss Drugs as GLP-1 Partners

GLP-1 receptor agonists — semaglutide (Wegovy/Ozempic), tirzepatide (Mounjaro/Zepbound) — changed everything. They produced weight loss results that no previous drug class had achieved. By 2024, they had become household names. But as millions of people started taking them, two stubborn problems emerged: side effects and weight regain.
Roughly half of patients quit GLP-1 drugs within a year, according to a 2024 analysis published in PMC. The primary reason is gastrointestinal side effects — nausea, vomiting, diarrhea, and constipation that can be severe enough to disrupt daily life. The second problem is more subtle but equally damaging: when people stop taking GLP-1s, the weight comes back. Fast. And it comes back as fat, not muscle — leaving patients with a worse body composition than when they started.
This is where leptin hormone weight loss drugs re-enter the picture. Researchers realized that leptin and GLP-1 control appetite through completely different brain circuits. GLP-1 works primarily on the brainstem — the primitive part of your brain that controls nausea and food aversion. That is why GLP-1s make you feel full, but also why they make you feel sick. Leptin works on the hypothalamus — a higher brain region that regulates long-term energy balance without triggering the nausea reflex.
In 2024, a landmark study published in Science Translational Medicine tested exactly this hypothesis. Randy Seeley at the University of Michigan, collaborating with Novo Nordisk, gave mice a dual-activating compound that stimulated both leptin and GLP-1 receptors simultaneously. The results, published in July 2024, showed that the combination produced greater weight loss than either drug alone. More importantly, the leptin component appeared to offset two of the GLP-1’s biggest downsides.
First, muscle preservation. GLP-1 weight loss can include up to 30–40% lean tissue loss — muscle, bone density, organ tissue. Leptin, in contrast, signals the body to burn fat while sparing protein stores. In the dual-activation study, mice on the combination preserved significantly more lean mass than those on GLP-1 alone.
Second, the weight-regain trap. When you lose weight on a GLP-1 drug, your own leptin levels plummet — sometimes by 50% or more. This leptin crash tells your brain you are starving, even if you still have plenty of body fat. Hunger surges. Metabolism slows. The moment you stop the drug, your body fights to return to its old weight. By co-administering leptin hormone weight loss drugs with GLP-1s, researchers hope to keep the leptin signal strong during weight loss, preventing the metabolic counterattack that drives regain.
The logic is elegant: GLP-1s handle short-term meal-by-meal appetite control. Leptin handles long-term weight stability. Together, they cover both sides of the equation that has made sustainable weight loss so difficult. Randy Seeley summarized the approach to WebMD in April 2026: “GLP-1s manage the meal. Leptin manages the month.”
Leptin Hormone Weight Loss Drugs: What’s in the Pipeline?
The pipeline for leptin hormone weight loss drugs is more active than it has been at any point since the 1990s. Multiple approaches are being explored, each targeting a different part of the leptin signaling problem. Here is what is in development:
| Drug / Approach | Mechanism | Developer | Stage | Estimated Timeline |
|---|---|---|---|---|
| Metreleptin (Myalept) | Recombinant leptin replacement; restores absent leptin signal | Amylin / AstraZeneca | FDA-approved 2014 (lipodystrophy only) | Available now for rare disease; obesity trials ongoing (Phase II) |
| Dual leptin/GLP-1 co-agonists | Single molecule activating both receptors simultaneously | Novo Nordisk / University of Michigan | Preclinical (mouse studies) | Phase I trials possible within 2–3 years; market 5–7+ years |
| Leptin sensitizers (rapamycin-based) | Restore LEPR-B receptor sensitivity in hypothalamus; reverses leptin resistance at cellular level | Rockefeller University (Friedman lab) | Mouse proof-of-concept (2025) | Early preclinical; human translation uncertain; 7–10+ years |
| Anti-leptin monoclonal antibodies | Neutralize excess circulating leptin; paradoxically LOWERING leptin may restore sensitivity | UT Southwestern (Scherer lab) | Preclinical (mouse studies) | Concept stage; potential applications in diabetes and age-related disease; 8–12+ years |
The most immediately relevant of these for people struggling with weight today is the dual leptin/GLP-1 co-agonist approach, because it builds on the existing GLP-1 infrastructure rather than requiring entirely new drug classes. The rapamycin-based leptin sensitizers, discovered by Friedman’s lab at Rockefeller in 2025, represent a more fundamental solution — reversing the cellular mechanisms that cause leptin resistance in the first place. But this approach is furthest from the clinic.
Who Is This For?
Future leptin hormone weight loss drugs may be most relevant for:
- People who experienced severe GLP-1 side effects and quit treatment
- Anyone concerned about muscle loss during pharmaceutical weight loss
- Those who regained weight rapidly after stopping a GLP-1 agonist
- Individuals with diagnosed leptin deficiency or partial lipodystrophy (metreleptin is already approved)
- People exploring weight loss treatment options who want to understand what the next generation of therapy looks like
Important: None of the combination leptin hormone weight loss drugs discussed here are commercially available yet. This article describes the research pipeline — not products you can request today.
Safety & Side Effects of Leptin Hormone Weight Loss Drugs
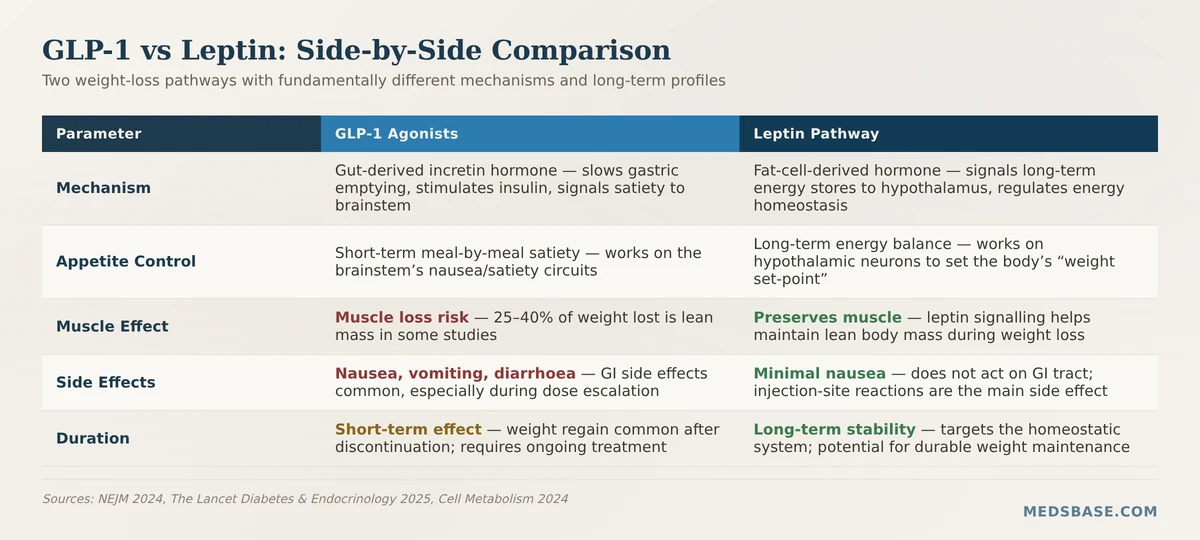
Safety is the question that hangs over every discussion of leptin hormone weight loss drugs. After all, we are talking about tinkering with one of the body’s most fundamental energy-regulation systems. The available data comes from metreleptin’s clinical experience (over a decade in lipodystrophy patients) plus preclinical studies of newer compounds. Here is how the side-effect profiles compare:
| Side Effect | GLP-1 Agonists (Semaglutide, Tirzepatide) | Leptin-Based Therapies (Metreleptin Data) |
|---|---|---|
| Nausea / Vomiting | Very common (20–45% of patients); primary reason for discontinuation | Rare to mild; leptin does not activate brainstem nausea centers |
| Muscle / Lean Tissue Loss | Significant (up to 30–40% of total weight lost) | Minimal; leptin signals preferentially burn fat, not protein |
| Weight Regain After Stopping | Rapid and near-universal; driven by leptin crash | Theoretically reduced (leptin maintains the “full” signal during weight loss) |
| Injection-Site Reactions | Mild, occasional | Moderate; more common with metreleptin (redness, swelling, bruising) |
| Hypoglycemia | Rare when used without insulin or sulfonylureas | Documented risk with metreleptin, especially in patients also taking insulin |
| Anti-Drug Antibodies | Rare; generally not clinically significant | Documented with metreleptin; can neutralize drug effect in some patients |
| Headache / Fatigue | Common (10–20% of patients) | Reported with metreleptin; generally mild and transient |
The side-effect comparison explains why researchers are excited about leptin hormone weight loss drugs as GLP-1 partners. Leptin’s primary safety concerns — injection-site reactions, antibody development, hypoglycemia risk in specific populations — are manageable. They do not include the nausea and vomiting that drive roughly half of GLP-1 patients to quit within a year.
What about long-term safety? This is the question nobody can fully answer yet. Metreleptin has been used in lipodystrophy patients for over a decade with a generally acceptable safety record. But lipodystrophy patients have a fundamentally different biology than people with common obesity — they lack leptin entirely. Long-term data on leptin-based therapies in leptin-resistant populations simply does not exist. The existing efficacy and safety data are promising but limited. Early studies indicate that the combination approach may carry fewer risks than either drug alone, but this conclusion requires confirmation in human trials.
If you are considering any pharmaceutical weight loss approach, you should discuss the full risk profile with a qualified healthcare provider. No leptin hormone weight loss drug — including metreleptin — should be used without medical supervision.
What Does the Research Say About Leptin Hormone Weight Loss Drugs?
The evidence base for leptin hormone weight loss drugs spans three decades and multiple research disciplines. The table below summarizes the key studies that built the case for today’s revival:
| Study / Publication | Year | Key Finding | Source |
|---|---|---|---|
| Friedman et al. — discovery of the ob gene and leptin | 1994 | Identified the hormone leptin; injection caused dramatic weight loss in leptin-deficient mice | Nature |
| Amgen clinical trials — recombinant leptin in human obesity | 1997–2002 | Disappointing results; identified leptin resistance as the barrier in common obesity | Multiple journals |
| FDA approval of metreleptin (Myalept) for lipodystrophy | 2014 | First regulatory approval of a leptin-based drug; limited to ultra-rare fat-tissue disorder | FDA |
| Oral et al. — metreleptin in fatty liver disease | 2018 | Modest reductions in liver fat with metreleptin treatment; established broader metabolic applications | Diabetes (ADA abstract) |
| Swiss study — leptin for anorexia nervosa | 2020 | Leptin treatment improved mood and reduced hyperactivity in anorexia patients; published in Nature Translational Psychiatry | Nature |
| Scherer et al. — anti-leptin monoclonal antibody | 2020 | Proposed paradoxical approach: lowering leptin levels may restore sensitivity and reduce obesity/diabetes risk | PubMed |
| Seeley / Novo Nordisk — dual leptin/GLP-1 co-agonism | 2024 | Dual activation produced greater weight loss than either drug alone in mice; preserved lean mass; published in Science Translational Medicine | Science Transl. Med. |
| GLP-1 discontinuation analysis | 2024 | ~50% of patients discontinue GLP-1 drugs within one year; published analysis in PMC | PMC |
| Friedman lab — cellular mechanism of leptin resistance + rapamycin reversal | 2025 | Discovered the cellular defect causing leptin resistance in hypothalamic neurons; rapamycin restored leptin sensitivity in mice | Rockefeller University |
The research arc tells a clear story. Early studies identified the hormone and its mechanism. Mid-period work explained why the simple replacement strategy failed. The most recent findings — particularly the dual-activation data from Seeley’s lab and the cellular mechanism discovery from Friedman’s group — provide the scientific rationale for leptin hormone weight loss drugs as a multi-pathway obesity treatment rather than a standalone solution.
According to the World Health Organization, global obesity rates have nearly tripled since 1975, with over 650 million adults now classified as obese. The NIH has documented the leptin signaling pathway in extensive detail, establishing that disruptions at multiple points — receptor expression, blood-brain barrier transport, intracellular JAK-STAT signaling — can all contribute to leptin resistance. This complexity explains why no single approach to leptin hormone weight loss drugs is likely to work for everyone. Different patients may need different interventions depending on where their leptin signaling breaks down.
How to Support Healthy Leptin Levels Naturally

While the pharmaceutical pipeline for leptin hormone weight loss drugs matures, there is plenty you can do right now to support healthy leptin function. These strategies target the lifestyle factors that research suggests contribute to leptin resistance:
1. Prioritize sleep — seriously. Sleep deprivation reduces leptin levels by 15–20% while simultaneously increasing ghrelin, your hunger hormone. One bad night of sleep measurably shifts your appetite hormones in the wrong direction. Aim for 7–9 hours of consistent, quality sleep. Research suggests that even partial sleep restriction over several nights can produce leptin changes similar to those seen in leptin resistance.
2. Cut back on processed foods — especially fructose. High-fructose corn syrup and other refined carbohydrates appear to promote leptin resistance through multiple mechanisms, including inflammation in the hypothalamus and impaired leptin transport across the blood-brain barrier. Whole foods — vegetables, lean proteins, legumes, whole grains — do not trigger the same inflammatory cascade. If you make one dietary change for leptin health, reducing processed food intake is the research-backed starting point.
3. Exercise — and make some of it high-intensity. Exercise improves leptin sensitivity through several pathways: it reduces inflammation, improves insulin sensitivity (which is tightly linked to leptin signaling), and directly affects hypothalamic function. High-intensity interval training may be particularly effective because it triggers greater metabolic adaptations than steady-state cardio. Aim for a mix of resistance training and cardio, with at least two high-intensity sessions per week.
4. Eat enough protein at breakfast. A high-protein breakfast reduces post-meal ghrelin levels and helps stabilize blood sugar throughout the day. This matters for leptin because glucose spikes and crashes contribute to the inflammatory environment that impairs leptin signaling. Research suggests that 25–30 grams of protein at breakfast produces the strongest satiety signal. Eggs, Greek yogurt, protein smoothies, or lean meats all work.
5. Avoid crash diets and extreme calorie restriction. When you slash calories too aggressively, your leptin levels can drop by 30–50% within days — even before you lose significant weight. This leptin crash triggers the same starvation response that GLP-1 discontinuation causes: surging hunger, slowing metabolism, and strong urges to overeat. A moderate calorie deficit (300–500 calories per day below maintenance) produces more sustainable results without tanking your leptin levels.
These strategies do not replace leptin hormone weight loss drugs — they address a different part of the problem. Pharmaceutical interventions target the receptor-level breakdown. Lifestyle strategies target the upstream contributors to that breakdown. Used together (when drugs become available), they may produce stronger and more durable results than either approach alone. For now, if you are managing your weight through diet and exercise while exploring evidence-based weight loss options, supporting healthy leptin function is one of the most underrated tools in your arsenal.
Frequently Asked Questions About Leptin Hormone Weight Loss Drugs
What exactly are leptin hormone weight loss drugs?
Leptin hormone weight loss drugs are medications that target the body’s leptin signaling pathway — the system fat cells use to communicate energy stores to the brain. They include leptin replacement therapies (like metreleptin), dual leptin/GLP-1 receptor activators, leptin sensitizers that restore receptor function, and anti-leptin antibodies designed to lower excess circulating leptin. Most are in preclinical or early clinical development.
Why did the first leptin hormone weight loss drugs fail?
The first leptin hormone weight loss drugs — recombinant leptin injections developed by Amgen in the late 1990s — failed because researchers did not yet understand leptin resistance. Most people with obesity produce too much leptin, not too little. Their brains are resistant to leptin’s signal, so injecting more of the hormone did nothing. The drug worked only in the tiny minority of patients who have a genuine leptin deficiency.
Can I get leptin hormone weight loss drugs today?
Only one leptin hormone weight loss drug is currently FDA-approved: metreleptin (Myalept), and it is restricted to patients with generalized lipodystrophy — a rare condition affecting roughly 1 in 10 million people. For common obesity, no leptin-based therapy is commercially available. The combination drugs discussed in this article are in preclinical or early-phase testing and are likely 3–7 years from market availability.
How do leptin hormone weight loss drugs compare to GLP-1s?
Leptin hormone weight loss drugs and GLP-1 agonists work through different brain circuits. GLP-1s act on the brainstem to suppress short-term appetite (which also triggers nausea). Leptin acts on the hypothalamus to regulate long-term energy balance without the nausea reflex. The key advantages of leptin-based approaches: less nausea, better muscle preservation, and reduced weight regain after stopping treatment. The key disadvantage: they are not yet available for common obesity.
Do leptin hormone weight loss drugs cause fewer side effects than semaglutide?
Based on metreleptin’s clinical experience in lipodystrophy patients, leptin hormone weight loss drugs appear to cause significantly less nausea and vomiting than GLP-1 agonists. However, they carry their own side-effect profile — injection-site reactions, possible hypoglycemia in certain patients, and the development of neutralizing antibodies in some cases. The side-effect comparison is promising but based on limited data from a different patient population.
Will leptin hormone weight loss drugs help me keep the weight off?
One of the primary rationales for developing leptin hormone weight loss drugs is weight-loss maintenance. When you lose weight, your own leptin levels drop, signaling your brain to increase hunger and slow metabolism. By providing exogenous leptin during weight loss, researchers hope to prevent this metabolic counterattack that drives regain after GLP-1 discontinuation. Early studies in mice support this mechanism, but human data is not yet available.
Can I boost my leptin levels naturally instead of taking drugs?
For most people, the issue is not low leptin — it is leptin resistance. You likely produce plenty of leptin already. Natural strategies focus on improving leptin sensitivity rather than raising leptin levels: prioritize sleep, reduce processed food intake, exercise regularly (including high-intensity sessions), eat adequate protein, and avoid extreme calorie restriction. These approaches complement leptin hormone weight loss drugs but do not replace them for people with severe receptor-level dysfunction.
Are leptin hormone weight loss drugs safe for long-term use?
The long-term safety of leptin hormone weight loss drugs in the general obesity population is unknown. Metreleptin has over a decade of safety data in lipodystrophy patients, but this population has fundamentally different biology. The dual leptin/GLP-1 co-agonists and leptin sensitizers currently in preclinical testing have no long-term human safety data. This is not a reason to dismiss the approach — it is a reason to insist on rigorous clinical trials before widespread adoption.
The Bottom Line on Leptin Hormone Weight Loss Drugs
The story of leptin hormone weight loss drugs is, above all, a story about persistence. A hormone discovered in 1994, hyped as a cure, dismissed as a failure, and resurrected three decades later because scientists refused to stop asking why it worked in mice but not in humans. The answer — leptin resistance — took twenty years to fully map. The solution — combination therapy that pairs leptin’s long-term energy regulation with GLP-1’s short-term appetite control — is only now entering the research pipeline.
Here is what you should take away: leptin hormone weight loss drugs are not a replacement for GLP-1s. They are a refinement — a way to make existing obesity treatments more effective, more tolerable, and more durable. The muscle-preserving effect alone could be significant, given how much lean tissue loss contributes to the “Ozempic face” appearance and long-term metabolic slowing. The nausea reduction could keep more people on treatment long enough to achieve meaningful results. The weight-regain prevention could address the single biggest weakness of current GLP-1 therapy.
The timeline is the honest caveat. Most of the leptin hormone weight loss drugs in the pipeline are years from pharmacy shelves. The dual leptin/GLP-1 co-agonists are the closest to human trials. The rapamycin-based leptin sensitizers and anti-leptin antibodies are further behind. If you are waiting for a leptin-based treatment before starting any weight loss medication, you may be waiting a long time.
What you can do today: If you are currently taking a GLP-1 agonist or considering one, talk to your doctor about strategies to preserve muscle mass during treatment — adequate protein intake, resistance training, and monitoring body composition rather than just scale weight. If you are looking for weight loss treatments you can start right now, review the evidence-based options available today and choose one that matches your health profile and tolerance for side effects.
What to read next:
- Leptin Resistance: Why Your Brain Ignores the “Full” Signal — Go deeper into the cellular mechanisms behind leptin resistance and the latest research on reversing it.
- Semaglutide vs Tirzepatide: Which Weight Loss Drug Is Right for You? — A head-to-head comparison of the two leading GLP-1 agonists, including efficacy data, side-effect profiles, and practical considerations.
Last updated: September 17, 2026
Reviewed by: [Medical Professional Title]
Medical Disclaimer
The information provided in this article is for educational and informational purposes only and does not constitute medical advice. It should not be used to diagnose, treat, prevent, or cure any disease or condition. Always consult a qualified healthcare professional before starting, stopping, or changing any medication or treatment plan. The drugs and therapies discussed in this article are in various stages of research and development; most are not currently approved for the treatment of common obesity. MedsBase does not prescribe medications or provide medical consultations. Any decision to use pharmaceutical weight loss treatments should be made in partnership with a licensed healthcare provider who understands your individual medical history.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.