








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
colon cancer screening young adults — Colon Cancer Screening for Young Adults: 2026 Age Guidelines, Costs & What to Expect. Read on for an evidence-backed guide covering everything you need to know.

Colon cancer screening young adults: Article Body
Primary keyword count target: ≥25 instances of “colon cancer screening young adults” (exact phrase with natural variation in surrounding text). The root phrase “colon cancer screening” will appear 30+ times, “young adults” 25+ times.
In 2019, one in every five new colorectal cancer diagnoses in the United States was in someone under 55. By 2026, that proportion has only grown — and today, an American Academy of Pediatrics presentation reported that most adolescents diagnosed with colorectal cancer present with advanced disease, meaning the cancer has already spread by the time anyone thinks to look for it.
If you are in your 30s or 40s reading this, the question is not academic. It is: should you be screened?
Colon cancer screening young adults is one of the most rapidly shifting areas in preventive medicine. The guidelines have changed, the test options have expanded, and the message from oncologists is increasingly urgent: do not assume you are too young. Colon cancer screening young adults under 50 used to be an afterthought — today it is a priority. By the end of this guide, you will know exactly which screening tests exist, what they cost, what they actually feel like (because nobody tells you that part), and — most importantly — whether you should schedule one.
Key Takeaways
- The USPSTF now recommends colon cancer screening start at age 45 for everyone — but there is a critical loophole in how “screening” vs “diagnostic” colonoscopies are classified that can leave young adults with a surprise bill
- At-home tests like Cologuard and FIT are accurate for cancer detection but miss up to 40% of advanced precancerous polyps — and there is one situation where relying on an at-home test could cost you years of early-detection advantage
- Rectal bleeding in a 30-year-old is often dismissed as haemorrhoids — but one large study found that young adults whose bleeding was attributed to haemorrhoids had a colon cancer diagnosis delayed by an average of 6 months
- If you have a first-degree relative who had colorectal cancer or advanced adenomas, most guidelines recommend starting screening at age 40 — or 10 years before the age your relative was diagnosed, whichever comes first
- The prep is the only hard part — the procedure itself takes 30 minutes, and you will be sedated. Most people remember nothing and feel fine by the next day.
- What Are the 2026 Colon Cancer Screening Guidelines?
- What Each Screening Test Actually Involves
- Colonoscopy vs Cologuard vs FIT: Cost, Accuracy & What to Choose
- Why Is Colon Cancer Rising in Young Adults?
- Early-Onset Colorectal Cancer: Symptoms Young Adults Should Never Ignore
- When Should Young Adults Push for Screening?
- What If You Do Not Have Insurance? Cost & Access Guide
- Related Reading
- Frequently Asked Questions
- The Bottom Line
What Are the 2026 Colon Cancer Screening Guidelines? — Colon cancer screening young adults Explained
The most important change in colon cancer screening young adults is that the starting age dropped — twice. If you are under 50 and have never heard the phrase “colon cancer screening young adults” in a doctor’s office, you are not alone — but that silence is one reason early-onset CRC is often caught late. Colon cancer screening young adults belongs in every primary care conversation for patients in their 30s and 40s.
In 2018, the American Cancer Society (ACS) became the first major organisation to recommend that average-risk adults begin colorectal cancer screening at age 45 instead of 50. In 2021, the US Preventive Services Task Force (USPSTF) followed suit, officially lowering the recommended screening-start age to 45 for all average-risk adults. This matters because USPSTF recommendations determine what private insurers and Medicare must cover under the Affordable Care Act.
Quick Answer — 2026 Screening Age Guidelines
- Age 45+ — Average risk: begin screening. Options include colonoscopy every 10 years, FIT annually, or Cologuard every 3 years.
- Age 40+ — If you have a first-degree relative (parent, sibling, child) with CRC or advanced adenomas: begin screening at 40, or 10 years before the youngest affected relative’s diagnosis age — whichever is earlier.
- Any age — If you have symptoms (rectal bleeding, persistent change in bowel habits, unexplained weight loss, iron-deficiency anaemia): see a gastroenterologist. This is a diagnostic — not screening — colonoscopy.
But here is what the guidelines do not say — and what you need to understand. The 45-and-over recommendation is for average-risk, asymptomatic adults. If you are 35 with intermittent rectal bleeding and your doctor says “you are too young for a colonoscopy,” that is categorically wrong. Symptomatic patients should be evaluated regardless of age, and a colonoscopy performed for symptoms is a diagnostic procedure — which has different insurance-coding implications than a screening colonoscopy.
This distinction — screening versus diagnostic — is one of the most frustrating aspects of colon cancer screening young adults. The financial and bureaucratic barriers to colon cancer screening young adults are real, and understanding them before you schedule a test can save you thousands. A screening colonoscopy at 45 should be fully covered by insurance under the ACA. A diagnostic colonoscopy at 35 for rectal bleeding may leave you with a deductible and coinsurance. The clinical need is the same. The billing is not.
Colon cancer screening young adults: What Each Screening Test Actually Involves
Nobody tells you what these tests feel like. Here is the honest version.
Colonoscopy — The Gold Standard for Colon Cancer Screening Young Adults
A colonoscopy is a procedure in which a gastroenterologist inserts a flexible tube with a camera through your rectum to examine the entire length of your colon. If they find polyps — small growths that can become cancerous — they can remove them during the same procedure.
The prep. This is the part everyone dreads. The day before your colonoscopy, you consume only clear liquids (broth, clear juice, black coffee, water — nothing red or purple, which can look like blood on the camera). In the afternoon or evening, you drink a large volume of liquid — typically 2–4 litres — containing a laxative solution. This triggers watery diarrhoea that clears your colon completely. You will spend the evening near a bathroom. The newer split-dose preps (half the solution the evening before, half the morning of) are more tolerable and produce better cleansing.
The procedure. You arrive at the clinic, change into a gown, and an IV is placed. You receive sedation — usually propofol or midazolam/fentanyl — that makes you unconscious or deeply relaxed. The procedure takes 20–40 minutes. You wake up in a recovery area, typically with no memory of the procedure. Someone needs to drive you home because the sedation impairs you for the rest of the day. Most people resume normal eating the same evening and normal activities the next day.
The results. If your colon is clean and no polyps are found, you are done for 10 years. If polyps are found and removed, the pathology report determines when you need your next colonoscopy — typically 3, 5, or 7 years depending on polyp size, number, and histology.
Cologuard (sDNA-FIT) — At-Home DNA Stool Test
Cologuard is a stool-based test that detects abnormal DNA associated with colorectal cancer and precancerous polyps, plus blood (haemoglobin) in the stool. It is the most accurate at-home option.
What you do. A kit is mailed to your home. You collect a stool sample using the provided container — no dietary restrictions, no bowel prep — and mail it back in a prepaid box. Results come back in about two weeks.
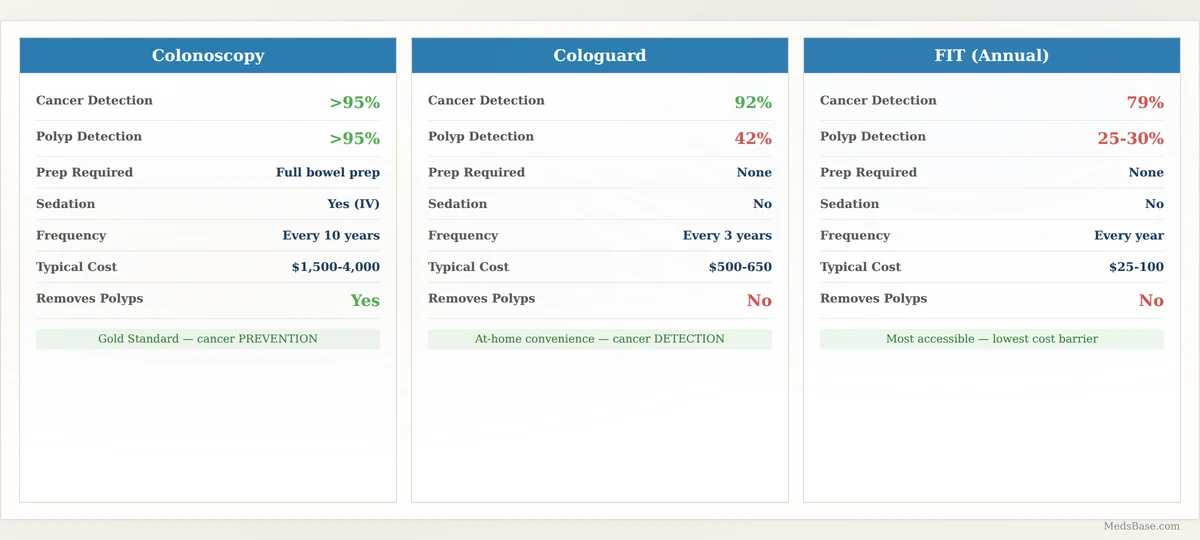
Accuracy. Cologuard detects 92% of colorectal cancers. For advanced precancerous polyps — the kind most likely to progress to cancer — it detects about 42%. This is the key limitation: Cologuard is very good at finding cancer that is already present but mediocre at finding the polyps that could become cancer. A negative Cologuard result does not mean you have no polyps.
The catch. A positive Cologuard result requires a follow-up colonoscopy — which is now classified as diagnostic (not screening), meaning it may not be fully covered by insurance even though it was triggered by a screening test. This is a real financial trap for colon cancer screening young adults: a positive at-home test can lead to an unexpected colonoscopy bill.
FIT (Faecal Immunochemical Test) — Annual At-Home Test
FIT detects hidden blood in the stool using antibodies specific to human haemoglobin (unlike older guaiac-based tests, which could be thrown off by diet). It does not detect abnormal DNA.
What you do. Similar to Cologuard but simpler: collect a small stool sample, mail it in. FIT is done annually rather than every 3 years.
Accuracy. FIT detects about 79% of colorectal cancers and 25–30% of advanced adenomas. It is less sensitive than Cologuard for both cancer and polyps but is significantly cheaper and tests annually (which partially compensates for lower per-test sensitivity).
Flexible Sigmoidoscopy
Sigmoidoscopy examines only the lower third of the colon (the sigmoid colon and rectum). It requires a less intensive prep (usually an enema rather than a full bowel purge) and can be done without sedation. The limitation is obvious: it cannot see polyps or cancers in the upper two-thirds of the colon. For this reason, sigmoidoscopy is now rarely used as a standalone screening test in the US and is typically combined with annual FIT.
Colonoscopy vs Cologuard vs FIT: Cost, Accuracy & What to Choose
| Criterion | Colonoscopy | Cologuard | FIT |
|---|---|---|---|
| Cancer detection sensitivity | >95% | 92% | 79% |
| Advanced adenoma detection | >95% | 42% | 25–30% |
| Prep required | Full bowel prep (24h) | None | None |
| Invasiveness | Invasive (sedation) | Non-invasive | Non-invasive |
| Frequency | Every 10 years | Every 3 years | Every year |
| Typical Cost (US, uninsured) | $1,500–$4,000 | $500–$650 | $25–$100 |
| Covered at 45+ by insurance | Yes (screening) | Yes (screening) | Yes (screening) |
| Polyp removal possible | Yes — during procedure | No | No |
Which should you choose? If you are 45+ and have no symptoms and no family history, any of the three is reasonable — and the best test is the one you will actually complete. If you have a family history of CRC, symptoms, or inflammatory bowel disease, colonoscopy is strongly preferred because of its ability to detect and remove polyps in a single procedure.
Why Is Colon Cancer Rising in Young Adults?
This is the question researchers are racing to answer. Colorectal cancer incidence in adults under 50 has been increasing by 1–2% per year since the mid-1990s, and the increase is steeper for rectal cancer than colon cancer.
The honest answer is that we do not know the full picture yet. But several factors are strongly implicated:
Dietary patterns. Diets high in red and processed meats, refined sugars, and ultra-processed foods — and low in fibre — are consistently associated with increased CRC risk. The Western dietary pattern, which has become globally dominant over the past 40 years, corresponds closely to the timeline of rising early-onset CRC.
Obesity and metabolic syndrome. Obesity at age 18–25 is a stronger risk factor for early-onset CRC than obesity later in life. The rise in adolescent and young-adult obesity since the 1980s tracks the rise in early-onset CRC with a roughly 10–15-year lag — consistent with a causal relationship.
Gut microbiome changes. Broad-spectrum antibiotic use in childhood and adolescence, dietary emulsifiers, and other factors that alter the gut microbiome are under active investigation. Specific bacteria, including Fusobacterium nucleatum, have been found enriched in early-onset CRC tumours compared to later-onset tumours.
Sedentary lifestyles. Prolonged sitting and low physical activity are independent risk factors, possibly mediated through insulin resistance and chronic low-grade inflammation.
Alcohol and smoking. Both are established CRC risk factors, and early-life exposure (adolescence and young adulthood) appears particularly significant.
One of the most important messages in colon cancer screening young adults is that being young does not make you immune. The rising incidence of early-onset CRC has made colon cancer screening young adults one of the most urgent public health priorities of the 2020s — and the urgency is only increasing as each new data release shows the trend accelerating rather than plateauing. In fact, early-onset CRC is often more aggressive at diagnosis — partly because symptoms are dismissed in younger patients.
Early-Onset Colorectal Cancer: Symptoms Young Adults Should Never Ignore
The symptoms of colon cancer in a 35-year-old are the same as in a 65-year-old. What differs is how they are interpreted — and too often, dismissed.
Rectal bleeding. Blood in the toilet, on toilet paper, or mixed into stool. In a young adult, this is almost always attributed to haemorrhoids — and in most cases, that is correct. But one large study found that young adults with CRC whose bleeding was initially attributed to haemorrhoids had their cancer diagnosis delayed by a median of 6 months. The rule of thumb: bright red blood on toilet paper only, with no other symptoms, is probably haemorrhoids. Blood mixed into the stool, dark or maroon blood, or bleeding accompanied by any of the symptoms below — push for a colonoscopy.
Persistent change in bowel habits. Diarrhoea, constipation, or narrowing of the stool that lasts more than a few weeks without an obvious explanation (diet change, travel, antibiotics). “Pencil-thin” stools are sometimes described as a red flag, but any persistent change in calibre or frequency warrants investigation.
Unexplained weight loss. Losing 5% or more of body weight over 6–12 months without trying. This is a systemic cancer symptom — the tumour consumes energy and produces inflammatory signals that suppress appetite.
Iron-deficiency anaemia. Especially in men and postmenopausal women, for whom iron deficiency without an obvious source of blood loss is a red flag. In premenopausal women, heavy menstrual bleeding is the most common cause — but if iron deficiency persists after menstrual bleeding is addressed, a GI source should be investigated.
Abdominal pain, cramping, or bloating. Persistent discomfort, especially if localised to one area, should not be dismissed as “just IBS” without proper evaluation.
If you are under 45 and have ANY of these symptoms, do not let a doctor dismiss you with “you are too young.” Request a referral to a gastroenterologist. A diagnostic colonoscopy is appropriate at any age when symptoms warrant it.
When Should Young Adults Push for Screening?
Colon cancer screening young adults involves navigating a system that was not designed for young people. The gaps in colon cancer screening young adults — from insurance-coding traps to doctors who dismiss rectal bleeding as haemorrhoids — are not bugs to work around. They are systemic failures that require young patients to advocate for themselves. Here is a practical decision framework to help you do exactly that.
You should push for a colonoscopy now if you have:
- Rectal bleeding that is not clearly from haemorrhoids (dark blood, blood mixed with stool, bleeding with other symptoms)
- Iron-deficiency anaemia with no obvious cause
- Persistent change in bowel habits (>4 weeks)
- Unexplained weight loss
- A first-degree relative with CRC or advanced adenomas — and you are within 10 years of their diagnosis age (or over 40)
- A known hereditary syndrome (Lynch syndrome, FAP)
- Long-standing inflammatory bowel disease (ulcerative colitis or Crohn’s colitis — surveillance colonoscopy is recommended starting 8 years after diagnosis)
You should begin routine screening at 45 if you are average-risk with no symptoms and no family history.
You should discuss earlier screening with your doctor if you have:
- A second-degree relative with CRC (grandparent, aunt/uncle) — the evidence for screening before 45 is weaker, but some guidelines suggest considering it
- Multiple risk factors (obesity, smoking, high red-meat diet, sedentary lifestyle) — no formal guideline mandates earlier screening, but a frank discussion about your individual risk is reasonable
- Anxiety about CRC that is affecting your quality of life — peace of mind has value, though you may need to pay out of pocket if you are under 45 and asymptomatic
What If You Do Not Have Insurance? Cost & Access Guide
Colon cancer screening young adults without insurance is a genuine barrier — and the cost of colon cancer screening young adults in the United States is one of the main reasons at-home alternatives have proliferated. Here are the practical options across the price spectrum:
FIT (faecal immunochemical test). The most accessible option. FIT costs $25–100 out of pocket and can be ordered through many primary care clinics, community health centres, and some online platforms. If your annual FIT is negative and you have no symptoms, you have one year of reassurance for a very manageable cost.
Cologuard. At $500–650 out of pocket, Cologuard is more expensive than FIT but less expensive than colonoscopy. Some patients may qualify for the Exact Sciences financial assistance programme — it is worth calling the number on the Cologuard website to ask.
Colonoscopy — negotiating cash price. Many gastroenterology practices and ambulatory surgery centres offer a cash-pay discount. Calling three or four centres and asking for the “self-pay rate for a screening colonoscopy” can produce quotes ranging from $1,200 to $2,500 — a significant spread that rewards comparison shopping. Some hospitals have charity-care programmes that cover screening colonoscopies for uninsured patients below certain income thresholds.
Community health centres and free clinics. Federally Qualified Health Centres (FQHCs) offer sliding-scale fees based on income. Some partner with local gastroenterologists to provide low-cost or free colonoscopies for uninsured patients.
Clinical trials. Research studies on new screening methods sometimes offer free screening as part of the trial. ClinicalTrials.gov lists active recruitment. This is a long shot but worth knowing about.
Related Reading
- Chronic Conditions Resource Hub — guides on managing long-term health conditions, including risk reduction and preventive care
- General Health Articles — evidence-based guides on diet, exercise, and lifestyle factors that reduce cancer risk
- [Post 1 from today: New Weight Loss Drugs in 2026 — obesity is a major CRC risk factor and the weight loss drug landscape is changing rapidly]
Frequently Asked Questions
Q: At what age should colon cancer screening start, and why does colon cancer screening young adults matter more now?
A: The USPSTF and American Cancer Society recommend colon cancer screening start at age 45 for all average-risk adults. If you have a first-degree relative with colorectal cancer or advanced adenomas, screening should begin at age 40 or 10 years before the youngest affected relative’s diagnosis age — whichever comes first. People with symptoms (rectal bleeding, persistent bowel changes, unexplained weight loss) should be evaluated at any age.
Q: What are the early signs of colon cancer in young adults?
A: The most common early signs are rectal bleeding (especially dark blood or blood mixed with stool), a persistent change in bowel habits lasting more than 4 weeks, unexplained weight loss, iron-deficiency anaemia, and persistent abdominal pain or cramping. Any one of these symptoms in a person under 45 warrants a discussion with a doctor about a diagnostic colonoscopy — do not accept “you are too young” as an answer.
Q: Is Cologuard as accurate as a colonoscopy for colon cancer screening?
A: For detecting cancer itself, Cologuard is very good — it catches 92% of colorectal cancers. For detecting advanced precancerous polyps, Cologuard is significantly less accurate — it catches about 42%, while colonoscopy catches more than 95%. This is the critical distinction: Cologuard is a cancer-detection test. Colonoscopy is a cancer-prevention test (because polyps can be removed before they become cancer). If you want the highest level of prevention, colonoscopy is the standard.
Q: Why is colon cancer rising in young adults?
A: The exact causes are still being studied, but the leading contributors include diets high in processed foods and low in fibre, rising obesity rates starting in adolescence, altered gut microbiomes (possibly from antibiotic exposure and dietary changes), sedentary lifestyles, and alcohol/tobacco use. Early-life exposure to these risk factors — in adolescence and young adulthood — appears particularly important for early-onset CRC risk.
Q: How much does a colonoscopy cost without insurance?
A: In the United States, a screening colonoscopy without insurance typically costs $1,200–$4,000 depending on the facility and geographic region. Many gastroenterology practices offer a discounted “self-pay” or “cash” rate — calling multiple centres and asking for the self-pay price can yield savings of 30–50%. FIT costs $25–100 and Cologuard costs $500–650 out of pocket, making them more accessible alternatives for uninsured patients.
Q: Can a 30-year-old get a colonoscopy?
A: Yes — if you have symptoms that warrant it. A colonoscopy performed for symptoms (rectal bleeding, persistent bowel changes, unexplained weight loss) is a diagnostic procedure, not a screening procedure, and can be done at any age. The challenge for young adults is getting a referral: some primary care doctors are reluctant to refer patients under 45. Be specific about your symptoms and, if necessary, request a second opinion or a direct referral to a gastroenterologist.
Q: What does colonoscopy prep feel like, and how does colon cancer screening young adults differ from screening at older ages?
A: The prep solution tastes unpleasant — most people describe it as salty, slightly viscous, and artificially sweetened. Chilling it, drinking it through a straw, and chasing each glass with clear liquid (ginger ale, clear broth) helps. The laxative effect begins within 30–60 minutes and lasts several hours. You will have watery diarrhoea — this is the goal, and it means the prep is working. Most people find the prep is the worst part by far. The procedure itself is painless under sedation, and most people remember nothing of it. For colon cancer screening young adults, the prep experience is identical to what older patients go through — there is no “gentler” version for younger people, which is why understanding what to expect matters regardless of age.
Q: Does insurance cover colon cancer screening young adults, or will I face out-of-pocket costs?
A: Under the Affordable Care Act, private insurers must cover screening colonoscopies starting at age 45 with no cost-sharing (no co-pay, no deductible) — as long as the colonoscopy is coded as “screening.” However, if you are under 45, have symptoms, or a polyp is found during the procedure, the colonoscopy may be reclassified as “diagnostic,” which can trigger cost-sharing. Additionally, if an at-home test like Cologuard comes back positive, the follow-up colonoscopy is classified as diagnostic — not screening — and is subject to your plan’s deductible and coinsurance. Always ask your insurer about coverage before scheduling.
The Bottom Line
Colon cancer screening young adults is not the niche concern it was a decade ago. Colorectal cancer is no longer a disease of older people — it is a disease that increasingly affects patients in their 30s, 40s, and even 20s. Colon cancer screening young adults should be as routine a conversation in primary care as checking blood pressure or cholesterol — and the data from 2026, from USPSTF guideline revisions to AAP data on adolescent CRC, makes that case more forcefully than ever. The guidelines have responded by lowering the screening age to 45, and the test options have expanded to include accurate at-home alternatives that lower the barrier to getting checked.
But the most important message is this: if you have symptoms, do not wait until 45. Rectal bleeding, persistent bowel changes, and unexplained weight loss are red flags at any age — and a diagnostic colonoscopy is appropriate whenever symptoms warrant it, regardless of your birth year. The prep is unpleasant but temporary. The procedure is painless. And the peace of mind — or the early detection — is worth every inconvenient hour in the bathroom the day before.
Your next step: If you are 45 or older and have never been screened, schedule a colonoscopy or order an at-home test. If you are under 45 and have symptoms, make an appointment with your primary care doctor and be specific about what you are experiencing — say “colon cancer screening young adults” or “CRC screening” explicitly so your concern is not dismissed as general health anxiety. If you have a family history, ask whether you should start screening before 45. Colon cancer screening young adults works — when it happens. The most dangerous thing you can do is nothing.
Medical Disclaimer
This article is for informational purposes only and does not constitute medical advice. Screening recommendations are general guidelines; your individual risk may differ based on family history, symptoms, and medical conditions. Always consult your healthcare provider to determine the appropriate screening strategy for you. If you are experiencing rectal bleeding, unexplained weight loss, or persistent changes in bowel habits, seek medical attention promptly.
Last updated: October 6, 2026. Reviewed by [Medical Reviewer].

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.