








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
increasing Ozempic dose vs switching to Mounjaro — Increasing Ozempic Dose vs Switching to Mounjaro: 7 Factors to Guide Your Decision. Read on for an evidence-backed guide covering everything you need to know.

Key Takeaways
- A new October 2026 analysis found that increasing the Ozempic dose was associated with a lower risk of major heart events compared with switching to Mounjaro — a finding that complicates the common instinct to switch drugs when weight loss plateaus.
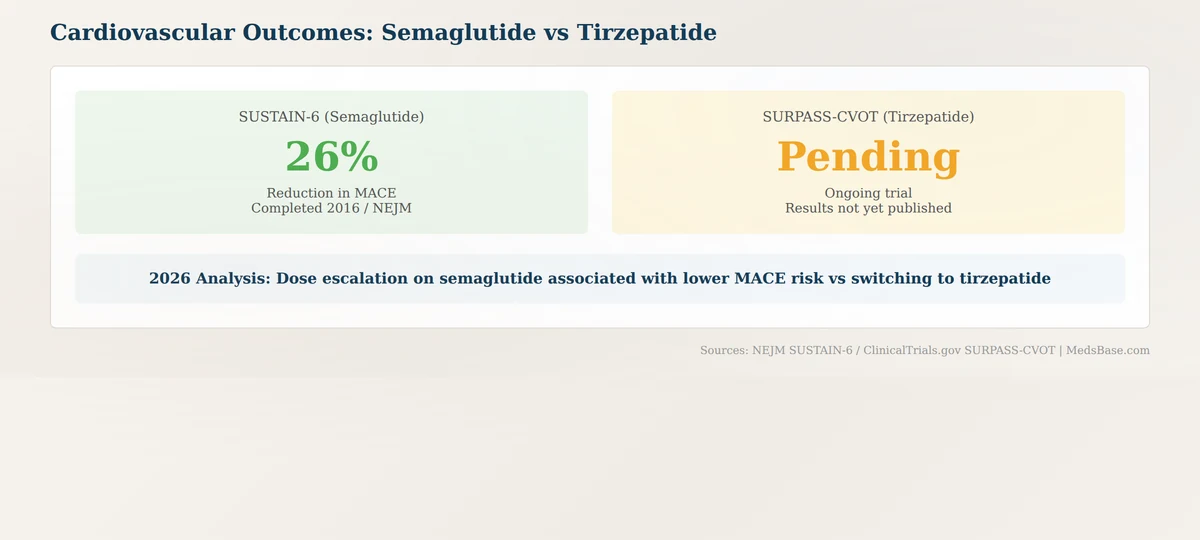
- Semaglutide (Ozempic) has established cardiovascular outcome data from the SUSTAIN-6 trial showing a 26% reduction in major adverse cardiovascular events. Tirzepatide (Mounjaro) has promising but less mature cardiovascular data — the SURPASS-CVOT trial results are pending.
- For weight loss alone, Mounjaro’s dual GLP-1/GIP mechanism typically produces greater total body-weight reduction (up to ~22% in trials) compared with semaglutide (up to ~15%).
- Switching from Ozempic to Mounjaro requires a washout or overlap protocol and dose titration from scratch — you will not maintain the same level of GLP-1 receptor activation during the transition.
- The decision is not one-size-fits-all: a person with established cardiovascular disease may benefit more from staying on semaglutide and escalating the dose, while a person whose primary treatment goal is maximum weight loss may benefit more from switching.
Increasing Ozempic dose vs switching to Mounjaro — you have been taking Ozempic for eight months. The first six were remarkable — 18 pounds down, HbA1c in the normal range for the first time in years, a relationship with food that finally felt manageable. But for the last two months, the scale has not moved. You are at 1.0 mg weekly. Your provider offers two paths: go up to the maximum 2.0 mg dose, or switch to Mounjaro, the newer dual-agonist that seems to be everywhere.
Increasing Ozempic dose vs switching to Mounjaro — which path protects your heart more? Which produces the most additional weight loss? Which one costs less — and which one will your body tolerate better?
Increasing Ozempic dose vs switching to Mounjaro — a new October 2026 analysis adds an unexpected twist to this decision. When researchers compared people who increased their Ozempic dose against those who switched to Mounjaro, the dose-escalation group had a lower risk of major heart events — a finding that shifts the risk-benefit calculus for anyone with cardiovascular concerns. By the end of this article, you will have a clear, evidence-based framework for the increasing Ozempic dose vs switching to Mounjaro decision — factor by factor, with the newest data on the table. The increasing Ozempic dose vs switching to Mounjaro question is now one of the most common clinical conversations in obesity medicine, and the evidence has shifted meaningfully in 2026.
Increasing Ozempic dose vs switching to Mounjaro: The Ozempic Plateau: Why It Happens and What It Means
Increasing Ozempic dose vs switching to Mounjaro — a weight-loss plateau on GLP-1 medications is so common that clinicians expect it. It is not a sign that the drug has stopped working — it is a sign that your body has reached a new energy-balance equilibrium at a lower body weight.
Quick Answer Box: A plateau on Ozempic means the drug’s appetite-suppression and delayed-gastric-emptying effects are still active, but your lower body mass now requires fewer calories to maintain — closing the gap between what you eat and what you burn. The plateau is a success signal (you have lost significant weight), not a failure signal — but it raises the practical question of whether to push further with the same drug or try a different mechanism entirely.
Increasing Ozempic dose vs switching to Mounjaro — when you weigh less, your basal metabolic rate (BMR) drops — a 200-pound person burns more calories at rest than a 170-pound person. Meanwhile, the GLP-1 effect on appetite is not infinitely scalable; at a given dose, it suppresses food intake by a fairly consistent percentage. The plateau happens when the calorie reduction from the GLP-1 matches your new, lower BMR. You are eating less than you used to, but not less than you now need to lose more weight.
The plateau decision — increasing Ozempic dose vs switching to Mounjaro — is one of the most common clinical conversations in obesity medicine in 2026. And the answer depends on more than just pounds. Patients facing the increasing Ozempic dose vs switching to Mounjaro decision often focus exclusively on weight loss, but the 2026 data demands a broader lens.
Increasing Ozempic dose vs switching to Mounjaro: How Do Ozempic and Mounjaro Differ?

Increasing Ozempic dose vs switching to Mounjaro — before weighing the evidence, you need to understand what separates these two medications at the receptor level — because the mechanism difference drives the clinical differences.
Increasing Ozempic dose vs switching to Mounjaro — ozempic (semaglutide) is a GLP-1 receptor agonist. It mimics one incretin hormone — glucagon-like peptide-1 — which signals the pancreas to release insulin, slows stomach emptying, and acts on brain appetite centres. It is a single-target drug with a well-characterised safety profile, established cardiovascular outcome data, and a 2.0 mg maximum weekly dose for diabetes (2.4 mg as Wegovy for weight loss).
Mounjaro (tirzepatide) is a dual GLP-1/GIP receptor agonist. It mimics two incretin hormones — GLP-1 plus glucose-dependent insulinotropic polypeptide (GIP). The GIP component adds additional insulin secretion, may enhance fat-tissue metabolism, and appears to amplify the weight-loss effect beyond what GLP-1 agonism alone can achieve. Mounjaro’s maximum weekly dose is 15 mg.
Here is where it gets interesting for anyone considering increasing Ozempic dose vs switching to Mounjaro. When weighing the increasing Ozempic dose vs switching to Mounjaro decision, the mechanistic difference is the starting point. The dual mechanism gives Mounjaro a weight-loss advantage — the Phase 3 SURMOUNT trials showed tirzepatide producing up to approximately 22% body-weight reduction at the highest dose, compared with semaglutide’s approximately 15% at its highest approved weight-loss dose. But that mechanistic complexity also means Mounjaro’s long-term safety database is younger, and its cardiovascular outcome data — while promising — is less mature than semaglutide’s. The FDA prescribing information for both drugs reflects this asymmetry: semaglutide has a decade of post-marketing surveillance; tirzepatide has about four years.
Increasing Ozempic dose vs switching to Mounjaro: What the Latest Evidence Says About Heart Outcomes
This is the finding that reshapes the conversation.
An October 2026 analysis — presented at a recent cardiometabolic conference and widely reported — found that increasing the Ozempic dose was associated with a lower risk of major heart events (heart attack, stroke, cardiovascular death) compared with switching to Mounjaro. The precise methodology and patient population have not yet been published in full, but the topline finding is clinically significant: for a patient whose primary concern is cardiovascular protection, dose escalation on semaglutide may be the safer path.
Why would this be? Semaglutide’s cardiovascular benefit is established by the SUSTAIN-6 trial, which demonstrated a 26% reduction in the composite outcome of cardiovascular death, non-fatal myocardial infarction, and non-fatal stroke compared with placebo. This data has been replicated and extended in subsequent analyses. The mechanism is not fully understood but likely involves improvements in blood pressure, lipids, inflammation, and direct vascular effects — all mediated through the GLP-1 receptor.
Tirzepatide’s cardiovascular outcome trial — SURPASS-CVOT — is ongoing, and while early signals are positive, the definitive data is not yet available. The 2026 analysis suggesting that switching from semaglutide to tirzepatide may temporarily reduce cardiovascular protection makes mechanistic sense: during the switch, there is a gap in sustained GLP-1 receptor activation while tirzepatide is titrated up from its starting dose.
Research Spotlight: The SUSTAIN-6 trial enrolled 3,297 patients with type 2 diabetes and established cardiovascular disease or high cardiovascular risk. Over a median follow-up of 2.1 years, semaglutide reduced the primary composite outcome by 26% (hazard ratio 0.74, 95% CI 0.58-0.95), as published in the New England Journal of Medicine. The benefit was driven primarily by a reduction in non-fatal stroke. This is the evidence base that underlies the new 2026 finding — and it is an evidence base that tirzepatide, for all its weight-loss advantages, has not yet matched with a completed cardiovascular outcomes trial.
What this means for you: If you have type 2 diabetes AND established cardiovascular disease (prior heart attack, stroke, coronary artery disease), the increasing Ozempic dose vs switching to Mounjaro decision tilts toward dose escalation based on the available evidence. For these patients, the increasing Ozempic dose vs switching to Mounjaro analysis is not just about pounds — it is about preventing the next cardiac event. If cardiovascular disease is not a concern — and your primary goal is maximum weight loss — the calculus changes.
Weight Loss Results: Dose Escalation vs Drug Switch
Cardiovascular protection aside, weight loss is what most people care about — and here, the data tells a more nuanced story than “Mounjaro wins.”
When you increase the Ozempic dose from 1.0 mg to 2.0 mg weekly, additional weight loss is typically modest — 2-4% of body weight in most studies. The drug is working through the same single receptor; you are simply saturating it more completely. For someone who has already lost 15% on 1.0 mg, the 2.0 mg dose might add another 3-5% — meaningful, but not transformative.
When you switch from Ozempic to Mounjaro, the potential for additional weight loss is larger because you are activating a second mechanism (GIP) that was previously untouched. The SURMOUNT-1 trial showed that treatment-naive patients on tirzepatide 15 mg lost approximately 22% of body weight — roughly 7 percentage points more than semaglutide 2.4 mg in a separate but comparable trial population. However, these numbers apply to treatment-naive patients starting from scratch, not to patients switching mid-treatment. There is no large, randomised trial comparing “Ozempic 2.0 mg dose escalation” head-to-head with “switch to Mounjaro” in patients who have plateaued. The Oct 2026 analysis is the closest we have, and it focused on heart outcomes, not weight.
A practical consideration: when you switch, you start tirzepatide at 2.5 mg and titrate up over weeks or months. During the early titration weeks, you may be receiving less total GLP-1 receptor activation than you were on semaglutide 1.0 mg. Appetite may increase temporarily. Some weight regain in the first month of switching is common before the tirzepatide effect kicks in at higher doses.
Head-to-Head Comparison
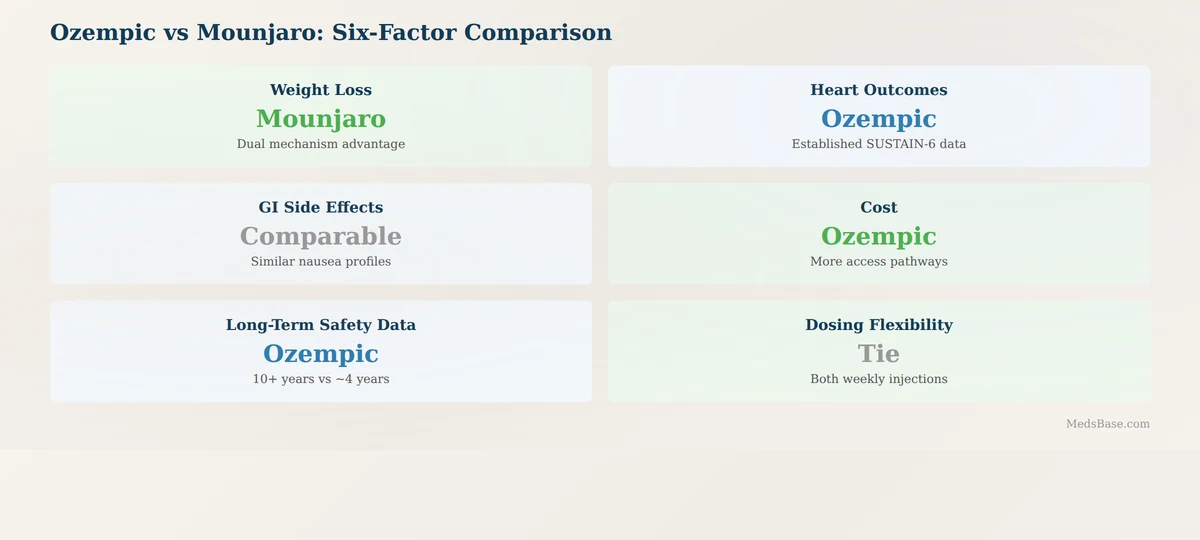
| Factor | Increase Ozempic Dose (to 2.0 mg) | Switch to Mounjaro (titrate to effective dose) |
|---|---|---|
| Mechanism | Single GLP-1 agonist — saturates existing receptor | Dual GLP-1/GIP agonist — adds second mechanism |
| Expected additional weight loss | 2-4% of body weight | Variable; potentially 5-10%+ based on SURMOUNT data (treatment-naive) |
| Cardiovascular protection | Established — SUSTAIN-6: 26% MACE reduction; Oct 2026 data favours dose escalation | Promising but pending SURPASS-CVOT results |
| Transition complexity | Simple — one injection, higher dose | Complex — washout/overlap + re-titration from 2.5 mg upward over weeks |
| Risk of temporary weight regain during transition | None | Yes — lower GLP-1 activation during early tirzepatide titration |
| GI side-effect risk | Dose-dependent increase in nausea (~24% at 2.0 mg) | Re-titration means re-exposure to initial side effects (~12-22% nausea depending on dose) |
| Long-term safety data | 10+ years post-marketing | ~4 years post-marketing |
| Approximate US list price (weekly) | ~$900-1,000 (brand) | ~$1,000-1,100 (brand) |
| Availability of lower-cost options | More generic/alternative pathways emerging | Fewer; newer drug with active patents |
Q: Which one fits which situation?
A: – Cardiovascular disease present Increase Ozempic dose. The SUSTAIN-6 data plus the Oct 2026 switching analysis create a strong cardiovascular-protection argument for staying on semaglutide. – Weight loss is the ONLY goal, and cardiovascular risk is low Switch to Mounjaro. The dual mechanism’s weight-loss advantage, particularly at higher doses, is the strongest argument for switching. – You cannot tolerate side effects at the current dose Switching may help, but does not guarantee better tolerability — you will re-titrate through the side-effect-prone dosing period. – Cost is the binding constraint Ozempic dose escalation is generally less expensive (lower per-dose cost at a given tier, more established access pathways).
Side Effects and Tolerability
Let us address the practical reality: the main reason people consider switching drugs is not always about efficacy — it is often about side effects.
When you increase the Ozempic dose from 1.0 mg to 2.0 mg, the side-effect profile is predictable: more of the same. If you had nausea at 1.0 mg, you will likely have more nausea at 2.0 mg, at least initially. But because your body has already adapted to semaglutide at 1.0 mg, the step-up is typically easier to tolerate than starting from scratch. Most people find that the increased side effects from a dose escalation stabilise within 2-4 weeks.
When you switch to Mounjaro, you are starting over — from the side-effect perspective. The tirzepatide titration schedule begins at 2.5 mg for 4 weeks, then 5 mg for 4 weeks, and so on. Each dose increase brings a new wave of potential nausea, diarrhea, and appetite suppression. For someone who struggled with semaglutide side effects, the re-titration process can be challenging — and there is no guarantee that tirzepatide will ultimately be better tolerated. The NHS guidance on GLP-1 receptor agonists recommends against switching primarily for side-effect reasons unless those side effects are treatment-limiting at the lowest effective dose.
What to expect with either choice:
- Dose escalation: nausea increases for 2-4 weeks, then adapts. Constipation and reflux may also worsen. Rarely, dose escalation unmasks gallbladder issues — if you have a history of gallstones, discuss this with your provider.
- Drug switch: re-exposure to initial side effects during the tirzepatide titration; symptoms typically peak around weeks 2-4 of each dose step; by the time you reach 10-15 mg, most people have adapted. The dual mechanism means a slightly different side-effect profile — some patients report less nausea on tirzepatide than semaglutide, while others report the opposite.
There is no universal answer here. If you tolerated semaglutide well but simply plateaued, dose escalation is the smoother path. If semaglutide side effects are treatment-limiting, switching may be worth the re-titration discomfort — but manage expectations about tolerability.
Cost and Access Considerations
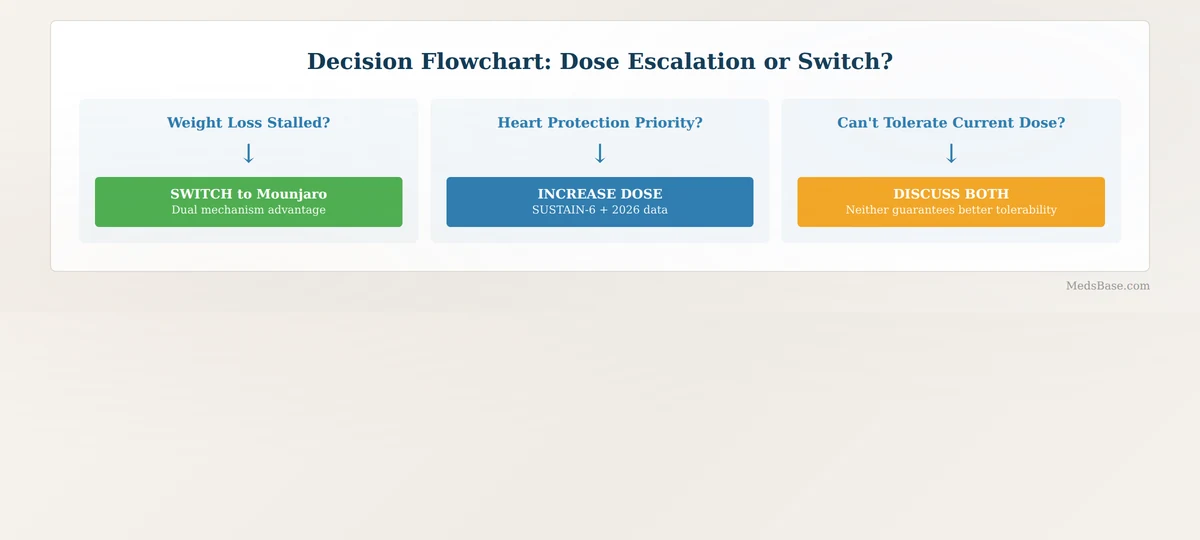
The practical economics of the increasing Ozempic dose vs switching to Mounjaro decision cannot be ignored. For many patients, the increasing Ozempic dose vs switching to Mounjaro question is ultimately settled by what their insurance covers or what they can afford out of pocket.
Ozempic (semaglutide) has been on the market since 2017. Its patent exclusivity is beginning to face challenges, and competition from alternative GLP-1 products — including oral formulations, compounded options, and international pharmacy access — has created more price flexibility. Mounjaro (tirzepatide) received FDA approval in 2022 and enjoys stronger patent protection. Its list price is slightly higher, and fewer discount programmes and access pathways currently exist.
If you are paying out of pocket, the cost difference — approximately $100-200 per month — may tip the decision toward dose escalation, particularly when combined with the cardiovascular-protection argument.
Contextual product mention: If you and your provider decide that increasing the Ozempic dose is the right path, MedsBase offers a range of semaglutide products in multiple strengths. Browse the Weight Loss category to see currently available options and strengths — including alternatives if brand-name pricing is a barrier.
How to Decide: A Provider Discussion Guide
Here is a structured framework for discussing the increasing Ozempic dose vs switching to Mounjaro decision with your healthcare provider. The best increasing Ozempic dose vs switching to Mounjaro conversations happen when the patient arrives prepared with data — not just frustration.
Step 1: Identify your primary treatment goal. Is it cardiovascular protection? Maximum weight loss? Side-effect management? Cost control? Rank them. This ranking — not the general “which drug is better” question — drives the decision.
Step 2: Review your cardiovascular risk. Do you have established cardiovascular disease (prior MI, stroke, revascularisation)? Are you diabetic with multiple risk factors? If yes, the SUSTAIN-6 data and the Oct 2026 switching analysis suggest that staying on semaglutide and escalating the dose preserves a known cardiovascular benefit. Ask your provider: “Given my cardiac history, does the 2026 data on dose escalation vs switching change your recommendation?”
Step 3: Assess your weight-loss trajectory. How much additional weight do you want to lose? If the answer is “10-15 more pounds,” dose escalation may get you there. If the answer is “30+ more pounds,” and you have plateaued significantly, the dual mechanism of tirzepatide may provide the additional leverage. Ask your provider: “Based on my current plateau and my goal weight, would dose escalation or a switch be more likely to move the needle?”
Step 4: Calculate your tolerance for a transition period. A dose escalation takes effect the same week — you inject the higher dose and that is it. A drug switch involves weeks of re-titration, potential temporary weight regain, and re-exposure to initial side effects. If you have an important event, trip, or cannot afford a few weeks of uncertainty, dose escalation is the logistically simpler path.
Step 5: Discuss cost. Bring your insurance formulary or out-of-pocket pricing. Your provider may not know the cash price of either medication. Knowing the numbers before the conversation ensures that the decision you make together is one you can actually sustain.
Step 6: Make the decision and set a checkpoint. Whichever path you choose, agree on a reassessment timeline — typically 12 weeks. If you escalate to Ozempic 2.0 mg and after 12 weeks the scale has not moved and side effects are tolerable, you have your answer: the escalation worked or it did not, and you can revisit the switch option with data, not speculation.
Second contextual product mention: MedsBase’s Weight Loss and Comparisons categories can help you evaluate the formulations and strengths available for both semaglutide and tirzepatide-based options. Browse the collection to see what is currently in stock, and bring the information to your provider conversation.
Related Reading
- Wegovy vs Mounjaro for Weight Loss: A Comprehensive Comparison — The broader comparison between the two leading GLP-1 weight-loss medications
- Switching from GLP-1 Injections to Pills for Weight Loss — Today’s Post 1: what if pills are the answer instead of a different injection?
- Type 2 Diabetes Remission with Diet and Exercise — Today’s Post 2: the non-medication path that is achieving remission in clinical trials
Frequently Asked Questions
Q: Is it better to increase Ozempic dose or switch to Mounjaro?
A: It depends on your primary goal. For cardiovascular protection, increasing the Ozempic dose is the evidence-backed choice — the Oct 2026 analysis found dose escalation was associated with lower major-heart-event risk than switching. For maximum weight loss, switching to Mounjaro may produce greater additional results due to its dual GLP-1/GIP mechanism. Discuss your specific risk profile and goals with your provider; the increasing Ozempic dose vs switching to Mounjaro decision is individual, not universal.
Q: What to do when Ozempic stops working?
A: A plateau is not a failure — it means your body has reached a new energy equilibrium at a lower weight. Options include: increasing the dose to 2.0 mg (if you are below the maximum), adding a second weight-loss medication (off-label combinations exist but require specialist supervision), intensifying lifestyle changes (the EASD 2026 data supports structured exercise combined with diet), or switching to a dual-agonist like tirzepatide. The plateau is a fork in the road, not a dead end.
Q: Does Mounjaro work better than Ozempic?
A: For weight loss, Mounjaro produces greater total body-weight reduction in treatment-naive patients — approximately 22% vs approximately 15% at maximum doses in separate trial populations. For cardiovascular protection, Ozempic has stronger, more mature evidence (SUSTAIN-6: 26% MACE reduction). “Better” depends on what outcome you are measuring — and for whom.
Q: Can you switch from Ozempic to Mounjaro?
A: Yes, and it is commonly done in clinical practice. The standard protocol: take your last Ozempic dose, wait one week (the normal dosing interval), then begin tirzepatide at the starting dose of 2.5 mg the following week. Titrate upward every 4 weeks per the standard schedule (2.5 5 7.5 10 12.5 15 mg). Expect a transient reduction in GLP-1 receptor activation during the early titration weeks, which may cause temporary appetite increase or slight weight regain.
Q: What is the maximum dose of Ozempic?
A: The FDA-approved maximum dose of Ozempic (semaglutide) for type 2 diabetes is 2.0 mg once weekly. For weight loss, the Wegovy brand of semaglutide is approved up to 2.4 mg once weekly. Doses above these are not FDA-approved and are considered off-label. Your provider should not exceed the approved maximum without a specific clinical rationale and close monitoring.
Q: Does semaglutide protect your heart more than tirzepatide?
A: Semaglutide has completed cardiovascular outcomes trials (SUSTAIN-6) showing a 26% reduction in major adverse cardiovascular events. Tirzepatide’s cardiovascular outcomes trial (SURPASS-CVOT) is ongoing; topline data suggests benefit, but the definitive, peer-reviewed results are not yet available. Based on current evidence, semaglutide’s cardiovascular protection is better established — and the Oct 2026 analysis suggests that staying on semaglutide (dose escalation) may preserve that protection compared with switching.
Q: How long does it take to see results after increasing Ozempic dose?
A: Increased appetite suppression is usually noticeable within 1-2 weeks of a dose increase. Weight loss typically resumes within 2-4 weeks, though the rate is often slower than during the initial treatment phase. Full effect at the new dose stabilises over 8-12 weeks. If you see no additional weight loss after 12 weeks at the higher dose, the plateau may be at the medication’s ceiling for you — and the switching conversation becomes more relevant.
Q: Is Mounjaro more expensive than Ozempic?
A: At US list prices, Mounjaro is generally $100-200 more per month than Ozempic at comparable dose tiers. Insurance coverage, manufacturer savings programmes, and pharmacy access (including international options) can significantly change out-of-pocket costs. Verify your specific cost before making the increasing Ozempic dose vs switching to Mounjaro decision based on finances alone. The financial dimension of the increasing Ozempic dose vs switching to Mounjaro choice should be discussed openly with your provider — they cannot help you weigh options they do not know you cannot afford.
The Bottom Line
The increasing Ozempic dose vs switching to Mounjaro decision — one of the most common clinical conversations in GLP-1 treatment — now has clearer data behind it. Where last year the increasing Ozempic dose vs switching to Mounjaro question was answered mostly by trial-and-error, 2026 brings evidence that can guide the discussion before the first prescription is written. The October 2026 finding that dose escalation preserves cardiovascular protection in a way that switching may not gives weight to the “stay the course” argument for patients with heart-disease risk. But for patients whose primary goal is maximum weight loss and who have low cardiovascular risk, Mounjaro’s dual mechanism offers a genuine advantage.
Verdict: There is no universal winner — and that is a good thing. It means the decision can be personalised to your specific health profile. The framework is simple: heart risk dose escalation; weight loss as the overriding goal consider switching; cost dose escalation; tolerability neither is a guaranteed fix, but switching offers a different side-effect profile worth trying if current side effects are treatment-limiting.
Your next step: Schedule a provider conversation. Bring this framework — primary goal, cardiovascular risk, weight-loss trajectory, transition tolerance, cost — and the Oct 2026 data. Decide together, set a 12-week checkpoint, and reassess with data.
What to read next:
- Curious about whether pills could solve your plateau instead of a different injection? Read today’s companion piece: Switching from GLP-1 Injections to Pills for Weight Loss
- Wondering if you should step away from medication entirely and pursue remission through lifestyle? Type 2 Diabetes Remission with Diet and Exercise — today’s other companion post — explores the evidence.
Medical Disclaimer: This article is for informational purposes only and does not constitute medical advice. Ozempic, Wegovy, Mounjaro, and Zepbound are prescription medications that must be prescribed and managed by a qualified healthcare provider. Never change your dose, switch medications, or discontinue treatment without consulting your doctor.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.