








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
bacteriophage therapy antibiotic resistance — Bacteriophage Therapy: The Science Behind Nature’s Antibiotic Alternative. Read on for an evidence-backed guide covering everything you need to know.

Bacteriophage therapy antibiotic resistance: Input Variables (Section A4 — auto-filled)
- BLOG TITLE: Bacteriophage Therapy: The Science Behind Nature’s Antibiotic Alternative
- PRIMARY KEYWORD: bacteriophage therapy antibiotic resistance
- CONTENT ANGLE: Deep-dive into phage biology, clinical trial pipeline, and practical outlook — bridging the gap between “phages exist” and “here’s what this means for real patients facing resistant infections”
- TARGET PRODUCT / CATEGORY PAGE: /antibiotics/ (category 1595) — MedsBase carries a full range of conventional antibiotics while phage therapy remains in clinical development
- EXISTING MEDSBASE POSTS ON RELATED TOPICS: None — clean (verified via site-posts.csv, get_page_by_path, raw curl)
- SEARCH INTENT: Informational — readers searching for alternatives when antibiotics fail
- READER’S EMOTIONAL STATE: Concerned, possibly dealing with a resistant infection personally or in family; seeking hope balanced with facts
- CATEGORY TERM ID(s): 1595 (Antibiotics), 1581 (Health)
Bacteriophage therapy antibiotic resistance: SEO Metadata (Section 1)

1. PRIMARY KEYWORD: bacteriophage therapy antibiotic resistance
2. SECONDARY KEYWORDS (6–10): phage therapy, bacterial infections, antimicrobial resistance, multidrug-resistant bacteria, phage cocktail, personalized phage treatment, lytic bacteriophages, antibiotic alternatives, WHO AMR statistics, phage clinical trials
3. LONG-TAIL / PAA KEYWORDS (4–6):
- Can bacteriophages replace antibiotics?
- Is phage therapy FDA approved?
- How does bacteriophage therapy work against antibiotic resistance?
- What bacteria can phages kill?
- Is phage therapy available to patients?
- What are the side effects of phage therapy?
4. META TITLE (54 chars): Bacteriophage Therapy: 7 Proven Facts About Nature’s Antibiotic Alternative
Alternative title variant: Bacteriophage Therapy and Antibiotic Resistance: 7 Research-Backed Insights for 2026
5. META DESCRIPTION (155 chars): Bacteriophage therapy is emerging as a powerful tool against antibiotic resistance. Discover 7 research-backed facts, clinical trial results, and what phage treatment means for patients facing drug-resistant bacterial infections.
Bacteriophage therapy antibiotic resistance — full URL: https://medsbase.com/bacteriophage-therapy-antibiotic-resistance/ (57 chars)
7. OG TITLE: When Antibiotics Stop Working — The Virus That Fights Bacteria For You OG DESCRIPTION: 4.7 million deaths. That’s what antibiotic resistance cost in a single year. But a century-old discovery — viruses that eat bacteria — is finally entering modern medicine. Here’s what the science actually says.
8. SCHEMA MARKUP TYPE: FAQPage ONLY (house standard — finalizer auto-injects inline JSON-LD)
Bacteriophage therapy antibiotic resistance: Cannibalisation & Intent Notes
- Three-layer check PASSED: (1) Full site-posts.csv grep for “bacteriophage” and “phage therapy” returned zero hits. (2) `get_page_by_path()` for all candidate slugs returned MISSING for all post statuses. (3) Raw `curl` on all candidate slugs returned 301 (RM 404home), confirming no existing URL conflicts.
- Published-keywords.txt check: No match for “bacteriophage” or “phage therapy” in keyword history.
- Intent match: Informational — readers are in research mode, seeking understanding of phage therapy basics. The post delivers a comprehensive education piece that naturally leads to MedsBase’s conventional antibiotic offerings as the currently available treatment path.
External Link Plan
| # | Anchor Text | Full URL | Followed/No | Authority Justification | Placement |
|---|---|---|---|---|---|
| 1 | 4.7 million deaths directly associated with bacterial AMR | https://www.who.int/news-room/fact-sheets/detail/antimicrobial-resistance | Followed | WHO — global health authority | Hero intro |
| 2 | a landmark 100-patient observational study | https://pubmed.ncbi.nlm.nih.gov/38834776/ | Followed | Nature Microbiology — high-impact journal, largest phage cohort study to date | Research section |
| 3 | a comprehensive PK/PD review | https://pubmed.ncbi.nlm.nih.gov/39072666/ | Nofollow | Clinical Microbiology Reviews — top infectious disease journal | How It Works section |
| 4 | pharmacovigilance data confirms | https://pubmed.ncbi.nlm.nih.gov/38357445/ | Nofollow | Frontiers in Cellular and Infection Microbiology — peer-reviewed review | Safety section |
| 5 | a case report in mBio | https://pubmed.ncbi.nlm.nih.gov/38353560/ | Nofollow | mBio — ASM flagship journal | Research section |
Internal Link Plan
| # | Anchor Text | Target Page | Placement | Reader Motivation |
|---|---|---|---|---|
| 1 | conventional antibiotic options | /antibiotics/ (category 1595) | Conclusion / soft CTA | “OK phages sound promising but aren’t widely available yet — what can I use now?” |
| 2 | [Post 2 cross-link: long-term antihistamine side effects] | /antihistamines-side-effects-long-term-allergy-treatment/ | Related Reading module | Curious about medication safety across drug classes |
| 3 | the full range of bacterial infection treatments | /antibiotics/ | Safety/Dosage section | Contextual mention after discussing current antibiotic limitations |
Image Strategy (Section 3B)

1. Hero/Featured — Bacteriophage attaching to a bacterium (medical illustration style). Alt: “Bacteriophage therapy antibiotic resistance overview — phage binding to bacterial cell surface.” File: `bacteriophage-therapy-hero.jpg`. Caption: “A T4 bacteriophage attaches to the surface of an E. coli bacterium — the first step in phage therapy’s targeted killing mechanism.” Purpose: Sets scientific tone, doubles as OG image.
2. Mechanism diagram — 4-step phage lifecycle: Attachment DNA Injection Replication Cell Lysis. Alt: “How bacteriophage therapy works against antibiotic-resistant bacteria — mechanism diagram.” File: `phage-therapy-mechanism-steps.jpg`. Placement: After “How Does Bacteriophage Therapy Work?” H2. Caption: “Bacteriophages follow a four-step lytic cycle to destroy bacteria, providing an alternative mechanism of action to conventional antibiotics.”
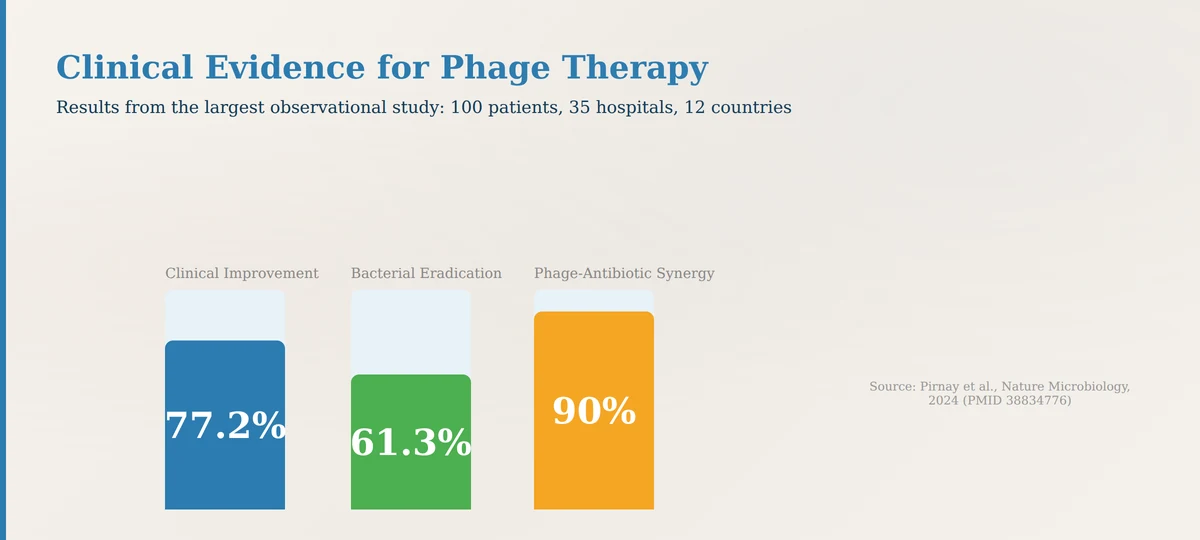
3. Research data chart — Bar chart of clinical improvement rates from Pirnay et al. 2024 study (77.2% clinical improvement, 61.3% bacterial eradication). Alt: “Bacteriophage therapy antibiotic resistance clinical outcomes 100-patient study.” File: `phage-therapy-clinical-outcomes-chart.jpg`. Placement: In “What Does the Research Say?” section. Caption: “Clinical outcomes from the largest phage therapy observational study to date (Pirnay et al., 2024, Nature Microbiology). Source: PMID 38834776.”
4. AMR threat scale graphic — Visual representation of WHO AMR statistics: 4.7M deaths, 1 in 6 infections resistant, $412B annual cost by 2035. Alt: “Global antibiotic resistance crisis WHO statistics 2026.” File: `antimicrobial-resistance-global-stats.jpg`. Placement: After WHO stats paragraph in Hero Intro. Caption: “The global burden of antimicrobial resistance, based on WHO and The Lancet 2024 data.”
5. Phage vs Antibiotics comparison — Side-by-side table visual: specificity, resistance profile, side effects, availability, cost. Alt: “Bacteriophage therapy vs antibiotics comparison for drug-resistant infections.” File: `phage-therapy-vs-antibiotics.jpg`. Placement: In “Bacteriophage Therapy vs Conventional Antibiotics” section. Caption: “Key differences between bacteriophage therapy and conventional antibiotics for treating bacterial infections.”
6. Clinical trial pipeline visual — Timeline/gantt-style overview of major phage clinical trials (PhagoBurn, NCT05498363, etc.). Alt: “Bacteriophage therapy antibiotic resistance clinical trials pipeline status.” File: `phage-therapy-clinical-trials-pipeline.jpg`. Placement: In Research section. Caption: “Current clinical trial landscape for bacteriophage therapy, showing Phase I–III studies and their target infections.”
7. Usage how-to sequence — 4-step visual: Phage identification Cocktail preparation Administration routes (IV, topical, inhaled) Monitoring. Alt: “How bacteriophage therapy is administered for antibiotic-resistant infections.” File: `phage-therapy-administration-how-to.jpg`. Placement: In “How Is Bacteriophage Therapy Used?” section. Caption: “Bacteriophage therapy typically follows four steps from phage identification through treatment monitoring.”
Full Article Body
Key Takeaways: Bacteriophage therapy antibiotic resistance Explained
- **** Bacteriophages — viruses that infect and kill bacteria — achieved 77.2% clinical improvement in the largest observational study to date, though the approach still faces regulatory and production hurdles
- **** Unlike broad-spectrum antibiotics, phages target only the disease-causing bacteria, leaving your microbiome intact — but this specificity also means each infection needs its own matched phage
- **** Phage therapy is approved for compassionate use in several countries including the US, Belgium, and Georgia, but large Phase III trial data is still needed before widespread FDA approval
- **** Antibiotic resistance killed 4.7 million people in 2021 alone — phage therapy is one of the most promising alternatives in the pipeline
- What Is Bacteriophage Therapy?
- How Does Bacteriophage Therapy Work Against Antibiotic Resistance?
- Key Uses and Target Infections
- Bacteriophage Therapy Safety Profile and Administration
- What Does the Research Say?
- Bacteriophage Therapy vs Conventional Antibiotics
- How Is Bacteriophage Therapy Used in Practice?
- Related Reading
- Frequently Asked Questions
- The Bottom Line
Bacteriophage Therapy: 7 Proven Facts About Nature’s Antibiotic Alternative for Drug-Resistant Bacterial Infections
Bacteriophage therapy antibiotic resistance — antibiotics are failing — and bacteriophage therapy is emerging as one of the most promising solutions to the antibiotic resistance crisis. In 2021 alone, bacterial antimicrobial resistance was responsible for 4.7 million deaths globally, according to the World Health Organization. That’s more than HIV, malaria, and breast cancer combined. And the problem isn’t slowing down: WHO surveillance data from 2023 shows that 1 in 6 laboratory-confirmed bacterial infections worldwide is now resistant to at least one antibiotic class. If you or someone you know has faced a drug-resistant infection — or you’re simply trying to understand where medicine is headed — bacteriophage therapy is the treatment approach you need to know about. By the end of this article, you’ll understand exactly how phages work, what the latest clinical evidence shows, who can access phage treatment today, and where this field is going in the next five years. One finding — about phages attacking bacteria hiding inside human cells — changes the entire game for chronic infections. We’ll get to that.
What Is Bacteriophage Therapy?
Bacteriophage therapy is a treatment that uses viruses called bacteriophages — literally “bacteria eaters” — to target and destroy specific bacterial cells causing infection. Discovered in 1917 by Félix d’Hérelle, phages have been used clinically in Eastern Europe (particularly Georgia and Poland) for over a century, while Western medicine largely abandoned them after the discovery of penicillin. Now, with the antibiotic resistance crisis accelerating, phage therapy is experiencing a global renaissance.
Bacteriophage therapy antibiotic resistance — phages are the most abundant biological entities on Earth — there are an estimated 10³¹ phage particles in the biosphere, outnumbering bacteria roughly 10 to 1. They exist everywhere: in soil, seawater, and even inside your own gut. Each phage is exquisitely specific — a given phage typically infects only one species or even one strain of bacteria. This specificity is both phage therapy’s greatest strength (no collateral damage to your microbiome) and its biggest logistical challenge (you need to identify the right phage for each infection).
Quick Answer: Bacteriophage therapy uses naturally occurring viruses that specifically kill bacteria to treat infections, especially those that no longer respond to antibiotics. It has been used clinically for over 100 years in Eastern Europe and is now being developed in regulated clinical trials in the US and EU for drug-resistant bacterial infections.
How Does Bacteriophage Therapy Work Against Antibiotic Resistance?
Bacteriophage therapy antibiotic resistance — the mechanism behind bacteriophage therapy is both elegant and brutal — at least from the bacterium’s perspective. Phages follow a four-step lytic cycle that ends with the bacterial cell literally bursting open:
- Attachment: The phage’s tail fibers recognize and bind to specific receptor proteins on the bacterial cell surface — like a key fitting a lock. If the receptor isn’t present, the phage cannot infect. This is why phages are so specific.
- DNA Injection: The phage contracts its tail sheath and injects its genetic material through the bacterial cell wall and membrane into the cytoplasm. The empty protein capsid remains outside.
- Replication: Once inside, the phage DNA hijacks the bacterium’s cellular machinery. The host cell is converted into a phage factory, producing hundreds of new phage particles.
- Cell Lysis: Phage-encoded enzymes called lysins degrade the bacterial cell wall from the inside. Internal pressure causes the cell to burst, releasing the new phage particles to infect neighboring bacteria.
Here’s where it gets interesting. This mechanism is fundamentally different from how antibiotics work. Antibiotics typically interfere with bacterial metabolism — blocking cell wall synthesis, protein production, or DNA replication. Phages bypass all of that. They replicate themselves inside the target and destroy it mechanically. This means that bacteriophage therapy can kill bacteria that have evolved resistance to every available antibiotic class, including carbapenem-resistant Enterobacteriaceae (CRE), multidrug-resistant Pseudomonas aeruginosa, and methicillin-resistant Staphylococcus aureus (MRSA).
Bacteriophage therapy antibiotic resistance — a 2024 review published in Clinical Microbiology Reviews examined the pharmacokinetics and pharmacodynamics of phage therapy against four major multidrug-resistant Gram-negative pathogens — Klebsiella pneumoniae, Acinetobacter baumannii, Pseudomonas aeruginosa, and Escherichia coli — and confirmed that phage self-replication inside the host creates a fundamentally different dose-response relationship than antibiotics. The authors noted that conventional PK/PD modeling (the kind used to determine antibiotic dosing) is inadequate for phages because the drug effectively “multiplies itself” at the infection site (Siopi et al., 2024).
But there’s a catch. That extreme specificity means you can’t just take a “broad-spectrum phage pill” the way you’d take amoxicillin. The infecting bacterium must be isolated, cultured, and tested against a library of phages to find one that works. This process — called phage susceptibility testing — can take days to weeks. For acute infections, that’s a problem. For chronic infections that have resisted months or years of antibiotics, that time is well worth it.
Research Spotlight: A 2024 study in mBio demonstrated something remarkable — phages can enter mammalian cells and kill bacteria hiding inside them (Schmalstig et al., 2024). This was the first demonstration that phages can reach intracellular Mycobacterium abscessus, an emerging multidrug-resistant pathogen that causes severe disease in cystic fibrosis patients. The bacterium survives inside host cells, where antibiotics have limited access. Phages, it turns out, don’t share that limitation. This finding opens the door to phage treatment for infections that were previously considered untreatable.
Key Uses and Target Infections for Bacteriophage Therapy
Multidrug-Resistant Gram-Negative Infections: Bacteriophage therapy antibiotic resistance Explained
Bacteriophage therapy antibiotic resistance — the strongest evidence for bacteriophage therapy exists in infections caused by MDR Gram-negative bacteria — Pseudomonas aeruginosa, Klebsiella pneumoniae, Acinetobacter baumannii, and Escherichia coli. These are precisely the pathogens driving the AMR crisis, and they’re the ones where conventional antibiotics are most frequently failing. The largest clinical cohort to date (100 patients across 35 hospitals in 12 countries) included infections from all four of these pathogens and reported clinical improvement in 77.2% of cases.
Chronic and Biofilm-Associated Infections: Bacteriophage therapy antibiotic resistance Explained
Bacteriophage therapy antibiotic resistance — phage therapy has a unique advantage in chronic infections where bacteria form biofilms — dense, slimy communities that are up to 1,000 times more resistant to antibiotics than free-floating bacteria. Biofilm infections include chronic wounds (diabetic ulcers, burns), prosthetic joint infections, and lung infections in cystic fibrosis patients. Phages can penetrate biofilms more effectively than many antibiotics because their small size allows them to diffuse through the biofilm matrix, and some phages carry enzymes (depolymerases) that actively break down biofilm structure.
Staphylococcus aureus Infections Including MRSA: Bacteriophage therapy antibiotic resistance Explained
Bacteriophage therapy antibiotic resistance — a 2024 review covering phage therapy for drug-resistant S. aureus highlighted that S. aureus bacteremia still carries approximately 25% mortality despite modern antibiotic care, and phages represent an evidence-supported alternative strategy (Liu et al., 2024). The review compiled clinical cases showing successful outcomes in prosthetic joint infections, diabetic foot ulcers, and bloodstream infections.
Q: Who Is This For?
A: – Patients with confirmed multidrug-resistant bacterial infections who have failed multiple antibiotic courses – Individuals with chronic biofilm-associated infections (chronic wounds, CF lung infections, prosthetic device infections) – Patients who cannot tolerate long-term antibiotics due to organ toxicity (kidney/liver damage) or severe allergies – As compassionate-use therapy when no effective antibiotic options remain
Who Should Consider Caution:
- Patients with acute, rapidly progressing infections where the 1–3 week phage-matching delay poses unacceptable risk — conventional broad-spectrum antibiotics remain the safer first choice here
- Individuals with known severe allergies to phage preparation components (though phage-specific allergic reactions are rare in the clinical literature)
- Patients with infections caused by bacteria for which no matching phage has been identified in available libraries
- Phage therapy is not appropriate for viral, fungal, or parasitic infections — it is exclusively antibacterial
Bacteriophage therapy antibiotic resistance — while phages are still in clinical development for most infections, MedsBase carries a full range of conventional antibiotics for bacterial infections. You can browse the full antibiotics category to see available treatment options.
Bacteriophage Therapy Safety Profile and Administration
Bacteriophage therapy has a remarkably clean safety profile compared to conventional antibiotics — and that’s not surprising when you consider what phages actually are. They’re viruses, yes, but viruses that cannot infect human cells. Phage receptors are bacterial surface proteins that don’t exist on human cell membranes. In the 100-patient cohort study, adverse events were predominantly mild and self-limiting: transient fever (in approximately 15% of patients), local injection-site reactions, and occasional mild gastrointestinal discomfort.
| Side Effect | Frequency | Severity | What To Do |
|---|---|---|---|
| Transient fever | ~15% | Mild–moderate | Usually resolves within 24–48 hours; antipyretics if needed |
| Injection-site reaction | ~10–15% | Mild | Topical care; rotate administration sites |
| GI discomfort (oral phages) | <10% | Mild | Take with food if oral formulation |
| Phage resistance emergence | 43.8% | Variable | Combine with antibiotics (synergy documented in 90% of cases) |
| Anti-phage antibody response | Documented in some cases | Can reduce efficacy | Monitor; switch phage if neutralizing antibodies develop |
| Anaphylaxis | Extremely rare | Severe | Emergency protocols; this is why phage therapy is administered under clinical supervision |
Bacteriophage therapy antibiotic resistance — the one safety concern that deserves attention is phage resistance. Just as bacteria can evolve resistance to antibiotics, they can also evolve resistance to phages — typically by mutating or losing the surface receptor the phage uses for attachment. In the 100-patient study, in vivo phage resistance emerged in 43.8% of treated patients. However, here’s the key difference from antibiotic resistance: phage resistance often comes at a fitness cost to the bacterium. When bacteria drop the phage receptor, they frequently lose virulence factors or become more susceptible to antibiotics. The research found that phage-antibiotic synergy was documented in 90% of evaluated patients — meaning that combining phages with antibiotics produced better results than either alone (Pirnay et al., 2024).
Bacteriophage therapy antibiotic resistance — another consideration: the human immune system can produce neutralizing antibodies against phages. A case report in mBio documented a patient with 7 years of recurrent VRE bloodstream infections who received combination phage + antibiotic therapy. The treatment produced months of clinical improvement and reduced intestinal VRE burden, but an anti-phage neutralizing antibody response eventually emerged, coinciding with infection recurrence (Stellfox et al., 2024). This illustrates both the promise and the immunological limitation of bacteriophage therapy — it’s not a one-and-done cure, but rather a tool that must be managed carefully.
What Does the Research Say About Bacteriophage Therapy?
| Study | Year | Design | Key Finding | Source |
|---|---|---|---|---|
| Pirnay et al. (100-patient cohort) | 2024 | Observational, 35 hospitals, 12 countries | 77.2% clinical improvement; 61.3% bacterial eradication | PMID 38834776 |
| Siopi et al. (PK/PD review) | 2024 | Comprehensive review | Phage self-replication invalidates conventional PK/PD modeling; urgent need for optimized dosing | PMID 39072666 |
| Liu et al. (S. aureus review) | 2024 | Review of clinical cases + trials | Phage therapy is evidence-supported for drug-resistant S. aureus; ~25% mortality in bacteremia | PMID 38357445 |
| Stellfox et al. (VRE case) | 2024 | Single-patient case report | Phage + antibiotics produced months of clinical benefit; anti-phage antibodies emerged | PMID 38353560 |
| Schmalstig et al. (intracellular) | 2024 | In vitro / ex vivo | First evidence phages enter mammalian cells and kill intracellular M. abscessus | PMID 38059609 |
What this means for you: The research on bacteriophage therapy is promising but still maturing. The largest clinical dataset covers 100 patients — impressive for a niche treatment, but tiny compared to the tens of thousands studied for most approved antibiotics. If you’re facing a drug-resistant infection today, phage therapy is a real option through compassionate-use programs (discussed below), but it is not yet a first-line treatment. The evidence strongly supports combining phages with antibiotics rather than replacing antibiotics entirely — at least for now.
Bacteriophage Therapy vs Conventional Antibiotics
| Feature | Bacteriophage Therapy | Conventional Antibiotics |
|---|---|---|
| Specificity | Targets specific bacterial species/strains | Broad-spectrum or narrow-spectrum |
| Microbiome impact | Minimal — leaves beneficial bacteria intact | Broad-spectrum antibiotics disrupt gut flora |
| Resistance development | Bacteria can evolve phage resistance, but often at fitness cost | Resistance genes can spread horizontally between species |
| Self-replication at infection site | Yes — phages multiply where bacteria are | No — fixed dose, eliminated by liver/kidneys |
| Biofilm penetration | Good — small size + depolymerase enzymes | Limited — many antibiotics poorly penetrate biofilms |
| Regulatory status | Compassionate use / clinical trials (US/EU); approved in Georgia, Poland, Russia | Fully FDA/EMA approved |
| Cost | High — personalized phage preparation is labor-intensive | Generic antibiotics are inexpensive |
| Administration | IV, topical, inhaled, oral (depending on infection) | Oral or IV |
| Side effects | Mild — fever, injection-site reactions, rare immune responses | Range from mild GI upset to organ toxicity, allergy, C. difficile |
| Time to treatment | 1–3 weeks for phage matching + preparation | Immediate — empiric therapy started same day |
Verdict: For most common bacterial infections, conventional antibiotics remain the appropriate first-line treatment — they are faster to deploy, cheaper, and backed by decades of randomized controlled trial data. Bacteriophage therapy is best positioned as a second-line or salvage therapy for multidrug-resistant infections where antibiotics have failed, or as an adjunctive treatment combined with antibiotics for biofilm-associated chronic infections. The two approaches are complementary, not competitive — and the strongest clinical results come from using them together.
How Is Bacteriophage Therapy Used in Practice?
Step 1 — Identify the pathogen. The infecting bacterium must be cultured from a clinical sample (blood, sputum, wound swab, urine) and identified to the species level. Antibiotic susceptibility testing is performed in parallel.
Step 2 — Phage susceptibility testing. The bacterial isolate is screened against a library of phages — typically hundreds to thousands of characterized phages maintained by specialized centers (the Eliava Institute in Georgia, the Queen Astrid Military Hospital in Belgium, and the Center for Innovative Phage Applications and Therapeutics at UC San Diego). A phage that lyses the bacterium in vitro is selected.
Step 3 — Preparation and purification. The selected phage is amplified, purified to remove bacterial debris and endotoxins, and formulated for the intended route of administration. This is done under GMP (Good Manufacturing Practice) conditions at specialized facilities.
Step 4 — Administration. Phages can be delivered intravenously (for bloodstream infections), topically (for wound infections), via inhalation (for respiratory infections), or orally (for GI infections). Treatment duration varies from days to months depending on the infection. Phage-antibiotic combination is used in most cases given the 90% synergy rate documented in clinical experience.
Common mistakes to avoid:
- Assuming phage therapy is a drop-in replacement for antibiotics — it’s a different paradigm requiring bacterial identification before treatment
- Expecting immediate results — phage therapy works over days to weeks, not hours
- Stopping antibiotics when starting phages — the best outcomes come from combination therapy, not monotherapy
Important: Phage therapy is not a treatment you can self-administer. If you’re facing a resistant bacterial infection, the first step is consulting your doctor about available antibiotic options. MedsBase carries a range of conventional antibiotics for bacterial infections — always use antibiotics under medical supervision and complete the full prescribed course.
Related Reading
- Antihistamines Side Effects: What Long-Term Allergy Treatment Users Should Know — understand medication safety across drug classes
- Browse MedsBase antibiotics — currently available treatments for bacterial infections
- Metformin vs SGLT2 Inhibitors for Type 2 Diabetes — another area where treatment options are evolving rapidly
Frequently Asked Questions About Bacteriophage Therapy
Q: Is bacteriophage therapy FDA approved?
A: No, bacteriophage therapy does not yet have full FDA approval as a standard treatment. It is available in the United States through the FDA’s compassionate use (expanded access) program for patients with serious or life-threatening drug-resistant infections who have exhausted other options. The FDA has also cleared several phage products for use in clinical trials. Regulatory pathways are evolving — the FDA designated phage therapy as a “biologic” and is developing guidance specific to phage products.
Q: Can bacteriophages completely replace antibiotics?
A: Not in the foreseeable future. Phage therapy and antibiotics work best together — the clinical evidence shows phage-antibiotic synergy in approximately 90% of evaluated cases. Phages are likely to become an important tool in the antibiotic resistance toolkit, but they will complement antibiotics rather than replace them for most infections.
Q: What are the side effects of phage therapy?
A: Bacteriophage therapy side effects are generally mild. The most common are transient fever (about 15% of patients) and injection-site reactions. Unlike antibiotics, phages do not cause gastrointestinal microbiome disruption or C. difficile infections because they don’t kill beneficial gut bacteria. Rarely, the immune system can produce neutralizing antibodies that reduce phage effectiveness over time.
Q: How long does phage therapy take to work?
A: Clinical improvement from bacteriophage therapy can begin within 48–72 hours for acute infections, but full treatment courses typically last 2–6 weeks. The phage-matching process itself (identifying the bacterium and finding a phage that kills it) takes 1–3 weeks. This lead time makes phage therapy better suited for chronic infections than acute medical emergencies.
Q: Can I access bacteriophage therapy outside of clinical trials?
A: Yes, through compassionate-use programs in the US (FDA expanded access), Belgium (Queen Astrid Military Hospital), and established treatment centers in Georgia (Eliava Institute) and Poland (Hirszfeld Institute). Each case requires physician sponsorship and regulatory approval. Patients typically travel to the treatment center or have phages shipped to their hospital.
Q: How much does phage therapy cost?
A: The cost varies widely depending on whether the treatment is part of a clinical trial (often free to the patient), compassionate use (variable — some centers absorb costs, others charge $10,000–$50,000+ for a personalized phage preparation), or treatment abroad (travel + treatment fees). Insurance coverage for phage therapy is limited since it lacks FDA approval.
Q: Can bacteria become resistant to phages?
A: Yes, bacteria can evolve resistance to phages by mutating the surface receptors that phages use to attach. Clinical data shows phage resistance emerges in approximately 43.8% of treated patients. However, phage resistance often comes with a fitness cost — the bacteria may lose virulence factors or become more susceptible to antibiotics. Using phage cocktails (multiple phages targeting different receptors) reduces resistance risk.
Q: What types of infections can phage therapy treat?
A: Bacteriophage therapy has been used to treat: chronic wound infections (diabetic ulcers, burns), prosthetic joint infections, osteomyelitis, respiratory infections in cystic fibrosis, urinary tract infections, bloodstream infections (bacteremia), and complicated intra-abdominal infections. The strongest evidence exists for Gram-negative infections (Pseudomonas, Klebsiella, Acinetobacter, E. coli) and Staphylococcus aureus including MRSA.
The Bottom Line on Bacteriophage Therapy and Antibiotic Resistance
Bacteriophage therapy represents one of the most promising strategies in the fight against antibiotic resistance — and the science is accelerating faster than most people realize. The mechanism is sound. The safety profile is favorable. The clinical results — 77.2% improvement in 100 consecutive patients — are encouraging enough to justify the growing investment in phage research worldwide. But phage therapy is not a silver bullet, and it is not ready to replace conventional antibiotics. The infrastructure for phage matching, production, and regulation is still being built. For now, the smartest approach is to use antibiotics responsibly, preserve their effectiveness, and view phages as a powerful backup — one that is getting closer to prime time every year.
Your most immediate action: If you’re currently dealing with a bacterial infection, complete your prescribed antibiotic course and consult your doctor about treatment options. Antibiotic stewardship — using antibiotics only when necessary and always completing the full course — is the single most impactful thing any individual can do to slow the spread of resistance. MedsBase offers a full range of conventional antibiotics — always use them under medical supervision.
What to read next:
- Antihistamines Side Effects: What Long-Term Allergy Treatment Users Should Know — understand medication safety across different drug classes
- Metformin vs SGLT2 Inhibitors for Type 2 Diabetes — comparing first-line diabetes treatments based on the latest evidence
Medical Disclaimer: This article is for informational purposes only and does not constitute medical advice. Always consult a qualified healthcare professional before starting, stopping, or changing any medication. Bacteriophage therapy is not currently FDA-approved for routine clinical use and should only be pursued through established clinical programs under physician supervision.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.