








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
exercise prescription for heart health — Exercise Prescription for Heart Health — What the New ACC Guidelines Mean and How to Get Started. Read on for an evidence-backed guide covering everything you need to know.

[Key Takeaways box styled #f4f8fb, border-left #2c7cb0] Key Takeaways: Exercise Prescription for Heart Health
- The American College of Cardiology now recommends formal exercise prescription for heart health — not as a generic suggestion but as a specific, dosed intervention that belongs in every cardiovascular treatment plan, just like a medication.
- The “dose” that matters most: 150 minutes of moderate aerobic activity per week plus two strength-training sessions — and meeting even half of that goal cuts cardiovascular mortality risk by nearly 20%.
- Exercise alone can lower systolic blood pressure by 5–8 mmHg — comparable to a low-dose single medication — and combining it with medication typically allows for lower doses and fewer side effects.
- The biggest gap in current care: fewer than 1 in 4 American adults meet both the aerobic and strength guidelines, yet the ACC says doctors rarely write anything more specific than “you should exercise more.”
- Starting safely is the part most articles skip — but the guidelines are clear: get medical clearance first if you have existing heart disease, start at 10 minutes of walking, and add 5 minutes per week.
- What Is an Exercise Prescription for Heart Health?
- How Does Exercise Protect the Heart?
- Who Benefits Most From an Exercise Prescription?
- Safety: How to Start Without Hurting Yourself
- What Does the Research Say?
- Exercise Alone vs Exercise + Medication
- How to Start an Exercise Prescription Safely
- Related Reading
- Frequently Asked Questions
- The Bottom Line
[Hero Intro — no heading, 150–200 words — uses myth-bust opener]
Most people believe that “exercise is good for your heart” is about as specific as cardiovascular advice gets. A new scientific statement from the American College of Cardiology, published in the Journal of the American College of Cardiology on October 20, 2026, says that approach is failing patients — and it is time for exercise prescription for heart health to be taken as seriously as a statin or a beta-blocker.
Released on October 20, 2026, the ACC statement makes a radical-in-its-simplicity argument: exercise should be prescribed. Not suggested. Not mentioned in passing at the end of an appointment. Prescribed — with a specific type, dose, frequency, and progression plan written down and followed up on, exactly the way a doctor would manage a new blood pressure medication.
By the end of this article, you will understand what an exercise prescription for heart health actually looks like, which cardiovascular conditions benefit most, what the research says about exercise versus (and alongside) medication, and — crucially — how to start safely if you have never had a structured exercise plan before. One finding about the blood-pressure-lowering power of combining strength and aerobic training surprises even longtime gym-goers.
Exercise Prescription for Heart Health: 8 Evidence-Based Facts From the New ACC Guidelines
What Is an Exercise Prescription for Heart Health?
An exercise prescription for heart health is a written, individualized plan that specifies the type, intensity, duration, and frequency of physical activity — designed to prevent or manage cardiovascular disease with the same rigor applied to a medication prescription. Instead of “you should exercise more,” it says: “Walk at a brisk pace for 30 minutes, 5 days per week, at an intensity where you can talk but not sing. Add resistance training with bands or bodyweight exercises twice per week on non-consecutive days. Progress to 45-minute sessions after 4 weeks.”
Quick Answer: An exercise prescription for heart health is physical activity translated into a medical intervention — with a specific dose, a target outcome, contraindications, and a follow-up plan, just like any drug your doctor prescribes. The ACC now says this should be standard practice, not an afterthought.
The concept is called “exercise is medicine” — a term that has been around for years but now has the weight of the ACC’s formal endorsement behind it. What makes the 2026 ACC statement different from prior guidelines is its specificity: it does not just say “150 minutes per week” (the long-standing public health guideline). It breaks down exactly how to prescribe exercise for specific cardiovascular conditions, how to escalate the dose, when to refer to supervised programs like cardiac rehabilitation, and how to monitor adherence — the same way you would monitor blood pressure response to a new medication.
Here is what most people miss: an exercise prescription for heart health is not just for people who already have heart disease. It is for prevention too. The ACC explicitly states that exercise prescription belongs in primary prevention — keeping healthy people healthy — not just in cardiac rehab after a heart attack.
How Does Exercise Protect the Heart? — Exercise prescription for heart health Explained

The heart protection from exercise is not one thing — it is five simultaneous biological effects that compound over time.
[Research Spotlight box styled #fff8e1, border-left #f5a623] Research Spotlight When you exercise regularly, five key changes happen inside your cardiovascular system: (1) your blood vessels produce more nitric oxide, which relaxes artery walls and lowers blood pressure; (2) your heart muscle thickens in a healthy way (athlete’s heart), increasing stroke volume so it pumps more blood per beat; (3) your HDL (“good”) cholesterol rises while triglycerides drop; (4) systemic inflammation — measured by C-reactive protein — falls, reducing the inflammatory damage that drives atherosclerosis; and (5) your resting heart rate drops because a stronger heart needs fewer beats to move the same amount of blood. Each of these effects independently predicts lower cardiovascular risk, and they happen together.
Think of it like this: your cardiovascular system is a plumbing-and-pump network that builds up mineral deposits (plaque), stiffens with age, and struggles against higher pressure over time. Medication can lower the pressure (blood pressure meds) and slow the deposits (statins). But exercise actually strengthens the pump, makes the pipes more flexible, and reduces the chemical irritants that cause deposits in the first place. It is not a substitute for medication in most cases — but it is the only intervention that improves the system at every level simultaneously.
Take James, a hypothetical patient: 58, desk job, newly diagnosed with stage 1 hypertension (142/90). His doctor writes an exercise prescription for heart health — 30 minutes of brisk walking 5 days per week plus bodyweight squats, lunges, and pushups twice weekly. At his 12-week follow-up, his blood pressure reads 128/84. He has not filled a prescription. His doctor keeps him on the exercise plan and schedules a 6-month check. Not every patient responds this well, but the research says about 50–70% of people with mild hypertension see a clinically meaningful drop from exercise alone.
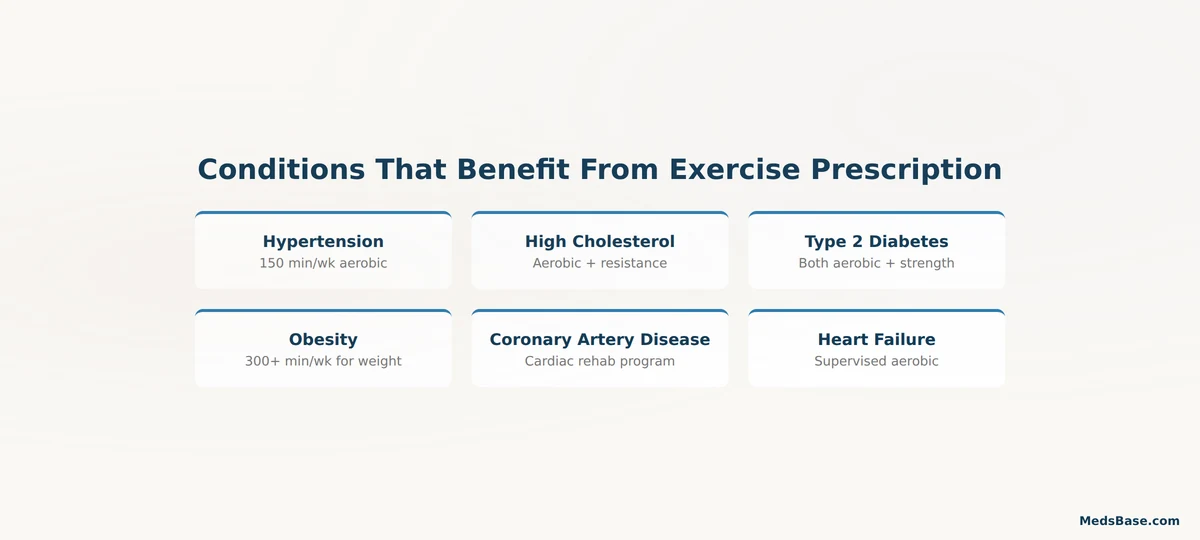
Who Benefits Most From an Exercise Prescription?
[Image: Key Conditions Infographic — see Image Strategy #3]
Hypertension
This is where the data are strongest. Aerobic exercise — particularly brisk walking, cycling, or swimming — lowers systolic blood pressure by an average of 5–8 mmHg and diastolic by 3–5 mmHg, comparable to a single low-dose antihypertensive. The effect is larger in people with higher starting blood pressure. An exercise prescription for heart health is now considered a first-line intervention for stage 1 hypertension (130–139/80–89) before medication.
High Cholesterol and Dyslipidemia
Regular aerobic exercise raises HDL cholesterol by roughly 3–6% and lowers triglycerides by 10–20%, though it has less effect on LDL. This is why exercise is typically prescribed alongside dietary changes and, when needed, statin therapy — not as a standalone cholesterol treatment, but as a powerful adjunct that improves the overall lipid profile and reduces the inflammatory component of atherosclerosis.
Type 2 Diabetes and Metabolic Syndrome
Exercise improves insulin sensitivity for 24–72 hours after each session. For someone with type 2 diabetes or prediabetes, regular exercise lowers HbA1c by an average of 0.5–0.7 percentage points — clinically meaningful and comparable to adding a second oral medication. The combination of aerobic and resistance training outperforms either alone for glucose control.
Coronary Artery Disease (Post-Event)
This is where an exercise prescription for heart health is most formally established: cardiac rehabilitation. After a heart attack, stent placement, or bypass surgery, structured, supervised exercise programs reduce cardiovascular mortality by approximately 26% and hospital readmissions by 18%. The ACC statement emphasizes that referral rates to cardiac rehab remain abysmally low — around 20–30% of eligible patients — and calls exercise prescription a tool to close that gap.
Heart Failure
Until the 1990s, bed rest was standard advice for heart failure. The evidence now shows the opposite: carefully prescribed exercise improves functional capacity, quality of life, and in some studies, survival in patients with stable heart failure with reduced ejection fraction. The HF-ACTION trial demonstrated a modest but significant reduction in cardiovascular mortality and heart failure hospitalization with supervised aerobic training.
[Who Is This For? / Who Should Avoid It? box styled #eef7ee / #4caf50] Who Is This For?
- Adults with stage 1 hypertension considering lifestyle treatment before medication
- Anyone with elevated cholesterol wanting to maximize their lipid profile naturally
- People with type 2 diabetes or prediabetes looking to improve insulin sensitivity
- Post-heart-attack or post-stent patients eligible for cardiac rehabilitation
- Anyone sedentary with a family history of early heart disease — prevention is where exercise prescription for heart health has the biggest payoff
Who Needs Medical Clearance First:
- Anyone with known coronary artery disease, heart failure, or valvular heart disease
- People who experience chest pain, unusual shortness of breath, or dizziness with exertion
- Those with uncontrolled hypertension (>180/110)
- Recent heart attack or cardiac surgery (within 6 weeks — supervised rehab required)
- Anyone with an implantable cardioverter-defibrillator (ICD) — need clearance on heart-rate limits
Safety: Starting an Exercise Prescription for Heart Health Without Injury
Quick Answer: For most sedentary adults without known heart disease, starting with 10–15 minutes of walking at a “talk test” pace (you can hold a conversation) is safe without medical clearance. The real risk is not the exercise — it is staying sedentary. Cardiac rehabilitation programs reduce cardiovascular mortality by 26% precisely because supervised exercise is safer than unsupervised inactivity in high-risk populations.
| Risk | Who Is Affected | How Common | How to Prevent It |
|---|---|---|---|
| Acute cardiac event during exercise | People with undiagnosed CAD; extremely rare in asymptomatic adults | ~1 per 700,000–1,500,000 exercise hours | Get medical clearance if you have risk factors; start low, progress slowly |
| Musculoskeletal injury | Sedentary adults starting too aggressively | Common (20–40% in first 3 months) | Start at 50% of target volume; increase by ≤10% per week; include rest days |
| Blood pressure spike during heavy lifting | People with uncontrolled hypertension | Depends on baseline BP | Avoid Valsalva maneuver (holding breath); use lighter weights with higher reps |
| Hypoglycemia during exercise | People on insulin or sulfonylureas | Common without precautions | Check blood glucose before/after; have fast-acting carbs available |
| Post-exercise hypotension (dizziness) | People on multiple antihypertensives | Uncommon | Cool down gradually; stay hydrated; avoid hot showers immediately post-exercise |
Here is the pattern interrupt. The single biggest risk — by an enormous margin — is not exercising at all. The ACC statement is explicit about this: sedentary behavior is an independent risk factor for cardiovascular disease, separate from not meeting exercise guidelines. This is precisely why the new exercise prescription for heart health framework treats activity as a medical necessity rather than a lifestyle suggestion. Sitting for more than 8 hours per day is associated with a 20–30% increase in cardiovascular mortality, even in people who meet the exercise guidelines. The takeaway: move more AND sit less — both matter.
One clinical insight: people who have been sedentary for years often feel winded after just a few minutes of activity and interpret that as a warning sign. In most cases, it is simply deconditioning — the body’s normal response to being asked to do something it has not done in a while. True warning signs — chest pressure, unusual breathlessness that does not recover with rest, lightheadedness, or palpitations — feel different from the burning lungs of deconditioning. If you are unsure, that is exactly what a pre-exercise medical clearance visit is for.
What Does the Research Say?
[Image: Mortality Reduction Bar Chart — see Image Strategy #4]
| Study | Year | Key Finding | Source |
|---|---|---|---|
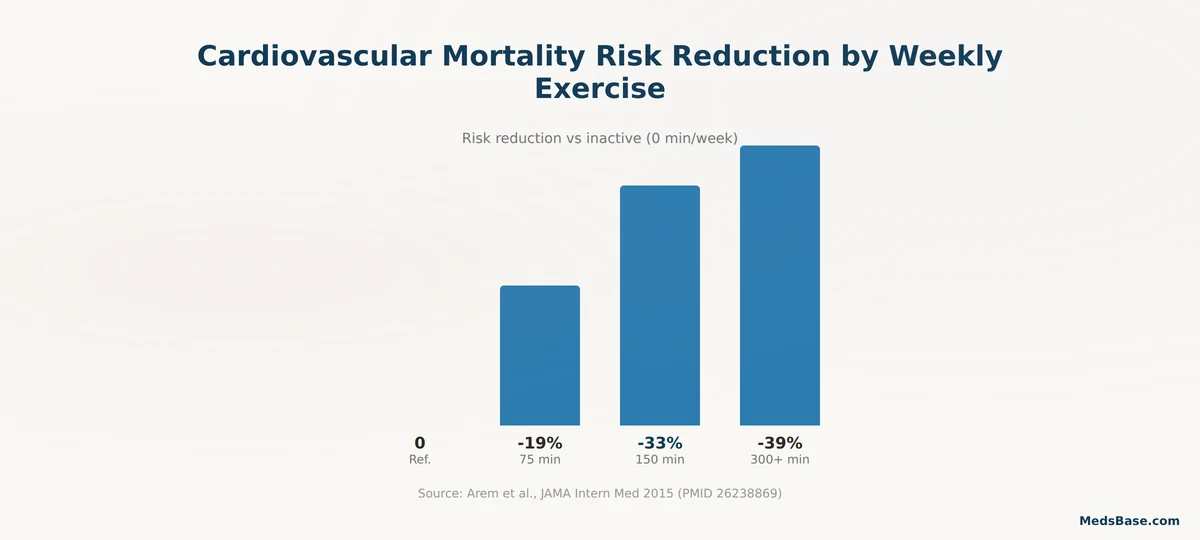
| Arem et al. (NCI Cohort) | 2015 | Meeting 150 min/week guideline reduced all-cause mortality by 31% and cardiovascular mortality by 33% vs inactive; 300+ min/week yielded additional benefit (39% reduction) | JAMA Intern Med |
| ACC 2026 Scientific Statement | 2026 | Formal exercise prescription recommended as standard cardiovascular care component; specific dosing by condition provided | Journal of the American College of Cardiology |
| Cornelissen & Smart (meta-analysis) | 2013 | Aerobic exercise reduced systolic BP by 5–8 mmHg; effect larger in hypertensives than normotensives | J Am Heart Assoc |
| Schroeder et al. (meta-analysis) | 2019 | Combining aerobic and resistance training produced greater BP reductions and improved body composition vs either alone | J Hum Hypertens |
| Anderson et al. (Cochrane review) | 2016 | Exercise-based cardiac rehabilitation reduced cardiovascular mortality by 26% and hospital admissions by 18% in coronary heart disease patients | Cochrane Database Syst Rev |
| HF-ACTION Trial | 2009 | In stable heart failure patients, supervised exercise training produced an 11% reduction in all-cause mortality/hospitalization (adjusted) after median 30-month follow-up | JAMA |
| ACC 2026 Scientific Statement | 2026 | Formal exercise prescription for heart health recommended as standard cardiovascular care; specific dosing by condition provided; physicians should write a written, individualized exercise plan with type, intensity, duration, frequency, and progression | Journal of the American College of Cardiology |
What this means for you: An exercise prescription for heart health is not wellness fluff — it is one of the most evidence-backed interventions in cardiovascular medicine. The dose-response relationship is clear: more activity, within reason, produces more protection. But the steepest part of the curve is the jump from zero to anything — a sedentary person who starts walking 10 minutes a day captures a disproportionate share of the benefit.
Exercise Alone vs Exercise + Medication: What the Data Show
[Image: Comparison Grid — see Image Strategy #5]
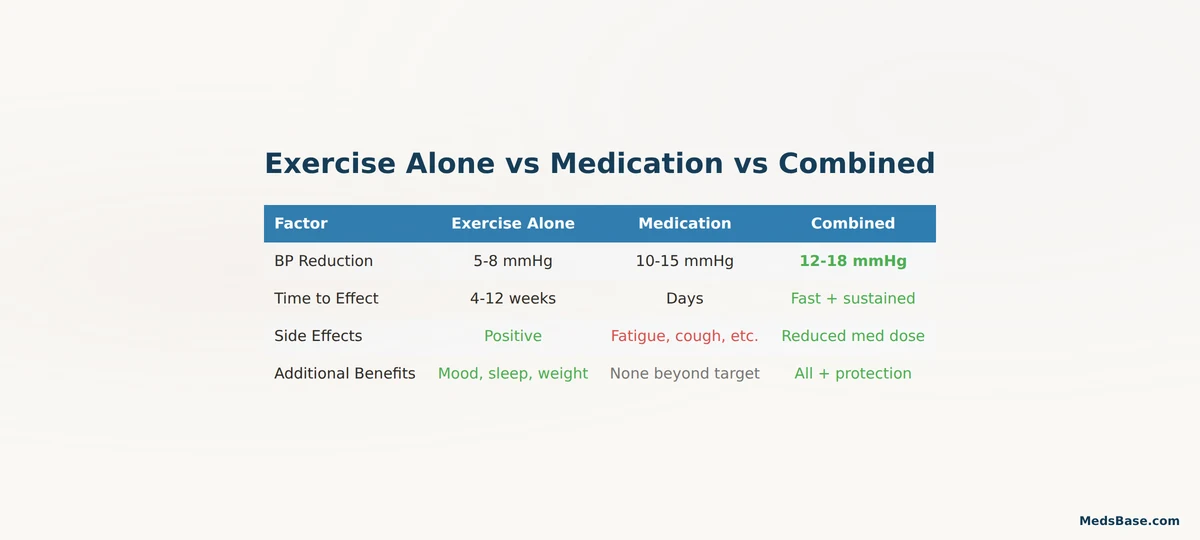
The question patients often ask is: “If exercise is so good for my heart, do I still need medication?” The answer depends on your starting point, but the comparison breaks down like this:
| Factor | Exercise Alone | Medication Alone | Exercise + Medication (Combined) |
|---|---|---|---|
| Systolic BP reduction | 5–8 mmHg | 10–15 mmHg (single drug) | 12–18 mmHg (lower drug dose needed) |
| LDL cholesterol reduction | Minimal (0–5%) | 30–50% (statin) | Same LDL drop as statin + HDL boost from exercise |
| Time to blood pressure effect | 4–12 weeks | Days to 2 weeks | Days (medication) + sustained (exercise) |
| Side effects | Muscle soreness (temporary) | Fatigue, cough, edema, electrolyte changes | Reduced medication side effects (lower dose) |
| Additional benefits | Weight loss, mood, sleep, insulin sensitivity, bone density | None beyond primary target | All exercise benefits + disease-specific medication protection |
| Adherence challenge | Behavioral; ~50% drop out by 6 months | Pill-taking; ~30% non-adherent at 1 year | Both challenges; but each reinforces the other |
| Cost | Free (walking) to gym membership ($30–50/mo) | Varies wildly; generic drugs often $5–20/mo | Combined cost of both |
Verdict: For stage 1 hypertension and primary prevention, an exercise prescription for heart health can reasonably be tried as first-line therapy with a 12-week re-evaluation. For established cardiovascular disease or stage 2 hypertension, the combination approach wins — exercise allows for lower medication doses, which means fewer side effects and better long-term tolerability. Research consistently shows that the combination of aerobic and resistance exercise produces the best blood pressure outcomes.
How to Start an Exercise Prescription Safely
[Image: How-To Steps — see Image Strategy #6]
Step 1: Get clearance if you need it. If you have known heart disease, symptoms with exertion, multiple risk factors, or are over 45 (men) / 55 (women) and completely sedentary, schedule a pre-exercise evaluation. Your doctor will check your blood pressure, possibly run an ECG, and give you heart-rate or intensity guidelines.
Step 2: Start at a “laughably easy” level. Walk for 10–15 minutes at a pace where you can hold a conversation. Do this 3 days in week one. The goal in the first two weeks is not fitness — it is establishing the habit without injury or burnout.
Step 3: Add 5 minutes per week until you hit 30 minutes per session. Once you are walking 30 minutes comfortably 3–4 days per week, add a fourth and then a fifth day. Target: 150 minutes per week of moderate aerobic activity.
Step 4: Add resistance training on two non-consecutive days. Start with bodyweight exercises: squats, wall pushups, lunges, glute bridges. Aim for 1–2 sets of 10–15 repetitions per exercise. The goal is not muscle bulk — it is maintaining muscle mass and metabolic health. Resistance bands or light dumbbells can be added once bodyweight feels easy.
Step 5: Track and escalate. The exercise prescription for heart health is not “set and forget.” After 8–12 weeks, reassess: Has your blood pressure changed? Can you go longer or add intensity? Your doctor may adjust the prescription — adding interval training, increasing resistance load, or referring you to a structured program.
Common mistakes to avoid:
- Starting with high-intensity workouts (HIIT, sprints) without a 4–6 week base of steady-state cardio
- Neglecting resistance training — aerobic-only programs leave muscle and metabolic benefits on the table
- Comparing yourself to pre-diagnosis fitness levels and getting discouraged
- Exercising through chest pain, unusual shortness of breath, or dizziness — these are stop-and-seek-care signals
- Assuming walking “doesn’t count” — it is the most studied, most accessible, and arguably best entry-point exercise for heart health
If you are managing blood pressure or cholesterol alongside your new exercise plan, you can browse heart health support options at MedsBase.
Related Reading
- Once Weekly Generic Hormone Therapy Patch: 6 Key FDA Approval Facts — for women navigating heart health decisions alongside menopause treatment
- Exercise vs Antidepressants for Depression: Which Works Better? — exercise benefits extend beyond the heart to mental health
Frequently Asked Questions
Q: How much exercise do I need for heart health?
A: The evidence-based minimum is 150 minutes of moderate aerobic activity per week plus two sessions of resistance training. This is the core of any exercise prescription for heart health. If 150 minutes feels daunting, start with what you can — even 75 minutes per week reduces cardiovascular mortality risk by nearly 20%.
Q: Can exercise replace blood pressure medication?
A: For stage 1 hypertension (130–139/80–89 mmHg), a structured exercise program can reduce blood pressure enough that some people avoid starting medication entirely. For stage 2 hypertension (≥140/90), exercise typically augments but does not replace medication — though it may allow for lower doses. Never stop or reduce medication without your doctor’s direction.
Q: What is the best exercise for your heart?
A: There is no single “best” — but the combination of aerobic exercise (walking, cycling, swimming) and resistance training (bodyweight, bands, weights) has the strongest evidence for cardiovascular protection. Within aerobic exercise, consistency beats type — the best exercise is the one you will actually do. Walking is dramatically underrated: it requires no equipment, is low-injury-risk, and produces robust cardiovascular benefits when done regularly.
Q: How to start exercising with high blood pressure?
A: Start with 10–15 minutes of walking at a comfortable pace, 3 times per week. Avoid heavy weightlifting that requires breath-holding (the Valsalva maneuver temporarily spikes blood pressure). Use lighter weights with higher repetitions. Check your blood pressure before and after exercise initially to understand how your body responds. If your resting BP is above 180/110, get medical clearance first.
Q: Is walking enough for heart health?
A: Yes — with a caveat. Brisk walking (at least 3 mph, where you are breathing harder but can still talk) meets the “moderate intensity” threshold. More than 30 major studies, including the landmark 2018 Physical Activity Guidelines for Americans, confirm that walking reduces cardiovascular risk across all age groups. The caveat: walking alone misses the muscle-preserving and insulin-sensitivity benefits of resistance training, so adding bodyweight exercises twice weekly creates a more complete exercise prescription for heart health.
Q: What does an exercise prescription look like?
A: It is a written plan that specifies: Type (e.g., brisk walking + resistance bands), Frequency (5 days aerobic + 2 days strength), Intensity (moderate — “talk test” pace for aerobic; 10–15 rep range for strength), Time (start 15 min, progress to 30–45 min), and Progression (add 5 min/week; increase resistance when 15 reps feels easy). Your doctor or a qualified exercise professional can write this for you.
Q: Are exercise guidelines different for women vs men?
A: The core guidelines — 150 min/week aerobic + 2x/week strength — apply to both sexes. However, women may benefit from emphasizing resistance training more, particularly after menopause, to combat the accelerated bone and muscle loss that accompanies estrogen decline. Women also experience a greater relative risk reduction from the same volume of exercise — the “start from zero” effect is particularly strong in women who have been sedentary.
The Bottom Line
The ACC’s call for formal exercise prescription for heart health is a long-overdue correction in cardiovascular medicine. For decades, doctors have told patients to exercise while prescribing medications with milligram precision — and the mismatch in rigor has cost lives. Exercise is not a nice-to-have wellness suggestion. It is a dose-dependent intervention with a mortality benefit that rivals or exceeds many drugs, zero copay, and side effects (temporary soreness) that most people would trade for medication side effects in a heartbeat.
The immediate action: if you are sedentary, start walking tomorrow for 10 minutes. Do it again the day after. That is not a placeholder — it is the beginning of your exercise prescription for heart health. If you have existing cardiovascular disease or risk factors, book the clearance visit. The single most important factor in whether exercise protects your heart is not intensity, not type, not even volume — it is whether you keep doing it. An exercise prescription for heart health works because it transforms vague good intentions into a concrete, dosed treatment plan that both you and your doctor can track.
Want to see how exercise stacks up in another domain entirely? Read our full comparison of exercise versus antidepressants for managing depression — the evidence for mental health is as strong as it is for the heart.
Medical Disclaimer: This article is for informational purposes only and does not constitute medical advice. An exercise prescription for heart health requires individual assessment by a qualified healthcare provider. Never begin a new exercise program — particularly if you have known cardiovascular disease — without appropriate medical evaluation. Do not stop or adjust cardiac medications without your doctor’s supervision.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.
Pingback: Exercise vs Antidepressants for Depression: 7 Key Facts