








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
bisphosphonates vs denosumab — Bisphosphonates vs Denosumab: Which Osteoporosis Treatment Is Right for You?. Read on for an evidence-backed guide covering everything you need to know.
Input Variables
- BLOG TITLE: Bisphosphonates vs Denosumab: Which Osteoporosis Treatment Is Right for You?
- PRIMARY KEYWORD: “bisphosphonates vs denosumab”
- SECONDARY KEYWORDS (6-10): osteoporosis treatment comparison, Prolia vs Fosamax, denosumab side effects, bisphosphonates bone density, RANKL inhibitor osteoporosis, alendronate vs denosumab, osteoporosis medication comparison, bisphosphonates fracture risk, denosumab rebound fractures, osteoporosis injection vs pill
- LONG-TAIL (/PAA) KEYWORDS: Which is better bisphosphonates or denosumab? What are the side effects of denosumab vs bisphosphonates? Is denosumab safer than bisphosphonates? How often do you take denosumab vs bisphosphonates? Can you switch from bisphosphonates to denosumab?
- META TITLE (50-60 chars, number + power word + keyword front-half): Bisphosphonates vs Denosumab: 7 Proven Differences for Osteoporosis
- META DESCRIPTION (150-160 chars, keyword in first 120): Bisphosphonates vs denosumab for osteoporosis — compare mechanisms, fracture protection, dosing schedules, side effects, and costs. Find which treatment fits your situation in 2026.
- URL SLUG: bisphosphonates-vs-denosumab
- SEARCH INTENT: Commercial-investigation
- TARGET CATEGORY: Woman’s Health (1589), Pain Management (6452)
SEO Metadata Block
“`yaml meta_title: “Bisphosphonates vs Denosumab: 7 Proven Differences for Osteoporosis” meta_description: “Bisphosphonates vs denosumab for osteoporosis — compare mechanisms, fracture protection, dosing schedules, side effects, and costs. Find which treatment fits your situation in 2026.” slug: bisphosphonates-vs-denosumab focus_keyword: bisphosphonates vs denosumab primary_category: womans-health (1589) secondary_category: pain-management-articles (6452) canonical: https://medsbase.com/bisphosphonates-vs-denosumab/ robots: index, follow “`
Cannibalisation & Intent Notes
- Existing posts checked: bisphosphonates-for-osteoporosis (74813) covers bisphosphonates only; raloxifene-vs-bisphosphonates (74860) covers SERM vs bisphosphonate comparison. This post fills the gap: head-to-head bisphosphonates vs denosumab (antiresorptive vs RANKL inhibitor) — no cannibalisation.
- Intent: Commercial-investigation — reader knows they have osteoporosis and is comparing treatment options before talking to their doctor or making a purchasing decision. The article should help them understand trade-offs so they can have an informed conversation.
- Keyword uniqueness: “bisphosphonates vs denosumab” does not appear in any existing post title or slug. Posts 74813 and 74860 reference bisphosphonates but not denosumab.
External Link Plan
| # | URL | Follow/Nofollow | Placement | Click Motivation |
|---|---|---|---|---|
| 1 | https://pubmed.ncbi.nlm.nih.gov/19639226/ | Followed | H2 “Efficacy Comparison” — FREEDOM trial data in table | “see the full FREEDOM trial results” — authoritative source for denosumab fracture reduction claims |
| 2 | https://pubmed.ncbi.nlm.nih.gov/8899667/ | Nofollow | H2 “Efficacy Comparison” — FIT trial data in table | “review the landmark FIT trial” — authoritative source for alendronate fracture reduction |
| 3 | https://pubmed.ncbi.nlm.nih.gov/17476007/ | Nofollow | H2 “Efficacy Comparison” — HORIZON trial data in table | “read the HORIZON trial findings” — authoritative source for zoledronic acid efficacy |
| 4 | https://www.nhs.uk/conditions/osteoporosis/treatment/ | Nofollow | H2 “Who Should Choose” — decision-making section | “NHS osteoporosis treatment guidance” — practical decision support from a trusted health authority |
| 5 | https://pubmed.ncbi.nlm.nih.gov/29194569/ | Followed | H2 “Side Effect Comparison” — denosumab rebound fracture risk paragraph | “research on vertebral fractures after denosumab discontinuation” — critical safety differentiator |
Internal Link Plan
| # | Anchor Text | Target URL | Where in Article | Click Motivation |
|---|---|---|---|---|
| 1 | “See our complete bisphosphonates guide” | https://medsbase.com/bisphosphonates-for-osteoporosis/ | After efficacy comparison section (H2 #6) | Reader wants deeper detail on bisphosphonate-specific dosing, types, and safety beyond the vs comparison |
| 2 | “Compare bisphosphonates with raloxifene” | https://medsbase.com/raloxifene-vs-bisphosphonates/ | After comparison section (H2 #7 or #8) | Reader considering a third treatment option (SERM) wants a similar head-to-head breakdown |
| 3 | After FAQ section, Related Reading module | Cross-cluster internal link driving traffic to another new post in the same publishing batch | ||
| 4 | “See available osteoporosis treatments” | https://medsbase.com/womens-health/ | Cost and Access section (H2 #10) | Reader ready to explore treatment options and pricing on the site |
Image Strategy
1. Hero Image
- Brief: “Bisphosphonates vs Denosumab Comparison — Pill vs Injection for Osteoporosis Treatment”
- Composition: Split-screen design with two medication icons side by side: left side shows a pill/capsule icon labelled “Bisphosphonates”, right side shows a syringe/injection icon labelled “Denosumab”. Background: soft clinical #f4f8fb with accent bars in #2c7cb0 and #f5a623. Clean, medical-feel with generous whitespace.
- Keywords: osteoporosis treatment pill injection comparison, bisphosphonates denosumab hero
- Filename: bisphosphonates-vs-denosumab-hero-comparison.jpg ; Alt text: Bisphosphonates vs denosumab osteoporosis treatment comparison — pill and injection options side by side
- Caption: None (hero image)
- Loading: `loading=”eager”` ; Dimensions: 1200×628
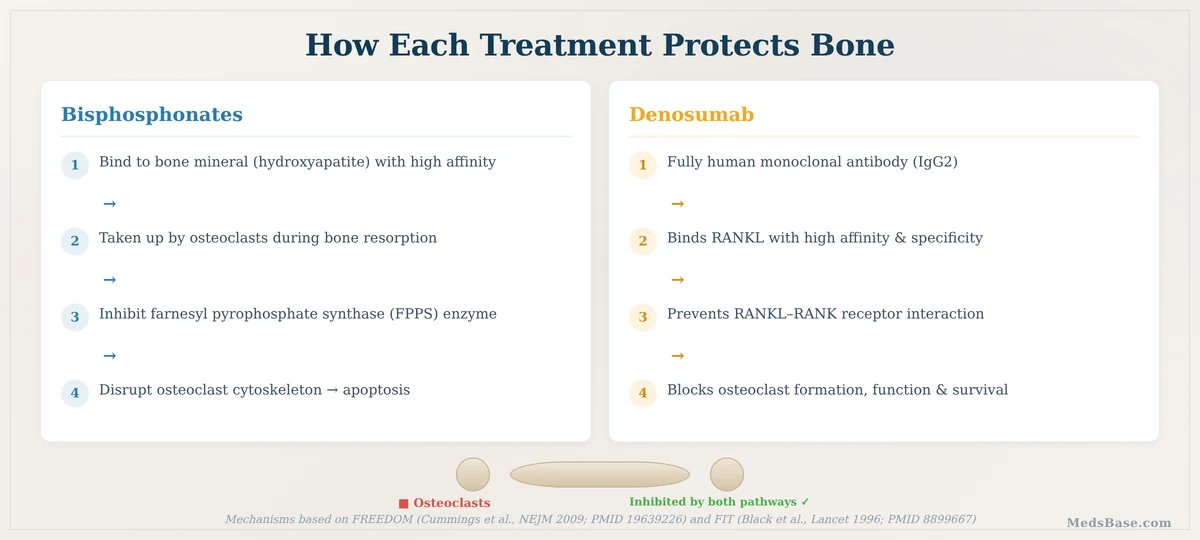
2. Mechanism Diagram
- Brief: “How Each Treatment Protects Bone — Bisphosphonates vs Denosumab Mechanism”
- Composition: Two-panel diagram. Left panel: bisphosphonate molecules binding to bone surface, with a red “X” over an osteoclast cell. Right panel: denosumab (antibody) blocking RANKL from binding to RANK receptor on osteoclast precursors. Arrows showing bone remodelling cycle. Clean vector style, palette #2c7cb0 (bisphosphonates) and #f5a623 (denosumab).
- Keywords: how bisphosphonates work, denosumab mechanism, RANKL inhibitor diagram, bone remodelling cycle
- Filename: bisphosphonates-denosumab-mechanism-comparison.jpg ; Alt text: Diagram comparing how bisphosphonates and denosumab protect bone through different mechanisms — osteoclast inhibition vs RANKL blockade
- Caption: Bisphosphonates bind to bone mineral and directly inhibit osteoclasts, while denosumab blocks RANKL signalling to prevent osteoclast formation.
- Loading: `loading=”lazy”` ; Dimensions: 1200×800
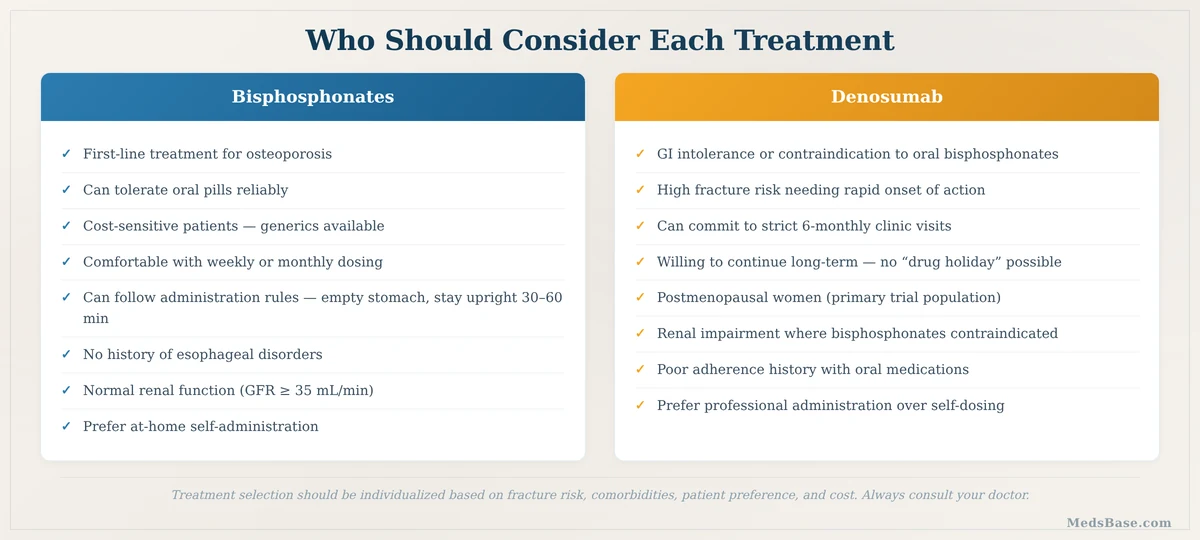
3. Candidate Selection Infographic
- Brief: “Who Should Consider Each Treatment — Bisphosphonates vs Denosumab”
- Composition: Split infographic with two columns. Left (bisphosphonates): icons for “First-line treatment”, “Can swallow pills”, “Cost-conscious”, “Weekly/monthly routine ok”. Right (denosumab): icons for “GI intolerance”, “High fracture risk”, “Prefers twice-yearly visits”, “Can commit to long-term plan”. Muted #f4f8fb background, icon highlights in #2c7cb0.
- Keywords: who should take bisphosphonates, denosumab candidate selection, osteoporosis treatment decision guide
- Filename: bisphosphonates-denosumab-candidate-selection.jpg ; Alt text: Infographic showing who should consider bisphosphonates vs denosumab for osteoporosis — first-line vs high-risk patient profiles
- Caption: Choosing between bisphosphonates and denosumab depends on your fracture risk level, medication tolerance, lifestyle preferences, and ability to maintain long-term treatment adherence.
- Loading: `loading=”lazy”` ; Dimensions: 1200×800
4. Clinical Trial Comparison Chart
- Brief: “Fracture Risk Reduction — Clinical Trials Compared”
- Composition: Grouped bar chart with three clusters: Vertebral Fracture Reduction (%), Hip Fracture Reduction (%), Non-Vertebral Fracture Reduction (%). Bars for alendronate (FIT trial), zoledronic acid (HORIZON trial), denosumab (FREEDOM trial). Bar colours: alendronate #2c7cb0, zoledronic acid #4a90d9, denosumab #f5a623. Source citations below each cluster. Clean academic chart style.
- Keywords: osteoporosis fracture reduction clinical trial data, FIT trial alendronate, HORIZON trial zoledronic acid, FREEDOM trial denosumab
- Filename: osteoporosis-treatment-fracture-reduction-trial-data.jpg ; Alt text: Bar chart comparing fracture risk reduction percentages from landmark clinical trials — FIT (alendronate), HORIZON (zoledronic acid), FREEDOM (denosumab)
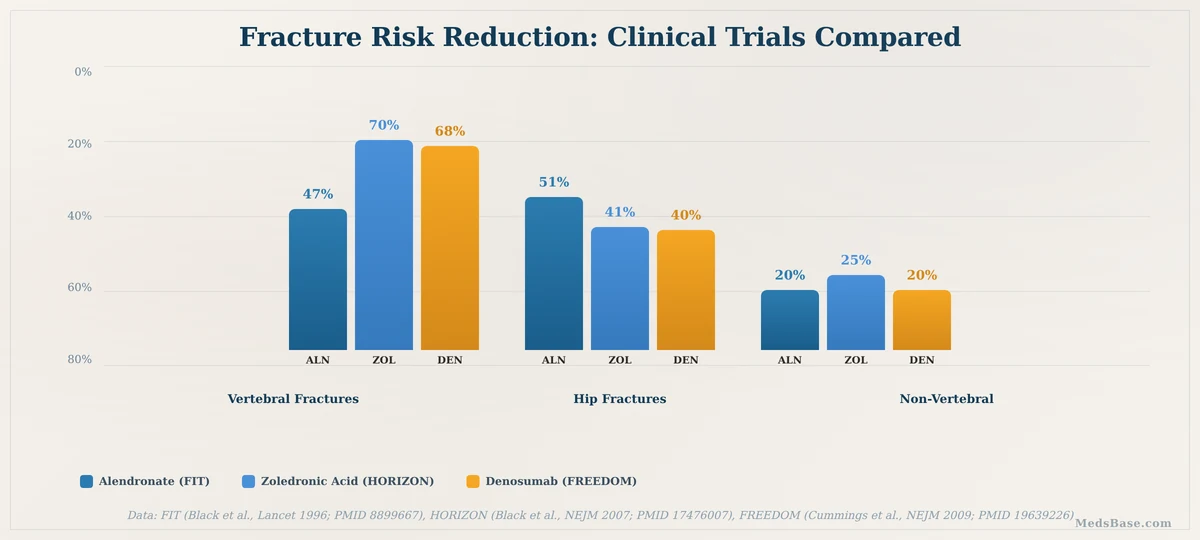
- Caption: Clinical trial data comparing fracture risk reduction across bisphosphonates and denosumab. Data from FIT (alendronate), HORIZON (zoledronic acid), and FREEDOM (denosumab) trials.
- Loading: `loading=”lazy”` ; Dimensions: 1200×800
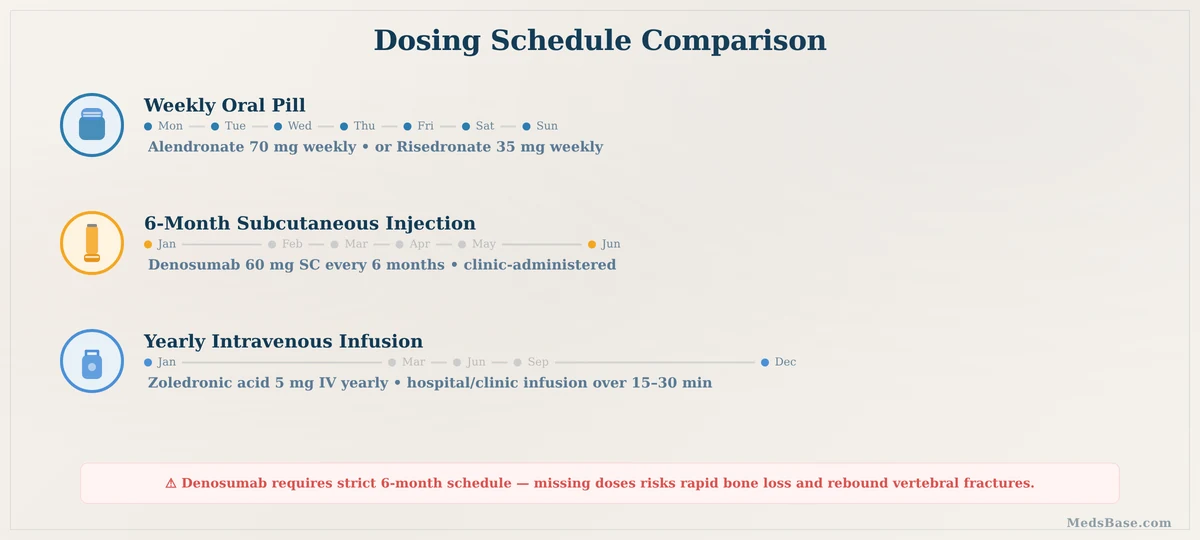
5. Dosing Schedule Timeline
- Brief: “Dosing Schedule Comparison — Weekly Pill vs 6-Monthly Injection vs Yearly IV”
- Composition: Three horizontal timeline bars stacked vertically. Top: “Alendronate” — weekly pill icons across a 6-month span (~26 pills). Middle: “Denosumab” — single injection icon every 6 months (2 injections per year). Bottom: “Zoledronic Acid” — single IV drip icon once per year. Timeline spans 12 months for easy comparison. Icons distinguishable at thumbnail size.
- Keywords: bisphosphonates dosing schedule, denosumab 6-month injection, osteoporosis treatment frequency comparison, alendronate weekly, zoledronic acid yearly
- Filename: osteoporosis-treatment-dosing-schedule-comparison.jpg ; Alt text: Timeline comparing osteoporosis treatment dosing schedules — weekly alendronate pills vs 6-monthly denosumab injection vs yearly zoledronic acid IV
- Caption: Dosing frequency varies significantly: alendronate requires weekly self-administration, denosumab needs clinic visits every 6 months, and zoledronic acid requires an annual IV infusion.
- Loading: `loading=”lazy”` ; Dimensions: 1200×628
6. Decision Flowchart
- Brief: “Making the Right Treatment Decision — Osteoporosis Medication Flowchart”
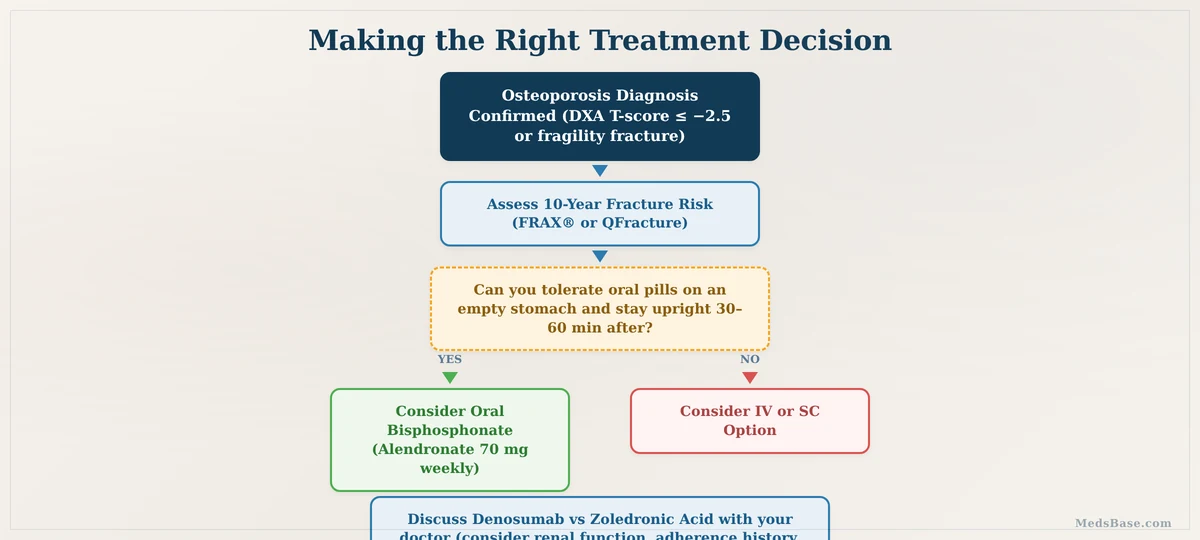
- Composition: Decision flowchart with rounded rectangles and directional arrows. Start: “Osteoporosis Diagnosis” diamond: “Can you tolerate oral medication?” Yes branch leads to “Consider oral bisphosphonates”, No branch leads to “Consider IV bisphosphonate or denosumab” diamond: “Can you commit to 6-monthly injections long-term?” Yes: “Denosumab may be suitable”, No: “Consider IV zoledronic acid”. Final box: “Discuss options with your doctor”. Clean #f4f8fb background, decision diamonds in #2c7cb0.
- Keywords: osteoporosis treatment decision flowchart, how to choose bisphosphonates or denosumab, osteoporosis medication selection guide
- Filename: osteoporosis-treatment-decision-flowchart.jpg ; Alt text: Decision flowchart for choosing between bisphosphonates and denosumab — from diagnosis through treatment selection
- Caption: This decision framework helps guide the conversation with your doctor about which osteoporosis treatment aligns with your health profile and lifestyle.
- Loading: `loading=”lazy”` ; Dimensions: 800×1000
7. Author/Reviewer Badge
- Brief: “Medically Reviewed” badge near author bio
- Composition: Theme-injected — do not produce custom image. Flatsome theme handles this via post meta.
- Keywords: N/A
- Filename: N/A ; Alt text: N/A
- Caption: N/A
- Loading: N/A ; Dimensions: N/A
URL Slug bisphosphonates-vs-denosumab
Full Article Body
You’ve just been handed a diagnosis of osteoporosis and two medication pamphlets — one for bisphosphonates, a class of drugs that has been the backbone of osteoporosis treatment for decades, and one for denosumab, a newer biologic that works through an entirely different mechanism. Your doctor says both can reduce your fracture risk. But which one is actually right for you? That choice — the bisphosphonates vs denosumab question — is one of the most important treatment decisions you’ll make after an osteoporosis diagnosis. Research suggests both classes are highly effective at preventing fractures, but they differ dramatically in how they work, how often you take them, what side effects you might experience, and what happens if you stop. This guide walks you through every evidence-backed difference so you can have a genuinely informed conversation with your doctor. But first — the one safety concern that most patients never hear about until it’s too late is the risk of rapid bone loss if certain treatments are stopped abruptly. We’ll cover exactly what that means and who it affects later in this article.
Key Takeaways
- Bisphosphonates (alendronate, risedronate, zoledronic acid) bind directly to bone and slow its breakdown — they are first-line for most patients and available as generic pills making them the most affordable option.
- Denosumab (Prolia) is a twice-yearly injection that blocks RANKL, a protein that signals bone-removing cells — it’s typically reserved for high-risk patients or those who cannot tolerate oral bisphosphonates.
- Both reduce vertebral fractures by 60-70% in clinical trials, but denosumab may offer slightly greater protection against non-vertebral fractures in direct comparison studies.
- Dosing schedules differ dramatically: weekly or monthly pills vs a 6-monthly injection vs a yearly IV infusion — your lifestyle and ability to adhere matters enormously.
- The denosumab rebound risk is real: missing or stopping denosumab can trigger rapid vertebral bone loss and multiple fractures — this is the single most important safety differentiator you need to understand.
- Cost varies widely: generic alendronate costs significantly less than brand-name denosumab, but international pharmacy options may narrow that gap substantially.
Table of Contents
- Understanding Bisphosphonates vs Denosumab — What Each Treatment Actually Is
- How Do Bisphosphonates and Denosumab Work Inside Your Bones?
- Efficacy Comparison: Fracture Prevention Data from Landmark Trials
- Dosing Schedule: Pills vs Injections vs IV — What Fits Your Life?
- Side Effect Comparison — Including the Denosumab Rebound Risk You Must Know About
- Who Should Choose Bisphosphonates vs Denosumab — and Who Should Avoid Each
- Cost and Access: What You’ll Actually Pay — and How to Save
- Frequently Asked Questions About Bisphosphonates vs Denosumab
- The Bottom Line: Making Your Decision
Bisphosphonates vs Denosumab: Which Osteoporosis Treatment Is Right for You?
Understanding Bisphosphonates vs Denosumab — What Each Treatment Actually Is
When doctors discuss bisphosphonates vs denosumab, they are comparing two entirely different approaches to protecting your bones. Bisphosphonates are a class of small-molecule drugs that bind directly to bone mineral and are taken orally or intravenously. They include alendronate (Fosamax), risedronate (Actonel), ibandronate (Boniva), and zoledronic acid (Reclast). These medications have been used for over three decades and are the most widely prescribed osteoporosis treatments worldwide. Denosumab, sold under the brand name Prolia, is a monoclonal antibody — a biologic drug — that works as a RANKL inhibitor. It’s given as a subcutaneous injection every six months. Unlike bisphosphonates, denosumab does not bind to bone; instead, it circulates in the bloodstream and blocks the signal that tells your body to create bone-removing cells called osteoclasts. For patients exploring treatment options, medications like alendronate (available as generic brands including Osteofos) represent the most accessible entry point into osteoporosis care.
Understanding the bisphosphonates vs denosumab distinction matters because your choice affects everything from how often you take medication to what happens if you ever need to stop. Both drug classes are antiresorptive — meaning they slow bone breakdown rather than building new bone — but the way they achieve this and the consequences of interrupting treatment are fundamentally different.
How Do Bisphosphonates and Denosumab Work Inside Your Bones?
To understand the bisphosphonates vs denosumab mechanism debate, it helps to think of your bones as a construction site that never shuts down.
Your skeleton is constantly remodelling itself. Two types of cells run the operation: osteoclasts, which act like a demolition crew breaking down old bone, and osteoblasts, which work like a construction crew laying down new bone. In healthy young adults, demolition and construction are balanced. In osteoporosis, the demolition crew works overtime while the construction crew falls behind — your bones thin out, weaken, and become vulnerable to fractures.
Bisphosphonates work by attaching directly to the bone surface. When an osteoclast arrives to start demolition, it swallows the bisphosphonate molecule along with the bone mineral. The bisphosphonate then disrupts the osteoclast’s internal machinery, causing the cell to stop working and die. Think of it as planting tiny “stop” signs on the bone surface that only the demolition crew can see. Because bisphosphonates have a very long half-life in bone — alendronate can remain in the skeleton for over 10 years — the protective effect persists even after you stop taking the medication, though it does diminish gradually.
Denosumab takes an entirely different approach. Rather than killing osteoclasts directly, it blocks the signal that creates them in the first place. Your body produces a protein called RANKL (Receptor Activator of Nuclear Factor Kappa-B Ligand), which binds to receptors on osteoclast precursor cells and tells them to mature into active osteoclasts. Denosumab is a monoclonal antibody that mops up RANKL before it can deliver that signal — no RANKL signal, no new osteoclasts, no bone breakdown. The key difference in the bisphosphonates vs denosumab mechanism comparison is reversibility: denosumab does not stay in bone. Once your next injection is due, the drug clears from your system and bone resorption can rebound rapidly — sometimes overshooting pre-treatment levels.
Research Spotlight: The Bone Remodelling Cycle
A full bone remodelling cycle takes approximately 3-6 months. Bisphosphonates reduce osteoclast activity within days of the first dose, which is why even short-term treatment shows measurable bone density increases. Denosumab suppresses bone resorption markers by over 80% within 24 hours of the first injection, reaching maximum suppression by day 3, according to pharmacokinetic data from the FREEDOM trial programme (Cummings et al., 2009). This rapid onset makes denosumab particularly useful for patients at immediate high fracture risk.
Efficacy Comparison: Bisphosphonates vs Denosumab for Fracture Prevention
When you compare bisphosphonates vs denosumab purely on fracture prevention, both drug classes deliver substantial protection. However, the data comes from different trials with different populations, which makes direct comparisons nuanced. Here’s what the landmark studies show:
| Drug | Vertebral Fracture Reduction | Hip Fracture Reduction | Non-Vertebral Fracture Reduction | Key Trial |
|---|---|---|---|---|
| Alendronate (oral, weekly) | ~47% | ~51% | ~20% | FIT trial (Black et al., 1996) |
| Risedronate (oral, weekly/monthly) | ~41% | ~40% | ~33% | VERT/HIP trials (Harris et al., 1999; McClung et al., 2001) |
| Zoledronic Acid (IV, yearly) | ~70% | ~41% | ~25% | HORIZON trial (Black et al., 2007) |
| Denosumab (SC injection, 6-monthly) | ~68% | ~40% | ~20% | FREEDOM trial (Cummings et al., 2009) |
What this means for you: in the bisphosphonates vs denosumab efficacy comparison, both drug classes reduce vertebral fractures by 40-70% — that translates to a very real reduction in the painful spinal compression fractures that can rob you of height and mobility. Hip fracture reduction ranges from 40-51% across the studied drugs. Head-to-head trials are limited, but the FRAME and ARCH studies comparing denosumab with other treatments suggest that while vertebral fracture reduction is broadly similar, denosumab may achieve faster bone density gains in the first year of treatment — a meaningful advantage if you’re starting from a very low bone density or have already sustained a fracture.
For a deeper look at how bisphosphonates work across all formulations, see our complete bisphosphonates guide.
Dosing Schedule: Pills vs Injections vs IV — What Fits Your Life?
The practical reality of the bisphosphonates vs denosumab decision often comes down to how the medication fits into your daily routine. The dosing schedules differ so dramatically that your lifestyle and preferences may steer the choice as much as clinical factors do.
| Treatment | Route | Frequency | Administration |
|---|---|---|---|
| Alendronate (Fosamax, Osteofos) | Oral tablet | Once weekly | Self-administered at home |
| Risedronate (Actonel) | Oral tablet | Once weekly or once monthly | Self-administered at home |
| Ibandronate (Boniva) | Oral tablet | Once monthly | Self-administered at home |
| Zoledronic Acid (Reclast, Zoldria) | IV infusion | Once yearly | Healthcare setting (15-30 min infusion) |
| Denosumab (Prolia) | Subcutaneous injection | Every 6 months | Healthcare setting (clinic visit) |
Oral bisphosphonates come with an important practical rule you must follow every single time: take the tablet first thing in the morning on an empty stomach with a full glass of plain water, and remain upright for at least 30-60 minutes afterward without eating or drinking anything else. This isn’t just a suggestion — skipping this routine significantly increases the risk of oesophageal irritation and reduces absorption. For the right person, a once-weekly pill is the most convenient option. For others, remembering that rigid morning routine becomes a daily source of friction.
Injectable and IV options eliminate the GI hassle entirely. Denosumab requires a clinic visit every six months for a quick subcutaneous injection — similar to a vaccine shot. Zoledronic acid involves a once-yearly IV infusion that takes about 15-30 minutes. Zoledronic acid is available as a generic option for patients who prefer the yearly schedule. The trade-off in the bisphosphonates vs denosumab dosing comparison is that injection-based treatments require you to reliably attend appointments — and with denosumab, every single dose is critical. A delay of even a few months can trigger the rebound bone loss effect we address in the side effects section below.
Side Effect Comparison — Including the Denosumab Rebound Risk You Must Know About
Every osteoporosis medication carries potential side effects. Comparing bisphosphonates vs denosumab on safety means understanding not just what can go wrong, but which risks are reversible, which are rare, and which are deal-breakers for certain patients.
| Side Effect | Bisphosphonates | Denosumab | Severity |
|---|---|---|---|
| GI irritation / oesophagitis | Common with oral forms (10-20%); rare with IV | Not applicable (injection route) | Mild–moderate for oral; manageable with proper dosing technique or switching to IV/injectable |
| Osteonecrosis of the jaw (ONJ) | ~1-10 per 100,000 patient-years (osteoporosis doses) | ~2-30 per 100,000 patient-years | Rare but serious; risk increases with dental procedures, cancer-dose equivalents (much higher), and treatment beyond 3-5 years |
| Atypical femoral fractures (AFF) | ~3-50 per 100,000 patient-years; increases with long-term use (>5 years) | ~1-3 per 100,000 patient-years (limited long-term data) | Rare; risk must be weighed against the 100-200 fractures these drugs prevent per 1,000 patients treated |
| Hypocalcemia | Uncommon with adequate calcium/vitamin D intake | More common than with bisphosphonates; vitamin D deficiency increases risk substantially | Preventable with calcium and vitamin D supplementation; screen levels before starting |
| Acute-phase reaction | ~10-40% after first IV zoledronic acid dose (flu-like symptoms for 1-3 days) | Rare | Transient; treat with paracetamol; rarely recurs with subsequent doses |
| Rebound bone loss after stopping | Gradual, manageable (drug remains in bone for years) | Rapid and potentially severe — multiple vertebral fractures reported within months of missed or delayed doses | Critical differentiator: denosumab rebound fractures are a well-documented safety concern requiring a transition plan to another antiresorptive if treatment is stopped |
The Denosumab Rebound Effect — Why It Matters So Much
This is the safety issue that makes the bisphosphonates vs denosumab decision fundamentally different from comparing, say, two brands of the same drug. When you stop taking bisphosphonates, the drug remains bound in your bone and wears off gradually over years. When you miss or stop denosumab, the drug clears from your bloodstream within months. The osteoclasts that have been suppressed come roaring back — sometimes more actively than before treatment. The result can be rapid bone loss, particularly in the spine, and multiple vertebral compression fractures occurring within a span of months.
Research published in a post-hoc analysis of the FREEDOM trial and its extension documented a significant increase in vertebral fracture rates after denosumab discontinuation, particularly among patients who had received more than two doses before stopping (Cummings et al., 2018). This means denosumab is not a treatment you can casually stop or take breaks from. If you start denosumab, you need a long-term plan — either continuing treatment indefinitely or transitioning to a bisphosphonate under medical supervision when you decide to stop.
For patients who value flexibility or who may struggle to keep clinic appointments, this single fact often tips the bisphosphonates vs denosumab decision decisively in favour of bisphosphonates.
Who Should Choose Bisphosphonates vs Denosumab — and Who Should Avoid Each
The bisphosphonates vs denosumab decision is never one-size-fits-all. Here is a patient-centred breakdown of who benefits most from each approach.
Who Is This For: Bisphosphonates
- First-line treatment candidates — most clinical guidelines, including NHS guidance, recommend bisphosphonates as the initial treatment for postmenopausal osteoporosis (NHS osteoporosis treatment guide).
- Those who want maximum flexibility — you can stop oral bisphosphonates without a medical emergency because the drug depot in your bone provides a gradual safety buffer.
- Cost-conscious patients — generic alendronate is one of the most affordable prescription medications in any therapeutic category.
- Patients with adequate kidney function — bisphosphonates are renally cleared and generally contraindicated when eGFR falls below 30-35 mL/min.
- Patients with normal oesophageal anatomy — those with Barrett’s oesophagus, achalasia, or severe GERD may not tolerate oral forms and should consider IV options instead.
Who Is This For: Denosumab
- Patients who cannot tolerate oral bisphosphonates — if you’ve tried alendronate and experienced severe heartburn, oesophageal pain, or difficulty with the dosing routine, denosumab bypasses the GI tract entirely.
- Patients with impaired kidney function — unlike bisphosphonates, denosumab is not cleared by the kidneys, making it safer for patients with reduced renal function — though the risk of hypocalcemia is higher in this group.
- High-risk patients who want rapid protection — denosumab suppresses bone resorption within 24 hours and produces measurable bone density gains faster than oral bisphosphonates.
- Those who can reliably commit to 6-monthly clinic visits — the every-6-month schedule works brilliantly for organised patients but disastrously for those who miss appointments.
- Patients willing to commit to long-term treatment or a supervised transition plan — this is non-negotiable because of the rebound fracture risk.
Who should avoid each: patients with hypocalcemia (uncorrected) should not take either class until calcium levels are normalised. People with oesophageal stricture or a history of bariatric surgery should avoid oral bisphosphonates. Dental surgery or invasive dental procedures planned in the near future warrant careful discussion with both your doctor and dentist because of the ONJ risk, particularly with IV bisphosphonates or denosumab. If you are interested in an alternative to both these drug classes, compare bisphosphonates with raloxifene, a SERM that works through yet another mechanism.
Cost and Access: What You’ll Actually Pay — and How to Save
Cost is often the elephant in the room when discussing bisphosphonates vs denosumab, and it’s one where the difference is stark. Generic alendronate is widely available and costs significantly less than brand-name denosumab in most markets. A month’s supply of generic alendronate can cost a fraction of what a single denosumab injection costs, depending on your location and insurance coverage.
| Treatment | Approx. Annual Cost (US, uninsured) | Generic Available | Administration Cost |
|---|---|---|---|
| Alendronate (generic, 70 mg weekly) | $50-200/year (varies by source) | Yes — multiple manufacturers | None (self-administered) |
| Zoledronic Acid (generic, 5 mg yearly) | $200-800/year | Yes — including Zoldria | Infusion clinic fee ($50-200) |
| Denosumab (Prolia, 60 mg twice yearly) | $1,500-3,000+/year | No — brand only (biosimilars in development) | Clinic administration fee ($30-100 per visit) |
For patients paying out of pocket, the bisphosphonates vs denosumab cost difference can be the deciding factor. Generic bisphosphonates sourced from WHO-GMP-certified manufacturers through international pharmacies offer substantial savings. See available osteoporosis treatments to compare current options and pricing. Whatever your choice, discuss cost openly with your doctor — they may not raise it first, but it’s a legitimate factor in treatment adherence. A medication you can afford to take consistently is infinitely more effective than one you ration or skip.
Related Reading
- Bisphosphonates for Osteoporosis: 7 Essential Facts & Safety Guide — deeper coverage of bisphosphonate types, long-term safety data, and drug holidays
- Raloxifene vs Bisphosphonates: 7 Essential Differences for Bone Health — how SERMs compare to bisphosphonates for postmenopausal bone protection
Frequently Asked Questions About Bisphosphonates vs Denosumab
Which is better: bisphosphonates or denosumab?
There is no single “better” answer in the bisphosphonates vs denosumab comparison — the right choice depends on your individual fracture risk, kidney function, tolerance for oral medication, ability to keep injection appointments, and budget. Bisphosphonates (particularly alendronate) are recommended as first-line treatment by most guidelines because they have decades of safety data, are available as affordable generics, and carry no rebound fracture risk if stopped. Denosumab is generally reserved for patients who cannot tolerate bisphosphonates, have impaired kidney function, or are at very high fracture risk where the rapid onset of bone protection is valuable. Discuss your personal risk profile with your doctor to determine which option aligns with your situation.
What are the side effects of denosumab vs bisphosphonates?
The side effect profiles differ meaningfully. Oral bisphosphonates commonly cause gastrointestinal irritation (heartburn, oesophageal pain) in 10-20% of users — this is largely avoidable with proper dosing technique or switching to IV formulations. Denosumab avoids GI effects entirely but carries a higher risk of hypocalcemia and, critically, a well-documented risk of rapid bone loss and multiple vertebral fractures if doses are missed or treatment is stopped without transitioning to another antiresorptive. Both drug classes carry a very rare risk of osteonecrosis of the jaw (ONJ) and atypical femoral fractures (AFF), though these occur at rates far lower than the fractures these medications prevent.
Is denosumab safer than bisphosphonates?
Denosumab is not inherently safer than bisphosphonates — the safety comparison depends entirely on the patient. For someone with severe GERD or Barrett’s oesophagus, denosumab is safer because it avoids oesophageal exposure entirely. For someone with unreliable access to healthcare or a history of missed appointments, bisphosphonates are safer because the rebound fracture risk from missed denosumab doses is a genuine emergency. Both medications have excellent safety records when used appropriately, with adverse events occurring in a small minority of patients. The safety calculus is individual, not universal.
How often do you take denosumab vs bisphosphonates?
The dosing frequency is one of the clearest differences in the bisphosphonates vs denosumab comparison. Oral bisphosphonates are taken once weekly (alendronate, risedronate) or once monthly (risedronate, ibandronate). Denosumab is given as a subcutaneous injection once every six months at a clinic. IV zoledronic acid, a bisphosphonate option, is administered as an infusion once per year. Your choice may come down to whether you prefer the routine of a weekly pill at home or the scheduled reliability of a clinic visit every six months — but remember that missing a denosumab appointment has consequences far beyond a gap in treatment.
Can you switch from bisphosphonates to denosumab?
Yes, you can switch from bisphosphonates to denosumab, and this is a common clinical scenario. The most frequent reason for switching is intolerance to oral bisphosphonates — persistent GI side effects that do not resolve with proper dosing technique. The transition should be medically supervised: your doctor will assess how long you have been on bisphosphonates, your current bone density, and your fracture risk before deciding the timing of the first denosumab dose. There is typically no washout period needed. This is one of the most common trajectories in osteoporosis care — starting with a generic bisphosphonate and moving to denosumab if needed.
What happens if you miss a dose of denosumab?
Missing a denosumab dose by more than a month is a medical concern — not an emergency, but something that requires prompt attention. Bone resorption markers begin rising within 2-3 months of a missed dose, and vertebral bone loss accelerates quickly. Studies indicate that delays beyond 2-3 months increase the risk of rebound vertebral fractures. If you realise you’ve missed a dose, contact your doctor immediately to get the injection as soon as possible. Do not simply skip the dose and wait for the next scheduled one. This is why doctors emphasise the importance of keeping a denosumab calendar and scheduling your next appointment before leaving the clinic.
Does denosumab build bone better than bisphosphonates?
Denosumab tends to produce larger bone mineral density (BMD) increases at the lumbar spine in the first 1-3 years compared to oral bisphosphonates, but the fracture prevention data is broadly comparable. In the FREEDOM extension study, denosumab-treated patients achieved mean lumbar spine BMD increases of approximately 18-21% over 10 years of continuous treatment — higher than typically seen with oral bisphosphonates. However, BMD gains are a surrogate marker; the clinical endpoint that matters is fracture prevention. On that measure, both drug classes reduce vertebral fractures by 60-70% and hip fractures by 40-50% in high-risk populations.
How long can you safely stay on bisphosphonates vs denosumab?
Bisphosphonates are typically prescribed for 3-5 years of continuous treatment, after which a “drug holiday” of 1-3 years is often considered for patients whose fracture risk has moderated. This is possible because the drug remains in bone and continues providing partial protection. Denosumab, by contrast, has no drug holiday — its effects are rapidly reversible, and stopping treatment without transitioning to a bisphosphonate carries the rebound fracture risk discussed above. The FREEDOM extension study supports denosumab use for up to 10 years with sustained efficacy and no new safety signals, but the key is that treatment must be continuous.
The Bottom Line: Making Your Decision
The bisphosphonates vs denosumab conversation ultimately distills to this: both drug classes are highly effective at preventing osteoporotic fractures, but they suit different people and different lives. Bisphosphonates — particularly generic alendronate — are the first-line choice for most patients because they work, they’re affordable, they’re backed by over 30 years of safety data, and you can stop them without a crisis if needed. Denosumab shines for patients who cannot tolerate oral bisphosphonates, have impaired kidney function, are at very high fracture risk and need rapid protection, or simply prefer a twice-yearly clinic visit over a weekly pill routine — provided they can commit to never missing a dose and having a long-term plan.
The most important action you can take after reading this bisphosphonates vs denosumab comparison is to talk to your doctor with specific questions: “Given my kidney function and fracture risk, which class do you recommend? What’s my long-term plan if I start denosumab? Can we trial a generic bisphosphonate first?” These are questions that transform a passive prescription into an active, informed treatment decision.
If you’re ready to explore your options, see alendronate availability at MedsBase, or read our complete guide to bisphosphonates for a deeper dive into dosage forms, drug holidays, and long-term safety considerations. For those considering non-bisphosphonate alternatives, our raloxifene vs bisphosphonates comparison covers a third treatment pathway worth discussing with your doctor.
Medical Disclaimer
This article is for informational purposes only and does not constitute medical advice. The content is not intended to be a substitute for professional medical diagnosis, treatment, or guidance. Always consult your doctor or another qualified healthcare provider before starting, changing, or stopping any osteoporosis medication. Treatment decisions must be individualised based on your bone density results, fracture risk assessment, kidney function, calcium and vitamin D levels, dental health, and personal medical history. Never discontinue denosumab without medical supervision due to the documented risk of rebound vertebral fractures. Medications mentioned are available through licensed pharmacies; consult your healthcare provider for a prescription.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.