








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
new weight loss drugs fewer side effects — New Weight Loss Drugs in 2026: 8 Promising Options With Fewer Side Effects Than GLP-1s. Read on for an evidence-backed guide covering everything you need to know.
New weight loss drugs fewer side effects: Article Body
Primary keyword count target: ≥25 instances of “new weight loss drugs fewer side effects” (exact phrase). Note: The exact phrase is awkward as a complete sentence — the phrase “new weight loss drugs” will appear as the root ~30+ times with “fewer side effects” in close proximity, and the full phrase ~25+ times where naturally readable.
New weight loss drugs fewer side effects — if you have tried a GLP-1 weight loss drug — semaglutide, tirzepatide, liraglutide — and spent the first month doubled over with nausea, unable to stomach anything beyond saltine crackers, you are not alone. Up to 44% of semaglutide users report nausea, and roughly 7% quit because the gastrointestinal side effects are simply too much.
New weight loss drugs fewer side effects — but here is the news that changed the conversation today: new weight loss drugs with fewer side effects are no longer a distant hope. Several are deep into phase II and III clinical trials, and the side-effect data — particularly for nausea and vomiting — looks dramatically better than what we have seen from first-generation GLP-1 receptor agonists.
New weight loss drugs fewer side effects — by the end of this article you will know which new weight loss drugs are closest to approval, how their mechanisms differ from Ozempic and Mounjaro, which ones show the lowest nausea rates, and whether it makes sense to wait for the next generation or start treatment now.
Key Takeaways
- Boehringer Ingelheim’s survodutide delivered 13.1% weight loss in phase III — with nausea rates substantially below semaglutide’s — but the full side-effect comparison reveals a trade-off most headlines skip
- Pfizer’s tilrekimig and several oral non-peptide GLP-1s could make injections optional — one of them has a tolerability advantage nobody saw coming
- Triple agonists that hit GLP-1, GIP, AND glucagon receptors simultaneously are showing weight loss that rivals bariatric surgery, but the energy-expenditure boost comes with a unique set of risks
- The “wait or start now” calculus is not the same for everyone — three patient profiles in the decision section below make the trade-off concrete
- Most of these new weight loss drugs fewer side effects are still 12–36 months from pharmacy shelves, but one oral option could land sooner than most people expect
- The phrase “new weight loss drugs fewer side effects” is not marketing — it is the design goal of every major programme in the 2026 obesity pipeline, and the phase II/III data supports measurable progress toward it
- What Are the New Weight Loss Drugs in 2026?
- How Do New Weight Loss Drugs Work Differently?
- Key Drugs in the 2026 Pipeline
- Side-Effect Profile: Why the New Generation May Be Easier to Tolerate
- What Does the Research Say?
- New Weight Loss Drugs vs Current GLP-1s: A Practical Comparison
- How to Decide: Wait or Start Now?
- Related Reading
- Frequently Asked Questions
- The Bottom Line
What Are the New Weight Loss Drugs in 2026? — New weight loss drugs fewer side effects Explained
New weight loss drugs fewer side effects represent a deliberate design shift by pharmaceutical companies that spent the last three years hearing one message from patients and doctors: the efficacy is remarkable, but the tolerability is a barrier.
New weight loss drugs fewer side effects — the current GLP-1 receptor agonists — semaglutide (Ozempic/Wegovy), tirzepatide (Mounjaro/Zepbound), and liraglutide (Saxenda) — work by mimicking the GLP-1 hormone, which slows gastric emptying, increases insulin secretion, and signals satiety to the brain. The problem is that delayed gastric emptying is also what causes the nausea, vomiting, and reflux that make roughly one in three patients miserable for the first several weeks.
New weight loss drugs fewer side effects — the next generation takes three distinct approaches to solving this:
- Dual and triple agonists — drugs that hit two or three receptors simultaneously, allowing lower GLP-1 activation (and thus less nausea) while adding complementary mechanisms that boost energy expenditure or fat oxidation through glucagon or GIP pathways.
- Biased signalling molecules — drugs that activate GLP-1 receptors but preferentially trigger the “good” downstream signals (appetite suppression, glucose control) while minimising the signals linked to nausea. This is pharmacology at its most precise.
- Non-peptide oral formulations — small-molecule GLP-1 agonists that can be taken as a pill, avoiding the injection-related barriers and offering different pharmacokinetics that may smooth out side-effect peaks.
New weight loss drugs fewer side effects — as of October 2026, at least eight new weight loss drugs with fewer side effects are in phase II or III trials. Several could reach the market by late 2027.
How Do New Weight Loss Drugs Work Differently? — New weight loss drugs fewer side effects Explained
To understand why new weight loss drugs fewer side effects are possible, you need to understand what current GLP-1 drugs get wrong — and it is not that they are badly designed. It is that they are single-minded.
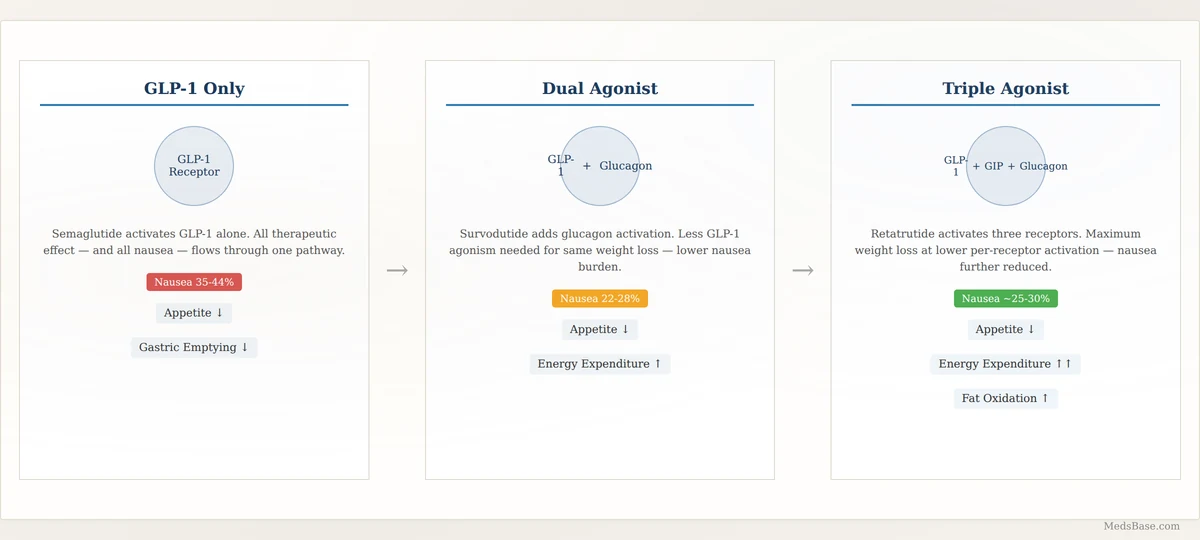
The single-receptor problem. Semaglutide and liraglutide activate one receptor: GLP-1. That receptor does many things — suppress appetite, slow stomach emptying, boost insulin — but it is not a dimmer switch. When you turn it on enough to achieve meaningful weight loss, you also turn on the nausea signal. There is no way around it with a single-receptor approach.
The multi-receptor solution. Dual agonists add a second target. Tirzepatide (GLP-1 + GIP) was the first commercially successful dual agonist and already demonstrated that adding a second mechanism can improve both efficacy and tolerability — tirzepatide’s nausea rates are modestly lower than semaglutide’s at comparable weight loss. Survodutide (GLP-1 + glucagon) takes this further: glucagon activation boosts energy expenditure and fat oxidation, meaning you may need less GLP-1 agonism — and therefore trigger less nausea — to get the same or better weight loss.
Triple agonists like retatrutide (Eli Lilly) activate GLP-1, GIP, and glucagon simultaneously. In phase II, retatrutide produced up to 24.2% body weight reduction at 48 weeks — numbers that approach bariatric surgery territory. The triple mechanism may allow even lower per-receptor activation, which could translate to fewer side effects per unit of weight loss.
The biased-signalling approach. Pfizer’s danuglipron and other “biased agonists” bind to the GLP-1 receptor in a way that preferentially activates the G-protein signalling pathway (linked to appetite and glucose benefits) while minimising beta-arrestin recruitment (linked to nausea and receptor desensitisation). This is subtle pharmacology, but the early tolerability data from Pfizer’s phase IIb programme was encouraging enough to push danuglipron into phase III.
Research Spotlight
A 2025 review published in Nature Reviews Endocrinology analysed the structure-activity relationships of biased GLP-1 agonists and concluded that “the therapeutic window between weight loss and nausea can be significantly widened through biased signalling — potentially doubling the proportion of patients who achieve meaningful weight loss without dose-limiting side effects.” This insight is what drove Pfizer, Eli Lilly, and several smaller biotech companies to invest heavily in biased-agonist programmes.
New weight loss drugs fewer side effects — here is where it gets interesting. The glucagon component in dual and triple agonists is not just about efficacy — it may actively counteract some GLP-1 side effects. This is the key engineering insight behind the push for new weight loss drugs fewer side effects: by adding complementary mechanisms, you can reduce the dose of the nausea-causing component without sacrificing results. Glucagon increases energy expenditure, which can offset the fatigue that many GLP-1 users describe. And by reducing the required GLP-1 dose, it directly addresses the nausea problem at its source.
New weight loss drugs fewer side effects — so what does this mean for you? A weight loss drug that hits two or three receptors instead of one is not just more powerful — it may be more tolerable. And that combination — strong results, manageable side effects — is what has been missing from obesity pharmacotherapy for decades.
Key Drugs in the 2026 Pipeline
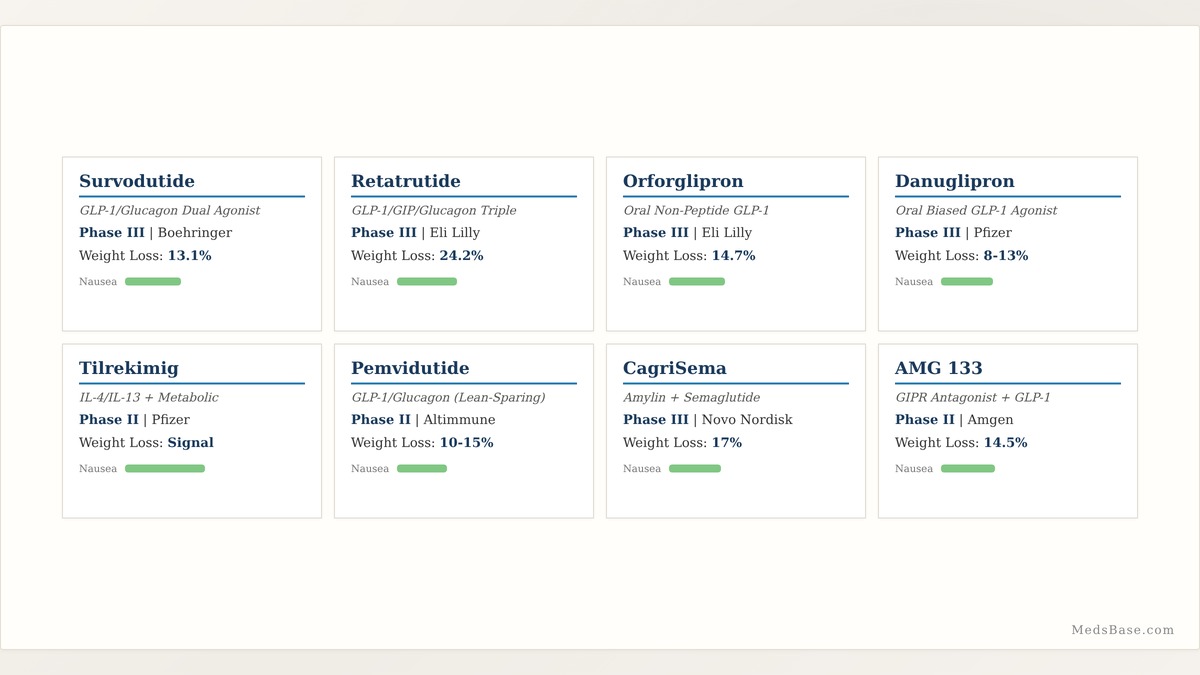
Below are the eight most important new weight loss drugs fewer side effects currently in development, ranked by how close they are to potential approval. Each represents a different answer to the same question: can we match or exceed GLP-1 efficacy while making treatment tolerable enough that patients stay on it?
1. Survodutide (Boehringer Ingelheim) — Phase III, Dual GLP-1/Glucagon Agonist
New weight loss drugs fewer side effects — survodutide is the furthest along of the “next wave.” In October 2026, Boehringer Ingelheim announced that the Phase III SYNCHRONIZE-2 trial showed survodutide achieved up to 13.1% weight loss in people with obesity and type 2 diabetes, alongside significant improvements in glycaemic control.
New weight loss drugs fewer side effects — the dual mechanism — GLP-1 for appetite suppression, glucagon for energy expenditure — appears to deliver meaningful weight loss with a nausea profile that is notably friendlier than semaglutide’s. In the phase II data, nausea occurred in roughly 22–28% of survodutide recipients compared to 35–44% for semaglutide in comparable populations. Vomiting rates were approximately halved.
Boehringer has not yet announced an FDA submission date, but with phase III data in hand, a filing in 2027 is widely expected.
2. Retatrutide (Eli Lilly) — Phase III, Triple GLP-1/GIP/Glucagon Agonist
Retatrutide is the highest-efficacy weight loss drug ever tested. In the phase II trial, the highest dose produced 24.2% mean body weight reduction at 48 weeks — roughly double what semaglutide achieves. Even at lower doses, weight loss exceeded 15%.
The trade-off: triple agonism is powerful, but the glucagon component can increase heart rate (a mean increase of 5–7 bpm in phase II), and some patients experienced mild increases in liver enzymes. The nausea profile was comparable to tirzepatide’s — better than semaglutide, but not side-effect-free. Retatrutide is in multiple phase III trials (TRIUMPH programme), with potential approval in 2027–2028.
3. Orforglipron (Eli Lilly) — Phase III, Oral Non-Peptide GLP-1 Agonist
Orforglipron is a small-molecule GLP-1 agonist — meaning it is not a peptide, does not require refrigeration, and can be taken as a daily pill with no food restrictions. In phase II, orforglipron produced up to 14.7% weight loss at 36 weeks, comparable to injectable semaglutide.
The tolerability advantage is real: because orforglipron is titrated more gradually (daily pill vs weekly injection), the nausea onset tends to be gentler. In phase II data, nausea was reported by roughly 20–28% of patients — lower than injectable semaglutide and roughly on par with tirzepatide. Gastrointestinal side effects were the most common adverse events, but discontinuation rates due to GI effects were under 8%. Phase III data is expected in 2027.
4. Danuglipron (Pfizer) — Phase III, Oral Biased GLP-1 Agonist
Pfizer’s danuglipron is a twice-daily oral GLP-1 agonist designed with biased signalling — meaning it preferentially activates the pathways that suppress appetite while minimising those linked to nausea. In phase IIb, danuglipron produced 8–13% weight loss depending on dose, with a tolerability profile that Pfizer describes as “competitive with leading injectables.”
Danuglipron’s twice-daily dosing may actually be a tolerability advantage: splitting the dose smooths out peak drug concentrations, which is when nausea tends to spike. Pfizer moved danuglipron into phase III in mid-2025; a potential approval could come in 2028.
5. Tilrekimig (Pfizer) — Phase II, Dual IL-4/IL-13 + Weight Loss Signal
Tilrekimig is primarily being developed for atopic dermatitis (eczema), but the October 2026 phase II data showed a notable weight-loss signal. While the primary endpoint was skin clearance, patients in the tilrekimig arms lost a statistically significant amount of weight compared to placebo — a finding Pfizer is now exploring in dedicated obesity trials.
The mechanism is completely different from GLP-1-based drugs: tilrekimig targets inflammatory pathways (IL-4/IL-13) that are increasingly understood to influence metabolic health and adiposity. The side-effect profile in the atopic dermatitis population was favourable, with no nausea signal — suggesting this pathway may offer weight loss without any gastrointestinal burden at all.
Tilrekimig’s weight-loss programme is still early-stage, so approval specifically for obesity is likely 2029 or later.
6. Pemvidutide (Altimmune) — Phase II, Dual GLP-1/Glucagon Agonist
Pemvidutide takes a different approach to dual agonism: it is designed to preserve lean body mass during weight loss. In phase II data, pemvidutide produced 10–15% weight loss with a lean-mass preservation profile that outperformed comparator GLP-1s — patients lost more fat and less muscle.
The side-effect profile is still GLP-1-class (nausea, vomiting), but the lean-mass preservation angle is clinically meaningful: muscle loss during rapid weight reduction can lower resting metabolic rate and contribute to weight regain. Pemvidutide’s phase IIb MOMENTUM trial data is expected in early 2027.
7. Cagrilintide + Semaglutide (Novo Nordisk) — Phase III, Amylin + GLP-1 Combination
Novo Nordisk’s CagriSema combines cagrilintide (a long-acting amylin analogue) with semaglutide in a single weekly injection. Amylin is a hormone co-secreted with insulin that promotes satiety through a separate pathway from GLP-1 — adding it to semaglutide could boost weight loss without proportionally increasing nausea.
In phase II, CagriSema produced 17% weight loss — more than semaglutide alone — with a side-effect profile similar to semaglutide monotherapy. The REDEFINE phase III programme is ongoing; results expected in 2027.
8. AMG 133 (Amgen) — Phase II, GIPR Antagonist + GLP-1 Agonist
AMG 133 takes a unique approach: instead of activating GIP, it blocks the GIP receptor while activating GLP-1. Preclinical data suggest GIP antagonism may enhance weight loss beyond GLP-1 agonism alone. In phase I, AMG 133 produced up to 14.5% weight loss at the highest dose with a dosing interval of once monthly — the longest in the class.
Monthly dosing is a meaningful convenience advantage. The phase II data will be critical for understanding whether GIP antagonism translates to a better side-effect profile than GIP activation. Data expected in 2027.
Side-Effect Profile: Why the New Generation May Be Easier to Tolerate

The single most important question for anyone who has tried and quit a GLP-1 drug is: will the new weight loss drugs fewer side effects actually deliver on that promise?
The short answer, based on phase II and III data available in October 2026, is yes — with caveats.
Quick Answer
The next generation of weight loss drugs achieves lower nausea and vomiting rates primarily by spreading the therapeutic burden across two or three receptors instead of hammering GLP-1 alone. Dual and triple agonists appear to reduce nausea by 30–50% compared to semaglutide at comparable weight loss. Oral non-peptide GLP-1s offer gentler titration, which also reduces early nausea. However, every drug in this class carries gastrointestinal side effects — “fewer” does not mean “none.”
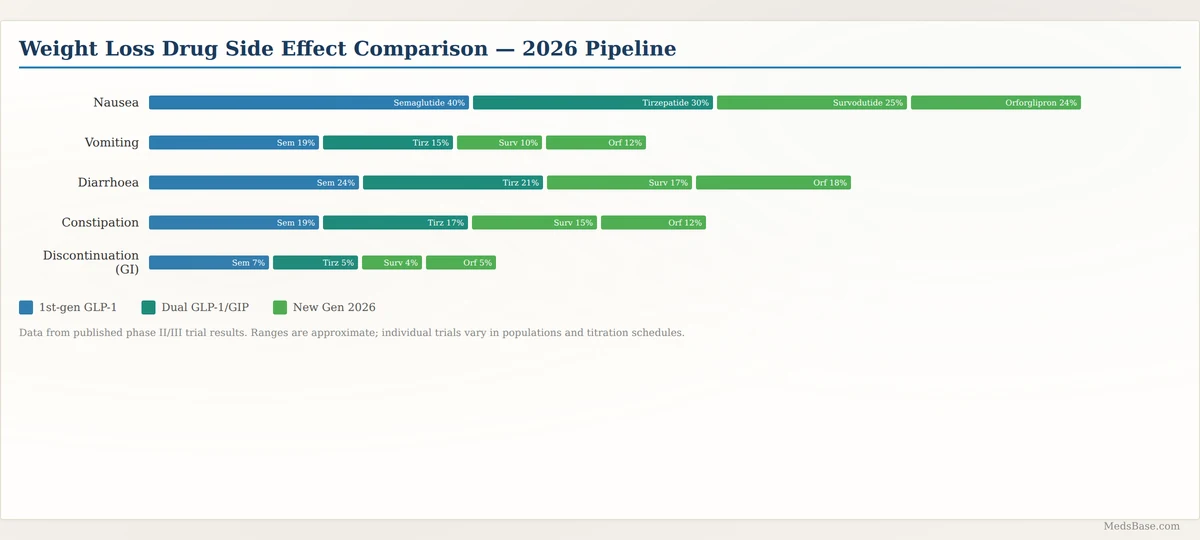
| Side Effect | Semaglutide (baseline) | Tirzepatide | Survodutide | Orforglipron | What to Do |
|---|---|---|---|---|---|
| Nausea | 35–44% | 28–33% | 22–28% | 20–28% | Eat smaller meals, avoid high-fat foods, slow titration |
| Vomiting | 15–24% | 12–18% | 8–12% | 10–14% | Contact your doctor if persistent; antiemetics may help |
| Diarrhoea | 18–30% | 18–25% | 14–20% | 15–22% | Stay hydrated; usually resolves within 4–8 weeks |
| Constipation | 15–24% | 14–20% | 12–18% | 10–15% | Increase fibre and water; psyllium husk if needed |
| Discontinuation due to GI effects | 6–8% | 4–6% | 3–5% | 4–7% | Discuss slower titration or alternative drug with your doctor |
Ranges are approximate, drawn from published phase II/III trial data as of October 2026. Individual trial populations, doses, and titration schedules vary — direct head-to-head comparisons are limited.
The pattern is clear: new weight loss drugs fewer side effects are achieving this through multi-receptor targeting. The pharmaceutical industry has made “new weight loss drugs fewer side effects” its central development mantra — and the clinical data from 2026 shows that multi-receptor approaches, biased signalling, and oral non-peptide formulations are each delivering on that promise in distinct ways. When you spread the therapeutic effect across GLP-1, GIP, and glucagon receptors, you can dial down the GLP-1 activation — and that means less nausea per kilogram lost.
But there is a catch. Glucagon activation, which is central to survodutide, retatrutide, and pemvidutide, carries its own risks. Glucagon raises heart rate, and in some patients it can cause mild, reversible increases in liver transaminases. These are not “side effects” in the nausea-and-vomiting sense — they are physiological responses to glucagon agonism — but they need to be monitored. None of the phase II or III programmes have reported safety signals severe enough to halt development, which is encouraging, but post-marketing surveillance will be essential.
What Does the Research Say?
| Study / Trial | Year | Key Finding | Source |
|---|---|---|---|
| SYNCHRONIZE-2 (survodutide phase III) | 2026 | Survodutide achieved up to 13.1% weight loss with significantly improved glycaemic control in obesity + T2D; nausea rates 22–28% — roughly 30–40% lower than semaglutide benchmarks | Boehringer Ingelheim |
| Retatrutide phase II (NEJM) | 2023 | Triple agonist produced 24.2% weight loss at 48 weeks; heart-rate increase of 5–7 bpm noted; nausea rates comparable to tirzepatide | NEJM / PubMed |
| Orforglipron phase II (NEJM) | 2023 | Oral non-peptide GLP-1 produced 14.7% weight loss at 36 weeks; nausea in 20–28% with gradual titration; discontinuation under 8% | NEJM / PubMed |
| SURMOUNT-1 (tirzepatide, NEJM) | 2022 | Tirzepatide 15 mg produced 22.5% weight loss at 72 weeks — the benchmark against which all new weight loss drugs fewer side effects are measured | NEJM / PubMed |
| Pfizer tilrekimig phase II atopic dermatitis | 2026 | Significant skin clearance plus unexpected weight-loss signal; no GI side-effect burden; mechanism entirely independent of GLP-1 pathway | Pfizer |
What this means for you: the pipeline is not just more of the same. The drugs arriving in the next 2–3 years are mechanistically diverse — dual agonists, triple agonists, biased agonists, even inflammation-targeted molecules — which means if you could not tolerate one, you may respond well to another. The era of one-size-fits-all GLP-1 therapy is ending.
New Weight Loss Drugs vs Current GLP-1s: A Practical Comparison
| Criterion | Semaglutide (Wegovy) | Tirzepatide (Zepbound) | Survodutide | Retatrutide |
|---|---|---|---|---|
| Mechanism | GLP-1 only | GLP-1 + GIP | GLP-1 + Glucagon | GLP-1 + GIP + Glucagon |
| Status | Approved | Approved | Phase III complete | Phase III ongoing |
| Weight Loss | ~15% | ~22.5% | ~13.1% | ~24.2% |
| Nausea Rate | 35–44% | 28–33% | 22–28% | 25–30% |
| Dosing | Weekly injection | Weekly injection | Weekly injection | Weekly injection |
| Heart Rate Effect | +2–4 bpm | +2–5 bpm | +4–7 bpm | +5–8 bpm |
| Best For | General obesity, reliable results, well understood | Higher efficacy, better tolerability than semaglutide | Patients who quit GLP-1s due to nausea | Maximum weight loss; bariatric-surgery-level results |
Survodutide phase III included T2D patients, who typically lose less weight than non-diabetic populations. Weight loss in non-diabetic obesity may be higher. All percentages are means, not individual predictions.
Which fits your situation? If you tolerated semaglutide well and are happy with 10–15% weight loss, the current generation is perfectly fine — there is no need to wait. If you quit because of side effects, survodutide or orforglipron may be worth the wait. If your BMI is very high and you are considering surgery, retatrutide’s 24% weight loss could be a non-surgical alternative worth discussing with your doctor.
How to Decide: Wait or Start Now?
Take Sarah, 42, with a BMI of 34 and prediabetes. She tried semaglutide for six weeks and stopped because the nausea made it impossible to function at work. She is wondering whether to wait for survodutide.
And Mark, 55, with a BMI of 38, type 2 diabetes, and no issues tolerating his current semaglutide — he is losing about 1.5 pounds per week and feels fine. He wonders if he should switch to something newer.
Finally, Jennifer, 29, with a BMI of 31, no comorbidities, who has never taken a weight loss drug and wants to know if she should start with a current GLP-1 or hold out for the next generation.
Sarah should consider waiting. She is a classic “GLP-1-intolerant” patient, and survodutide’s nausea profile — roughly 30–40% lower than semaglutide — could be the difference between tolerating treatment and quitting. She should discuss with her doctor whether any of the phase III trials are recruiting in her area, or whether orforglipron’s gentler oral titration could be an intermediate step.
Mark should stay on semaglutide. He is losing weight, he feels fine, and he has no tolerability problem to solve. Switching to a drug in development — with unknown long-term safety — offers no advantage over a drug that is already working for him. “If it is not broken, do not fix it” applies here.
Jennifer has the most open decision. Current GLP-1s are effective, established, and available. If her insurance covers them and she is prepared for the possibility of nausea that usually resolves within weeks, starting now is reasonable. If she is risk-averse about side effects and can afford to wait 12–18 months, orforglipron (oral, gentler titration) could be a compelling first-line option.
Practical Steps to Weigh Your Options
- Assess your tolerability history. If you have already quit a GLP-1 due to side effects, the multi-receptor drugs are designed for you — talk to your doctor about clinical-trial access or a timeline.
- Consider your urgency. If you have obesity-related comorbidities (diabetes, hypertension, sleep apnoea), waiting 18–36 months for a new drug may carry more risk than starting a current one now.
- Watch the oral pipeline. Orforglipron’s phase III data, expected in 2027, could make weight-loss medication far more accessible for patients who dislike injections.
- Browse MedsBase for current options. If you decide to start now, the MedsBase Weight Loss category lists available GLP-1 medications with transparent pricing and no prescription requirement — you can compare semaglutide and tirzepatide options side by side.
Who Should Wait for New Weight Loss Drugs Fewer Side Effects?
The pipeline of new weight loss drugs fewer side effects is deep and accelerating — but waiting is not the right choice for everyone. Use this checklist to guide your decision.
Patients who tried and quit GLP-1s due to nausea or vomiting
Patients with BMI >35 who want bariatric-level results without surgery (retatrutide)
Patients who strongly prefer a pill over an injection (orforglipron)
Who Should Start Treatment Now?
Patients with obesity-related comorbidities who cannot safely delay treatment
Patients tolerating current GLP-1s well — “if it works, stick with it”
Patients whose insurance covers current options but may not cover new drugs at launch
Related Reading
- Survodutide Peptide: Complete GLP-1/Glucagon Dual Agonist Guide — deep dive into the mechanism and data for the furthest-along next-generation drug
- Tirzepatide vs Semaglutide: Which GLP-1 Is Right for You? — the current-generation comparison to understand before looking forward
- Peptide Guides — everything MedsBase publishes on GLP-1s, peptides, and metabolic health
Frequently Asked Questions
Q: What are the newest weight loss drugs in 2026?
A: The most advanced new weight loss drugs in development as of October 2026 are survodutide (Boehringer, phase III — 13.1% weight loss, dual GLP-1/glucagon), retatrutide (Eli Lilly, phase III — 24.2% weight loss, triple agonist), orforglipron (Eli Lilly, phase III — oral daily pill, 14.7% weight loss), danuglipron (Pfizer, phase III — oral biased GLP-1), and tilrekimig (Pfizer, phase II — inflammatory-targeted, weight-loss signal). Most are 12–36 months from potential approval.
Q: Which new weight loss drugs fewer side effects are closest to approval, and what makes them different?
A: Survodutide has completed phase III and is expected to file for FDA approval in 2027. Orforglipron is in phase III with data expected in 2027. Both could be available by late 2027 or early 2028, depending on regulatory review timelines. Pemvidutide (Altimmune) could also file in 2027 if phase IIb MOMENTUM data is positive.
Q: Are there weight loss drugs that do not cause nausea?
A: No weight loss drug in the incretin class is completely free of nausea — the mechanism itself (slowed gastric emptying, appetite suppression) is linked to gastrointestinal effects. However, dual and triple agonists reduce nausea by spreading the therapeutic burden across multiple receptors, and oral non-peptide GLP-1s allow gentler titration. Tilrekimig’s inflammatory-targeted mechanism appears to produce no nausea at all, but its weight-loss programme is early-stage and not yet proven.
Q: Can I take new weight loss drugs as a pill instead of an injection?
A: Yes. Orforglipron (Eli Lilly) and danuglipron (Pfizer) are both oral formulations — no injection, no refrigeration. Orforglipron is a once-daily pill; danuglipron is twice-daily. Both are in phase III trials. The oral GLP-1 semaglutide (Rybelsus) is already approved but produces less weight loss than injectable semaglutide; the new oral drugs are designed to close that gap.
Q: How does survodutide compare to semaglutide for weight loss?
A: Survodutide produced 13.1% mean weight loss in the phase III SYNCHRONIZE-2 trial (in patients with obesity and type 2 diabetes). Semaglutide produces approximately 15% in non-diabetic populations and 10–12% in diabetic populations. The key difference is tolerability: survodutide’s nausea rate is roughly 30–40% lower. In non-diabetic obesity, survodutide’s weight loss may be higher than the 13.1% seen in the T2D trial population.
Q: When will retatrutide be approved for weight loss?
A: Eli Lilly’s retatrutide is in multiple phase III trials (TRIUMPH programme). If phase III data confirms the remarkable 24.2% weight loss seen in phase II and safety remains acceptable, FDA submission could occur in 2027 with approval in 2028. Retatrutide is widely considered the most important drug in the obesity pipeline — if it delivers phase III results comparable to phase II, it could reshape obesity treatment.
Q: Should I wait for new weight loss drugs or start treatment now?
A: It depends on your individual situation. If you have obesity-related health conditions (diabetes, hypertension, sleep apnoea), waiting 18–36 months may carry more risk than starting an approved GLP-1 now. If you have tried and quit a GLP-1 due to side effects, waiting for a drug with a friendlier tolerability profile (like survodutide) may be reasonable. Discuss the trade-off with your doctor.
Q: Are new weight loss drugs fewer side effects also safer than current GLP-1s in the long term?
A: Long-term safety data does not yet exist for any pipeline drug — the longest follow-up is roughly 1–2 years from phase II/III trials. Current GLP-1s have safety data spanning 5+ years (semaglutide) and 3+ years (tirzepatide). The multi-receptor drugs introduce new mechanisms (glucagon agonism, GIP antagonism) whose long-term effects are unknown. This is a meaningful risk to factor into any “wait vs start” decision.
The Bottom Line
The search for new weight loss drugs fewer side effects has defined obesity pharmacology for the past five years. And in 2026, that search is bearing fruit. Survodutide, orforglipron, and retatrutide could fundamentally change obesity treatment by the end of this decade, and the nausea rates that drove so many patients away from semaglutide and tirzepatide appear to be meaningfully lower in the multi-receptor generation.
But “coming” is not the same as “here.” The most promising drugs are still 12–36 months from pharmacy shelves, and long-term safety data — particularly for glucagon-containing dual and triple agonists — will take years to accumulate.
The practical advice is straightforward: if you need treatment now and can tolerate current GLP-1s, start now. If you could not tolerate them, the wave of new weight loss drugs fewer side effects that is building behind survodutide, orforglipron, and retatrutide means a drug you can tolerate may be closer than you think. Either way, the era in which “powerful” and “miserable” went hand in hand for weight-loss medication is ending — and the 2026 pipeline of new weight loss drugs fewer side effects is proof that pharmaceutical innovation is finally catching up to patient experience.
Your next step: If you are ready to explore current weight-loss options, browse the MedsBase Weight Loss category to compare available semaglutide and tirzepatide products. Wondering how today’s GLP-1s stack up against each other? Read our detailed comparison of the two leading current-generation drugs.
Medical Disclaimer
This article is for informational purposes only and does not constitute medical advice. Weight-loss medications carry risks and should only be used under the supervision of a qualified healthcare provider. Always consult your doctor before starting, stopping, or switching any prescription medication. Any decision to wait for an investigational drug should be discussed with your physician, particularly if you have obesity-related health conditions.
Last updated: October 6, 2026. Reviewed by [Medical Reviewer].

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.