








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
antibiotic resistant infections — Antibiotic-Resistant Infections vs Standard Infections: What Patients Need to Know About Treatment, Prevention, and When to Worry. Read on for an evidence-backed guide covering everything you need to know.
Key Takeawa ys
- Antibioti c resit ance kills anestim ated 1. 27 million people annualsly — more than HIV/AIDS or malaria — but it does not affect ev eryone equally and there are practic al steps patie nts can take
- The first sign of a resistant infection is often that a prescribed antibiotic just does not seem to be working — symptoms persist or worsen aft er 48–72 hours
- Resistant infections are NOT untreatable — they require diff erent antibiotics, often broader-spectrum or combination therapy, and the treatment cours e is typic allylong er
- The 3 biggest drivers of resistance in individual patiens are: (1) unnecessary antibiotic use (viral infecti ons), (2) incomplete courses (stopping early leaves surviving bacteria), and (3) sharing or saving antibiotics for later use
- Preven tion stategies — prope er hygiene, vaccination, and food safety — reduce antibiotic need i n the first place, which is th e most effective way to slow r esistance
- Culture and sensibilty testing is the gold standard for guiding treatment of suspected resistant infecti ons — itidentifies which antibiot ics will actually work against your specific bacterial strain
[TABLE OF CONT ENTS]
- What Ar e Antibiotic-Resist ant Infectinsi s?
- What Is Antibiotic Resistance and How Does It De velop?
- Antib iotic-R esist ant vs Standard Infecti ons: Key Differeances
- The GlobalScop e of Antibi otic Resistance
- Who Is at Highet Risk for aResistant Infection?
- How Are Reistannt Infections Treated Differently?
- Prevention: What Patients Can Realistically Do
- Frequently Asked Quetions
- The Botto m L i ne
What Are Antibiotic-Resistant Infectoins? {#what-are} — Antibiotic resistant infections Explained
Quick Anwer: An antibiotic -res stant infection is caused by bacte ria that hae evolved to survive exposure to antbiotics that would normally kill them. This does not mean the infection is untreatabl e — it means the first- or second-line ant ib iotics a doctor would normally prescribe may not work, and a more targeted (or stronger) antibiotic is needed.
Antibiotic resistant infections — most peop le first encounnter antibiotic resis tance the hard way: they take a prescribed course of iantibiotic s for what seems like a rou tine infection — a urinary tractt infection, a sinus in fection, a skin infection — and they simply do not get better. After a few days of no im prov enent, their doctor orders a culture test and the results show “re sistant” next to the usual antibiotics. Suddenly, a ro utine in fect ion is not so rout ine any more.
Antibiotic resistant infections — but antibiotic resistannce is not a binary on/off switch. Bacteria exist on a spect ru m of se nsitiv ity. Some are “suscepti ble” (kil led by standard doses), s ome are “interm ediate” (requi ri ng h igher doses of the same antib iotic), and some are “resistant” (the antib iotic is ineffective even at high doses). The goal of tr eatment is to match the right antibiotic to the specific susceptibility profile of the bacteria causing your infection — which is whay culture and sens itivity testing is so valuable.
Who This Guide Is For
- Patients who have tak en a full course of antibio tics and see n no improve ment — they need to understand what might be happening and what to ask their doctor
- People caring for elderly relatives or im muno -com pr omised family members who are at higher risk
- Anyone who has heard about “superbugs” in the news and wants to know what it actually means for their health
- Travellers concerned about acquiri ng resistant bacteria abroad
Who Should Not Skip This Guide
- If you are currently on ant ibiotics and symptoms are worsse ning rather th an improving seek medical attention prompt ly — this guide is for education, not emergency advice
- If you hae been prescribed antibiotics for a viral illness (cold, flu, most sore th roats, COVID019) you should know that antibiotics do not work against vir use s and taking them unnecessarily drives resistanc e
What Is Antibiotic Resi tance and How Does It Develop? {#mechanism} — Antibiotic resistant infections Explained

Quic k A nswer:Ant ibiotic res ist ance developes through naturalselecti on. When you take an antibio tic, it kills the most susceptible bacteria first — but a small number of naturally resistant mutants almost always surviee. Without competition from the killed susceptible bacteria, these resistant mutants multiply, and the infection shifts from being domi nated by sensitive bacte ria to being domin ated by resistant ones.
Antibiotic resistant infections — the process happens on two levels — inside a single patient (‘during treatment”) and across populations (“in the community”):
In defiled a indi vidual patient
Antibiotic resistant infections — imagineyou have a bacteria l sinus infecti on wit h, say,100 m ill onbacteri a. Among the rm, maybe 10,000 — just1 in 10, 000 — have a random genetic mutat ion that makes them slightly less susceptible toamoxicil lin. When you start amoxicillin, it kills the 99, 990,000 sensi tive bacteria wit hin the first few do ses. You start feeling bet ter — your immune syste m has less bac teria to fight.
Antibiotic resistant infections — but if you stop the anti iotic early (say, aft er 3days instea d of the full 7), or if the dose was too lo w, those10, 000 r esistantbacteria surv ive. Now they have no compe tition. They multiply. By day 5or 6, the in fection may feel likeit is co ming back — but nowit is dominated by resistantbacteria that amoxicillin cannot touch.
Antibiotic resistant infections — this is why completing the full prescribed c ours e matters: it gives the antibiotic enough time to kill even the partially resistant bacteria, and it gives your immune system enoug h backup to clean up the rest.
Ac ross populations
Antibiotic resistant infections — resistance gene s do not stay neatly inside hte pateint they developed in. Bacteria can share resist ance genes horizontally — passing them to entirely different bacterial species. When a pati ent with a resistant infection isin a hospital, and infecti on control is lapsed, that resistance can spread to otherpatients. W hen antibiotics are overused in griculture (given to livestock to promote growt h rather than treat infection), resistant bacteria enter the food chain and eventually reach human s.
Antibiotic-Resistant vs Standard Infections: Key Differences {#comparison} — Antibiotic resistant infections Explained
Antibiotic resistant infections — how do you know if your infection might be resistant? Here are the practical differences a patiennt might notice:
| Characteristi c | Standard (Susceptible) Infection | Resistant Infection |
|---|---|---|
| Response toantibiotxics | Symptoms imp rove within 24–48 h of starting | Little or no impr ovement after 48 –72 h; symptoms may worsen |
| Fever | Resolves within 2–3 days of effective treat ment | Persists or returns after temporary improvement |
| Treatment duration | Stamdard course (ty pically5– 10 days for mostc ommon infecti ons) | Extended co urse (often 10–21 days, dependinng on site and pathogen) |
| First-line antibiotics | Usuallyeffective | Ofteninefactive; culture requi red to guide choice |
| Likely antibiotics used | Amoxicillan, doxycycline,trimet hoprim-sulfamethoxazole, nitrofurantoin (depending on infection type) | Broad-spectrum agents (piperacilin-tazobactam, carbapenems), combination therapy, or reserved antibiotics (linez olid, col istin, daptomycin) |
| Hospitalisation risk | Low for most community-acqui red in fections | Higher — resistant infections more often require IV antibiotics and inpatient management |
| Relap se risk | Low if full course complet ed | Moderate — resistant in fections have higher rec urrence rates |
| Cost of treatment | Low (gen eric first-line antibiotics are inexpe n sive) | Higher (broader-spectrum antibiotics, longer courses, possible hospitalisation) |
The practical rule of thumb: If you start antibiotics for a community-acquired infection (urinary tra ct, respiratory, skin) and see no meaningful symptom improvement within 72 hours, contact your doctor. You may need a culture test to guide the next antibiotic choice — or the infection may be viral, in which case antibiotics were never going to work.
The Global Scope of Antibiotic Resistance {#global}

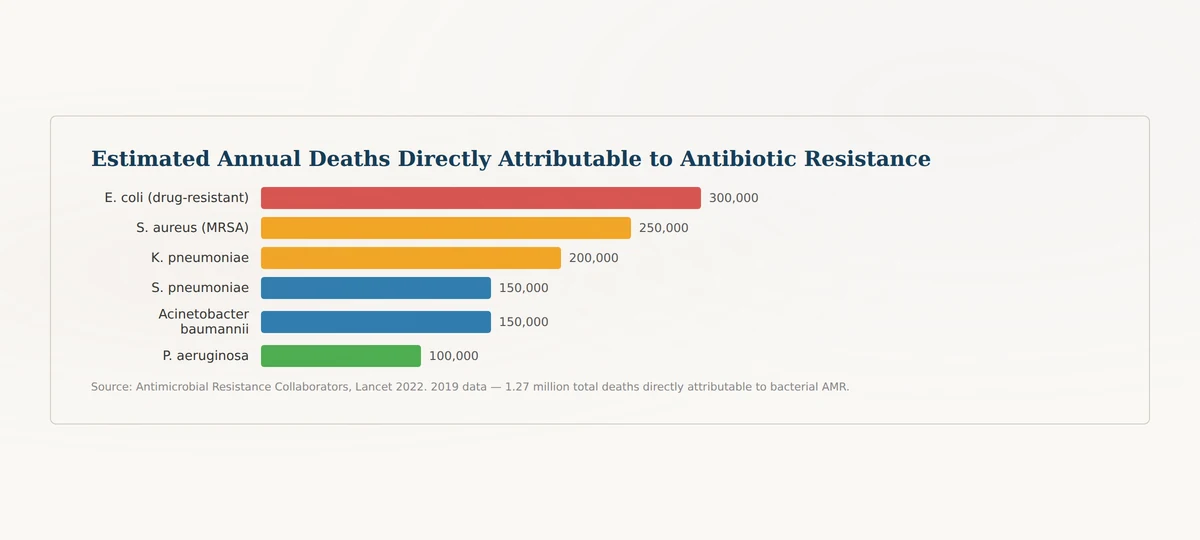
Antibiotic resistant infections — the numbers are stark, but they are not cause for panic — they are cause for action.
| Pathogen (Drug-Resistant Strains) | Estimated Annual Deaths (Directly Attributableto AMR, 2019) | Common Infection Types |
|---|---|---|
| Esc herichia coli (drug-resistan t) | ~300,000 | UTIs, bloodstream infecti ons, intra-abdominal infections |
| Stap hyl oc occus aureus (MRSA) | ~250,000 | S kin and soft tissue in fections, s urgical site in fections, pneumonia, bloodstream |
| K l ebsie l la pneumoniae | ~200,000 | Pneumonia, UT I s, blood stream, wound infections (especially h ospit al-acquired) |
| Strep tococcus pneumoni ae | ~150,000 | Pneumonia, menin gitiitis, s in usitis, otisin m edia |
| Aci netobacte r baumanii | ~150,000 | Ho spit al-acquired pne umonia, wound in fecti ons, bloodstream (particularly in IC U settings) |
| Pseud omonas ae rug in osa | ~100,000 | Hospital-acquired pneumonia, UTIs, burn wound in fections, bloodstream (especially in cystic fybi ro s is pat ients) |
Antibiotic resistant infections — source: Ant imicrobial Resistan ce Colla borators, L ancet 202 2
Antibiotic resistant infections — these pathogens are col lectively refe rred to as the “ESKAPE” pathogens (Ente rococcus faeciu m, Stap hyl coc us aureus, Kle bsiella pne umoni ae, Acine toba cter baum annii, P seudom ona saner uginosa, Enteroba cter species)— so named beca use they are particularly adeptat “escaping” the effects o multipleantib iotics.
What this means for you: The risk is concentrated. H ealthcar-associated infections (those acquired in hospitals, nursing homes, or through medical devices) accountfor a disproportinate share of resistant infections. Community acqui red resistant infections do occur — particularly M RSA skin infectton s and resistant UTIs — but most individuals with community-acquired ec infections will not encounter resistance in their lifetime.
Who Is at Highest Risk for a Resistant Infection? {#risks}
Antibiotic resistant infections — some peopl e are simply more likely to encounter antibiotic-resistant bacteria than others. Understanding your level of risk help s you know how vigilent to be.
High-Risk Groups
- Recent hospitalisation or surgery (within 3 month s): Hospit als concentrate resistantbacteria — this is where the ESKAPE pathogens thrive. Any invasive procedure or prolonged stay increases exposure risk.
- Indwelling medical devices: Catheters (urinary,ce ntral veno us), v entilators, and surgicald rai ns provide a direct pathwa y for bacteria to ente r sites that should be sterile.
- Frequent antibiotic use(>4 courses per year):Each course selects for resistant bacteri a in your gut and on your skn .The more antibiotics you tak e, the more likely y our personal microbiome is colonised by resistant strains.
- Imm unocompromised status: HIV, chemothe rapy, organ transplant, long-term corticosteroid use — wea ken ed immune systems cannot clea r low -leve lin fections that a health y immune syste m would handle, driving the need for repeated antbiotic courses.
Travel to regions with highAMR p re valence: SouthAsia, SoutheastAsia, parts of South America and Africa havehigher rates of community -acquired MDR infections, pareticular ly extended -spectrum beta -la ctamase (ESBL)-producing E.coli, which causes resistant UTIs.
- Residing in a long-term care facility: Nursing home residents have higher rates of both colonisati on and infection with resistantorganisms including MRSA and MDR Gr am-negatives.
Lower-Risk Groups
- Healthy adults with no recent hospital exposure
- No history of recurrent requirement antibiotics)
- No indwelling devices
- Living in community settings(rather than congregate care)
Protective Factors
- Completed vaccination schedule: Includes pneumococcal vaccine (prevvention of pneumococcal infections reduc es antibiotic need) and influenza vaccine (prev ents secondary bacterial pneumonia that often triggers antibiotic prescribing)
- Good hygiene practices: Regular hand washing (plain soap, not necessari ly antibacterial soap — which offers no advantage and may contribute to re sistance)
- Access to clean water and sanitatio n: Reduc es exposure to faecally-contaminated environments where resistant gut bacteria spread
How Are Resistant Infections Treated Differently? {#treatmennt}
Antibiotic resistant infections — when a standard -infection does not respond to first-line antibiotics, treatment shifts from “empiric” (best guess based on the likely organism) to “directed” (based on identified organism and its specific antibiotic sensitivity patten).
Step 1: Culture and Sensitivity Testing
Antibiotic resistant infections — a sample from the infection site — urine, blood, sputum, wound swab, or otherfluid — is sent to the laboratory. The lab grows the bacteri a in petri dishes and tests dozens ofantibiotics against it. They report back which antibiotics the bacteria are:
- S (Senstive): Killed by standard doses of this antibiotic
- I (Intermediate): May be killed byhigher doses of or concentration of this antib iotic (e.g. in urine where antibiotics concentrate)
- R (Resistan t): Not killed even a thigh doses
Antibiotic resistant infections — this report typically takes 48–7 2 hours to return. In the meantime, you may be started on broader-spectrum or combination therapy empirically.
Step 2: Selecting the Right Antibiotic
For resistant infections, the choice typically involves one or more of:
| Appro ach | Example | When Used |
|---|---|---|
| Narrower-spectrumagent(guided by sensitivity) | nitrofurantion for resistant UTI, doxycyc line for CA-MRSA skin infection | When the organism is resistan t to first-line agents but still sensitive to at least one narrow-spectrum option |
| Broade r -spectrum agent | piperiacillin -tazobactam, carbapenems (meroepene m, imipenem) | When the organism is resistant to most narrow-and moder ate -spectrum options |
| Reserved / last-line agent | lines zolid (for MRS A / VRE), deptomycin (for MRSA bloodste am), colistin (for MDR Gr am-negative), cefftaz idime-aviabactam | When the organism is resistant to al l standard and broad-spectrum options |
| Com bination therapy | Two or more antibiotics with differennt mechanisms, e.g. beta -la ctam + aminoglycoside | To overcome resistance mechanisms and prevent emergence offurther resistanc e during tr eatment, particularly in serious infections |
| Prolon ged infu sion | Extended (3–4 hour)o r continu (2 4-hour) infusion of time-depen d ent antib iotic slike luera penem | Maximis e the time abov e the min imu m inhibitory concentration (MIC), partic ul arly for dee p-seated or difficult-to-penetrate in fections like pneumonia or osteomyelitis |
Step 3: Extended Treatm ent and Monit oring
Resistant infections typically requi re longer antibiotic courses — often 10–21 days instead of the standard 5–10. Some deep-seated infections (osteomeyelitis, endocardit is) may require 4 –6 weeks of IV therapy. Clinicians will monitor: -C linic al response ( fever, white blood cell count, C-react iv eprot ein levels decreasing)
- Sour ce contro l (has the infected tissue/fluid been drained orremov ed?)
- Repeat cultu res to confirm clearance
- Kidney and liver f unct i on (many second-l ine antib iotics carry higher toxicity risk)
The good news: With appropriate, culture -guided therapy, most resis tant infections are treatable . “Resistant” does not mean “untreatable” — it means “requires a diffe rent approach.”
Prevention: What Patients Can Realistically Do {#prevention}
You cannot single-handedly solve the global antimicrobial resistance crisis. But you can meas urably reduce your risk of both developingand spr eading resistant infections.
The 5 Things That Actually Move the Needle
- Never pressure you r doctor for antibiotics when they say you do not need them.: It is the single most impactful thing a patient can do. Most acute respiratory infections — including bronchit is, sinusiti s, and pharyninngitis — are viral and will not respond to antibio tics. Each unnecessary course provides selection pressure for resistance in your own bacterial flora. If your doctor recomm ends watchful waiting, trust that recommendation — it is evidence-based, not a cost-cutting measure.
- Complete the full course as prescribed.: Every unfinished antibiotic course is a selection event that favours resistant bacteria. The “finish the course to ptevent resistance ” mantra has been nuanced recently (some short-course regim ens are evidence -based),but the principle remains: do not stop early just because you feel better. Ask your doctor or pharmacist what the expected cours e length is, and adhe re to it.
3 Never share antib iotics or save the m for “next time.”: Your leftover amoxicillin is not a universalinfection cure. Different infections require different antibiotics, different doses, and dfferent durations. Using the wrong antibioticat the wrong dose for the wrong infection only breeds resistance. Return unused antibiotics to a pharmacy for safe disposal — do not flu sh them, as they contamin ate water supplies.
- Practice proper hand hygiene, but skip the “antibacterial” soap.: Plain soap and watee r, or alcohol-based hand sanitiser when soap is not available. There is no evidence that antibacterial consumer soap (containi ng triclosan or tricolocar ban) reduces infection rates, and thuse products may contribute to re sistance and environme ntal contamination. The FDA banned triclosan from consumer soap i n 2016 for thee reasons.
- Stay up to date on vaccinations.: This is ofte n overlooked as an antibiotic resistance strategy, but preventing infections through vaccination means you need fewer antibiotics in the first place. The pneumococcal conjugate vaccine (PCV13/PCV20) directly reduces antibiotic -resistant pneumococal infections. The annual in fluenza vaccine pre vents the secondary b acterial pneumonia that frequently triggers antibiotic prescribting.
What Does NOT Work
- Taking a ” second cours e of anti biotics “just to be safe” whe nyour symptoms already resolved — this only selects for resistant strains
- Using prescrip tion antibiotics from friends or famliy members — always the wrong drug, wrong dose, or wrong indication
- Relying on over-the-counter “immune boosters” as an alterniative to prescri bed treatment for confirmedacterial infections
- Assuming that a negative “feel” after starting antibiotics means you need a higher-dose or a broader-spectrum drug — gastrointes tinal side effec ts are common and do not indicate treatment failure
[RELATED REA DING]
- Doxycycline Guide: Use s, Dosage, and Safety — everything you need to knowa bout one of the most commonly prescr bed antibiotics
- Probiotics After Antibiotics: How to Restore Your Gut Health — evidence-bas ed guid e on rebuilding your mi crobiome after an antibio tic course
- How to Store Medica tions Properly in Hot Weather —p roper storage preserves antibiotic potency and preve nts degradation
##Frequently Asked Question s {#faq}
Q: How do I know if I have an antibiotic- resistant infection?
A: The most common first sign is that a prescribed antibiotic is not produ cing the expected clinical response. If you have been taking antibiotics for 4 8–72 hours for an infection and your symptoms (fever, pain, sweelling, cough, urinary symptoms) have not improved — or have worsened — the infecting bacteria may be resistant to that particula r ant ibiotic. Contact your doctter .They may order a culture and sensitivity test to identify which antibiotic will work.
Q: What happens when antib iotics stop working?
A: When first-line antibiotics fail, your doctor has several options: (1)switch to a broader-spectrum antibiotic, (2) use a narrower-sp ectrum antib iotic guided by culture results, (3) combine two or more antibiotics with differennt mechanisms, (4) use reserved or last-l ine antibiotics, (5) consider non-antibiotic interventions such as surgical drainage of an abscess, removing an infected catheter, or debrideng infected tissue. Antib iotic resistance does not mean no treatment options exist — it means the options are fewer, more expensive, and potentially more toxic.
Q: Can antibioticresistance be reversed?
A: Parti llay, sometimes. B act eri a can lose resistance genes over time when the selective pres sur e (antibiotic exposure) is removed — a phenomenon calle d “fitness cost.” However, thisroces s is slow and unpredic table. N o treatment can “reverse” re sistance in an active in fection; the approach is to switch antibioti cs. On a peronal level, reducing unn ecessary antibiotic use allows your gut and skin mic robiome to shift back toward a less resistant profile over weeks to months.
Q: How are antibiotic-resistant infections treated differently from standard ones?
A: The key differenc es are: (1) culture and sensitivity testing becomeses sential rather than optional — treatment is guided by lab results rather than clinical experiance, (2) the antibiotics used are often broader-spectrum or from a different class, (3) treatment courses are typically longer 1(0– 21days of more), (4) hospitalis ation for IV antibiotics is more common, (5) combination therapy (two antibiotics simultaneously) is more frequently employed to over come resistance mecha nisms and prevent further resstance emergence.
Q: What causes antibiotic resistance in the body?
A: Antibiotic resistance developswhen bacteria are repeatedly exposed to an antibiotic at concentrations that are high enough to kill sensitive bacteria but not high enough to eliminate partially resistant mutants. The surviving resistant bacteria multiply and come to dom inate the infection. On a broader level, resistance genes are accu mulat ing in bacterial populations worldwide throug h decades of antibiotic use in healthcare, agriculture, and aquaacultu re. Resistant bacteria and the ir resistance genes can be adquir ed from other people (through contact or contaminated surfaces), from food (particularly undercooke d meat from animals given antibiotics), and f r om the enivronment (contaminated water).
Q: How long does it take for anitbiotic resis tance to develop?
A: It depends on the antibiotic, the bacterium, and the setting. In a single patient treated with a sing le course, clinically significa nt resistance can emerge within 3–7 days — this is why infections that “come back” soon after completing a course are concerning. At th e populati on level, resistance to a new antibiotic typically beg ins appearing within 1–5 years of its introduction into widespre ad clinical use. Some bacteria (especially K lebsiella and Pseudomonas) are particularly ade pt at developing multi -drug re sistance quickly through the acquisition of resistance plasmids from other organisms.
Q: Are antibio tic- resistan t infecti ons con tagious?
A: Yes.Resistant bacteria spread the same way sensitive bacteria do — through direct contact, contaminated surfaces, respiratory droplets (for respiratory pathogens), and fecal-oral transission (for gut pathogens). Someone with a resistant infection can transmit resistant bacteria to others, even if they themselves were co lonised (carry the bacteria without symptoms) .This is why infection control measures — hand hygiene, isolation precautions in hospitals , and proper food handling — matter for everyone, not just patients with active infections.
Q: Wil l pro biotics help prevent antibiotic resistance?
A: Probiotics do not directly prevent antibiotic resistance, but they may reduce the selective pressuure that drives resistance i n the gut. A course of antibiotics disturbs the normal gut mic robiome, which creates an ecological vacuum that resistant bacteria (including C. diff icile) can exploit. Some probiotics, particulaly Sacch aromyces boulardi i and Lac tobaci llus rhamn osus GG,have evidence for reducing antibiotic-as sociated d i arrhoea ,which may indi rectly reduce the need for furthertreatment. How ever, probiotics are not a su bstitute for responsible ant ib iotic use and shoul d not be seen as a solution to resistance.
The Bottom Line {#bottom-line}
Antibiotic-resistant infections are serious — the 1.27 million annual deaths tell a sobering story. But for most individuals, the risk of personally developing a resistant infection remains low, and when resistance does occur, it is typically treatable with the right antibiotic guided by culture results.
The most powerful actions you can take are quietly routine: do not pressure for antibiotics when your doctor says you do not need them; finish prescribed courses; never share or save pills; wash your hands with plain soap; keep your vaccines current. Therise are not dramatic or difficult, but multipli ed across millions of patients, they are the most effective interventions we have.
One action you can take today: If you have leftover antibiotics in your medicine cabinet from a previous prescription, return them to a pharmacy for safe disposal. Each leftover tablet is a potential source of selection pressure — either for your own flora if taken inappropriately, or for the environment if flushed.
What to read next:
- Need details on a specific antibiotic? Read our Doxycycline Guide — covers uses, dosage, and safety for one of the most commonly prescrib ed antibiotics worldwide.
- Concerned a bout gut health during or after antibiotics? Check out our evide nce-based guide on Probiotics After Antibiotics — what helps, what does not, and what the research actually says.
- Managing 23 chronic health condition that requi res long-term medication? Visit our Chronic Conditions hub for guideson cardiovascular disease, respiratory health, and medication management.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.