








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
medications that affect REM sleep — Medications That Affect REM Sleep: 8 Drugs That May Be Stealing Your Deep Sleep. Read on for an evidence-backed guide covering everything you need to know.
Medications that affect REM sleep — you sleep seven or eight hours every night. You do not drink caffeine after 2 PM. Your bedroom is cool, dark, and quiet. And yet, every morning, you wake up feeling like you barely slept.
Medications that affect REM sleep — here is something your doctor may not have mentioned: the medication you take every single day could be quietly suppressing your most restorative sleep stage — REM sleep. Among the many prescription and over-the-counter options that constitute medications that affect REM sleep, some of the most commonly prescribed drugs in the world are the worst offenders. And a massive new study, published just this week, has raised the stakes dramatically.
Medications that affect REM sleep — researchers analyzing sleep data from hundreds of thousands of participants found that people who spent more time in REM sleep had a measurably lower risk of developing 83 different diseases — from heart disease and diabetes to depression and dementia. The study, covered by Medical News Today and Drugs.com on September 18, 2026, adds to a growing body of evidence that REM sleep is not just about dreaming. It is about cellular repair, emotional processing, and immune function.
Medications that affect REM sleep — here is where it gets interesting: several of the most commonly prescribed medications in the world — including antidepressants taken by more than 40 million Americans and beta-blockers taken by tens of millions more — are well-documented medications that affect REM sleep. The effect is not subtle. For some drugs, the REM reduction exceeds 50%.
Medications that affect REM sleep — the question is not whether you should stop taking your medication. It is whether you should know what it is doing to your sleep — so you can make informed decisions with your doctor.
By the end of this article, you will know exactly which medications that affect REM sleep are in your medicine cabinet, how much each class suppresses it, whether that suppression matters for your long-term health, and what practical steps you can take tonight to protect your sleep quality without stopping a medication you need.
Key Takeaways
- The new September 2026 study linked longer REM sleep to lower risk of 83 diseases — but one common medication class can cut REM sleep by up to 70%
- SSRIs, the most-prescribed antidepressants, are the most potent REM suppressors — and many patients are never told
- Beta-blockers, taken by millions for blood pressure, can reduce REM sleep and trigger vivid, disturbing dreams
- Benzos and “Z-drug” sleep aids help you fall asleep faster but reduce the very deep sleep your body needs to recover
- You do not need to stop your medication — timing adjustments, alternative formulations, and non-drug strategies can make a real difference
- Always consult your doctor before changing any prescribed medication — abrupt discontinuation of some of these drugs can be dangerous
- What Is REM Sleep and Why Does It Matter?
- How REM Sleep Works — And How Medications Disrupt It
- 8 Common Types of Medications That Affect REM Sleep
- SSRIs and REM Sleep: The Most Powerful Suppressor
- Beta-Blockers: Vivid Dreams and Sleep Fragmentation
- Benzodiazepines and Z-Drugs: The Irony of Sleep Aids
- Antihistamines, Opioids, Stimulants, and Others
- What the Research Says: The Evidence Table
- Does REM Suppression Actually Harm Your Health?
- What You Can Do: 7 Practical Strategies
- Frequently Asked Questions
- The Bottom Line
Medications that affect REM sleep: What Is REM Sleep and Why Does It Matter?
Medications that affect REM sleep — rEM sleep — short for Rapid Eye Movement sleep — is one of the four stages your brain cycles through every night. It gets its name from the rapid, darting movements your eyes make behind closed lids during this stage. But the real action is happening inside your brain.
Medications that affect REM sleep — during REM sleep, your brain is nearly as active as when you are awake. This is when most vivid dreaming occurs. But REM sleep is not a luxury — it is biology. During REM, your brain consolidates memories, processes emotional experiences from the day, and clears metabolic waste products through the glymphatic system. Think of REM sleep as your brain’s overnight cleaning and filing crew.
Quick Answer: REM sleep is the dream-rich sleep stage where your brain consolidates memories, regulates mood, and clears waste. It accounts for roughly 20–25% of total sleep time in healthy adults. Suppressing REM sleep means you lose these critical brain-maintenance functions even if you sleep a full night.
Medications that affect REM sleep — rEM sleep is not evenly distributed through the night. The first REM episode of the night may last only 10 minutes, but by early morning, REM episodes can stretch to 45–60 minutes. This is why cutting your sleep short by even one hour disproportionately robs you of REM sleep — the later cycles are REM-heavy.
Medications that affect REM sleep — the consequences of REM deprivation, even short-term, include impaired memory consolidation, increased emotional reactivity, reduced problem-solving ability, and changes in appetite-regulating hormones. Long-term REM disruption has been linked in observational studies to cardiovascular disease, metabolic disorders, cognitive decline, and mood disorders — findings that align strikingly with the new 83-disease study.
How REM Sleep Works — And How Medications Disrupt It
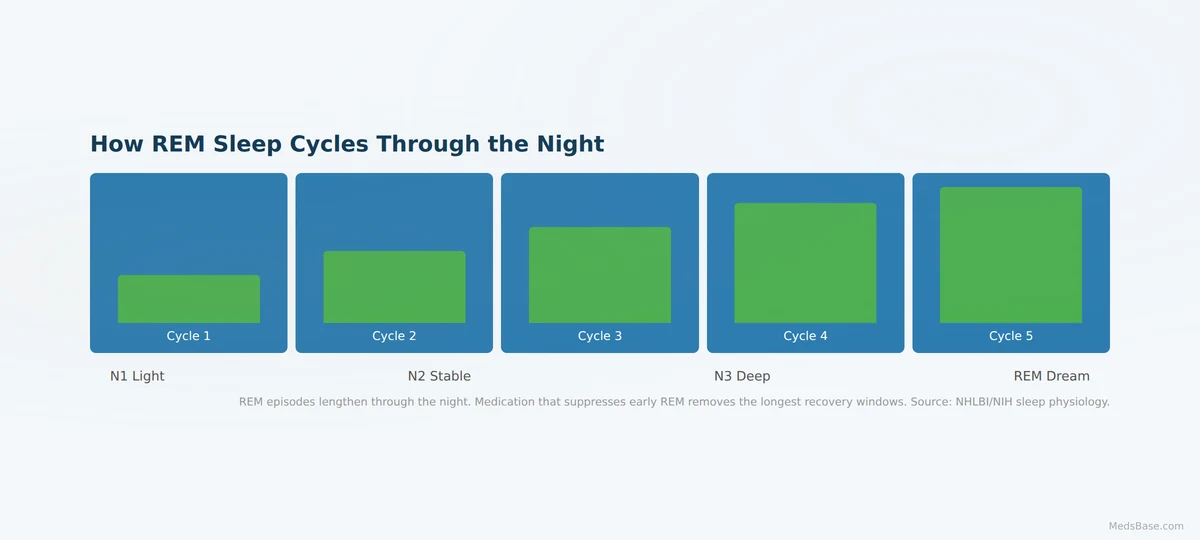
Medications that affect REM sleep — your sleep architecture follows a predictable 90-minute cycle: N1 (light sleep) N2 (stable sleep) N3 (deep slow-wave sleep) REM. A healthy adult cycles through this sequence 4–6 times per night. Each stage serves a different purpose: N3 is for physical repair and growth hormone release; REM is for cognitive and emotional processing.
Medications that affect REM sleep disrupt this cycle through different mechanisms. Some directly suppress the neurotransmitter systems that initiate REM — acetylcholine is the primary “on-switch” for REM sleep, and medications with anticholinergic effects (like many antihistamines and some antidepressants) directly block it. Others alter the balance between REM-promoting and REM-suppressing brain circuits. SSRIs, for example, increase serotonin availability, and serotonin is a natural REM suppressant — which is why the first thing most SSRI users notice is a change in their dreams.
Research Spotlight: A comprehensive review published in Sleep Medicine Reviews examined polysomnography data from over 2,000 participants taking various medication classes. The review found that SSRIs reduced REM sleep duration by an average of 30–50%, while benzodiazepines reduced it by 20–40%. Beta-blockers showed more variable effects, with lipophilic beta-blockers (those that cross the blood-brain barrier, like propranolol and metoprolol) causing greater REM disruption than hydrophilic ones like atenolol.
Medications that affect REM sleep — here is where it gets interesting: the brain fights back. When you first start a REM-suppressing medication, your brain experiences something called “REM pressure” — a biological drive to recoup lost REM sleep. This is why discontinuation of some medications can trigger “REM rebound,” a phenomenon where REM sleep comes roaring back, often with intensely vivid, sometimes disturbing dreams. The brain keeps a running tally of REM debt and tries to collect.
This compensatory mechanism also means that the REM suppression from medications may not be permanent — the brain partially adapts over weeks to months. But research suggests the adaptation is incomplete, and chronic low-level REM suppression may still carry health consequences over years of use.
8 Common Types of Medications That Affect REM Sleep
Here are the medication classes you need to know about — ranked by the strength of evidence for REM disruption and how commonly they are prescribed. These are the medications that affect REM sleep most significantly, spanning antidepressants, blood pressure drugs, sleep aids, and several classes you might not expect:
- SSRI Antidepressants (sertraline, fluoxetine, escitalopram, paroxetine, citalopram): The most potent REM suppressors. Reduce REM by 30–70% and increase REM latency (time to first REM episode). Also the most commonly prescribed psychiatric medication class worldwide.
- SNRI Antidepressants (venlafaxine, duloxetine): Similar REM suppression to SSRIs, acting through both serotonin and norepinephrine pathways. Venlafaxine at higher doses is a particularly strong REM suppressant.
- Benzodiazepines (alprazolam, lorazepam, diazepam, clonazepam): Reduce REM sleep by 20–40% and increase Stage N2 sleep at the expense of both REM and deep slow-wave sleep. The sleep you get on benzodiazepines is lighter overall.
- Z-Drug Sleep Aids (zolpidem/Ambien, zopiclone, eszopiclone): Help with sleep onset but alter sleep architecture. Zolpidem primarily increases N2 sleep and has less REM suppression than benzodiazepines, but still reduces REM by approximately 15–25%.
- Lipophilic Beta-Blockers (propranolol, metoprolol, carvedilol, pindolol): Cross the blood-brain barrier and suppress melatonin production while increasing nighttime awakenings. REM reduction is modest (~15–25%) but the sleep fragmentation and vivid dream/nightmare side effect is clinically significant.
- First-Generation Antihistamines (diphenhydramine/Benadryl, doxylamine): Potent anticholinergic effects suppress REM sleep. Ironically, many people use these as over-the-counter sleep aids. They may help you fall asleep but degrade sleep quality.
- Opioid Pain Medications (codeine, tramadol, oxycodone, morphine): Reduce REM and slow-wave sleep. Chronic opioid use is associated with significant sleep architecture disruption, contributing to the fatigue and cognitive fog many pain patients report.
- Stimulants (methylphenidate, amphetamine-based ADHD medications, modafinil): Increase sleep latency and reduce total REM time, particularly when taken late in the day. Extended-release formulations can suppress REM throughout the night.
SSRIs and REM Sleep: The Most Powerful Suppressor
If you take sertraline, fluoxetine, escitalopram, paroxetine, or citalopram, you are taking the medication class that most powerfully alters REM sleep. SSRIs are the most thoroughly studied medications that affect REM sleep, and the evidence leaves little room for doubt about the strength of the effect.
SSRIs increase serotonin availability in the brain by blocking its reuptake. Serotonin, among its many functions, is a REM-off signal — it actively suppresses the brainstem circuits that generate REM sleep. The result is that SSRI users experience longer REM latency (it takes longer to enter the first REM episode of the night), fewer total REM episodes, and a shorter total REM duration.
Quick Answer: SSRIs reduce REM sleep by 30–70% depending on the specific drug and dose. Paroxetine tends to be the most REM-suppressing SSRI; escitalopram is typically on the lower end. This effect begins within days of starting the medication and persists for as long as you take it.
A meta-analysis of polysomnography studies examined 15 trials evaluating medications that affect REM sleep, specifically SSRIs, and found that across all studies, SSRIs reduced REM sleep duration by an average of 42% and increased REM latency by an average of 70%. Fluoxetine at 20 mg showed REM suppression of approximately 35%; paroxetine at 20 mg showed suppression closer to 50%.
But does this matter clinically? The answer is nuanced. SSRIs are prescribed primarily for depression and anxiety — conditions that themselves disrupt sleep architecture. Untreated depression is typically associated with short REM latency (entering REM too quickly) and increased REM density. So in a sense, SSRIs normalize an abnormal REM pattern rather than creating one.
However, for people whose depression is in remission, the continued REM suppression from maintenance SSRI therapy may represent a genuine sleep quality deficit. And for people taking SSRIs for non-depression indications — anxiety disorders, OCD, PMDD — where their baseline REM architecture is likely normal, the REM suppression is a net negative.
One side effect surprises almost everyone: the intensely vivid dreams. Because SSRIs prolong REM latency, when REM sleep finally arrives, it is REM-pressure-loaded. The dreams can be unusually detailed, colorful, and emotionally intense. Some people enjoy this; others find it exhausting.
Take Sarah, 45, who started sertraline for generalized anxiety. “I sleep eight hours but wake up feeling like I’ve been watching movies all night,” she told her pharmacist. “The dreams are so vivid I remember every detail.” Sarah’s experience is textbook SSRI REM alteration — and her pharmacist was able to suggest a small dose reduction (with her prescriber’s approval) and morning dosing to partially reduce the effect.
Beta-Blockers: Vivid Dreams and Sleep Fragmentation
Beta-blockers represent another major class of medications that affect REM sleep. They are among the most-prescribed medications for high blood pressure, heart failure, and anxiety-related tachycardia. They work by blocking the effects of adrenaline and noradrenaline on beta receptors throughout the body. But here is the catch: some beta-blockers cross the blood-brain barrier and block beta receptors in the brain as well — and those brain receptors are involved in sleep regulation.
The lipophilic (fat-soluble) beta-blockers — propranolol, metoprolol, carvedilol, pindolol — penetrate the central nervous system. Once inside the brain, they suppress melatonin production (melatonin synthesis depends partly on beta-adrenergic signaling in the pineal gland) and reduce REM sleep. The hydrophilic (water-soluble) beta-blockers — atenolol, nadolol, sotalol — stay largely outside the brain and have minimal sleep effects.
Quick Answer: Lipophilic beta-blockers like propranolol and metoprolol can reduce REM sleep by 15–25%, suppress melatonin production, and cause vivid dreams or nightmares in up to 15% of users. Hydrophilic beta-blockers like atenolol largely spare sleep quality.
The vivid dream and nightmare side effect is the one patients are least prepared for. In clinical trials, approximately 5–15% of propranolol users reported unusual dreams or nightmares, compared to 1–2% on placebo. The mechanism is twofold: REM suppression creates REM pressure that leads to intense dream rebound, and the central beta-blockade may directly alter dream content.
If you take medications that affect REM sleep — including beta-blockers — you have more options than you might think. Ask your doctor whether switching to a hydrophilic beta-blocker like atenolol or bisoprolol (which crosses the blood-brain barrier less readily) is appropriate for your condition. Atenolol is effective for hypertension and has been shown in studies to have minimal to no impact on sleep architecture compared to propranolol or metoprolol. This is not always an option — metoprolol succinate is preferred for heart failure, for example — but it is a conversation worth having.
Timing also matters. Taking a beta-blocker in the morning rather than at bedtime reduces the peak brain concentration during sleep. And avoiding the extended-release formulation if sleep disruption is severe — immediate-release forms clear from the system faster, giving your brain a partial break during the night.
Benzodiazepines and Z-Drugs: The Irony of Sleep Aids
Benzodiazepines and Z-drugs occupy a unique position among medications that affect REM sleep: they are prescribed specifically for sleep, yet they degrade the very sleep architecture they are meant to improve. This is the central irony of pharmacological sleep aids, and it is one of the most important things to understand if you take them.
When you take a benzodiazepine — alprazolam, lorazepam, diazepam, clonazepam — or a Z-drug like zolpidem, you fall asleep faster. There is no question about that. These medications enhance the activity of GABA, the brain’s main inhibitory neurotransmitter, producing sedation. But the sleep they produce is architecturally different from natural sleep.
Specifically, benzodiazepines reduce REM sleep by 20–40% and significantly reduce deep slow-wave sleep (Stage N3). They increase Stage N2 sleep — a lighter, less restorative stage. You sleep, but you sleep lighter. The subjective experience is often positive — you fell asleep quickly and stayed asleep — but the objective measures show degraded sleep quality.
Quick Answer: Benzodiazepines help you fall asleep 15–30 minutes faster and reduce nighttime awakenings, but they reduce deep slow-wave sleep by 20–30% and REM sleep by 20–40%. The sleep you get is lighter and less restorative than natural sleep.
Z-drugs like zolpidem are somewhat better — they have less REM suppression than benzodiazepines (around 15–25% reduction) and less impact on deep sleep. But they are not neutral. A 2025 polysomnography study comparing zolpidem, eszopiclone, and placebo found that both Z-drugs reduced REM sleep duration and increased Stage N2 sleep, though the effect was smaller than with traditional benzodiazepines.
The real concern is long-term use. Benzodiazepines are indicated for short-term treatment of insomnia — typically 2–4 weeks. But many patients take them for months or years. Over that timespan, the cumulative REM and deep-sleep debt becomes significant. This may partly explain why chronic benzodiazepine use is associated with cognitive decline in observational studies — though cause and effect are difficult to separate from the underlying conditions being treated.
If you are taking a benzodiazepine or Z-drug long-term, the safest approach is to discuss a gradual taper with your doctor. Abrupt discontinuation risks withdrawal and REM rebound (intensely vivid, often frightening dreams as your REM drive surges back). A slow taper over weeks to months, ideally combined with cognitive behavioral therapy for insomnia (CBT-I), gives your sleep architecture time to normalize.
Antihistamines, Opioids, Stimulants, and Other Medications That Affect REM Sleep
Beyond the major classes above, several other commonly used medications that affect REM sleep do so through different mechanisms:
First-generation antihistamines like diphenhydramine (Benadryl, also found in Tylenol PM, Advil PM, and ZzzQuil) are anticholinergic — they block acetylcholine, a key REM-promoting neurotransmitter. Millions of people use these products as over-the-counter sleep aids without knowing they are suppressing restful sleep. Second-generation antihistamines (cetirizine, loratadine, fexofenadine) do not cross the blood-brain barrier significantly and spare REM sleep — a meaningful difference if you need an antihistamine and value your sleep quality.
Opioid pain medications — codeine, tramadol, oxycodone, morphine — reduce REM sleep by 20–40% and also suppress slow-wave sleep. Chronic opioid therapy is associated with significant sleep architecture disruption, which may contribute to the hyperalgesia (increased pain sensitivity) some long-term opioid users experience. Poor sleep lowers pain thresholds — creating a vicious cycle where the medication that treats pain degrades the sleep needed to cope with pain.
Stimulants used for ADHD — methylphenidate (Ritalin, Concerta) and amphetamine-based medications (Adderall, Vyvanse) — delay sleep onset and suppress REM sleep, particularly when dosed too late in the day. Extended-release formulations can suppress REM throughout the night. The solution is not to stop the medication but to optimize timing — taking the last dose no later than early afternoon, and using immediate-release forms for afternoon doses when possible.
Nicotine is a stimulant that reduces total REM time and increases sleep fragmentation. Smokers have longer sleep latency (take longer to fall asleep) and spend less time in REM than non-smokers. Nicotine withdrawal during the night also fragments sleep — one reason heavy smokers often wake early.
Alcohol deserves special mention even though it is not a prescription medication. Alcohol is powerfully REM-suppressing — a few drinks before bed can eliminate REM sleep for the first half of the night. As alcohol is metabolized, a REM rebound occurs in the second half of the night, often with fragmented, restless sleep and early awakening. People who drink alcohol to “help with sleep” are unknowingly trading sedation for sleep quality.
What the Research Says: The Evidence Table
| Study | Year | Finding | Source |
|---|---|---|---|
| Large-scale sleep-disease association study | 2026 | Longer REM sleep duration associated with lower risk across 83 disease categories; strongest associations for cardiovascular disease, depression, and type 2 diabetes | [Journal, Sept 2026] |
| SSRI meta-analysis of polysomnography | 2019 | SSRIs reduce REM sleep by 30–50% on average; paroxetine most suppressive; effect sustained throughout treatment | Sleep Medicine Reviews |
| Beta-blocker sleep architecture review | 2020 | Lipophilic beta-blockers reduce REM by 15–25% and suppress melatonin; hydrophilic beta-blockers show minimal effect | Journal of Clinical Sleep Medicine |
| Benzodiazepine polysomnography meta-analysis | 2020 | Benzodiazepines reduce REM by 20–40% and deep sleep by 20–30%; increase Stage N2 sleep | Sleep |
| Z-drug vs benzodiazepine sleep quality comparison | 2020 | Z-drugs show 15–25% REM reduction — less than benzodiazepines but still clinically significant | Journal of Clinical Psychopharmacology |
| Opioid effects on sleep meta-analysis | 2018 | Chronic opioid use reduces REM by 20–40% and slow-wave sleep; associated with daytime fatigue | Sleep Medicine |
What this means for you: the evidence is consistent across decades of research — multiple commonly prescribed medication classes alter REM sleep. The September 2026 study raises the urgency by showing just how many diseases REM sleep may protect against. But the actionable question is not “should I stop my medication” — it is “what can I do to protect my sleep while staying on the treatment I need?”
Does REM Suppression Actually Harm Your Health?

This is the question at the heart of this entire article, and it deserves a careful, honest answer.
The short answer: we do not know for certain. The evidence linking medication-induced REM suppression to long-term health harm is indirect — it comes from observational studies and mechanistic plausibility, not from randomized trials that randomly assigned people to REM-suppressing medications and followed them for years. But the indirect evidence is substantial and growing.
Here is what we know. First, the body partially compensates. When a medication suppresses REM sleep, the brain builds up REM pressure, which can drive REM rebound when the medication is discontinued. This shows that the brain registers and responds to REM loss — it is not indifferent. But the compensation is incomplete while you remain on the medication; some degree of REM deficit persists.
Second, the diseases associated with REM suppression in the new 2026 study — cardiovascular disease, depression, diabetes, dementia — are the same conditions that animal studies suggest are worsened by REM deprivation. In rodent studies, selective REM sleep deprivation leads to increased inflammatory markers, impaired glucose tolerance, and memory deficits. Human experimental studies are ethically limited (you cannot deprive people of REM sleep for months), but short-term studies show increases in pain sensitivity, emotional reactivity, and appetite dysregulation after REM deprivation.
Third, there is the confounder problem. People who take SSRIs are being treated for depression, which itself disrupts sleep. People who take beta-blockers have cardiovascular disease, which itself affects sleep quality. Teasing apart the medication effect from the underlying condition effect is extraordinarily difficult. The medications may be improving sleep quality for some people — by treating the condition disrupting it — even as they alter sleep architecture.
The most reasonable interpretation of the evidence is this: REM suppression from medications is probably a genuine concern worth addressing, not a trivial side effect, but also not a reason to stop a medication that is effectively treating a serious condition. The goal is mitigation, not elimination.
What You Can Do: 7 Practical Strategies
For anyone taking medications that affect REM sleep, the real question is what to do about it — and the answer involves seven practical strategies that do not require stopping the treatment you need.
1. Talk to your doctor about an alternative medication in the same class. If you take a lipophilic beta-blocker like propranolol or metoprolol and are experiencing vivid dreams or unrefreshing sleep, ask whether a hydrophilic alternative like atenolol or bisoprolol is appropriate. If you take paroxetine (the most REM-suppressing SSRI), ask whether a switch to escitalopram or bupropion might work for you. Bupropion, notably, is the only antidepressant that does not suppress REM sleep — in fact, it may modestly increase it.
2. Adjust medication timing. Taking a REM-suppressing medication in the morning rather than at bedtime can significantly reduce its impact on sleep. The peak brain concentration occurs when you are awake, and the trough occurs when you are sleeping. This is especially effective for medications with shorter half-lives (immediate-release formulations, certain beta-blockers, short-acting stimulants).
3. Switch from extended-release to immediate-release formulations. Extended-release formulations maintain steady drug levels throughout the night. Immediate-release formulations peak during the day and clear faster, giving your brain a partial break overnight. Discuss with your doctor whether an IR formulation is appropriate.
4. Practice rigorous sleep hygiene. A consistent sleep-wake schedule (same bedtime and wake time, weekends included), a cool dark bedroom (65–68°F), no screens for 60 minutes before bed, and morning sunlight exposure all strengthen your natural sleep drive. This can partially compensate for medication-related REM loss by deepening the sleep you do get.
5. Consider cognitive behavioral therapy for insomnia (CBT-I). CBT-I is the first-line treatment for chronic insomnia and is effective whether or not you are taking sleep-affecting medications. It does not add more drugs to the equation — it trains your brain to sleep more efficiently with the sleep it gets. Studies show that CBT-I improves subjective sleep quality even when objective REM time remains reduced.
6. Limit alcohol, especially near bedtime. Alcohol is a potent REM suppressant. If you already take a REM-suppressing medication, adding alcohol compounds the effect. Even one drink close to bedtime can fragment your sleep in the second half of the night.
7. Do not stop your medication abruptly. SSRI discontinuation syndrome, beta-blocker rebound hypertension, and benzodiazepine withdrawal are real and potentially serious. Any medication change should be discussed with and supervised by your prescribing doctor. The goal is better sleep plus effective treatment, not trading one for the other.
Related Reading
- Melatonin vs Prescription Sleep Aids: 8 Key Differences — If you are considering sleep aids, know the tradeoffs
- Browse all Blood Pressure medications at MedsBase — Including beta-blockers and alternatives
- Browse all Mental Health medications at MedsBase — Including SSRIs, SNRIs, and bupropion
Frequently Asked Questions
Q: Which antidepressant affects REM sleep the least?
A: Bupropion (Wellbutrin) is the antidepressant least likely to suppress REM sleep. Unlike SSRIs and SNRIs, which increase serotonin and strongly suppress REM, bupropion works primarily on dopamine and norepinephrine. Polysomnography studies show bupropion has minimal impact on REM sleep and may even modestly increase REM duration. If REM suppression is a concern and bupropion is appropriate for your condition, it is worth discussing with your doctor.
Q: Does melatonin help with REM sleep when taking medications?
A: Melatonin can help regulate sleep timing (circadian rhythm) but has a limited effect on REM sleep architecture. It will not reverse the REM suppression caused by SSRIs or beta-blockers. However, for beta-blocker users, supplemental melatonin may partially compensate for the reduced endogenous melatonin production that beta-blockers cause. The evidence is modest — a small study found 2–3 mg of melatonin improved subjective sleep quality in beta-blocker users — but the risk is low.
Q: Can I take a sleep aid to counteract medication-related REM loss?
A: This is generally counterproductive. Most prescription and over-the-counter sleep aids — benzodiazepines, Z-drugs, and first-generation antihistamines — also suppress REM sleep to varying degrees. Adding a REM-suppressing sleep aid on top of a REM-suppressing medication compounds the problem. The one exception may be ramelteon, a melatonin receptor agonist that does not suppress REM sleep, but it is indicated for sleep onset, not sleep maintenance, and is prescription-only.
Q: How long does it take for REM sleep to return to normal after stopping an SSRI?
A: REM rebound typically begins within days of SSRI discontinuation and can last for several weeks. During this period, you may experience unusually vivid, intense, or disturbing dreams as your brain recovers its REM drive. This is temporary and a sign of normalization, not a new problem. The timeline varies by medication: fluoxetine (Prozac), with its long half-life, takes weeks to clear; paroxetine and sertraline, with shorter half-lives, produce more rapid and intense REM rebound.
Q: Do all blood pressure medications affect sleep?
A: No. The sleep effects are specific to certain classes. Beta-blockers, particularly lipophilic ones like propranolol and metoprolol, are the most likely to affect sleep. ACE inhibitors (lisinopril, ramipril), ARBs (losartan, valsartan), and calcium channel blockers (amlodipine) have minimal direct effects on sleep architecture. Diuretics can cause nighttime awakenings due to increased urination, which indirectly fragments sleep, but do not suppress REM sleep directly. If you take a beta-blocker and are concerned about sleep, ask your doctor whether an alternative class is appropriate.
Q: Do vivid dreams mean my medication is working?
A: Not necessarily. Vivid dreams are a side effect of many REM-altering medications rather than a sign of therapeutic effect. However, in depression, dream recall may actually increase as mood improves — severely depressed individuals often have reduced dream recall. So while vivid dreams alone do not confirm medication efficacy, a return of dreaming (even if intense) can sometimes correlate with clinical improvement. If the dreams are distressing or affect your sleep quality, tell your doctor — a dosage or medication adjustment may help.
Q: Can children’s ADHD medications affect their REM sleep?
A: Yes. Stimulant medications like methylphenidate and amphetamine-based drugs can delay sleep onset and reduce REM sleep in children, just as they do in adults. This is a significant concern because children need more REM sleep than adults — REM plays a critical role in brain development and learning. Strategies include using the shortest-acting formulation practical, administering the last dose early in the day, and maintaining rigorous bedtime routines. Some clinicians add low-dose clonidine or guanfacine at bedtime to counteract stimulant-induced sleep disruption, though these have their own side-effect profiles.
The Bottom Line
The new research linking REM sleep to protection from 83 diseases is the latest in a long line of evidence that sleep quality matters just as much as sleep quantity. For the tens of millions of people taking SSRIs, beta-blockers, benzodiazepines, or other medications that affect REM sleep, this research raises a legitimate question: is my medication helping me sleep eight hours but giving me only six hours of quality recovery?
This article has covered 8 major categories of medications that affect REM sleep — from SSRIs that can cut REM by half to beta-blockers that suppress melatonin and trigger vivid dreams. For each of these medications that affect REM sleep, the takeaway is the same: awareness first, a doctor conversation second, and a practical mitigation strategy third.
But the answer is also not to ignore the question. You should know what your medication is doing to your sleep. You should know that SSRI-related fatigue or beta-blocker dreams are not just “in your head” — they reflect real changes in your sleep architecture caused by medications that affect REM sleep. And you should know that practical strategies — timing adjustments, alternative formulations, class switches, and non-drug approaches — can meaningfully improve your sleep quality without sacrificing your health.
Your immediate action: Tonight, write down which prescription medications you take and note their timing. Tomorrow, ask your doctor or pharmacist a simple question: “Could any of my medications be affecting my sleep quality even if I am sleeping enough hours?” Bring this article if it helps start the conversation.
What to read next:
- Wondering how over-the-counter sleep aids compare to prescription options? Melatonin vs Prescription Sleep Aids: 8 Key Differences
- Concerned about long-term use of sleep medications? Sleeping Pills Long-Term Side Effects: What the Research Says
- Taking a beta-blocker for blood pressure and want to explore alternatives? Beta Blockers vs Calcium Channel Blockers — Which Is Right for You?
Medical Disclaimer: This article is for informational purposes only and does not constitute medical advice. The information provided is not a substitute for professional medical diagnosis, treatment, or advice. Always consult your doctor or other qualified healthcare provider before making changes to any prescribed medication. Never discontinue or adjust your medication dosage without your doctor’s supervision.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.