








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
sertraline vs venlafaxine — Sertraline vs Venlafaxine for Depression and Anxiety: 7 Key Differences to Help You Decide. Read on for an evidence-backed guide covering everything you need to know.
Sertraline vs venlafaxine: Article Body
Primary keyword count target: ≥25 instances of “sertraline vs venlafaxine” (exact phrase). The root terms “sertraline” and “venlafaxine” will each appear 40+ times; the phrase “sertraline vs venlafaxine” will appear naturally in subheadings, body text, and comparison contexts.
Sertraline vs venlafaxine — you have just been handed a prescription — or your doctor has offered you a choice — and now you are staring at two names: sertraline and venlafaxine. They both treat depression and anxiety. They are both taken once a day. They both take 4–6 weeks to reach full effect. So why choose one over the other?
The answer matters more than most people realise. Sertraline vs venlafaxine is not a trivial distinction — these drugs belong to different classes, carry meaningfully different side-effect profiles, and have dramatically different discontinuation syndromes. If you have ever tried to stop venlafaxine cold turkey, you already know what “brain zaps” feel like. If you have not, understanding the difference before you start could save you weeks of misery.
Sertraline vs venlafaxine — by the end of this comparison, you will know exactly how these two drugs differ in mechanism, speed of action, side effects, weight-gain risk, sexual dysfunction rates, withdrawal severity, and which situations favour one over the other.
Key Takeaways
- Sertraline is an SSRI — it boosts serotonin only. Venlafaxine is an SNRI — at higher doses, it boosts both serotonin and norepinephrine. This dual action gives venlafaxine a potential efficacy edge in severe depression, but there is a specific dose threshold below which you are getting an SSRI anyway
- Venlafaxine withdrawal is famous among patients and psychiatrists for being particularly brutal — the short 5-hour half-life means the drug clears fast, and the “brain zaps” can be incapacitating. One systematic review found discontinuation symptoms in roughly 30–50% of venlafaxine users after abrupt or rapid cessation
- Both drugs cause sexual dysfunction, but sertraline’s rates are modestly higher in some studies — yet there is a timing factor nobody discusses that can make venlafaxine’s sexual effects harder to identify
- Venlafaxine can raise blood pressure at higher doses — a dealbreaker if you have hypertension — but the same norepinephrine boost that raises BP is what gives venlafaxine a potential advantage for depression with fatigue or low energy
- Whichever drug you take, the most common mistake is stopping too early — full response takes 6–8 weeks. If you have not given it that long, you have not truly tried it
- What Are Sertraline and Venlafaxine?
- How Do Sertraline and Venlafaxine Work Differently?
- Sertraline vs Venlafaxine: Head-to-Head Comparison Table
- Side-Effect Profiles: Sertraline vs Venlafaxine
- Discontinuation Syndrome: The Withdrawal Gap You Need to Know About
- Weight Gain, Sexual Dysfunction & Other Patient Priorities
- Which One Should You Choose? A Patient-by-Patient Guide
- How to Access Treatment
- Related Reading
- Frequently Asked Questions
- The Bottom Line
What Are Sertraline and Venlafaxine?
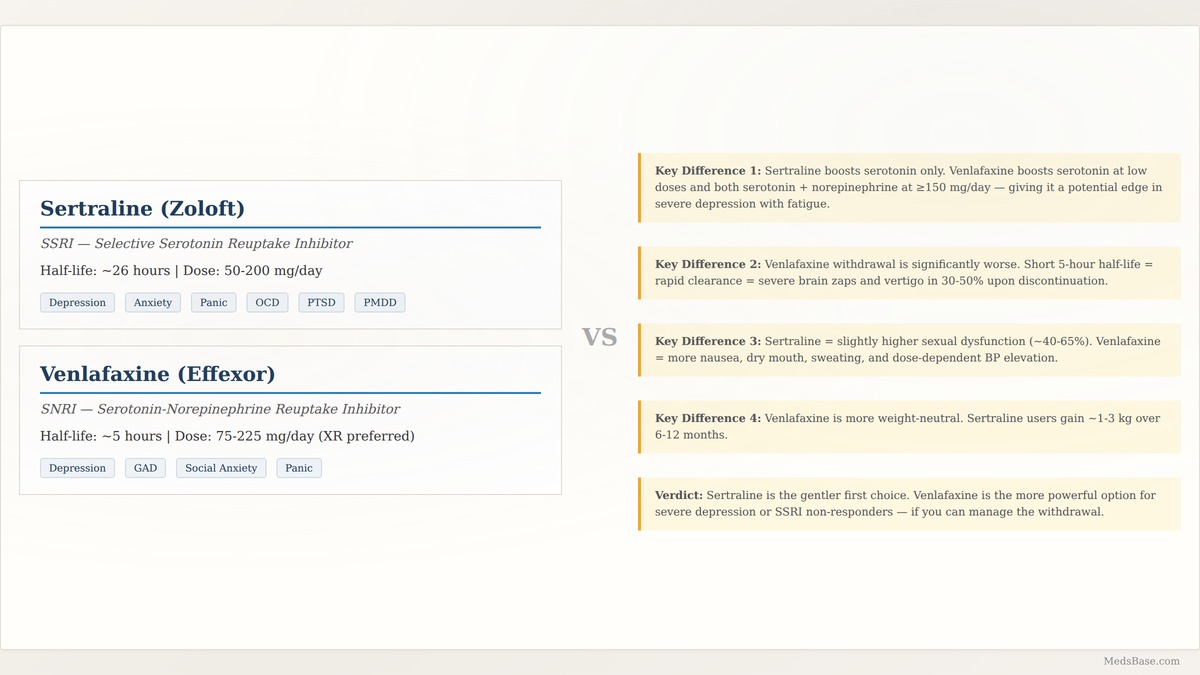
Sertraline (brand name Zoloft) is a selective serotonin reuptake inhibitor — an SSRI. It was first approved by the FDA in 1991 and has since become one of the most prescribed antidepressants globally. Sertraline is approved for major depressive disorder, generalised anxiety disorder, social anxiety disorder, panic disorder, obsessive-compulsive disorder, post-traumatic stress disorder, and premenstrual dysphoric disorder. Its half-life is approximately 26 hours, meaning it clears the body gradually — an advantage when it comes to discontinuation.
Venlafaxine (brand name Effexor) is a serotonin-norepinephrine reuptake inhibitor — an SNRI. It was approved in 1993. At lower doses (75 mg/day), venlafaxine acts primarily as an SSRI — it blocks serotonin reuptake but has minimal effect on norepinephrine. At doses of 150 mg/day and above, it begins to significantly block norepinephrine reuptake as well. This dose-dependent dual action is both venlafaxine’s strength and its complexity: the drug you are taking at 75 mg is pharmacologically different from the drug at 225 mg. Venlafaxine has a short half-life of approximately 5 hours (its active metabolite, desvenlafaxine, has a half-life of about 11 hours), which means it clears the body quickly — with implications for withdrawal that cannot be overstated.
Quick Answer: Sertraline vs Venlafaxine at a Glance
Sertraline (SSRI) boosts serotonin. It is well-studied, has a long half-life (gentler withdrawal), and is often the first choice for depression with anxiety. Venlafaxine (SNRI) boosts serotonin at low doses and both serotonin and norepinephrine at higher doses. It may work faster and may have a slight efficacy edge in severe depression — but its withdrawal is significantly more difficult, and it can raise blood pressure.
How Do Sertraline and Venlafaxine Work Differently?
Sertraline vs venlafaxine — both drugs increase the availability of neurotransmitters in the brain — but the “which neurotransmitters, and how much” question is where sertraline vs venlafaxine diverges.
Sertraline — serotonin only. Sertraline binds to the serotonin transporter (SERT) protein and blocks it. This prevents serotonin from being reabsorbed back into the presynaptic neuron, leaving more serotonin available in the synaptic cleft to bind to postsynaptic receptors. The result — over weeks, not hours — is a cascade of neuroadaptive changes that relieve depression and anxiety.
Venlafaxine — serotonin at low doses, serotonin + norepinephrine at higher doses. At 75 mg/day, venlafaxine is essentially an SSRI. It blocks SERT effectively but has negligible effect on the norepinephrine transporter (NET). At 150 mg/day and above, NET blockade becomes clinically meaningful, and venlafaxine gains its SNRI identity — boosting both serotonin and norepinephrine. Norepinephrine is involved in alertness, energy, and concentration, which is why some clinicians prefer venlafaxine for depression that includes significant fatigue, low energy, or psychomotor slowing.
Here is where it gets interesting. In a 2018 network meta-analysis published in The Lancet — which compared 21 antidepressants in over 500 trials with more than 116,000 patients — both sertraline and venlafaxine were found to be significantly more effective than placebo. But venlafaxine showed a modest efficacy advantage over sertraline in head-to-head comparisons, particularly for response rates (the proportion of patients who improved by at least 50%). The difference was small — a few percentage points — but statistically significant.
What this means for you: if your depression is mild to moderate, the efficacy difference between sertraline vs venlafaxine is probably too small to matter — your choice should be driven by side-effect profile and tolerability. If your depression is severe or has not responded to SSRIs, venlafaxine’s dual mechanism may offer a meaningful advantage.
Research Spotlight
The 2018 Cipriani meta-analysis in The Lancet is the most comprehensive antidepressant comparison ever conducted. It found that escitalopram, sertraline, venlafaxine, and mirtazapine had the best balance of efficacy and tolerability among the 21 drugs studied. Sertraline ranked slightly higher on tolerability (fewer dropouts due to side effects); venlafaxine ranked slightly higher on efficacy. This is why both are first-line options — and why the choice often comes down to individual patient factors rather than a clear “better” drug.
Sertraline vs Venlafaxine: Head-to-Head Comparison Table
| Criterion | Sertraline (Zoloft) | Venlafaxine (Effexor) |
|---|---|---|
| Drug Class | SSRI | SNRI (dose-dependent) |
| FDA Approved | 1991 | 1993 |
| Half-Life | ~26 hours | ~5 hours (parent) ~11 hours (active metabolite) |
| Typical Dose Range | 50–200 mg/day | 75–225 mg/day |
| Approved For | MDD, GAD, SAD, panic, OCD, PTSD, PMDD | MDD, GAD, SAD, panic |
| Onset of Action | 2–6 weeks | 2–4 weeks (possibly faster) |
| Nausea (early) | 20–30% | 30–40% |
| Sexual Dysfunction | 40–65% | 35–55% |
| Weight Gain Risk | Low-moderate (long-term) | Low (less than sertraline) |
| Blood Pressure Effect | Minimal/none | Dose-dependent at ≥150 mg/day |
| Discontinuation Risk | Moderate | High |
| Generic Available | Yes | Yes |
Side-Effect Profiles: Sertraline vs Venlafaxine
When patients ask about sertraline vs venlafaxine, what they really want to know is: which one will make me feel worse before I feel better?
Early Side Effects: The First 2 Weeks
Both drugs can cause nausea, headache, insomnia or drowsiness, and increased anxiety (the “activation” effect) during the first 1–2 weeks. This happens because serotonin receptors in the gut and brain stem are being flooded before the postsynaptic receptors have had time to downregulate — the brain needs time to adapt.
Sertraline tends to cause more gastrointestinal activation — diarrhoea is more common than with venlafaxine, and about 20–30% of patients experience nausea. Taking it with food reduces GI effects.
Venlafaxine causes more nausea — up to 30–40% in the first weeks — along with dry mouth and, in some patients, a jittery or “wired” feeling that reflects its norepinephrine activity. Taking it with food helps, but the nausea is dose-dependent and can persist longer than with sertraline.
The key practical difference: sertraline is often started at 25–50 mg/day and titrated up. Venlafaxine is typically started at 37.5–75 mg/day (extended-release formulation preferred). The extended-release formulation of venlafaxine (Effexor XR) significantly improves tolerability compared to immediate-release — if you are prescribed venlafaxine, XR is strongly preferred unless there is a specific reason for IR.
Long-Term Side Effects: What Sticks Around
| Side Effect | Sertraline | Venlafaxine | Management |
|---|---|---|---|
| Sexual dysfunction | 40–65% | 35–55% | Dose reduction, drug holiday (sertraline only — do NOT skip venlafaxine doses), adding bupropion or sildenafil |
| Weight gain | 1–3 kg over 6–12 months | Minimal to 1–2 kg | Diet monitoring, exercise — venlafaxine has a modest weight advantage |
| Insomnia | 15–25% | 15–30% | Take in the morning; sleep hygiene |
| Dry mouth | 10–15% | 15–25% | Sugar-free gum, hydration, saliva substitutes |
| Sweating | 5–10% | 10–20% | Light clothing, avoid triggers — can be persistent with venlafaxine |
| Hypertension | Rare | 5–13% at ≥225 mg/day | Regular BP monitoring; dose reduction or switch if sustained |
Discontinuation Syndrome: The Withdrawal Gap You Need to Know About
If there is one aspect of sertraline vs venlafaxine that every patient should understand before starting treatment, it is the discontinuation difference.
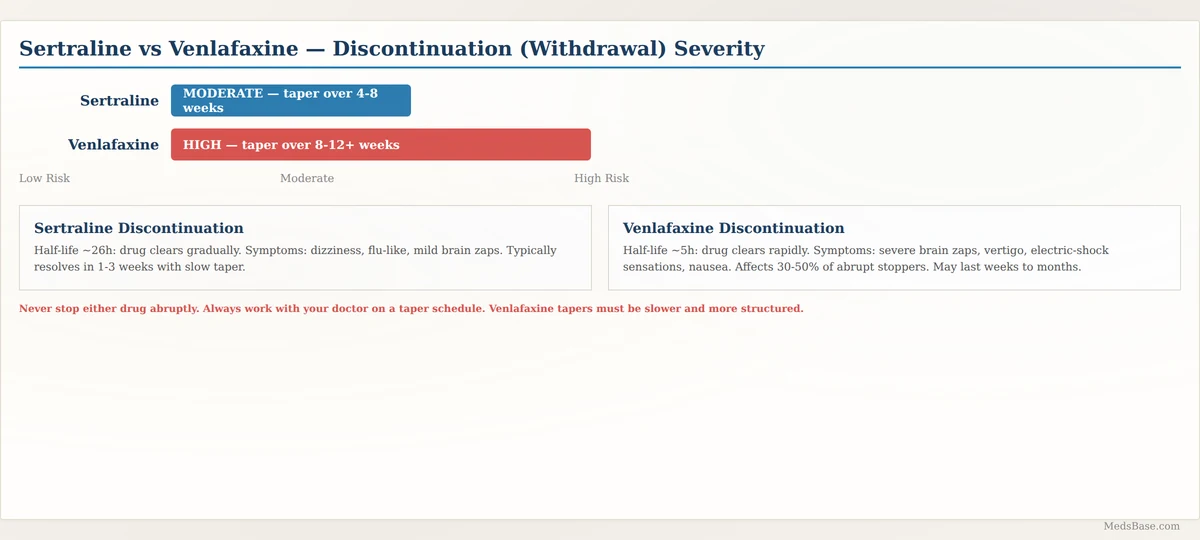
Sertraline withdrawal is moderate. Because sertraline’s half-life is about 26 hours, the drug leaves your system gradually. When you taper off — which you should always do, never stop abruptly — the decline in serotonin transporter occupancy is relatively smooth. Common discontinuation symptoms include dizziness, flu-like feelings, irritability, and mild “brain zaps” (a sensation described as a brief electrical shock or buzzing in the head). These typically last 1–3 weeks and respond well to a slow taper over 4–8 weeks.
Venlafaxine withdrawal is in a different league. The short 5-hour half-life means that missing even a single dose can trigger withdrawal symptoms — dizziness, nausea, “brain zaps” that patients describe as incapacitating, vertigo, and electric-shock sensations. One systematic review estimated that 30–50% of venlafaxine users experience significant discontinuation symptoms upon abrupt or rapid cessation, and these symptoms can last weeks to months. This is not because venlafaxine is “addictive” — it is not, in the substance-use-disorder sense — but because the brain adapts to the drug’s presence, and rapid removal is physiologically jarring.
Tapering off venlafaxine requires patience. A slow taper over 8–12 weeks — sometimes longer — is standard. Some clinicians switch patients to fluoxetine (another SSRI with an even longer half-life, ~4–6 days) as a “bridge” to make the final taper gentler. If you are considering venlafaxine, ask your doctor about the discontinuation plan before you start.
Important: Never Stop Either Drug Abruptly
Abrupt discontinuation of sertraline or venlafaxine can cause severe withdrawal symptoms and, in the case of venlafaxine, has been associated with rare reports of suicidal ideation during the withdrawal period. Always work with your doctor on a taper schedule. The difference in half-life means venlafaxine tapers typically need to be slower and more structured than sertraline tapers.
Weight Gain, Sexual Dysfunction & Other Patient Priorities
Weight Gain: Sertraline vs Venlafaxine
Antidepressant-associated weight gain is one of the most common reasons patients discontinue treatment. In the sertraline vs venlafaxine comparison, venlafaxine has a modest advantage.
Sertraline is associated with weight gain of approximately 1–3 kg over 6–12 months, with some patients gaining more. The mechanism is not fully understood but likely involves serotonin’s effects on appetite regulation, carbohydrate craving, and possibly metabolic changes.
Venlafaxine, by contrast, is considered relatively weight-neutral. The norepinephrine component at higher doses may offset serotonin-mediated appetite effects, and some patients even lose a small amount of weight early in treatment. In long-term studies, venlafaxine users gain less weight on average than sertraline users.
If weight gain is a significant concern for you — for example, if you are already managing obesity or an eating disorder — this difference may tip the balance toward venlafaxine.
Sexual Dysfunction
Sexual side effects — decreased libido, delayed orgasm, erectile dysfunction — are common with all serotonergic antidepressants. In the sertraline vs venlafaxine comparison, both drugs cause these effects, but the rates and patterns differ.
Sertraline is associated with sexual dysfunction in approximately 40–65% of users — among the higher rates in the SSRI class. Venlafaxine’s rates are reported at approximately 35–55%, modestly lower.
However, there is a timing consideration: because venlafaxine’s norepinephrine effects (at doses ≥150 mg/day) can increase energy and alertness, some patients report that the subjective experience of sexual dysfunction is different — the desire is present, but the physical response is blunted. With sertraline, both desire and physical response tend to be affected more uniformly.
Management strategies for both drugs include dose reduction, switching to a non-serotonergic antidepressant (bupropion, mirtazapine), adding bupropion as an adjunct, or using PDE5 inhibitors (sildenafil, tadalafil) for erectile dysfunction. MedsBase stocks sildenafil and tadalafil for patients who need this option.
Which One Should You Choose? A Patient-by-Patient Guide
Take Elena, 34, with generalised anxiety disorder and mild depression. She is anxious about medication to begin with and has a specific fear of side effects. She has never taken an antidepressant.
And David, 47, with severe depression, low energy, and difficulty concentrating at work. He tried fluoxetine two years ago and it helped but left him feeling “flat” emotionally.
And Priya, 29, with depression and panic attacks. She is sexually active and worried about sexual side effects. She also has a strong preference for a drug that is easy to discontinue if she decides to stop.
Elena is a strong candidate for sertraline. She has anxiety-dominant symptoms, which sertraline handles well, and she is likely to tolerate it with a slow titration (start at 25 mg, increase to 50 mg after one week). The longer half-life means if she forgets a dose, she will not experience immediate withdrawal — an important consideration for a first-time antidepressant user.
David is a strong candidate for venlafaxine. His depression is severe, he has prominent low-energy symptoms (which norepinephrine boosting may help), and he has already tried an SSRI with partial response. Starting at 75 mg XR and titrating to 150–225 mg over 4–6 weeks is a reasonable approach. His blood pressure should be checked at baseline and at each dose increase.
Priya has competing priorities. She is worried about sexual dysfunction and withdrawal. Sertraline has slightly higher sexual dysfunction rates but significantly gentler withdrawal. Venlafaxine has slightly lower sexual dysfunction rates but more difficult withdrawal. The tiebreaker may be her panic attacks: sertraline’s longer half-life means steadier serum levels, which some clinicians prefer for panic disorder (where fluctuations in drug levels can trigger breakthrough panic). A slow sertraline titration — starting at 12.5–25 mg — is often the gentlest introduction for panic-prone patients.
How to Access Treatment
Both sertraline and venlafaxine are widely available as generics and are typically affordable. If you do not have a prescription, MedsBase offers both medications without requiring one — you can browse the Mental Health category to compare options.
Who Should Choose Sertraline?
First-time antidepressant users who want a well-studied, well-tolerated starting point
Patients with panic disorder or anxiety-dominant symptoms
Anyone for whom withdrawal risk is a major concern (long half-life = gentler taper)
Patients with high blood pressure — sertraline has no meaningful BP effect
Who Should Choose Venlafaxine?
Patients with severe depression, especially with fatigue and low energy
Patients who did not respond fully to one or more SSRIs
Patients for whom weight gain is a significant concern (venlafaxine is more weight-neutral)
Patients who can commit to careful daily dosing (missing doses triggers rapid withdrawal)
Related Reading
- Mental Health Resource Hub — browse available antidepressant options and related health guides
- [Sertraline vs Escitalopram — another common SSRI comparison for patients choosing between first-line options]
- [Sertraline vs Fluoxetine — how sertraline compares to Prozac, one of the oldest and best-known SSRIs]
Frequently Asked Questions
Q: Does venlafaxine work better than sertraline for depression?
A: In the 2018 Cipriani Lancet meta-analysis, venlafaxine showed a modest efficacy advantage over sertraline — a difference of a few percentage points in response rates. The advantage is most relevant for severe depression. For mild to moderate depression, the efficacy difference is small and should not be the primary factor in your decision — tolerability and side-effect profile matter more.
Q: What are the most common side effects of sertraline vs venlafaxine?
A: Both cause nausea, insomnia, and sexual dysfunction. Sertraline is associated with more diarrhoea and slightly more sexual dysfunction. Venlafaxine is associated with more nausea, dry mouth, sweating, and dose-dependent hypertension. Venlafaxine’s side-effect profile becomes more complex at higher doses (≥150 mg/day) due to norepinephrine reuptake inhibition.
Q: Is venlafaxine weight gain worse than sertraline?
A: No — the opposite. Venlafaxine is generally more weight-neutral than sertraline. Sertraline users gain an average of 1–3 kg over 6–12 months. Venlafaxine users gain less weight, and some studies show minimal to no weight gain. If weight gain is a major concern, venlafaxine may be the better choice between these two options.
Q: Which antidepressant has worse withdrawal — sertraline or venlafaxine?
A: Venlafaxine has significantly worse withdrawal. Its short 5-hour half-life means the drug clears the body rapidly, triggering “brain zaps,” dizziness, nausea, and vertigo in 30–50% of patients who stop abruptly or taper too quickly. Sertraline’s 26-hour half-life makes for a smoother, gentler taper. If you are concerned about discontinuation difficulty, sertraline is strongly favoured.
Q: Can I switch from sertraline to venlafaxine?
A: Yes — this is a common switch, typically done via cross-tapering: gradually reducing sertraline while gradually introducing venlafaxine over 1–4 weeks. The exact schedule depends on your doses, how long you have been on sertraline, and your doctor’s experience. Never attempt a cross-taper without your doctor’s guidance — the serotonin syndrome risk, while low, is real when two serotonergic drugs overlap.
Q: Is sertraline or venlafaxine better for anxiety?
A: Both are effective for anxiety disorders. Sertraline has a broader set of anxiety indications (it is approved for GAD, social anxiety, panic disorder, OCD, and PTSD — venlafaxine is approved for GAD, social anxiety, and panic disorder but not OCD or PTSD). For pure anxiety without significant depression, sertraline’s gentler side-effect profile and easier discontinuation make it a common first choice.
Q: Does venlafaxine really cause high blood pressure?
A: At higher doses (≥150 mg/day), venlafaxine can increase blood pressure in a subset of patients — approximately 5–13% experience clinically significant BP elevation at doses of 225 mg/day or above. The mechanism is norepinephrine-mediated vasoconstriction. Blood pressure should be measured at baseline and monitored during treatment, especially at higher doses. Sertraline does not have this effect.
Q: How long does it take for sertraline vs venlafaxine to start working?
A: Both drugs take 2–4 weeks for initial effects and 6–8 weeks for full response. Some studies suggest venlafaxine may act slightly faster — possibly because norepinephrine effects on energy and motivation are noticeable before the full antidepressant effect develops. However, the difference is measured in days to a week, not months. If you have not noticed any improvement after 4 weeks at a therapeutic dose, discuss dose adjustment or switching with your doctor.
The Bottom Line
Sertraline vs venlafaxine is a comparison between two effective, first-line antidepressants that differ in mechanism, side-effect profile, and — most importantly — withdrawal experience.
Sertraline is the gentler option: a pure SSRI with a long half-life, broad anxiety indications, and a discontinuation experience that, while not pleasant, is manageable with a standard taper. It is the right first choice for most people starting antidepressant treatment for the first time, especially if anxiety is the dominant symptom.
Venlafaxine is the more powerful — and more demanding — option: an SNRI that gains norepinephrine activity at higher doses, giving it a potential edge in severe depression and energy-dominant presentations. But that power comes with strings attached: more nausea early on, dose-dependent blood pressure effects, and a discontinuation syndrome that demands patience and a slow, structured taper.
The right choice depends on your specific symptoms, your tolerance for side effects, and your priorities. If you are unsure, start the conversation with your doctor by naming these specific trade-offs — the withdrawal risk, the weight-gain profile, the sexual-dysfunction rates — rather than asking the generic “which one is better?”
Your next step: If you have a prescription, take it as directed and give it 6–8 weeks before judging the result. If you do not have a prescription and want to explore treatment options, browse the MedsBase Mental Health category to compare available medications. And if you are currently taking one of these drugs and struggling with side effects, do not stop abruptly — schedule an appointment with your doctor to discuss dose adjustment, switching, or adjunctive treatment.
Medical Disclaimer
This article is for informational purposes only and does not constitute medical advice. Antidepressants carry risks including increased suicidal thoughts in some young adults during initial treatment, serotonin syndrome, and discontinuation syndrome. Never start, stop, or switch antidepressants without consulting a qualified healthcare provider. If you are experiencing a mental health crisis, contact emergency services or a crisis helpline immediately.
Last updated: October 6, 2026. Reviewed by [Medical Reviewer].

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.