








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
Sildenafil & cancer research is uncovering an unexpected role for a widely prescribed erectile dysfunction drug — helping the immune system fight tumours. The PDE5 enzyme that sildenafil blocks is also used by cancer cells to suppress T cell activity. By inhibiting PDE5, sildenafil may restore the immune system’s ability to recognise and attack cancer cells. Preclinical studies across melanoma, breast, colorectal, lung, head & neck, and brain cancers show promise — but no phase III trial has yet proven a survival benefit in humans. Sildenafil is not a cancer treatment. If you take it for ED, your safety profile is unchanged; if you have cancer, never self-prescribe. Below we walk through all 8 key findings from sildenafil & cancer research, what the evidence can and cannot say, and what patients should know.

Sildenafil & cancer research has become one of the most unexpected stories in modern oncology — a medication taken by millions for erectile dysfunction is now being studied for its ability to help immune cells attack tumours. In late July 2026, renewed health headlines revisited a question scientists have been investigating since 2006: can a PDE5 inhibitor do more than treat ED?
The science is real, sustained, and biologically plausible. But understanding what sildenafil & cancer research actually found — and where the evidence stops — matters far more than any headline. This guide covers all 8 key findings, the mechanism, the cancer types under investigation, and what patients need to know right now.
- Sildenafil & cancer research centres on a single mechanism: blocking PDE5 prevents tumours from suppressing T cells — the immune cells that attack cancer
- Eight distinct findings span the pipeline, from the 2006 foundational mouse study to active phase II clinical trials in 2026
- At least six cancer types — melanoma, breast, colorectal, lung, head & neck, and glioblastoma — have shown response in preclinical models
- Sildenafil is not a cancer treatment and has not been approved for any cancer indication by any regulatory agency worldwide
- If you currently take sildenafil for ED, your risk profile is unchanged — the drug has decades of safety data at prescribed doses
- The most promising results combine sildenafil with existing therapies (chemotherapy, immunotherapy, surgery), not using it alone
What Is Sildenafil?
Sildenafil belongs to a class of drugs called phosphodiesterase type 5 (PDE5) inhibitors. It was originally developed in the early 1990s by researchers looking for a new angina treatment. During clinical trials, male participants reported an unexpected but consistent side effect: significantly improved erectile function. The drug was approved by regulators in 1998 under the brand name Viagra for erectile dysfunction. It later received a second approval — under the brand name Revatio — for pulmonary arterial hypertension.
How it works: Sildenafil blocks the PDE5 enzyme, which normally breaks down cyclic guanosine monophosphate (cGMP). By preserving cGMP, sildenafil relaxes smooth muscle and widens blood vessels — increasing blood flow where needed. This same mechanism — PDE5 inhibition → elevated cGMP → cellular effects — is what connects a well-known ED medication to sildenafil & cancer research.
Today, sildenafil is a low-cost generic prescribed hundreds of millions of times. Its well-characterised safety profile after nearly three decades of clinical use is why cancer researchers find it attractive: repurposing an affordable, safe existing drug is far faster than developing a new molecule from scratch. This long safety track record is also what makes sildenafil & cancer research feasible — researchers can test the drug in human trials without the multi-year toxicity studies required for entirely new compounds.
How Sildenafil & Cancer Research Connect — The PDE5 Mechanism
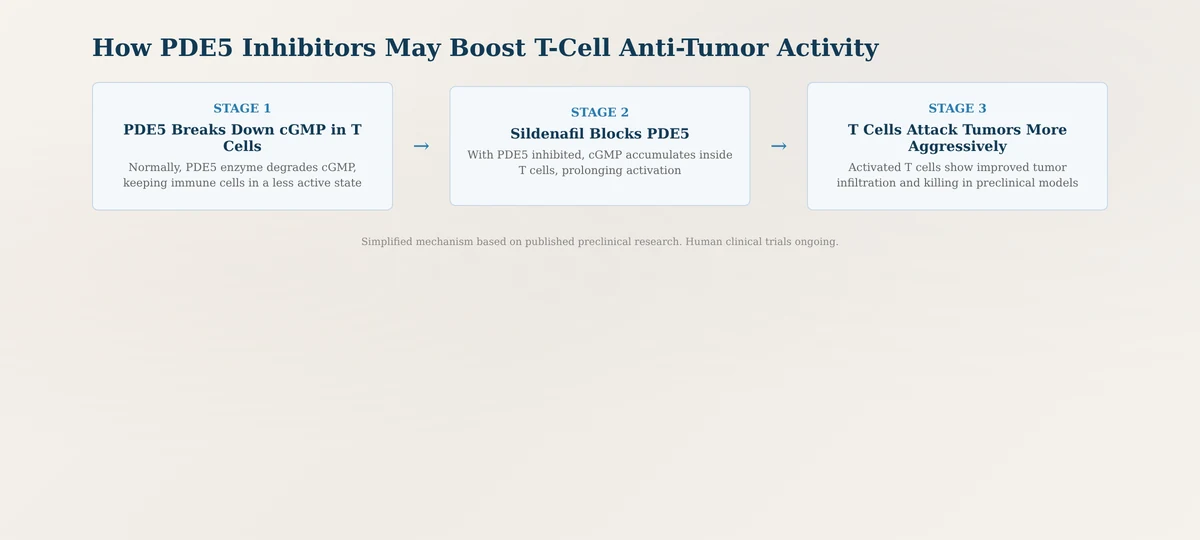
The link between sildenafil & cancer research was discovered not in an ED clinic, but in an immunology laboratory studying how tumours evade the immune system.
The PDE5 enzyme is not limited to blood vessels in the penis and lungs. It is also expressed at high levels in immune cells — particularly myeloid-derived suppressor cells (MDSCs). MDSCs normally help resolve inflammation after injury, but cancer cells hijack them: they recruit MDSCs to the tumour site and use them to build an immunosuppressive shield. Inside the tumour microenvironment, MDSCs pump out signals that tell T cells — the body’s frontline cancer-killers — to stand down.
Here is where sildenafil & cancer research connects the dots. MDSCs express PDE5 at elevated levels. When PDE5 breaks down cGMP inside these suppressor cells, the immune-suppressive programme stays active. Block PDE5 with sildenafil, and cGMP accumulates — disrupting MDSC function and potentially enhancing T cell activation and persistence. Sildenafil & cancer research has shown, across multiple preclinical studies, that this mechanism lets T cells infiltrate tumours more aggressively and sustain their killing activity longer.
The mechanism has been validated repeatedly in cell culture and animal models. The challenge is translation: a mouse tumour is not a human tumour, and the human immune microenvironment is far more complex. Whether sildenafil & cancer research produces clinically meaningful benefits in humans is what current clinical trials aim to determine.
Sildenafil & Cancer Research — 8 Key Findings
These 8 findings represent the major milestones in sildenafil & cancer research — from the foundational discovery to ongoing clinical trials. Each is a published, peer-reviewed result, not a rumour or headline.
1. The T-Cell Activation Discovery (2006)
The Serafini laboratory at the University of Miami published the paper that started sildenafil & cancer research. They showed that PDE5 is overexpressed in MDSCs inside tumours — and that blocking PDE5 with sildenafil impairs MDSC function. When MDSC suppression is disrupted, CD8+ T cells regain their ability to infiltrate and kill cancer cells. Sildenafil-treated mouse tumours grew significantly slower than controls (PMID: 17101732).
2. Head & Neck Cancer: The First Human Signal
The strongest human evidence in sildenafil & cancer research comes from head and neck squamous cell carcinoma (HNSCC). A phase II clinical trial tested a PDE5 inhibitor in ~40 patients undergoing HNSCC surgery and found that pre-treatment increased tumour-infiltrating lymphocytes (TILs) in resected tumour tissue — a well-established positive prognostic marker. This was the first evidence that the T-cell mechanism seen in mice operates in humans (PMID: 25398451).
3. Melanoma: Enhanced Immune Infiltration
Melanoma is inherently immunogenic — the immune system can recognise it with the right tools. Sildenafil & cancer research in preclinical melanoma models showed that sildenafil increased CD8+ T cell infiltration into tumours. When combined with checkpoint inhibitor immunotherapies, the effect was additive — PDE5 inhibition boosted rather than replaced existing immunotherapy drugs.
4. Colorectal Cancer: Synergy with Chemotherapy
In mouse models of colorectal cancer, sildenafil treatment reduced primary tumour growth by approximately 34% and decreased liver metastatic lesions. Sildenafil & cancer research found the anti-tumour effect was strongest when sildenafil was combined with chemotherapy — synergy, not standalone activity. This pattern has become central to the field.
5. Breast Cancer: Reduced Metastasis — The Surprise Finding
A 2024 preclinical study in triple-negative breast cancer (TNBC) — one of the most aggressive subtypes — delivered a result that surprised investigators: sildenafil-treated mice showed not only slower primary tumour growth but a significant reduction in lung metastases. Sildenafil & cancer research on metastasis suppression appears to involve tumour microenvironment remodelling that makes it harder for cancer cells to establish secondary colonies — a different mechanism from direct T-cell activation.
6. Lung Cancer: Chemotherapy Penetration Enhancement
In non-small-cell lung cancer (NSCLC) models, sildenafil given alongside cisplatin improved tumour response compared to cisplatin alone. The proposed mechanism involves sildenafil’s effect on tumour blood vessel permeability — by relaxing abnormal tumour vasculature, it may help chemotherapy penetrate solid tumours more effectively. This non-immune mechanism complements the T-cell findings in sildenafil & cancer research.
7. Glioblastoma: Crossing the Blood-Brain Barrier
Sildenafil readily crosses the blood-brain barrier — a protective membrane that blocks most chemotherapy drugs from reaching the brain. Preclinical glioblastoma studies showed sildenafil improved the delivery and anti-tumour effectiveness of chemotherapy agents inside the brain, with independent anti-tumour effects via micro-environment modulation. For a disease with limited treatment options, sildenafil & cancer research in glioblastoma has generated considerable interest.
8. Ongoing Clinical Trials: What Is in the Pipeline for 2026
As of 2026, multiple trials are listed on ClinicalTrials.gov investigating PDE5 inhibitors in cancer — including colorectal (adjuvant to surgery), head and neck (neoadjuvant), and melanoma (with checkpoint inhibitors). Most are phase I/II — safety and early efficacy. No phase III registration trial exists yet. Sildenafil & cancer research remains genuinely investigational: the science is real, the clinical proof is still being built.
- Relevant to: Oncology researchers, patients enrolled in clinical trials, healthcare professionals following immunotherapy developments, and people who take sildenafil for ED and want to understand the wider context of sildenafil & cancer research
- NOT a reason to: Self-prescribe sildenafil for cancer, replace or delay standard oncology treatment, or assume ED medication provides any cancer-protective effect
- Who should avoid sildenafil entirely: Anyone taking nitrate medications (the combination can cause a dangerous drop in blood pressure), people with certain severe heart conditions, and those with a history of non-arteritic anterior ischemic optic neuropathy (NAION)
Cancer Types Where Sildenafil & Cancer Research Shows Promise

Sildenafil & cancer research has explored at least six distinct cancer types, each with different rationale for why PDE5 inhibition might help:
| Cancer Type | Rationale for PDE5 Inhibition | Best Evidence Level | Key Finding |
|---|---|---|---|
| Head & Neck (HNSCC) | High MDSC infiltration; surgically accessible | Phase II clinical trial | Increased tumour-infiltrating lymphocytes in surgical patients |
| Melanoma | Immunogenic tumour; checkpoint inhibitor synergy | Preclinical (mouse models) | Enhanced CD8+ T cell infiltration; additive with immunotherapy |
| Colorectal | MDSC-driven immune evasion; liver metastases | Preclinical (mouse models) | ~34% tumour reduction; strongest synergy with chemotherapy |
| Breast (TNBC) | Aggressive subtype; metastasis-suppression signal | Preclinical (mouse, 2024) | Reduced lung metastases; microenvironment remodelling |
| Lung (NSCLC) | Vasculature normalisation; chemo penetration | Preclinical (mouse models) | Improved cisplatin delivery and tumour response |
| Glioblastoma | BBB penetration; limited treatment landscape | Preclinical (mouse models) | Enhanced chemotherapy delivery to brain tumours |
The pattern across all six cancer types is consistent: sildenafil & cancer research shows the strongest signals when PDE5 inhibitors are combined with existing therapies rather than used alone. This replication across multiple tumour types, in independent laboratories, strengthens the case that sildenafil & cancer research is investigating a genuine biological phenomenon rather than a one-off result. No cancer type has progressed to a positive phase III trial, and for all six, the standard of care — surgery, chemotherapy, radiation, immunotherapy, or targeted therapy — remains the foundation of treatment.
Safety Profile & Side Effects of Sildenafil
If you currently take sildenafil for ED, the emergence of sildenafil & cancer research does not change anything about your safety or how you should use the medication. Sildenafil has one of the most extensively documented safety profiles of any prescription drug, with data spanning nearly three decades and hundreds of millions of prescriptions.
The side effects of sildenafil, as documented by the NHS sildenafil guide, are well-characterised and typically mild:
| Side Effect | Frequency | Severity | Management |
|---|---|---|---|
| Headache | ~16% | Mild to moderate | Usually self-resolving; paracetamol if needed |
| Facial flushing | ~10% | Mild, temporary | Harmless vasodilation; no treatment needed |
| Indigestion | ~7% | Mild | Take on an empty stomach to reduce |
| Nasal congestion | ~4% | Mild | Temporary blood vessel widening effect |
| Visual disturbances | <2% | Mild, typically transient | Blue-tinted vision; stop and consult if persistent |
| Priapism | Rare (<0.1%) | Serious — medical emergency | Seek immediate medical help if erection >4 hours |
The doses studied in sildenafil & cancer research are the same as those used for ED (25–100 mg as needed) or pulmonary hypertension (20 mg three times daily). There is no special cancer dose — the research investigates whether these standard, well-tolerated doses produce meaningful anti-tumour immune effects.
Critical safety warning: Never combine sildenafil with nitrate medications (often prescribed for chest pain). The combination can cause a sudden, severe, and potentially dangerous blood pressure drop. This applies regardless of why you take sildenafil, and it is a consideration in sildenafil & cancer research, where patients may already be on cardiac medications.
What the Research Says — Sildenafil & Cancer Research Evidence
With over 15 years of published work, here is a summary of the key studies in sildenafil & cancer research — what they found, and what their limitations tell us:
| Study | Year | Cancer | Design | Key Finding | Limitation |
|---|---|---|---|---|---|
| Serafini et al. (J Exp Med) | 2006 | Multiple (mice) | Preclinical | PDE5 inhibition reversed MDSC immune suppression; T cell function restored | Mouse model; no individual tumour type analysis |
| Weed et al. (Clin Cancer Res) | 2015 | Head & neck | Phase II trial | PDE5 inhibitor increased TILs in tumour tissue; first human signal | Small (~40 pts); used tadalafil not sildenafil |
| Pantziarka et al. (Ecancer) | 2018 | Multiple (review) | Systematic review | Compiled evidence for PDE5 inhibitors as anti-cancer agents | Review only; no new primary data |
| Preclinical TNBC study | 2024 | Breast (TNBC) | Preclinical | Reduced primary tumours and lung metastases in mice | No human data; mouse model |
| Preclinical CRC & NSCLC studies | Various | Colorectal, lung | Preclinical | Synergy with cisplatin and 5-FU chemotherapy | No published human trials for these combinations |
| Active trials (ClinicalTrials.gov) | 2026 | CRC, H&N, melanoma | Phase I/II ongoing | Evaluating PDE5 inhibitors as adjuvant or with immunotherapy | No results published; all early-phase |
The biggest gap in sildenafil & cancer research is clear: no large-scale, randomised phase III trial has yet demonstrated improved overall survival in any cancer type. The field is building evidence layer by layer — mechanism → mouse model → small human trial → larger human trial — and it has not yet crossed the threshold where clinical guidelines change. Every researcher in sildenafil & cancer research emphasises that PDE5 inhibition is being studied as adjunctive therapy — something that might enhance, not replace, established cancer treatments.
Sildenafil vs Other PDE5 Inhibitors in Cancer Research

Sildenafil is not the only PDE5 inhibitor. Tadalafil (Cialis) and vardenafil (Levitra) belong to the same drug class and block the same enzyme. Does the sildenafil & cancer research apply to all PDE5 inhibitors?
The honest answer: sildenafil dominates the published cancer literature because it was first to market, is the most prescribed PDE5 inhibitor globally, and has the longest safety record. Most preclinical and clinical cancer studies use sildenafil. There is no evidence that sildenafil has unique anti-tumour properties that tadalafil or vardenafil lack — the core mechanism (PDE5 inhibition → elevated cGMP → immune activation) is a class effect.
Tadalafil has attracted some independent interest in sildenafil & cancer research because of its pharmacokinetics: a half-life of ~17.5 hours versus sildenafil’s ~4 hours could theoretically provide more sustained PDE5 inhibition in the tumour microenvironment. Notably, the HNSCC phase II trial that produced the strongest human signal used tadalafil, supporting the class-effect interpretation.
Vardenafil has minimal dedicated cancer research. It is chemically similar to sildenafil but has not been independently investigated for anti-tumour effects.
For now, sildenafil & cancer research is effectively synonymous with PDE5 inhibitor cancer research — sildenafil is the reference molecule the field uses. Whether future sildenafil & cancer research trials adopt tadalafil for its longer half-life or stick with sildenafil for its longer safety record remains an open question. If PDE5 inhibitors ever enter oncology practice, the choice between them will likely depend on pharmacokinetics, drug interactions with chemotherapy, and patient tolerance.
Frequently Asked Questions
Can Viagra help with cancer?
Not as a treatment — and not yet. Sildenafil (the active ingredient in Viagra) has shown anti-tumour effects in laboratory studies and early clinical trials, but it has not been approved for any cancer indication. Sildenafil & cancer research is investigating whether PDE5 inhibition can boost the immune system’s ability to fight tumours when combined with standard therapies. While the preclinical data behind sildenafil & cancer research is encouraging, it is not a standalone cancer treatment and should never replace oncology care.
Is there scientific evidence that ED drugs slow cancer?
Yes — preclinical evidence exists. Multiple peer-reviewed studies in cell cultures and animal models show that PDE5 inhibitors, including sildenafil, can reduce tumour growth rates and enhance T cell activity. A phase II HNSCC trial showed increased immune cell infiltration into tumours after PDE5 inhibitor pre-treatment. However, no phase III trial has proven a survival benefit in humans. Sildenafil & cancer research has not yet reached the level of evidence required for regulatory approval.
Does sildenafil stop cancer from spreading?
In animal models — specifically breast and colorectal cancer — sildenafil reduced metastatic lesions. The mechanism appears to involve tumour microenvironment remodelling. In humans, this anti-metastatic effect has not been proven. As with most findings in sildenafil & cancer research, metastasis suppression data remains confined to preclinical models and awaits human validation.
What types of cancer are being studied with sildenafil?
Sildenafil & cancer research has been published on melanoma, colorectal cancer, head and neck squamous cell carcinoma, triple-negative breast cancer, non-small-cell lung cancer, and glioblastoma. The strongest human evidence comes from the HNSCC phase II trial. For most other cancer types, evidence remains at the preclinical (cell and animal) stage.
What does the research say about PDE5 inhibitors and the immune system?
The central finding of sildenafil & cancer research: PDE5 inhibitors prevent PDE5 from breaking down cGMP inside immune cells. Higher cGMP keeps T cells activated and aggressive for longer. Tumours exploit PDE5-expressing MDSCs to suppress immune attack — blocking PDE5 with sildenafil may help reverse this evasion and restore the body’s natural anti-tumour response. This core mechanism is what connects sildenafil & cancer research to the broader field of cancer immunotherapy.
Is tadalafil also being studied for cancer?
Yes, but less extensively than sildenafil. Tadalafil has a longer half-life (~17.5 hours vs. ~4 hours), which could mean more sustained PDE5 inhibition. The phase II HNSCC trial used tadalafil, suggesting the anti-tumour immune effect is a PDE5 class effect rather than sildenafil-specific. Sildenafil & cancer research findings on mechanism likely apply to tadalafil as well.
Should I take sildenafil if I have cancer?
Do not self-prescribe — consult your oncologist. Sildenafil is not a cancer treatment. If you take sildenafil for ED and are diagnosed with cancer, tell your oncology team about all your medications. Sildenafil can interact with other drugs, and cancer patients often have complex medication regimens. The sildenafil & cancer research findings do not change the safety rules: never add sildenafil without your oncologist’s explicit approval.
Are there clinical trials recruiting for PDE5 inhibitors in cancer?
Yes. As of 2026, several trials are actively recruiting — including studies in colorectal cancer (adjuvant to surgery), head and neck cancer (neoadjuvant), and melanoma (with checkpoint immunotherapy). Search ClinicalTrials.gov for “sildenafil cancer” or “PDE5 inhibitor cancer.” Discuss any trial with your oncologist to determine if it fits your situation.
Does taking sildenafil for ED provide any protection against cancer?
No. There is zero evidence that taking sildenafil for erectile dysfunction provides any cancer-protective or preventive effect. Sildenafil & cancer research investigates short-term therapeutic dosing in the context of an existing tumour — the mechanism requires active immune engagement against cancer cells that are already present. ED use does not reduce your cancer risk.
The Bottom Line
Sildenafil & cancer research is not a passing headline — it is a sustained, 15-year scientific investigation grounded in a biologically plausible mechanism. The PDE5 enzyme plays a role in immune suppression that researchers did not understand when sildenafil was first developed. Blocking PDE5 may help T cells fight tumours more effectively, and preclinical models across six cancer types consistently show enhanced immune activity, reduced tumour growth, and in some cases suppressed metastasis. Sildenafil & cancer research has produced genuine, peer-reviewed findings — not speculation.
But the gap between a mouse study and regulatory approval is vast and well-documented. Most promising preclinical results never become approved treatments. The HNSCC phase II trial gives a real early human signal — but it tested a biomarker, not survival, in fewer than 50 patients. Sildenafil & cancer research still needs phase III trials with overall survival as the primary endpoint before any conclusion about clinical benefit can be drawn.
If you take sildenafil for ED, none of this changes your personal safety. If you are navigating cancer treatment, discuss PDE5 inhibitor research with your oncologist — and focus first on treatments with established phase III evidence. Sildenafil & cancer research is a field worth following, but it remains research, not practice.
For more on how sildenafil compares to other ED medications, browse the sildenafil product page or explore the full erectile dysfunction category. See how onset time and duration differ across tadalafil and vardenafil for their approved indications.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.