








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
insomnia long-term health risks — Insomnia’s Long-Term Health Risks: 7 Ways Chronic Poor Sleep Damages Your Body and What to Do About It. Read on for an evidence-backed guide covering everything you need to know.

# Insomnia’s Long-Term Health Risks: 7 Ways Chronic Poor Sleep Damages Your Body and What to Do About It
Insomnia long-term health risks — if you have been sleeping poorly for months or years, you already know what insomnia feels like — the foggy mornings, the 3 a.m. ceiling stares, the caffeine dependency that barely touches the exhaustion. What you may not know is that insomnia long-term health risks extend far beyond feeling tired. A growing body of research now links chronic poor sleep to measurable changes in your heart, brain, immune system, metabolism, and even your DNA. Understanding insomnia long-term health risks is not just about knowing what can go wrong — it is about recognizing that most of the damage is reversible when sleep improves.
Insomnia long-term health risks — here is the part most sleep articles skip: exactly how insomnia damages each body system, in plain English, with the specific mechanisms and the numbers. By the end, you will understand the biology, know which risks apply to you, and — most importantly — have a practical, evidence-backed plan to reverse the damage. One treatment, cognitive behavioral therapy for insomnia, has been shown to not just improve sleep but also reduce the inflammatory markers that insomnia elevates. Insomnia long-term health risks are serious, but they are not a life sentence — the body can heal when the sleep improves.
Key Takeaways
Insomnia long-term health risks — chronic insomnia is an independent risk factor for cardiovascular disease — linked to a 45 percent higher risk of heart attack and a 54 percent higher risk of stroke, even after controlling for other factors.
Insomnia long-term health risks — long-term poor sleep accelerates cognitive decline and raises dementia risk by an estimated 30 to 50 percent — but the mechanism is reversible when sleep quality improves.
Insomnia dysregulates cortisol, inflammatory markers, and immune function in ways that affect nearly every organ system — and these changes show up on blood tests.
The safest and most effective long-term treatment is cognitive behavioral therapy for insomnia (CBT-I); medication has a role, but it should be short-term and targeted.
Most of the biological damage caused by insomnia can be reversed or substantially reduced when normal sleep patterns are restored — your body is remarkably resilient when you give it the conditions to recover.
- What Is Insomnia — and When Does It Become Chronic?
- How Insomnia Changes Your Body at the Cellular Level
- Heart and Blood Vessels: The Cardiovascular Toll
- Brain and Cognition: Dementia, Memory, and Mood
- Metabolism and Diabetes: Why Insomnia Affects Blood Sugar
- Immune System: Why Poor Sleepers Get Sick More Often
- Mental Health: The Two-Way Street
- Other Body Systems: Gut, Hormones, and Pain
- How to Treat Insomnia: Behavioral First, Medication Second
- 7 Evidence-Backed Steps to Reverse Insomnia’s Damage
- Frequently Asked Questions
- The Bottom Line
What Is Insomnia — and When Does It Become Chronic? — Insomnia long-term health risks Explained
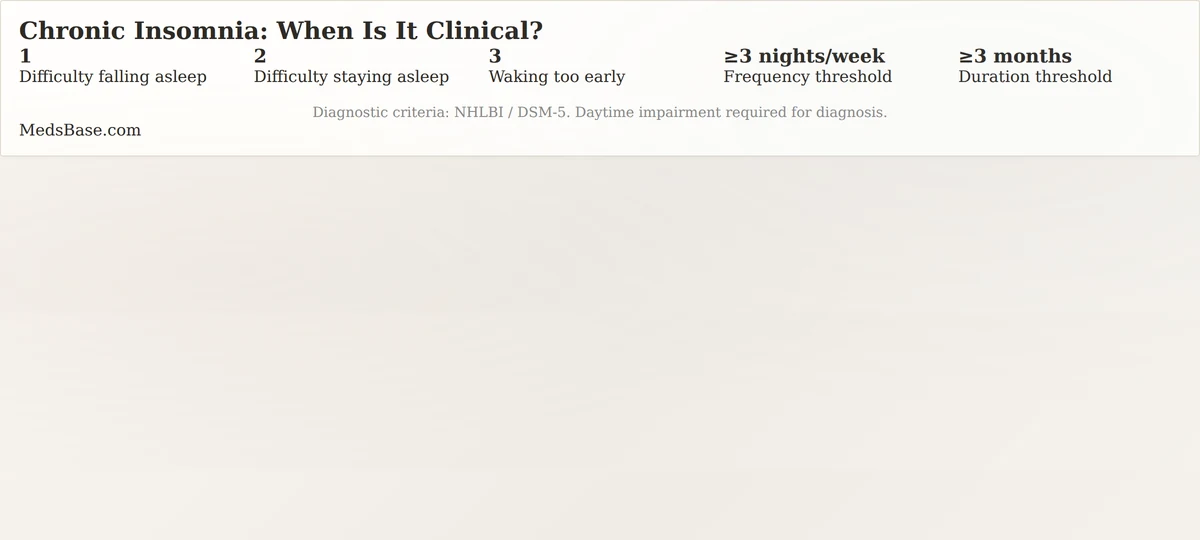
Insomnia is difficulty falling asleep, staying asleep, or waking too early — with the key distinction that these problems happen despite adequate opportunity to sleep. If you are sleep-deprived because you are working double shifts or caring for a newborn, that is sleep deprivation, not insomnia. Insomnia is the inability to sleep when you want to and can.
According to the National Heart, Lung, and Blood Institute, chronic insomnia disorder is diagnosed when sleep difficulties occur at least three nights per week and persist for at least three months, causing significant distress or daytime impairment. An estimated 10 to 15 percent of adults meet the criteria for chronic insomnia, and up to 30 percent experience insomnia symptoms at any given time.
The daytime consequences are what most people report first: fatigue, irritability, difficulty concentrating, reduced performance at work, and an increased risk of accidents. But it is the nighttime biology — the sustained elevation of stress hormones, the failure of the brain’s glymphatic clearance system, the chronic low-grade inflammation — that drives the long-term health risks. Insomnia is not merely the absence of sleep; it is an active state of hyperarousal that keeps your body’s stress response system switched on 24 hours a day. This hyperarousal state is the central biological driver of insomnia long-term health risks, and understanding it is the first step toward effective treatment.
How Insomnia Changes Your Body at the Cellular Level — Insomnia long-term health risks Explained
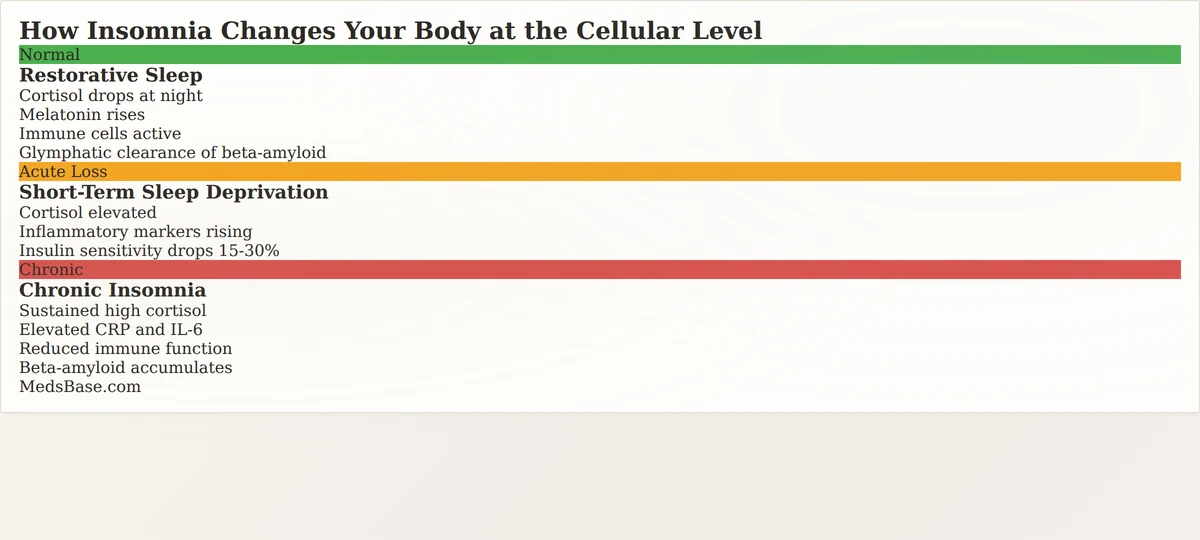
To understand insomnia long-term health risks, you have to start at the cellular level — because that is where the damage begins.
During normal sleep, your body cycles through a carefully orchestrated set of changes. Cortisol, the primary stress hormone, drops to its lowest point around midnight. Melatonin rises. Growth hormone is released, driving cellular repair. The brain’s glymphatic system — essentially its waste-clearance mechanism — becomes more active, flushing out metabolic byproducts that accumulate during waking hours, including beta-amyloid, the protein that forms the plaques found in Alzheimer’s disease.
When sleep is chronically disrupted, this entire program is thrown off. Cortisol stays elevated through the night and into the morning. Inflammatory markers such as C-reactive protein (CRP) and interleukin-6 (IL-6) rise and stay elevated. The glymphatic system gets fewer hours to do its work, and beta-amyloid clearance slows. These are not theoretical effects — they have been measured in dozens of controlled laboratory studies and large epidemiological cohorts. The cellular disruption explains why insomnia long-term health risks span so many different organ systems — the damage begins at the molecular level and cascades outward.
Here is where it gets interesting: one study found that just a single night of total sleep deprivation measurably increased beta-amyloid levels in the brain’s interstitial fluid. Multiply that by 1,000 nights over three years of chronic insomnia, and you begin to see how the damage accumulates. But the brain is not the only organ affected.
Insomnia long-term health risks: Heart and Blood Vessels: The Cardiovascular Toll
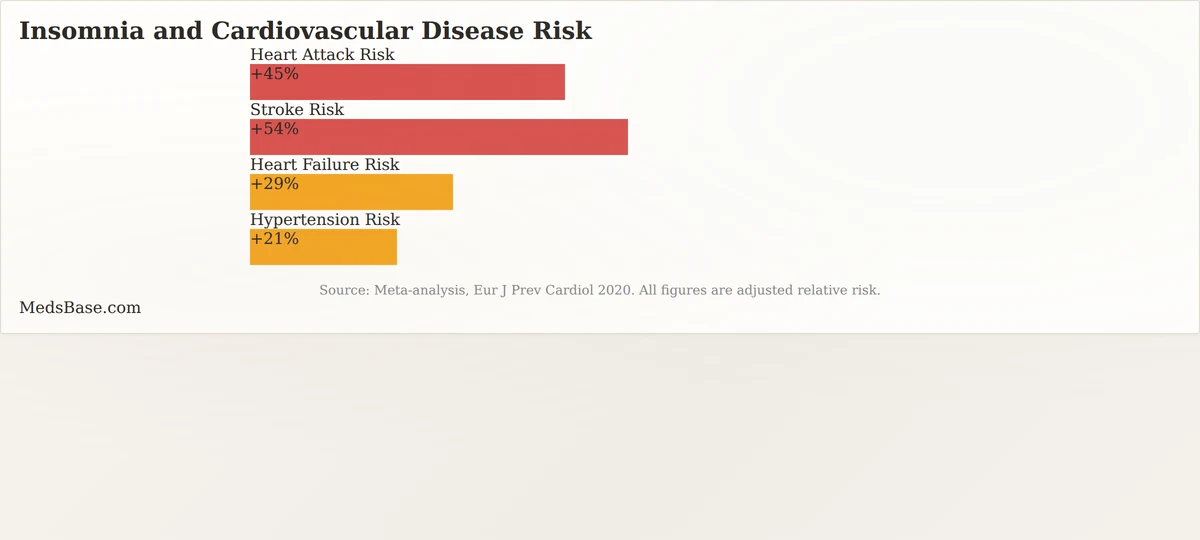
The cardiovascular consequences of insomnia are among the best-documented health risks in sleep research. Multiple studies have confirmed that insomnia long-term health risks include significantly elevated cardiovascular disease — a relationship that is independent of other risk factors. A landmark meta-analysis published in the European Journal of Preventive Cardiology pooled data from multiple prospective cohort studies and found that insomnia was associated with:
- 45 percent higher risk of heart attack (myocardial infarction)
- 54 percent higher risk of stroke
- 29 percent higher risk of heart failure
- 21 percent higher risk of hypertension
These numbers reflect adjusted risk — meaning the researchers statistically controlled for age, body mass index, smoking, alcohol use, and other factors that could confound the relationship. The insomnia-cardiovascular link appears to be independent of those variables.
How does poor sleep actually damage the heart? Three main pathways have been identified. First, elevated nighttime cortisol and sympathetic nervous system activity raise blood pressure and heart rate during hours when they should be at their lowest — a phenomenon called “non-dipping” blood pressure, which is itself a strong predictor of cardiovascular events. Second, chronic low-grade inflammation, driven by elevated IL-6 and CRP, accelerates atherosclerosis — the buildup of plaque inside artery walls. Third, insomnia disrupts endothelial function — the ability of blood vessels to dilate properly in response to increased blood flow — which is an early marker of vascular disease.
Take the hypothetical case of Mark, 52, who has not slept well since a stressful job change three years ago. He gets about five hours of fragmented sleep most nights. His blood pressure, previously well-controlled, has crept up. His CRP, measured at a recent physical, was mildly elevated. Neither Mark nor his doctor connected these changes to his sleep — but the biological chain is increasingly clear: insomnia chronic inflammation + autonomic dysregulation early vascular damage cardiovascular disease down the line. Mark’s case illustrates why insomnia long-term health risks are easy to overlook in clinical practice — the effects build gradually and are often attributed to aging or stress until an event occurs.
Brain and Cognition: Dementia, Memory, and Mood
A systematic review published in Sleep Medicine Reviews examined the relationship between sleep disturbances — particularly insomnia — and the risk of developing dementia. The findings were consistent across multiple studies: people with chronic insomnia had a roughly 30 to 50 percent higher risk of developing all-cause dementia, and the risk for Alzheimer’s disease specifically was similarly elevated.
The biological mechanism is fairly direct. During deep (slow-wave) sleep, the brain’s glymphatic system clears beta-amyloid and tau proteins — the two pathological hallmarks of Alzheimer’s disease — from the interstitial spaces between neurons. When deep sleep is consistently shortened or fragmented, clearance is reduced. Over years, this leads to greater protein accumulation, which in susceptible individuals can accelerate the neurodegenerative process.
But the cognitive effects of insomnia are not limited to the distant future. Short-term consequences include impaired attention, reduced working memory, slower processing speed, and poor decision-making — effects that anyone who has gone several nights with little sleep has experienced firsthand. What is less appreciated is that these “short-term” effects can become semi-permanent in chronic insomnia, creating a state of persistent cognitive underperformance that people often attribute to aging or stress. This cognitive toll is one of the least discussed insomnia long-term health risks, yet it affects day-to-day functioning more immediately than the cardiovascular or metabolic consequences.
Mood is deeply intertwined with sleep. Insomnia and depression share a bidirectional relationship: insomnia increases the risk of developing depression by approximately two-fold, and depression makes insomnia worse. The common denominator may be the hypothalamic-pituitary-adrenal (HPA) axis — the body’s central stress response system — which is hyperactive in both conditions. The mental health component of insomnia long-term health risks deserves as much attention as the physical components, because mood deterioration often precedes and accelerates the cardiovascular and metabolic effects.
Metabolism and Diabetes: Why Insomnia Affects Blood Sugar
If you have ever noticed that a bad night of sleep leaves you craving carbohydrates and sugar the next day, you have experienced the metabolic effects of sleep loss firsthand. A large prospective study published in Diabetes Care followed thousands of participants over several years and found that people with persistent insomnia had a significantly higher risk of developing type 2 diabetes — even after controlling for body weight, physical activity, and dietary patterns.
The mechanism involves multiple hormonal disruptions. Sleep restriction reduces insulin sensitivity — the ability of your cells to respond to insulin and take up glucose from the bloodstream — by 15 to 30 percent after just a few nights of poor sleep. At the same time, cortisol elevation promotes gluconeogenesis (the liver producing more glucose) and reduces pancreatic beta-cell function. The appetite-regulating hormones ghrelin and leptin are also thrown off: ghrelin (hunger signal) rises, while leptin (satiety signal) falls — a combination that drives increased calorie intake, especially from high-carbohydrate foods. The metabolic effects of insomnia long-term health risks highlight why sleep should be considered a modifiable metabolic factor alongside diet and exercise.
For someone already managing prediabetes or type 2 diabetes with medication, chronic insomnia adds an additional layer of metabolic stress that can make glucose control harder to achieve, regardless of how well they follow their diet and medication regimen.
Immune System: Why Poor Sleepers Get Sick More Often
The connection between sleep and immunity is one of the most intuitive — most people have noticed they are more likely to catch a cold when they have been sleeping poorly. But the scale of the effect is surprising.
A classic study exposed healthy volunteers to the rhinovirus (common cold virus) after measuring their sleep over the preceding weeks. Participants who averaged less than 7 hours of sleep per night were nearly three times more likely to develop a clinical cold than those who slept 8 hours or more. The effect was dose-dependent: shorter sleep meant higher infection risk.
The immunological mechanism goes deeper than just acute infection risk. A review in Nature Reviews Immunology detailed how sleep regulates both arms of the immune system — innate immunity (the immediate, non-specific defense) and adaptive immunity (the slower, targeted response that creates immunological memory). During sleep, the production of T-cells and pro-inflammatory cytokines is enhanced, and the immune system effectively “learns” from pathogens encountered during the day. Chronic sleep disruption impairs this process, leading to reduced vaccine responses, slower wound healing, and a state of chronic low-grade inflammation that researchers now recognize as a contributor to many age-related diseases. The immune dysfunction in insomnia long-term health risks is a particularly insidious pathway because it amplifies the damage from all other risk categories.
Mental Health: The Two-Way Street
Insomnia is both a cause and a consequence of mental health conditions. This two-way relationship means that when insomnia goes untreated, anxiety and depression tend to worsen — and when anxiety and depression are treated without addressing sleep, treatment outcomes are generally poorer.
The numbers reinforce the point. Approximately 40 percent of people with insomnia have a co-occurring mental health condition, most commonly anxiety or depression. Among people with major depressive disorder, up to 90 percent report significant sleep disturbance. But the relationship is not merely correlational — longitudinal studies show that insomnia that develops before depression predicts a more severe and treatment-resistant depressive course. The mental health dimension of insomnia long-term health risks is doubly significant because it both worsens the experience of the physical health risks and makes people less likely to seek or adhere to treatment.
The mechanism is partly neurochemical. The same neurotransmitter systems implicated in mood regulation — serotonin, norepinephrine, dopamine — are also involved in sleep-wake regulation. When sleep is disrupted, these systems do not reset properly overnight, leading to cumulative dysregulation that manifests as worsening mood, irritability, and emotional reactivity.
Other Body Systems: Gut, Hormones, and Pain

Insomnia’s reach extends into systems that are less frequently discussed:
Gastrointestinal system: Sleep disturbance alters the gut microbiome composition, reducing microbial diversity and shifting the balance toward pro-inflammatory bacterial species. People with insomnia report higher rates of irritable bowel syndrome (IBS) and functional dyspepsia — conditions where the gut-brain axis is implicated. Insomnia long-term health risks are not limited to traditionally studied systems; the gut-brain connection is an emerging frontier of sleep research.
Endocrine system: Beyond cortisol, insomnia disrupts the secretion of growth hormone (which peaks during deep sleep and drives tissue repair), thyroid-stimulating hormone, and reproductive hormones. In men, chronic sleep restriction has been shown to reduce testosterone levels by 10 to 15 percent — an effect comparable to aging 10 to 15 years in terms of hormonal profile. The hormonal disruption component of insomnia long-term health risks highlights that the effects go beyond what most people associate with poor sleep.
Pain perception: Sleep deprivation lowers pain thresholds, making existing pain feel worse. This creates a vicious cycle: pain disrupts sleep, and poor sleep amplifies pain perception. Breaking this cycle — either by treating the pain, the insomnia, or both simultaneously — is often the key to improvement. Insomnia long-term health risks include this under-recognized pain-amplification effect, which can make chronic pain conditions like fibromyalgia and arthritis significantly harder to manage.
How to Treat Insomnia: Behavioral First, Medication Second
If you have been living with insomnia for months or years, the question that matters most is: what actually works?
Cognitive Behavioral Therapy for Insomnia (CBT-I) is the first-line treatment recommended by the American College of Physicians, the American Academy of Sleep Medicine, and the European Sleep Research Society. It addresses the thoughts and behaviors that perpetuate insomnia through several components: stimulus control (associating the bed only with sleep), sleep restriction (temporarily limiting time in bed to build sleep pressure), cognitive restructuring (challenging catastrophic thoughts about sleeplessness), and relaxation training.
CBT-I is effective for approximately 70 to 80 percent of people who complete it, and its benefits are durable — people who learn the techniques typically maintain improved sleep for years. It can be delivered in person (typically 4 to 8 sessions), online through digital platforms, or via self-guided books and apps.
Where medication fits in. Sleep medications — including benzodiazepine receptor agonists (zolpidem, eszopiclone), melatonin receptor agonists (ramelteon), dual orexin receptor antagonists (suvorexant, daridorexant), and sedating antidepressants (trazodone, mirtazapine, doxepin) — can be helpful for short-term relief, especially during acute crises. However, they are not recommended as the sole long-term strategy because of tolerance, dependence, and side-effect concerns.
The ideal approach for many people is a combined strategy: medication for immediate relief during the first weeks while CBT-I skills take hold, then tapering off the medication as behavioral strategies become effective. This should be done under medical supervision. A comprehensive approach to insomnia long-term health risks includes addressing both the acute need for symptom relief and the long-term need for sustainable behavior change.
7 Evidence-Backed Steps to Reverse Insomnia’s Damage
The body’s capacity for repair is remarkable. When sleep normalizes, many of the biological markers that insomnia elevates — inflammatory cytokines, cortisol, blood pressure — begin to trend back down. Here are seven evidence-backed steps to start that process.
1. Fix your wake time before you fix your bedtime. The single most powerful behavioral change for insomnia is a consistent wake time, seven days a week, regardless of how poorly you slept the night before. This stabilizes your circadian rhythm and builds sleep pressure at the right time of night. Sleeping in on weekends after a bad week of sleep feels restorative but actually perpetuates the problem by shifting your internal clock.
2. Get bright light within 30 minutes of waking. Morning light exposure is the strongest zeitgeber (time cue) for your circadian system. Aim for 15 to 30 minutes of outdoor light or, if that is not practical, a light box delivering 10,000 lux. This suppresses residual melatonin, elevates cortisol to its normal morning peak, and sets the countdown timer for sleep onset roughly 16 hours later.
3. Move your caffeine cutoff to early afternoon. Caffeine has a half-life of 4 to 6 hours, which means that a 3 p.m. coffee still leaves roughly half of its caffeine in your bloodstream at 9 p.m. — enough to fragment sleep even if you do not consciously feel wired. A 2 p.m. cutoff (or earlier if you are particularly sensitive) is a low-cost, high-yield change.
4. Use your bed only for sleep and intimacy. This is the core of stimulus control: if you lie awake for more than 20 minutes, get up, go to another room, and do something calm and low-stimulation until you feel sleepy. The goal is to re-associate the bed with sleep rather than with frustration, worry, and screen-scrolling.
5. Try CBT-I — in any format that fits your life. Whether through a sleep clinic, a digital program (several FDA-cleared apps now deliver CBT-I), or a well-reviewed self-help book, the specific components of CBT-I have decades of evidence behind them. Six to eight weeks of consistent effort typically produce meaningful improvement.
6. Discuss short-term medication with your doctor if needed. If sleep deprivation is acutely impairing your functioning, a short course of a sleep medication can break the cycle. The newer dual orexin receptor antagonists (DORAs) such as daridorexant have a lower dependence potential than traditional benzodiazepine receptor agonists and may be a safer bridge while behavioral strategies take hold. Never start or stop prescription sleep medication without medical guidance.
7. Track your sleep with a simple log, not a device. Sleep-tracking wearables can fuel anxiety (a phenomenon called “orthosomnia”) by presenting sleep data that is often inaccurate and makes people obsess over metrics. A simple paper log — what time you went to bed, roughly what time you fell asleep, how many times you woke up, what time you got up — for two weeks provides enough data for you and your doctor to identify patterns without the anxiety amplification.
Frequently Asked Questions
Q: What happens to your body when you don’t sleep for years?
A:
A: Chronic insomnia — defined as poor sleep at least three nights per week for three months or longer — triggers a sustained elevation of stress hormones (cortisol), inflammatory markers (CRP, IL-6), and sympathetic nervous system activity. Over years, these changes contribute to measurable increases in the risk of hypertension, heart attack, stroke, type 2 diabetes, obesity, depression, anxiety disorders, and cognitive decline. The body does not “get used” to insufficient sleep; the damage accumulates.
Q: Can chronic insomnia cause permanent damage?
A:
A: Most of the biological changes associated with insomnia — elevated inflammatory markers, impaired glucose tolerance, elevated blood pressure, cognitive slowing — are reversible or substantially improvable when sleep normalizes. The exception may be the neurodegenerative protein accumulation (beta-amyloid, tau) associated with Alzheimer’s disease; while clearance improves with restored sleep, whether existing deposits can be reversed is less clear. The takeaway is that it is never too late to improve sleep, and the earlier the intervention, the better the long-term outcome.
Q: How does insomnia affect the heart?
A:
A: Insomnia affects the heart through three primary pathways: (1) elevated nighttime blood pressure (loss of the normal nocturnal “dip” in blood pressure), (2) chronic low-grade inflammation that accelerates atherosclerosis, and (3) impaired endothelial function, which reduces the ability of blood vessels to dilate properly. Together, these mechanisms explain the 45 percent increased risk of heart attack and 54 percent increased risk of stroke found in large meta-analyses.
Q: Does lack of sleep increase dementia risk?
A:
A: Yes. Multiple large prospective cohort studies have found that people with chronic insomnia have a 30 to 50 percent higher risk of developing dementia. The most established biological mechanism is reduced glymphatic clearance — the brain’s waste-removal system, which is most active during deep sleep, clears less beta-amyloid and tau protein when sleep is chronically insufficient, allowing these proteins to accumulate.
Q: Can you reverse damage from chronic insomnia?
A:
A: Yes, most of the damage is reversible. Studies following patients through CBT-I treatment have documented reductions in inflammatory markers (CRP, IL-6), improved insulin sensitivity, lower blood pressure, and improved cognitive function — all corresponding with improved sleep quality. The key is that reversal takes time: 6 to 12 weeks of consistently improved sleep is typically needed to see measurable biological improvements. The reversibility of insomnia long-term health risks is one of the most hopeful findings in sleep medicine — but it requires sustained effort, not quick fixes.
Q: What is the safest treatment for long-term insomnia?
A:
A: Cognitive Behavioral Therapy for Insomnia (CBT-I) is the safest and most effective long-term treatment. It has zero pharmacological side effects, produces durable results, and addresses the underlying behavioral and cognitive patterns that perpetuate insomnia. For short-term relief, dual orexin receptor antagonists such as daridorexant are considered safer (lower dependence potential) than traditional benzodiazepine receptor agonists, but no sleep medication is recommended as the sole long-term strategy. When weighing treatment options against insomnia long-term health risks, the evidence consistently favors behavioral approaches over pharmacological ones for sustained improvement.
The Bottom Line
Insomnia long-term health risks are real, well-documented, and affect more body systems than most people realize. Chronic poor sleep contributes to cardiovascular disease, cognitive decline, metabolic dysfunction, immune impairment, and mental health deterioration — not through a single mechanism, but through a sustained elevation of stress hormones, inflammation, and autonomic nervous system activity that gradually damages tissues over years. The evidence on insomnia long-term health risks continues to grow, and the message is increasingly clear: sleep is not a luxury; it is a biological necessity with consequences for every organ system.
The hopeful part — and it is genuinely hopeful — is that your body is resilient. When sleep improves, the inflammatory markers drop, the blood pressure normalizes, the cognitive fog lifts, and the emotional regulation returns. The treatment that has the strongest evidence behind it is not a pill; it is a set of behavioral techniques (CBT-I) that you can learn in a few weeks and use for life. Medication can help bridge the gap, but behavioral change is what sustains recovery.
If you have been living with insomnia for months or years, the first step is the hardest but also the simplest: talk to your doctor specifically about your sleep. Bring a two-week sleep log. Ask about CBT-I. Consider whether a short-term medication makes sense while you develop better sleep habits. The goal is not perfect sleep every night — that is not realistic for anyone. The goal is consistent, restorative sleep most nights — and that is achievable for the vast majority of people with chronic insomnia.
For a deeper dive into specific sleep medications, read our comparison of mirtazapine vs trazodone for sleep and depression or explore the Mental Health category at MedsBase to understand all your treatment options.
Medical Disclaimer: This article is for informational purposes only and does not constitute medical advice. Chronic insomnia is a medical condition that should be evaluated by a healthcare professional. The treatment approaches described here — including CBT-I and sleep medications — should only be undertaken under the supervision of a qualified doctor or sleep specialist. Never start, stop, or change any medication without consulting your healthcare provider. If you are experiencing thoughts of self-harm, contact a crisis helpline immediately.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.