








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
once weekly insulin for type 2 diabetes — Once-Weekly Insulin for Type 2 Diabetes: 7 Essential Facts About the New FDA-Approved Onswik. Read on for an evidence-backed guide covering everything you need to know.

Once weekly insulin for type 2 diabetes — if you take insulin every day, you already know the arithmetic: one injection. Every night. Three hundred and sixty-five times a year. Seven injections a week. Fifty-two weeks a year without a single day off — and that is before you count the finger pricks, the mealtime doses, the pharmacy refills, and the planning required every time you travel, stay late at work, or simply want to forget you have diabetes for one evening.
Once weekly insulin for type 2 diabetes — now multiply that by the years you have been doing it. The lifetime tally is staggering — and so is the mental load of a disease that demands your attention every 24 hours.
Once weekly insulin for type 2 diabetes — on September 24, 2026, the FDA changed that calculation. It approved Onswik (insulin efsitora alfa-gobe), the first and only once weekly insulin for type 2 diabetes — a single injection that replaces seven daily basal insulin shots. For the millions of adults managing type 2 diabetes who have been waiting for exactly this kind of option, the question is not just “does it work?” but “is this actually real, and is it for me?”
Once weekly insulin for type 2 diabetes — the short answer: yes, it is real, the clinical data is solid, and it is approved for adults with type 2 diabetes. But it is not for everyone — and one group in particular should stay far away from it. We will get to exactly who that is.
By the time you finish reading, you will know how once weekly insulin for type 2 diabetes works, how it compares to daily basal insulin in head-to-head trials, which patients qualified in those trials, what the safety trade-offs are, and the practical steps for talking to your doctor about whether Onswik belongs in your treatment plan.
Key Takeaways
- On September 24, 2026, the FDA approved Onswik (insulin efsitora alfa-gobe) — the first once weekly insulin for type 2 diabetes — replacing 365 daily basal injections per year with just 52.
- Four Phase 3 QWINT clinical trials enrolling over 3,400 adults demonstrated that once-weekly Onswik was non-inferior to daily basal insulin (degludec and glargine) for A1C reduction, with a comparable safety profile.
- Once weekly insulin for type 2 diabetes is not for type 1 diabetes — the FDA explicitly contraindicates it due to an increased risk of severe hypoglycemia, and the trials enrolled only type 2 patients.
- Onswik uses a novel molecular design — an Fc fusion protein — that slows absorption and extends the half-life to approximately 17 days, producing steady basal insulin levels across the full week.
- The missed-dose window is generous: you can take a forgotten dose within 4 days (96 hours) and stay on your regular schedule — flexibility that daily basal insulins cannot match.
Once weekly insulin for type 2 diabetes: Table of Contents
- What Is Once-Weekly Insulin (Onswik) — and Why It Matters?
- How Does Once-Weekly Insulin for Type 2 Diabetes Work?
- How Effective Is Once-Weekly Insulin for Type 2 Diabetes?
- Who Is Once-Weekly Insulin For — and Who Should Avoid It?
- Safety, Side Effects, and Dosing — What the Trials Found
- Once-Weekly Insulin vs Daily Insulin — A Direct Comparison
- Practical Guidance for Starting Once-Weekly Insulin
- Frequently Asked Questions
- The Bottom Line
Once-Weekly Insulin for Type 2 Diabetes: 7 Essential Facts About the New FDA-Approved Onswik
What Is Once-Weekly Insulin (Onswik) — and Why It Matters? — Once weekly insulin for type 2 diabetes Explained
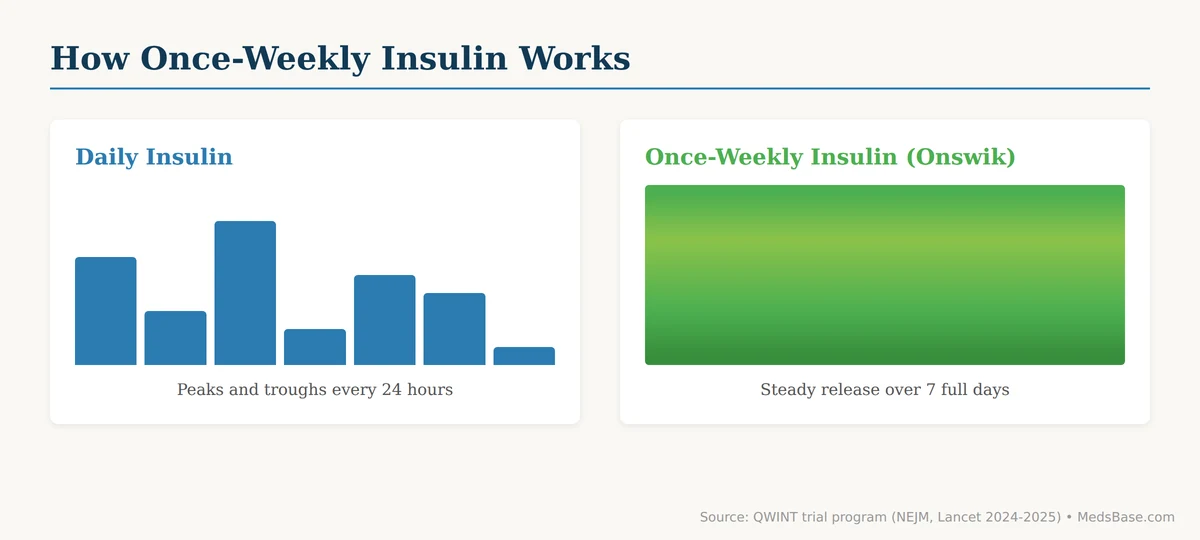
Quick Answer: Once weekly insulin for type 2 diabetes is a long-acting basal insulin injection taken just once per week instead of every day. Marketed as Onswik (insulin efsitora alfa-gobe) by Eli Lilly, it received FDA approval on September 24, 2026, making it the first and only once-weekly basal insulin available in the United States. It is indicated for adults with type 2 diabetes — not type 1 — and is designed to provide steady background insulin coverage across a full seven days.
The significance of this approval is difficult to overstate if you live with the daily reality of insulin injections. For roughly a century — since insulin was first isolated in 1921 — basal insulin has meant a daily injection. The innovation curve over that century produced faster-acting mealtime insulins, longer-lasting basal insulins (from NPH to glargine to degludec), and smarter delivery devices. But the fundamental rhythm never changed: one shot, every 24 hours, without exception.
Once weekly insulin for type 2 diabetes breaks that century-old pattern.
The numbers put it in perspective. A once-daily basal insulin user takes approximately 365 injections per year solely for background insulin — not counting mealtime boluses, correction doses, or the occasional needle that bends and needs replacing. Onswik requires 52 injections per year. That is a reduction of over 300 injections annually, according to Lilly’s own analysis of the dosing schedules (FDA approval press release, Sep 24, 2026).
But this is about more than counting needles. The burden of daily insulin goes well beyond the physical act of injecting. There is the mental overhead: remembering whether you took your dose, planning around travel and time zones, finding a private place to inject if you are out at your usual dosing time, and the low-grade anxiety of wondering whether you remembered to pack your insulin pen. Reducing that burden from 365 decision points to 52 is, for many patients, the real headline.
Around one in eight Americans lives with diabetes, and the vast majority have type 2 diabetes. Globally, researchers project that over 510 million people will be living with the disease by 2030 — and approximately 38 million of those will require insulin. For those 38 million people, the choice between 365 injections and 52 injections is not a small one.
That said, once weekly insulin for type 2 diabetes is not simply “daily insulin, but less often.” It is a different molecule, with a different dosing approach, different trial data, and a different safety profile. Understanding the details matters before you and your doctor decide whether it belongs in your treatment plan.
How Does Once-Weekly Insulin for Type 2 Diabetes Work? — Once weekly insulin for type 2 diabetes Explained
To understand once weekly insulin for type 2 diabetes, you first need to understand what happens with daily basal insulin — and why extending coverage to a full week was so difficult.
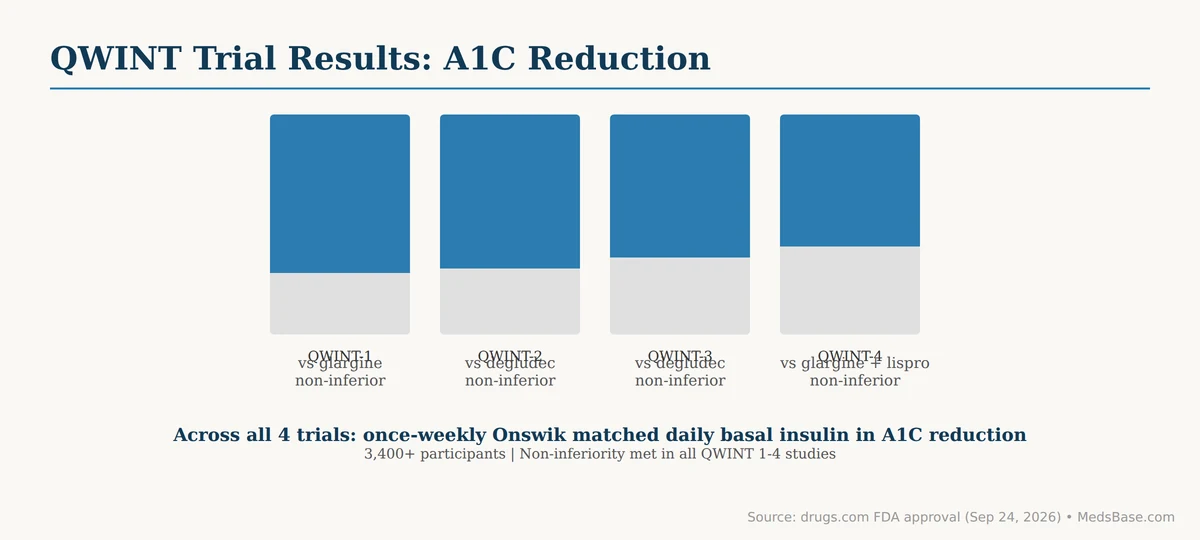
Daily basal insulins like insulin glargine (Lantus, Basaglar) and insulin degludec (Tresiba) work by forming slow-dissolving depots under the skin after injection. Glargine forms micro-precipitates at the injection site, releasing insulin gradually over roughly 24 hours. Degludec forms multi-hexamer chains that dissolve even more slowly, giving it a duration of action beyond 42 hours — which is why it is sometimes dosed flexibly within an 8-hour window. But even degludec cannot stretch to a full week: eventually, the depot dissolves, and insulin levels drop.
Insulin efsitora alfa-gobe (Onswik) solves this problem differently. It is not just a slower-dissolving version of a daily insulin — it is a fundamentally different molecular design. Efsitora is a fusion protein: a single-chain insulin analogue fused to a human IgG2 Fc domain. The Fc domain is the same type of protein fragment that gives monoclonal antibodies their long circulating half-life, because the body recycles Fc-containing proteins rather than clearing them rapidly.
Here is what that means in plain terms: after you inject Onswik under your skin, the efsitora molecule enters your circulation and stays there far longer than a standard insulin molecule would. The Fc domain engages a recycling receptor (the neonatal Fc receptor, or FcRn) that rescues the molecule from degradation and returns it to the bloodstream. The result is a half-life of approximately 17 days — more than long enough to provide stable basal insulin coverage for an entire week between injections.
Think of daily basal insulin like a cup of coffee that wears off by the end of the day. You need another cup tomorrow morning. Once weekly insulin for type 2 diabetes is more like a slow-release caffeine patch — it delivers a steady, low-level effect across days without the peaks and troughs. For your blood sugar, steady is better: it means fewer nocturnal hypoglycemic dips and fewer fasting glucose spikes, assuming your dose is correctly titrated.
This design does come with a practical consequence worth understanding upfront. Because efsitora has such a long half-life, the loading period is different from what you may be used to with daily insulin. When you start Onswik, your first dose begins building toward a steady state that takes several weeks to fully establish. This means dose adjustments should not be made too aggressively in the first month — a point your doctor will manage, but one worth knowing so you do not become frustrated if you do not see perfect numbers in week one.
How Effective Is Once-Weekly Insulin for Type 2 Diabetes?
The FDA approval of once weekly insulin for type 2 diabetes was based on the QWINT Phase 3 clinical development programme, which began in 2022 and enrolled over 3,400 adults with type 2 diabetes across four global registration studies. Each trial compared once-weekly Onswik against a daily basal insulin — either insulin degludec or insulin glargine — and every trial met its primary endpoint: non-inferior A1C reduction.
Non-inferiority is the standard bar for a new insulin formulation. It means Onswik was statistically no worse than the existing daily insulin comparator by a pre-specified margin — in this case, a difference in A1C change of less than 0.4 percentage points. In every QWINT trial, Onswik cleared that bar comfortably. Two of the trials (QWINT-2 and QWINT-4) even demonstrated statistically significant superiority in certain secondary endpoints, though the headline takeaway is that once weekly insulin for type 2 diabetes controls blood sugar just as well as daily basal insulin.
Here is a summary of what each trial found:
| Trial | Population | Comparator | Duration | Primary Result | Source |
|---|---|---|---|---|---|
| QWINT-1 | 796 insulin-naive adults with T2D | Insulin glargine U-100 (daily) | 52 weeks | Non-inferior A1C reduction; fixed-dose escalation design | Rosenstock et al., NEJM 2025 |
| QWINT-2 | 928 insulin-naive adults with T2D | Insulin degludec U-100 (daily) | 52 weeks | Non-inferior A1C reduction; assessed with/without GLP-1 RA use | Wysham et al., NEJM 2024 |
| QWINT-3 | 986 adults with T2D already on basal insulin | Insulin degludec U-100 (daily) | 78 weeks (primary at 26 weeks) | Non-inferior A1C reduction at 26 weeks | Philis-Tsimikas et al., Lancet 2025 |
| QWINT-4 | 730 adults with T2D on basal + mealtime insulin | Insulin glargine U-100 (daily) + insulin lispro | 26 weeks | Non-inferior A1C reduction; more complex insulin regimen | Blevins et al., Lancet 2025 |
A few details from these trials deserve attention because they match real-world clinical scenarios — not just the idealised trial patient.
QWINT-2, the largest insulin-naive trial published in NEJM, enrolled patients both with and without background GLP-1 receptor agonist use. This matters because a significant and growing number of type 2 diabetes patients use GLP-1 medications (semaglutide, tirzepatide, liraglutide), and the trial confirmed that once weekly insulin for type 2 diabetes works effectively whether or not you are also on a GLP-1. Wysham and colleagues reported that A1C reduction with efsitora was approximately -1.3% from baseline over 52 weeks — statistically non-inferior to the -1.3% seen with daily degludec.
QWINT-3, published in The Lancet, addressed the patient group most likely to consider switching: adults already established on daily basal insulin. Philis-Tsimikas and colleagues found that switching from daily degludec to once-weekly efsitora maintained equivalent glycemic control at 26 weeks, with A1C change of approximately -0.2% in both arms (patients entering the trial were already on basal insulin and had relatively well-controlled A1C at baseline).
The bottom line from the efficacy data: once weekly insulin for type 2 diabetes is not better than daily insulin at lowering A1C — and it does not claim to be. It is equivalent. The value proposition is not superior glucose lowering; it is equivalent glucose lowering with one-seventh the injection burden.
Who Is Once-Weekly Insulin For — and Who Should Avoid It?
If you have type 2 diabetes and currently take a daily basal insulin — or your doctor has told you that you may need to start basal insulin — you are in the broad population that the FDA approved Onswik to treat. But the label and the trial data draw a sharper boundary than “everyone with type 2 diabetes.”
Good candidates for once weekly insulin for type 2 diabetes include:
• Adults with type 2 diabetes who are insulin-naive and need to start basal insulin for the first time (QWINT-1, QWINT-2 populations)
• Adults with type 2 diabetes already on a stable daily basal insulin regimen who want to reduce their injection burden (QWINT-3 population)
• Patients on more complex insulin regimens (basal + mealtime insulin) who want to simplify the basal component (QWINT-4 population)
• People who travel frequently across time zones and find daily insulin timing disruptive — the weekly schedule and 4-day missed-dose window offer practical flexibility
• Adults with type 2 diabetes who use GLP-1 receptor agonists alongside basal insulin, as the QWINT-2 trial confirmed compatibility
Note: The decision to start or switch to once weekly insulin for type 2 diabetes should be made with your healthcare provider, who will consider your current A1C, hypoglycemia history, kidney and liver function, concurrent medications, and individual treatment goals.
Onswik is contraindicated in:
• People with type 1 diabetes. This is the group you must not overlook. The FDA label explicitly states that Onswik should not be used in type 1 diabetes due to an increased risk of severe hypoglycemia. If you have type 1 diabetes and are reading about once-weekly insulin, understand that this approval is for type 2 diabetes only — the QWINT trials enrolled zero type 1 patients, and the safety profile in that population is unknown and presumed unfavourable.
• Episodes of hypoglycemia. Do not take Onswik during an active low blood sugar episode.
• Known hypersensitivity to insulin efsitora alfa-gobe or any of the excipients in the formulation.
Use with extra caution and close monitoring in:
• Patients with liver or kidney impairment — insulin clearance is altered in these conditions, and the long half-life of efsitora means that effects of altered clearance are amplified
• Patients taking thiazolidinediones (TZDs such as pioglitazone) — the combination may exacerbate fluid retention and heart failure, a known class effect of TZDs with insulin
• People who are pregnant, planning to become pregnant, or breastfeeding — safety has not been established in these populations
• Children — Onswik is not approved for paediatric use, as safety and efficacy have not been established
• Patients with a history of severe, recurrent hypoglycemia — the long half-life makes hypoglycemic episodes potentially more prolonged and difficult to correct
The hope versus skepticism dynamic here is real, and it is worth addressing directly. If you are tired of daily injections — genuinely worn down by the relentlessness of it — the idea of once weekly insulin for type 2 diabetes sounds almost too good to be true. The data says it is not too good to be true: it works. But it is not a miracle, and it is not for everyone. The type 1 exclusion is absolute. The liver and kidney caveats are important. And anyone with brittle diabetes or a history of frequent, unpredictable hypoglycemic episodes should approach a 17-day-half-life insulin with particular caution — once it is in your system, you cannot turn it off quickly.
For the right patient — an adult with type 2 diabetes, on stable basal insulin or needing to start, without advanced kidney or liver disease, and with a desire to reduce injection burden — the risk-benefit calculus is favourable. For the wrong patient, it is not. The distinction matters.
Safety, Side Effects, and Dosing — What the Trials Found
Across the QWINT programme, once weekly insulin for type 2 diabetes demonstrated an overall safety profile similar to the daily basal insulins studied. This is an important finding because safety, not efficacy, was the open question heading into these trials. A novel Fc-fusion insulin with a 17-day half-life naturally raises concerns about prolonged hypoglycemia, unexpected immunogenicity, or accumulation effects that shorter-acting insulins avoid.
The trials largely put those concerns to rest — with the crucial caveat that the type 2 population studied was selected to exclude the highest-risk groups.
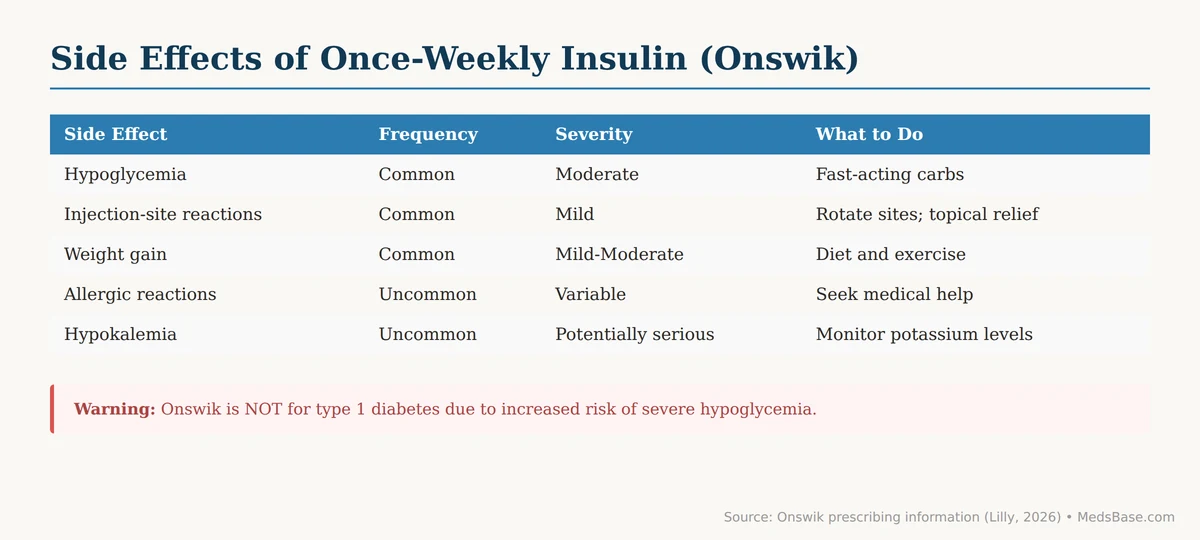
Here is the side effect profile, based on the integrated safety data from over 3,400 participants across QWINT 1-4:
| Side Effect | Frequency | Notes |
|---|---|---|
| Hypoglycemia (low blood sugar) | Common | Rates comparable to daily basal insulin comparators; severe hypoglycemia was rare in the type 2 trial population. Risk is highest during dose titration. |
| Injection site reactions | Common | Redness, swelling, or itching at the injection site. Typically mild and transient. Rotating injection sites reduces this risk. |
| Allergic reactions | Uncommon | Includes localised and, rarely, systemic allergic reactions. Stop Onswik and seek medical attention if you develop a rash over your whole body, trouble breathing, or facial swelling. |
| Lipodystrophy (skin thickening or pitting) | Uncommon | Can occur at injection sites if the same spot is used repeatedly. Rotating sites prevents this. Do not inject into thickened or pitted skin. |
| Itching (pruritus) | Moderate | Generalised itching, not necessarily at the injection site. Generally mild. |
| Rash | Moderate | May occur at the injection site or elsewhere on the body. |
| Swelling of hands and feet (peripheral oedema) | Moderate | Related to insulin’s sodium-retaining effects. Usually mild; more significant in patients taking TZDs. |
| Weight gain | Common | A known class effect of insulin therapy. Rates were comparable to daily basal insulin comparators in QWINT. |
| Hypokalemia (low potassium) | Uncommon | All insulins can lower serum potassium. Risk is higher in patients taking potassium-wasting diuretics. |
The hypoglycemia question deserves a closer look. Insulin-induced hypoglycemia is the safety concern that keeps both patients and doctors up at night, and a once-weekly insulin with a 17-day half-life raises the stakes. If you take too much daily insulin, the excess clears within 24 to 42 hours. If you take too much Onswik, the excess takes much longer to clear.
In the QWINT trials, rates of clinically significant hypoglycemia (blood glucose below 54 mg/dL) were comparable between once-weekly efsitora and daily comparators. Severe hypoglycemia — events requiring external assistance — was rare in both arms. But these were clinical trial populations with careful dose titration, regular glucose monitoring, and exclusion of patients at highest hypoglycemic risk. Real-world use will test these boundaries.
A practical safety recommendation embedded in the Onswik label: your healthcare provider should show you how to use the KwikPen before your first injection, and you should check your blood sugar as directed. Do not drive or operate heavy machinery until you know how Onswik affects you, and avoid alcohol or alcohol-containing medications while taking it.
Dosing specifics. Onswik comes in the KwikPen, a prefilled, single-patient-use pen available in two concentrations:
- U-500 (500 units/mL) — 3 mL pen containing 1,500 units total. Doses can be dialled in 5-unit increments, delivering up to 400 units in a single injection.
- U-1,000 (1,000 units/mL) — 3 mL pen containing 3,000 units total. Doses can be dialled in 10-unit increments, delivering up to 800 units in a single injection.
The concentration you need depends on your total weekly insulin requirement, which your doctor will calculate from your current daily dose (if switching) or estimated insulin needs (if starting). The key dosing principles:
- Inject Onswik once each week, on the same day of the week.
- If you need to change your injection day, wait at least 4 days since your last dose before starting the new schedule.
- If you miss a dose, take it as soon as possible within 4 days (96 hours) — then continue your regular schedule. If more than 4 days have passed, skip the missed dose and take your next scheduled dose.
- Never take two doses in the same week unless specifically instructed by your healthcare provider. If you accidentally double-dose, skip the following week’s dose and contact your doctor.
- Rotate injection sites (stomach, thigh, buttock, upper arm) with each dose. Do not inject into skin that is thickened, pitted, bruised, or tender.
- Use a new needle for every injection. Do not reuse or share needles.
- Do not dilute or mix Onswik with any other insulin or liquid medication.
The 4-day missed-dose window is genuinely useful — it means that if you forget your Tuesday injection and remember on Friday, you can still take it and stay on your Tuesday schedule. No daily insulin offers this flexibility. But it also means you must track your doses carefully: the penalty for an accidental double-dose is a skipped week, and the penalty for a truly forgotten dose (beyond the 96-hour window) is a full week without basal insulin, which your doctor needs to plan for with a contingency strategy.
Once-Weekly Insulin vs Daily Insulin — A Direct Comparison
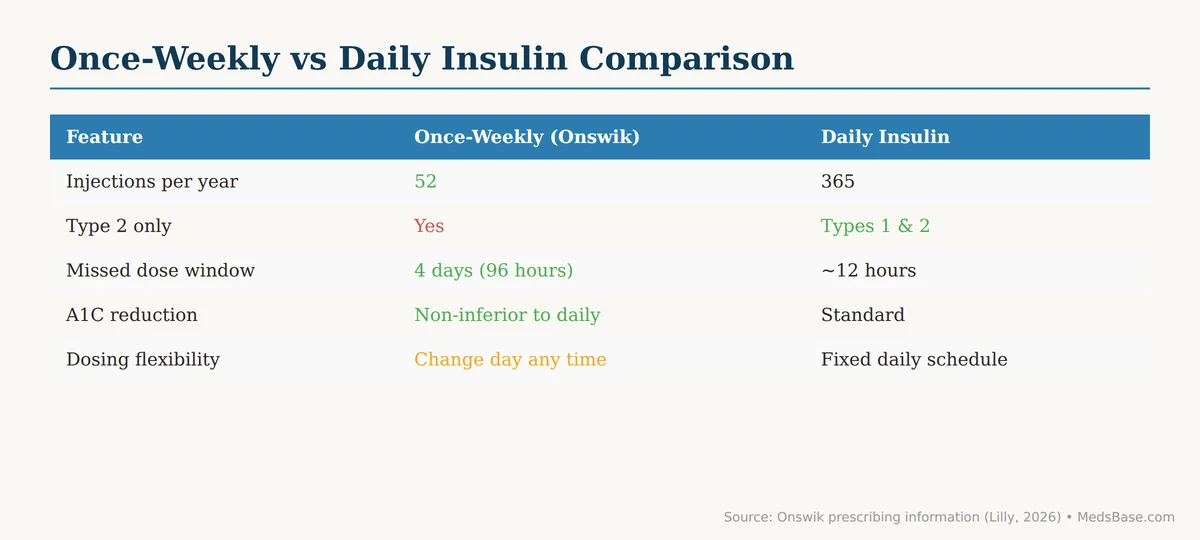
Putting once weekly insulin for type 2 diabetes side by side with the daily basal insulins you may already use helps clarify what changes — and what stays the same.
| Feature | Once-Weekly Insulin (Onswik) | Daily Basal Insulin (degludec/glargine) |
|---|---|---|
| Injection frequency | 1 per week (52/year) | 1 per day (365/year) |
| Active ingredient | Insulin efsitora alfa-gobe (Fc-fusion protein) | Insulin degludec or insulin glargine (modified human insulin analogues) |
| Half-life | ~17 days | ~25 hours (degludec); ~12 hours (glargine) |
| Duration of action | 7 days (beyond 7 days at lower levels) | ~24 hours (glargine); >42 hours (degludec) |
| Glycemic control | Non-inferior A1C reduction vs daily basal insulin | Established standard of care |
| Missed-dose window | Up to 4 days (96 hours) | Same day only; missed dose = skipped day |
| Time to steady state | Several weeks (~3-4 half-lives) | 2-4 days (glargine); 2-3 days (degludec) |
| Reversibility | Slow — effects persist for days after stopping | Rapid — cleared within 24-42 hours |
| Type 1 diabetes use | Contraindicated | Standard of care |
| Approved populations | Adults with type 2 diabetes only | Adults and children with type 1 or type 2 diabetes |
| Concurrent GLP-1 RA use | Supported (QWINT-2 data) | Supported (routine clinical practice) |
The reversibility point is the one that deserves the most reflection. With daily insulin, if your dose is too high, you feel the hypoglycemia, you eat some glucose, and the insulin clears within a day. With once weekly insulin for type 2 diabetes, you correct the hypoglycemia with glucose today — but the insulin that caused it is still there tomorrow and the day after. This is the practical trade-off baked into the long half-life: you trade daily-injection burden for reduced reversibility. For patients with stable insulin requirements who dose carefully, the trade-off makes sense. For patients with highly variable day-to-day insulin sensitivity — due to fluctuating activity levels, variable meal patterns, or unpredictable gastric emptying — the reduced flexibility may outweigh the convenience.
Practical Guidance for Starting Once-Weekly Insulin
If you and your doctor decide that once weekly insulin for type 2 diabetes is right for you, here is what the process looks like in practice — and the mistakes worth avoiding.
Step 1 — Confirm you are a candidate. Before anything else, your doctor should confirm that you have type 2 diabetes (not type 1), review your kidney and liver function (blood tests), assess your hypoglycemia history, and check whether you are taking any TZDs. If you are pregnant, planning pregnancy, or breastfeeding, Onswik is not recommended pending safety data.
Step 2 — Calculate the starting dose. If you are switching from daily basal insulin, your doctor will convert your total weekly basal insulin requirement into a single weekly Onswik dose using the conversion guidance in the prescribing information. If you are starting basal insulin for the first time, the starting dose follows a fixed-dose escalation protocol similar to the one used in QWINT-1.
Step 3 — Learn the pen. The Onswik KwikPen is a prefilled device that differs from other insulin pens, particularly in the way doses are dialled. Your healthcare provider — not a YouTube video — should demonstrate proper use before your first injection. Pay close attention to the dose window: the U-500 pen dials in 5-unit increments, and the U-1,000 pen dials in 10-unit increments. A dosing error at these concentrations can mean a significant overdose or underdose.
Step 4 — Pick your injection day and protect it. The day you choose becomes your weekly routine. Set a recurring phone alarm, mark your calendar, or use a medication reminder app — whatever system you will actually follow. Consistency matters not just for glycemic control but because the once-weekly schedule is unfamiliar and easier to forget than a daily habit. Consider a backup reminder system: if your phone dies, how will you know it is injection day?
Step 5 — Monitor and be patient during the loading phase. Because efsitora has a 17-day half-life, it takes several weeks to reach steady-state levels in your body. Your blood sugar readings in week one and week two do not reflect the full effect of your dose. Do not conclude that the dose is “not working” and self-adjust upward — impatience during the loading phase is the most common cause of early hypoglycemia with long-half-life insulins. Your doctor should schedule a follow-up at 4 to 6 weeks to review your glucose logs and adjust the dose.
Step 6 — Have a hypoglycemia plan that accounts for the long half-life. With daily insulin, treating a mild low means 15 grams of fast-acting carbohydrate and rechecking in 15 minutes. That protocol still applies to Onswik-induced hypoglycemia, but you need to be aware that the blood sugar drop may recur hours later because the insulin is still active. Keep a fast-acting glucose source with you through the full week — not just on injection day — and know the signs of hypoglycemia (dizziness, shakiness, sweating, confusion, blurred vision, fast heartbeat) well enough to recognise them early.
Mistakes to avoid:
- Assuming once-weekly insulin means you check your blood sugar less often. It does not. Glucose monitoring frequency should follow your doctor’s recommendation — at minimum, fasting glucose checks remain important for dose titration, especially during the first 4-6 weeks.
- Self-adjusting the dose during the first month. Wait for the steady state.
- Injecting into the same spot every week. Rotate sites to prevent lipodystrophy, which can impair insulin absorption unpredictably.
- Stopping daily basal insulin completely on day one of the switch without confirming the transition protocol with your doctor. The prescribing information includes specific guidance for the overlap or transition period.
- Using Onswik in an insulin pump or injecting it into a vein or muscle. Onswik is for subcutaneous injection only.
- Assuming that once weekly insulin for type 2 diabetes means you do not need mealtime insulin if you were previously on a basal-plus-bolus regimen. Onswik replaces your basal insulin only — your mealtime insulin regimen continues unchanged unless your doctor adjusts it.
Once weekly insulin for type 2 diabetes is one option in a broad landscape of diabetes medications. If you are exploring treatment options — whether oral medications, GLP-1 receptor agonists, or insulin products — browse our diabetes medication category for a full overview of accessible options. If you are currently on metformin and concerned about side effects, read our guide to metformin gastrointestinal side effects for practical management strategies.
Related Reading
- Diabetes Medications — Complete Guide to Type 2 Diabetes Treatment Options
- Metformin Gastrointestinal Side Effects — What They Are and How to Manage Them
- GLP-1 Medications for Sleep Apnea — What the Research Shows
Frequently Asked Questions
What is once-weekly insulin for type 2 diabetes?
Once weekly insulin for type 2 diabetes is a long-acting basal insulin injection taken once per week instead of once per day. The first product in this class, Onswik (insulin efsitora alfa-gobe), was approved by the FDA on September 24, 2026. It uses a novel Fc-fusion protein design that extends the insulin half-life to approximately 17 days, enabling steady background insulin coverage from a single weekly injection. It is indicated for adults with type 2 diabetes and is not approved for type 1 diabetes.
Is once-weekly insulin FDA approved?
Yes. The FDA approved once weekly insulin for type 2 diabetes (brand name Onswik) on September 24, 2026, following the QWINT Phase 3 clinical trial programme that enrolled over 3,400 adults with type 2 diabetes. This was the fourth global approval for Onswik, following regulatory actions by the European Medicines Agency, Mexico’s COFEPRIS, and Japan’s PMDA. The approval is specifically for adults with type 2 diabetes mellitus.
How does once-weekly insulin work in the body?
Once weekly insulin for type 2 diabetes works through an Fc-fusion protein design. Insulin efsitora alfa consists of a single-chain insulin analogue fused to a human IgG2 Fc domain. After subcutaneous injection, the Fc domain engages the neonatal Fc receptor (FcRn), which recycles the molecule back into circulation rather than allowing it to be degraded. This recycling mechanism, combined with attenuated insulin receptor binding, extends the half-life to approximately 17 days — long enough for once-weekly dosing. The result is a flat pharmacokinetic profile with no pronounced peak and sustained basal insulin activity across the full seven-day interval.
Is once-weekly insulin as effective as daily insulin?
Yes — it is equally effective, not more effective. Across four QWINT Phase 3 clinical trials, once weekly insulin for type 2 diabetes met the primary endpoint of non-inferior A1C reduction compared to daily basal insulin (insulin degludec or insulin glargine). In QWINT-2, published in the New England Journal of Medicine, efsitora and degludec both reduced A1C by approximately 1.3 percentage points from baseline over 52 weeks. The value proposition is equivalent glycemic control with one-seventh the injection burden — not superior glucose lowering.
Who should NOT use once-weekly insulin?
The single most important exclusion is type 1 diabetes — once weekly insulin for type 2 diabetes is contraindicated in type 1 diabetes due to an increased risk of severe hypoglycemia. Other groups who should not use Onswik include: people currently experiencing hypoglycemia, anyone with a known hypersensitivity to insulin efsitora alfa-gobe or its excipients, pregnant or breastfeeding women (safety not established), and children (not approved for paediatric use). Patients with significant liver or kidney impairment, a history of severe recurrent hypoglycemia, or those taking TZDs should be monitored with extra caution if prescribed Onswik.
What are the side effects of once-weekly insulin?
The most common side effects of once weekly insulin for type 2 diabetes are hypoglycemia (low blood sugar), injection site reactions (redness, swelling, itching), allergic reactions, lipodystrophy (skin thickening or pitting at injection sites), itching, rash, swelling of the hands and feet (peripheral oedema), and weight gain. The side effect profile in the QWINT clinical trials was comparable to that of daily basal insulins. Severe allergic reactions and severe hypoglycemia were rare in the trial population. Hypokalemia (low potassium) is an uncommon but potentially serious side effect common to all insulins.
Can I switch from daily insulin to once-weekly insulin?
If you have type 2 diabetes and are currently on a stable daily basal insulin regimen, you may be a candidate to switch to once weekly insulin for type 2 diabetes. The QWINT-3 trial specifically studied this scenario — 986 adults on basal insulin switched from daily degludec to once-weekly efsitora and maintained equivalent glycemic control. The switch requires a dose conversion calculation by your doctor (your total weekly basal insulin dose is converted to a single weekly Onswik dose) and careful monitoring during the transition period. Do not attempt to calculate the dose conversion yourself.
How much does Onswik cost and when will it be available?
Lilly has stated that Onswik will be available in the United States “in the coming months” following the September 24, 2026 approval. Exact pricing has not been publicly disclosed at the time of writing. As with most branded insulin products, the list price and the out-of-pocket cost will depend on your insurance coverage, formulary placement, and eligibility for manufacturer savings programmes. Check with your insurance provider and pharmacy benefit manager for coverage details once the product launches, and enquire about Lilly’s patient assistance programmes if cost is a concern.
The Bottom Line
Once weekly insulin for type 2 diabetes is the most meaningful innovation in basal insulin delivery since degludec extended the dosing window beyond 24 hours — and arguably the most significant since the introduction of long-acting insulin analogues replaced NPH. The clinical evidence is clear, the FDA approval is real, and the practical benefit — 52 injections per year instead of 365 — is substantial for the right patient.
But the line between “right patient” and “wrong patient” is drawn more sharply here than with daily basal insulins. Type 1 diabetes is an absolute contraindication. Advanced kidney or liver disease demands heightened caution. A history of severe or unpredictable hypoglycemia should give any prescriber — and any patient — serious pause before committing to an insulin that stays in the body for the better part of a month after the last injection. The convenience is real, but so is the irreversibility.
If you have type 2 diabetes and the daily injection burden has worn you down — if you have been hoping for a simpler option without sacrificing glycemic control — Onswik may well be that option. The conversation to have with your doctor is straightforward: “Given my A1C, my current insulin regimen, and my medical history, am I a candidate for once-weekly insulin, and what would switching look like for me?”
Your immediate next step is not to make a decision — it is to get informed enough to have that conversation productively. Review your recent A1C results. Note your current basal insulin dose and how stable it has been over the past several months. Think about how often you travel, how reliably you remember your daily injections, and how much the daily burden actually affects your quality of life. These are the factors that determine whether once weekly insulin for type 2 diabetes is worth pursuing.
For those managing type 2 diabetes and exploring treatment options, browse our complete diabetes medication category to understand what is available without prescription. And if GLP-1 medications are part of your treatment picture, read our article on GLP-1 medications for sleep apnea — a related topic with emerging research that may affect your broader diabetes management strategy.
Reviewed by Morgan Ellis, Medical Content Reviewer
Last updated: September 26, 2026

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.