








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
switching from GLP-1 injections to pills for weight loss — Switching from GLP-1 Injections to Pills for Weight Loss: 5 Key Facts from the Latest Research. Read on for an evidence-backed guide covering everything you need to know.

Key Takeaways
- A 2026 study found people switching from GLP-1 injections to the oral Wegovy pill lost an additional 4.1% of body weight over 3 months — the pill didn’t just maintain, it added to the results.
- Two oral GLP-1s are FDA-approved today (Rybelsus and higher-dose oral semaglutide branded as Wegovy pill), with a third — Orforglipron (Foundayo) — showing up to 14% total body-weight loss in trials.
- Oral GLP-1s use an absorption technology called SNAC that protects the molecule from stomach acid — but it also means you must take the pill on an empty stomach with no more than 4 oz of water and wait 30 minutes before eating. Skip this rule and you may absorb less than 1% of the dose.
- Side-effect profiles are similar to injections (nausea, vomiting, diarrhea), but the daily oral routine gives you more day-to-day control — if side effects hit, they fade faster than with a weekly injection already in your system.
- Switching is not a DIY decision — the overlap protocol, equivalent dose conversion, and monitoring require a healthcare provider who knows your full history.
Switching from GLP-1 injections to pills for weight loss — imagine this: you have lost 20 pounds on a weekly GLP-1 injection over the last six months. The results are real, but the needle routine is wearing on you. Travel means packing a refrigerated pen. The Friday-night shot leaves you nauseated all weekend. So you wonder: could a daily pill work just as well — or even better?
Switching from GLP-1 injections to pills for weight loss — that question, asked by millions of people taking injectable GLP-1s, now has a data-backed answer. New 2026 research shows that switching from GLP-1 injections to pills for weight loss is not just about convenience — for many people, the switch actually produces additional weight loss. If you have been considering switching from GLP-1 injections to pills for weight loss, the data has never been stronger.
Switching from GLP-1 injections to pills for weight loss — by the end of this article, you will know which oral GLP-1s are available, how their results compare to what you are taking now, who is the best candidate for a switch, and exactly what a safe transition looks like. One finding — the absorption rule that can reduce your dose to near zero — is something even experienced users get wrong.
Switching from GLP-1 injections to pills for weight loss: What Are GLP-1 Medications and Why the Shift to Pills?
Switching from GLP-1 injections to pills for weight loss — glucagon-like peptide-1 (GLP-1) receptor agonists work by mimicking a natural hormone that slows stomach emptying, increases insulin release, and signals fullness to the brain. The injectable versions — semaglutide (Ozempic, Wegovy), tirzepatide (Mounjaro, Zepbound), liraglutide (Saxenda), and dulaglutide (Trulicity) — have dominated the obesity and diabetes treatment landscape for years.
Quick Answer Box: Oral GLP-1 medications deliver the same active ingredient as the injections, but in a tablet form that uses a special absorption enhancer (SNAC) to survive stomach acid. They are taken daily rather than weekly, require strict fasting before and after dosing, and — according to 2026 data — can produce results comparable to or exceeding injectable formulations for some people switching mid-treatment.
Switching from GLP-1 injections to pills for weight loss — but here is the thing: oral GLP-1s are not simply “the same drug in a pill.” The molecule is identical, but the delivery system changes everything — from how much reaches your bloodstream to how your body tolerates it day by day.
The shift from injections to pills — and the growing interest in switching from GLP-1 injections to pills for weight loss — reflects two major forces. First, patient preference: surveys consistently show that a significant proportion of GLP-1 users would prefer a non-injectable option. Needle fatigue, travel logistics, refrigeration requirements, and simple dislike of injections all push people toward the oral route. Second, pharmaceutical innovation: the development of absorption-enhancement technologies like SNAC (sodium N-[8-(2-hydroxybenzoyl)amino]caprylate) made it possible to deliver large peptide molecules like semaglutide through the stomach lining without them being destroyed by gastric acid.
The result? By late 2026, three distinct oral GLP-1 pathways exist: Rybelsus (low-to-moderate dose oral semaglutide, approved for type 2 diabetes), higher-dose oral semaglutide branded as the Wegovy pill (approved for weight loss), and the investigational Orforglipron / Foundayo (a non-peptide oral GLP-1 that does not require fasting, currently under FDA review).
Switching from GLP-1 injections to pills for weight loss: How Do Oral GLP-1s Work?

The mechanism of action — GLP-1 receptor agonism — is identical to the injectable versions. What differs is everything that happens between the moment you swallow the tablet and the moment the drug enters your bloodstream.
When you take an oral GLP-1 tablet, the semaglutide molecule faces a hostile environment: stomach acid can break it apart before it ever reaches the absorption site in the gastric mucosa. This is where SNAC comes in. SNAC temporarily raises the local pH around the tablet, creating a micro-environment where semaglutide remains stable long enough to cross the stomach lining. Without SNAC, oral semaglutide would have near-zero bioavailability — you would essentially be swallowing an expensive placebo.
Research Spotlight: The development of SNAC technology was a pharmaceutical breakthrough. Before SNAC, delivering peptide drugs orally was considered nearly impossible because peptides are large, fragile molecules that digestive enzymes and stomach acid destroy rapidly. The STEP clinical trial programme demonstrated that oral semaglutide with SNAC achieves clinically meaningful bioavailability — approximately 0.4 to 1% of the ingested dose reaches systemic circulation. It sounds tiny, but because the starting dose is high enough, the absolute amount that gets through is therapeutically effective.
Here is where it gets interesting — and where many people switching from GLP-1 injections to pills for weight loss make a critical mistake. The decision to pursue switching from GLP-1 injections to pills for weight loss hinges on understanding exactly how oral absorption works, and getting it wrong means the pill delivers a fraction of what the injection does.
The SNAC-based absorption is extremely sensitive to the stomach environment. Food, more than 4 ounces of water, or any other medication taken at the same time can dilute the local pH buffer that SNAC creates. The result? Bioavailability can drop to less than 0.1% — meaning you might absorb only one-tenth of your intended dose. The prescribing instructions are unforgiving for a reason: take the tablet first thing in the morning, on an empty stomach, with no more than 4 oz (about 120 mL) of plain water, and wait at least 30 minutes before eating, drinking, or taking any other oral medication.
By comparison, Orforglipron (Foundayo) takes a fundamentally different approach. Instead of being a peptide that needs protection, it is a small-molecule GLP-1 agonist — chemically stable enough to survive the GI tract without an absorption enhancer. It does not require fasting, which is one reason it is generating so much excitement: it removes the biggest practical barrier to oral GLP-1 use.
Who Should Consider Switching from GLP-1 Injections to Pills? — Switching from GLP-1 injections to pills for weight loss Explained
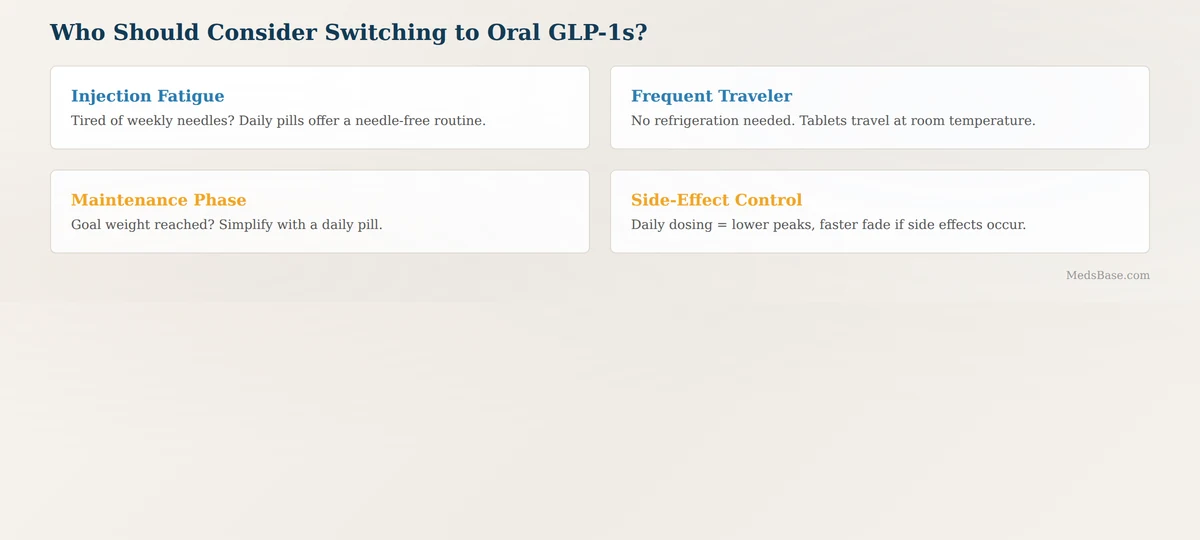
Not everyone on an injectable GLP-1 is a good candidate for switching. But for several specific profiles, the data suggests that switching from GLP-1 injections to pills for weight loss may be more than just a convenience upgrade — it could actually improve results.
Q: Who Is This For?
A: – People with needle phobia or injection-site reactions (rashes, nodules, lipohypertrophy) who dread their weekly shot. – Frequent travellers who find refrigerated injectable pens impractical — oral tablets travel at room temperature. – Those in the weight-maintenance phase who have reached their goal and want a simpler daily routine rather than a weekly medication event. – People who experience intense side effects from the peak plasma concentration of a weekly injection — daily oral dosing produces a flatter pharmacokinetic curve, with lower peak concentrations that some patients tolerate better. – Individuals whose insurance or budget situation makes a daily generic-grade pill more accessible than a branded weekly injection.
Q: Who Should Avoid It?
A: – Anyone with gastroparesis or severe GI motility disorders — oral GLP-1s slow gastric emptying further, and the fasting requirement may be dangerous. – People with unpredictable schedules who cannot reliably take a pill first thing in the morning and wait 30 minutes — missing doses with oral GLP-1s leads to inconsistent blood levels and reduced efficacy. – Those with severe nausea as a GLP-1 side effect — while oral forms may produce a flatter side-effect curve, the daily exposure means you face potential nausea every single morning rather than once a week. – Individuals who struggle with medication adherence — a once-weekly injection is, for some, easier to remember than a daily pill with strict timing rules. – Anyone with a history of medullary thyroid carcinoma or Multiple Endocrine Neoplasia syndrome type 2 (MEN2) — this is a class-wide contraindication for all GLP-1 receptor agonists, oral or injectable.
Contextual product mention: MedsBase offers a range of GLP-1 options for weight management. If you are considering switching from GLP-1 injections to pills for weight loss, browse our Weight Loss category to compare available formulations and strengths. Patients who have successfully navigated switching from GLP-1 injections to pills for weight loss often report that the daily pill routine became second nature within weeks.
What the Latest Research Says
The evidence base for oral GLP-1s has expanded dramatically in 2026. Here are the key findings that matter if you are considering a switch.
Research Summary Table
| Study | Year | Finding | Source |
|---|---|---|---|
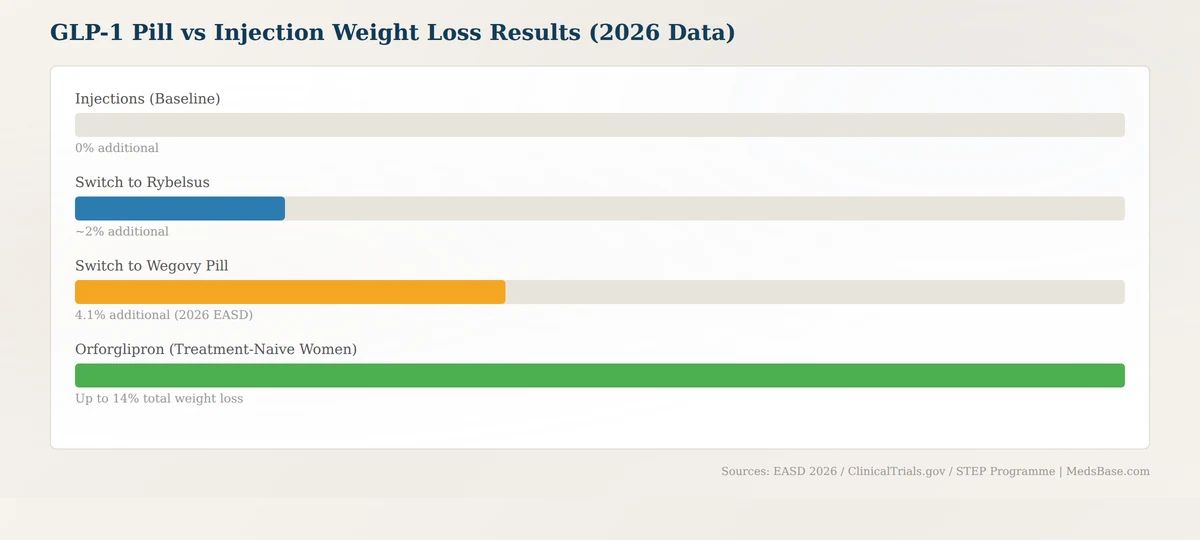
| Oral semaglutide switch analysis | 2026 (EASD) | Patients who switched from injectable GLP-1s to the Wegovy pill achieved an additional 4.1% mean body-weight reduction over 3 months | EASD 2026 Conference |
| Orforglipron women subgroup | 2026 | Women taking oral Orforglipron (Foundayo) lost up to 14% of baseline body weight — comparable to injectable GLP-1 results | ClinicalTrials.gov |
| PIONEER programme (oral semaglutide) | 2019-2024 | Oral semaglutide 14 mg reduced HbA1c by 1.3-1.5% and body weight by 4.4 kg vs placebo across multiple trials | PubMed / Novo Nordisk |
| STEP UP sub-analysis (semaglutide liver fat) | 2026 | Semaglutide reduced liver fat to normal levels in 9 out of 10 adults with obesity and excess liver fat | PubMed |
| Orforglipron Phase 3 | 2025-2026 | Non-peptide oral GLP-1 without fasting requirement; weight loss comparable to injectable semaglutide 2.4 mg | FDA |
What this means for you: The oral GLP-1 pipeline is no longer a promise — it is delivering. The 4.1% additional weight-loss finding in the switch study is particularly important because it challenges the assumption that injectable GLP-1s are always superior. For patients who have plateaued on an injectable, switching to an oral formulation may actually restart weight loss. The Orforglipron data is equally significant: a non-fasting oral GLP-1 achieving injectable-level results would fundamentally change the treatment landscape.
The STEP UP sub-analysis provides another layer: many people on GLP-1s are simultaneously improving their liver health — an effect that seems robust across both oral and injectable formulations.
Oral GLP-1 Options Head-to-Head
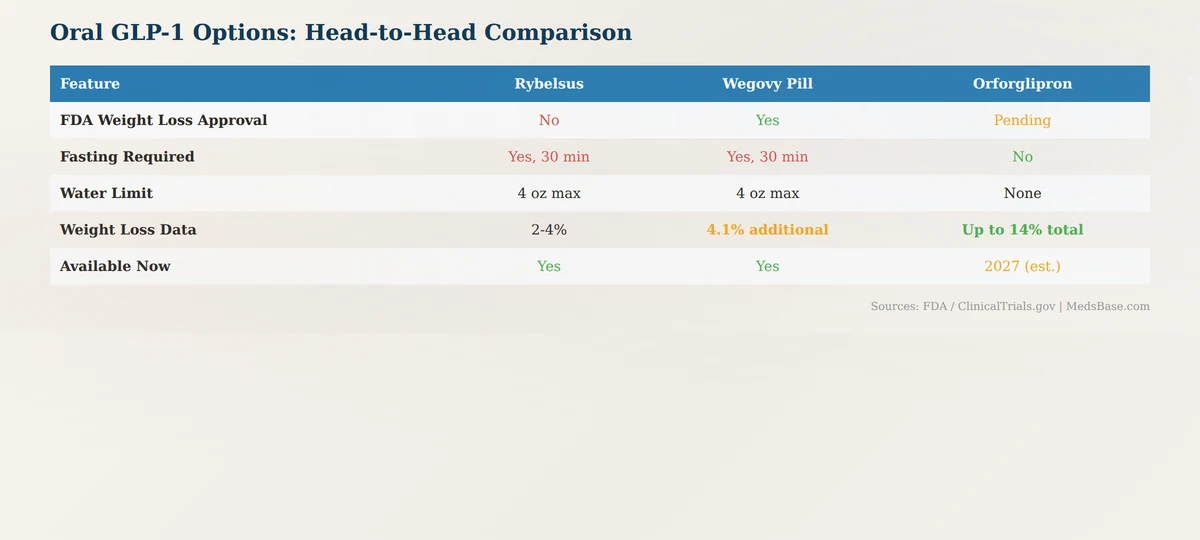
There is no single “best” oral GLP-1 — the right choice depends on whether you are switching from an injectable, starting fresh, treating diabetes, or targeting weight loss.
| Feature | Rybelsus (oral semaglutide 3/7/14 mg) | Wegovy Pill (oral semaglutide 25/50 mg) | Orforglipron / Foundayo (investigational) |
|---|---|---|---|
| FDA-approved for weight loss | No (diabetes only) | Yes | Under review (expected 2027) |
| Dosing frequency | Daily | Daily | Daily |
| Fasting required | Yes — 30 min before food/drink | Yes — 30 min before food/drink | No |
| Water limit with dose | Max 4 oz (120 mL) | Max 4 oz (120 mL) | None |
| Room-temperature stable | Yes | Yes | Yes |
| Weight loss data | ~2-4% additional on switch | 4.1% additional over 3 months (2026 EASD data) | Up to 14% total in women (Phase 3) |
| GI side-effect profile | Nausea 15-20%, diarrhea 10%, vomiting 8% | Similar to Rybelsus at equivalent exposure | Similar class effects; fasting-free may improve tolerability |
| Cost (US list, approximate) | ~$900-1,000/month | ~$1,300/month | Not yet priced |
Q: Which one fits which situation?
A: – If you have type 2 diabetes and want an oral option now, Rybelsus is your evidence-backed, FDA-approved choice. – If you are switching from GLP-1 injections to pills for weight loss specifically, and you can handle the fasting requirement, the Wegovy pill’s higher-dose formulation and weight-loss-specific approval make it the logical transition target — with the 2026 4.1% additional-loss data supporting the switch. – If you cannot or will not comply with the fasting protocol, wait for Orforglipron (if it receives FDA approval). A non-fasting oral GLP-1 removes the biggest adherence barrier. Check the MedlinePlus GLP-1 overview for the latest regulatory updates.
Safety, Side Effects, and What to Expect When Switching
The side-effect profile of oral GLP-1s is broadly consistent with the injectable class — but the daily dosing pattern changes how patients experience it.
Side Effects Table
| Side Effect | Frequency (Oral Semaglutide) | Severity | What To Do |
|---|---|---|---|
| Nausea | 15-20% | Mild to moderate | Take with minimal water; start at lowest dose; if severe, discuss dose reduction or anti-nausea medication with your provider |
| Diarrhea | 8-12% | Mild | Usually transient — resolves within 2-4 weeks; stay hydrated; avoid high-fat meals around dosing time |
| Vomiting | 5-8% | Mild to moderate | If persistent, the dose may be too high — contact your provider; do not double-dose if you vomit shortly after taking the tablet |
| Constipation | 5-7% | Mild | Increase water and fibre intake between doses; gentle exercise helps |
| Abdominal pain | 4-6% | Mild | Take with minimal water; eat smaller meals; if severe, rule out gallbladder issues with your provider |
| Headache | 3-5% | Mild | Usually resolves; ensure adequate hydration throughout the day after the fasting window ends |
| Decreased appetite | 10-15% | Mild | This is part of the mechanism — ensure you are still eating enough protein and nutrients; consider smaller, more frequent meals after the fasting window |
Here is what often surprises people switching from GLP-1 injections to pills for weight loss: the side effects come and go faster. For anyone weighing the decision of switching from GLP-1 injections to pills for weight loss, this daily control over side-effect exposure can be a deciding factor.
With a weekly injection, the drug is in your system at a sustained level for seven days. If you have a bad reaction to a dose, you are in for a rough week. With a daily oral tablet, the peak plasma concentration is lower and the drug clears more rapidly. If a dose causes nausea, you are uncomfortable for hours — not days. And because you take the pill every morning, you have day-by-day control: your provider can adjust the dose upward or downward much more nimbly than with a weekly injection.
The absorption mistake that can undermine your results. An open-looped question from earlier — about experienced users getting the absorption rule wrong — resolves here. The most common error is drinking too much water with the tablet, or eating too soon. The SNAC buffer needs a specific, concentrated environment. More water dilutes it. Food changes the gastric pH. Both reduce absorption dramatically. A second common error: taking the pill at bedtime to “sleep through the fasting window.” Gastric motility slows during sleep, and the tablet may not reach the optimal absorption site. Morning dosing, on an empty stomach, remains the standard.
Serious but rare risks: As with all GLP-1 receptor agonists, the class carries a boxed warning for thyroid C-cell tumours (observed in rodent studies; human relevance unclear). Pancreatitis, gallbladder disease, and acute kidney injury have been reported. These risks are class-wide — they apply to injectable and oral forms equally — and the absolute incidence is low. Discuss your personal risk factors with your prescriber before switching.
Medical disclaimer: This article is for informational purposes only and does not constitute medical advice. Switching from GLP-1 injections to pills for weight loss should only be done under the supervision of a qualified healthcare provider who knows your full medical history. The risks and benefits of switching from GLP-1 injections to pills for weight loss are individual, and no online article can substitute for a personalised clinical assessment. Never change your medication regimen without consulting your doctor.
How to Switch Safely: A Practical Guide
If you and your provider decide that switching from GLP-1 injections to pills for weight loss is right for you, here is what a safe, evidence-informed transition looks like.
Step 1: Dose Equivalence Mapping Your provider will calculate an equivalent oral dose based on your current injectable dose. As a general principle, the conversion is not 1:1 — oral semaglutide has lower bioavailability, so the prescribed oral dose in milligrams will be higher than your injectable dose. For example, if you take semaglutide 1.0 mg weekly by injection, your provider might start you on Rybelsus 7 mg daily or Wegovy pill 25 mg daily and titrate based on tolerance and response.
Step 2: Overlap Protocol In most cases, you will not stop the injection cold turkey and start the pill the next day. The standard approach is an overlap period: take your last injection, wait until you would normally take your next dose (one week), and — instead of that next injection — begin the oral tablet the following morning. This prevents a gap in GLP-1 receptor coverage that could trigger rebound hunger or blood-sugar fluctuations.
Step 3: Titration and Monitoring (weeks 1-4) The first month is about finding the right oral dose. Your provider will typically start you at a lower dose and increase every 2-4 weeks based on tolerability. Track your weight, blood glucose (if diabetic), and side effects daily for the first two weeks. A simple notes-app log works fine. If nausea does not improve by week 2, ask about a slower titration schedule.
Step 4: Full Transition and Long-Term Management By weeks 4-8, most people have stabilised on their maintenance oral dose. From here, the routine is: pill every morning, on an empty stomach, 30 minutes before anything else. Set a phone alarm. Keep the tablets in your bathroom or kitchen — room temperature, no refrigeration needed. That daily rhythm becomes automatic faster than most people expect.
Common mistakes when switching:
- Forgetting the 30-minute wait — eat or drink too soon and you will absorb a fraction of the dose. Set a timer.
- Taking the tablet with coffee — acidic beverages disrupt the SNAC buffer. Plain water only.
- Skipping doses because “I feel fine” — oral GLP-1s need daily consistency for plasma levels to stay therapeutic. A missed dose here and there will not ruin your progress, but a pattern of skipping will.
- Doubling up after a missed dose — if you forget one morning, take it as soon as you remember, unless it is close to the next day’s dose. Never take two tablets in one day.
Second contextual product mention: If you are ready to explore oral GLP-1 options after switching from GLP-1 injections to pills for weight loss, MedsBase stocks a range of formulations. See the current Weight Loss collection for available strengths and formats.
Related Reading
- GLP-1 Medications Beyond Weight Loss: What Else These Drugs Can Do — The liver, heart, and brain benefits emerging from 2026 research
- Increasing Ozempic Dose vs Switching to Mounjaro: A Clinical Decision Guide — Today’s companion post: if pills aren’t your answer, should you escalate or change drugs?
- Rybelsus: Weight Loss, Dosing, and Cost Guide — A deeper dive into the oral semaglutide option already on the market
Frequently Asked Questions
Q: Can you switch from Ozempic to a pill?
A: Yes, and a 2026 study showed that switching from GLP-1 injections to pills for weight loss can produce additional results. Patients who transitioned from an injectable GLP-1 to the Wegovy pill lost an additional 4.1% of body weight over 3 months. The switch must be dose-equivalent and supervised — your provider maps your current injectable dose to a starting oral dose and typically uses an overlap protocol.
Q: Does the Wegovy pill work as well as the injection?
A: The data suggests yes — and for people switching mid-treatment, it may actually outperform continued injections. The 2026 EASD switch study showed the Wegovy pill group lost an additional 4.1% beyond what injectables had already achieved. For treatment-naive patients, the oral options (Rybelsus, Wegovy pill, and the investigational Orforglipron) produce weight-loss results in the same range as injectable formulations when taken as prescribed.
Q: What happens when you stop GLP-1 injections?
A: GLP-1 receptor agonists — injectable or oral — are not a cure; they are a treatment. When you stop, the appetite suppression, delayed gastric emptying, and insulin-sensitising effects fade, typically over 1-2 weeks for oral forms and 4-5 weeks for injectable forms (due to the longer half-life of weekly injections). Most people experience some weight regain. This is why switching from GLP-1 injections to pills for weight loss, rather than stopping entirely, is the recommended path for anyone who wants to maintain results. Patients contemplating switching from GLP-1 injections to pills for weight loss should view this as a continuation strategy, not a treatment holiday.
Q: Is oral semaglutide as effective as injectable?
A: At equivalent systemic exposure, the mechanism is the same — the active molecule is identical. The key variable is bioavailability. Injectable semaglutide has near-100% bioavailability; oral semaglutide ranges from 0.4% to 1%. But because oral dosing is daily (vs weekly for injectable) and the absolute milligram dose is much higher, the area under the curve (total drug exposure over time) can be comparable. The 2026 switch-study data confirms that oral formulations can deliver results comparable to injectables, and in some cases exceed them.
Q: How much weight can you lose on oral GLP-1?
A: Results vary by formulation and individual response. Rybelsus (oral semaglutide for diabetes) produces 2-4% body-weight reduction. The Wegovy pill (higher-dose oral semaglutide for weight loss) delivered an additional 4.1% among switchers in 2026 data. Orforglipron produced up to 14% total body-weight loss in Phase 3 trials — comparable to injectable semaglutide 2.4 mg. These numbers depend heavily on adherence to the fasting protocol (for Rybelsus and Wegovy pill).
Q: What are the side effects of oral GLP-1 medications?
A: The side-effect profile mirrors injectable GLP-1s: nausea (15-20%), diarrhea (8-12%), vomiting (5-8%), constipation (5-7%), decreased appetite (10-15%). The difference: because the oral tablet produces lower peak concentrations and a daily rather than weekly cycle, side effects tend to be shorter-lived and easier to manage day to day. The daily fasting requirement is a practical burden — but also a built-in adherence reminder.
Q: Do oral GLP-1s require refrigeration?
A: No — this is one of the major practical advantages. Injectable GLP-1 pens must be refrigerated until first use (with some allowing room-temperature storage for a limited period after opening). Oral GLP-1 tablets are stable at room temperature — no refrigeration, no cold-chain logistics, no anxiety about leaving your medication in a hot car. For anyone who travels frequently or lives in a warm climate, this is a meaningful quality-of-life upgrade.
Q: Can I take oral GLP-1 with other medications?
A: The absorption window creates a practical challenge. Because you must take the oral GLP-1 tablet first thing in the morning on an empty stomach with minimal water and wait 30 minutes, any other morning oral medications — thyroid hormone (levothyroxine), blood pressure pills, antidepressants — must be spaced at least 30 minutes after the GLP-1 dose. This can be managed with a staggered morning routine. Orforglipron, which does not require fasting, may solve this problem entirely once approved. Discuss your specific medication schedule with your prescriber before switching from GLP-1 injections to pills.
The Bottom Line
Switching from GLP-1 injections to pills for weight loss is no longer a theoretical question — 2026 data gives a clear answer: for many people, the switch works, and works well. The Wegovy pill’s 4.1% additional weight loss in recent switch studies challenges the assumption that injectable GLP-1s are always the gold standard. And with Orforglipron on the horizon — a non-fasting oral GLP-1 achieving injectable-class results — the landscape is shifting faster than most patients realise.
Verdict: If you have needle fatigue, travel frequently, have plateaued on an injectable, or simply want more day-to-day control over your GLP-1 treatment, switching to an oral option is a conversation worth having with your provider. The data supports it. The practical burden — the 30-minute morning fast — is real but manageable for most people. And if that burden is a dealbreaker, Orforglipron’s expected approval may remove it entirely.
Your next step: Talk to your healthcare provider about whether switching from GLP-1 injections to pills for weight loss makes sense for your specific situation. Bring the 2026 switch-study data and a list of your current challenges with injectables to guide the discussion.
What to read next:
- Wondering whether to change your dose instead of changing your medication? Read our companion piece: Increasing Ozempic Dose vs Switching to Mounjaro
- Curious about what else GLP-1 medications can do beyond weight loss? GLP-1 Medications Beyond Weight Loss: Liver, Heart, and Brain Benefits
Medical Disclaimer: This article is for informational purposes only and does not constitute medical advice. Always consult a qualified healthcare professional before starting, stopping, or changing any medication. Weight-loss results vary by individual and depend on factors including diet, exercise, and medication adherence.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.