








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
amlodipine side effects — Amlodipine Side Effects: 10 Common Issues and How to Manage Them. Read on for an evidence-backed guide covering everything you need to know.

Amlodipine side effects — you started amlodipine three weeks ago. Your blood pressure numbers are finally where your doctor wants them — 128/82, down from 152/94. You should be relieved. And you are. But there is one thing bothering you: by the end of the day, your ankles look different. A little puffy. Your shoes feel tighter than they used to. You pull off your socks and see an indentation that stays for a few seconds longer than it should.
Amlodipine side effects — you are not imagining it. And you are not alone.
Amlodipine side effects — ankle swelling — known medically as peripheral edema — happens to roughly 1 in 10 people who take amlodipine, making it the single most common side effect of one of the most prescribed blood pressure medications in the world. The swelling is not dangerous for most people. But it is uncomfortable, it can be alarming, and it is the number one reason patients stop taking a medication that is objectively working.
What most people are never told is that amlodipine side effects — including the swelling — are almost always manageable. There is a clear physiological mechanism behind the ankle swelling, and there are proven strategies to reduce it without giving up the blood pressure control you worked to achieve.
Amlodipine side effects — by the end of this article, you will understand why amlodipine causes each of its most common side effects, which ones are normal versus which ones require an urgent call to your doctor, and — most importantly — the seven evidence-backed steps you can take to manage side effects while staying on track with your blood pressure treatment.
Key Takeaways
- Ankle swelling affects roughly 1 in 10 amlodipine users and is caused by a specific capillary pressure mechanism — it does not mean you are retaining fluid everywhere or your heart is failing
- Most amlodipine side effects are dose-dependent: 10 mg roughly doubles the ankle-swelling rate compared to 5 mg
- The swelling almost always starts in the feet and ankles because gravity pulls that capillary fluid to the lowest point in your body
- Gum overgrowth (gingival hyperplasia) is a rare but real amlodipine side effect that develops over months to years — and excellent dental hygiene significantly reduces the risk
- Combining amlodipine with an ARB or ACE inhibitor can reduce ankle swelling by up to 50% while improving blood pressure control
- Sudden amlodipine discontinuation can cause rebound hypertension — always talk to your doctor before stopping
- What Is Amlodipine and How Does It Work?
- Why Does Amlodipine Cause Ankle Swelling? (The Mechanism Nobody Explains)
- The 10 Most Common Amlodipine Side Effects
- Which Side Effects Are Normal vs. Concerning?
- Dosage Matters: 2.5 mg vs 5 mg vs 10 mg
- What the Research Says: Clinical Trial Evidence
- How to Manage Amlodipine Side Effects: 7 Evidence-Backed Strategies
- Amlodipine and Other BP Medications: How It Compares
- Frequently Asked Questions
- The Bottom Line
What Is Amlodipine and How Does It Work? — Amlodipine side effects Explained
Amlodipine side effects — amlodipine, sold under the brand name Norvasc and widely available as a generic, belongs to a class of medications called calcium channel blockers — specifically the dihydropyridine subclass. It works by blocking calcium from entering the smooth muscle cells that line your blood vessel walls.
Amlodipine side effects — when calcium enters these cells, it triggers muscle contraction — your blood vessels tighten. By blocking calcium entry, amlodipine allows the blood vessels to relax and widen, a process called vasodilation. Wider blood vessels mean lower resistance against which your heart must pump. Lower resistance means lower blood pressure.
Quick Answer: Amlodipine is a calcium channel blocker that relaxes and widens your blood vessels, lowering blood pressure by reducing the resistance your heart pumps against. It is one of the top five most-prescribed medications globally because it is effective, well-tolerated by most people, and dosed once daily.
Amlodipine side effects — amlodipine has several advantages over other blood pressure medications. It has a long half-life — 30 to 50 hours — meaning it provides smooth 24-hour blood pressure control even if you occasionally take it a little late. It does not require kidney function monitoring, unlike ACE inhibitors and ARBs. And it has a strong evidence base, having been studied in landmark trials like ASCOT (Anglo-Scandinavian Cardiac Outcomes Trial) and ALLHAT, which collectively enrolled tens of thousands of participants.
Amlodipine side effects — for most people, amlodipine is started at 5 mg once daily and can be increased to 10 mg if additional blood pressure lowering is needed. A 2.5 mg starting dose is available for people who are elderly, have liver impairment, or are sensitive to medications. The medication reaches steady-state levels in the blood after about 7 to 8 days of daily dosing.
Why Does Amlodipine Cause Ankle Swelling? (The Mechanism Nobody Explains)
Amlodipine side effects — if your doctor has ever told you that the ankle swelling from amlodipine is “just a side effect” and moved on, you are in the majority. But understanding exactly why it happens makes it less alarming — and points directly to the strategies that reduce it.
Amlodipine side effects — amlodipine-induced ankle swelling is not the same as the generalized fluid retention you might experience from heart failure or kidney disease. It is a localized phenomenon driven by physics and physiology.
Amlodipine side effects — here is the step-by-step mechanism:
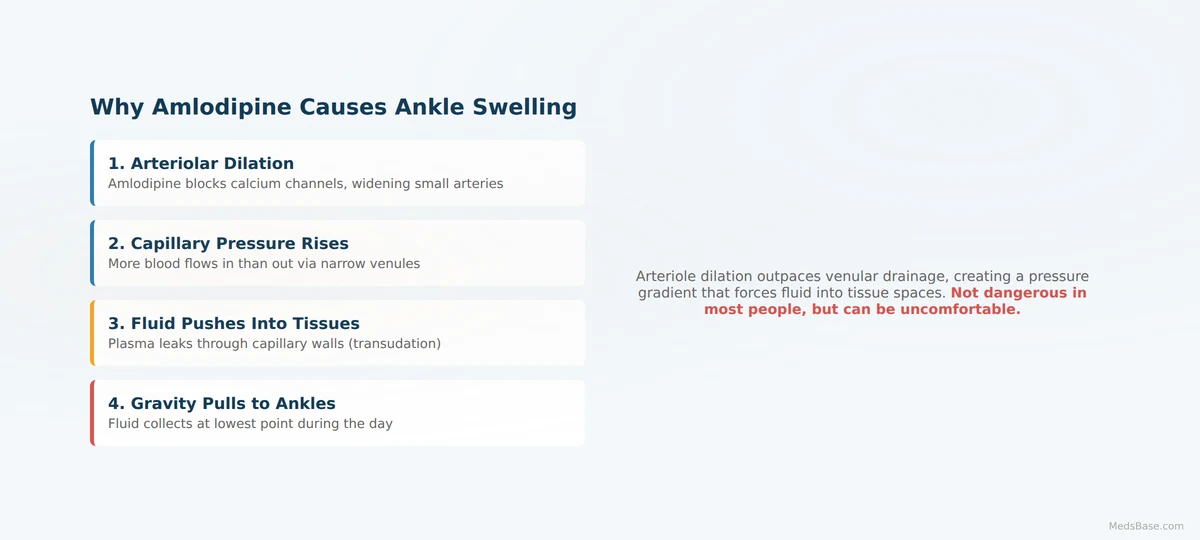
Step 1: Arteriolar vasodilation outpaces venular vasodilation. Amlodipine dilates arterioles — the small arteries that deliver blood to your tissues — much more than it dilates venules, the small veins that drain blood away. This creates an imbalance: more blood flows into the capillary bed than flows out.
Step 2: Capillary hydrostatic pressure rises. The increased inflow without matching outflow raises the pressure inside your capillaries. Capillaries are thin-walled — they are designed for nutrient and gas exchange, not for withstanding pressure.
Step 3: Fluid is pushed into tissues. The elevated pressure forces plasma — the fluid component of blood — through the capillary walls into the surrounding interstitial space. This is transudation, and it is the same mechanism that causes swelling when you stand for too long on a hot day, except amlodipine makes it happen more readily.
Step 4: Gravity pulls fluid downward. While you are upright during the day, gravity pulls this interstitial fluid toward your feet and ankles — the lowest point of your body. When you lie down at night, the fluid redistributes, which is why the swelling typically improves by morning and then worsens again through the day.
Amlodipine side effects — this is also why ankle swelling from amlodipine is usually pitting edema — when you press your finger into the swollen area and remove it, an indentation remains for a few seconds. The fluid is loosely held in the tissue space, not bound to proteins or inside cells.
Quick Answer: Amlodipine ankle swelling happens because the medication widens the arteries feeding your tissues more than the veins draining them, creating a pressure imbalance that pushes fluid out of your capillaries. Gravity pulls that fluid to your ankles and feet during the day. The swelling is positional and improves overnight.
The 10 Most Common Amlodipine Side Effects
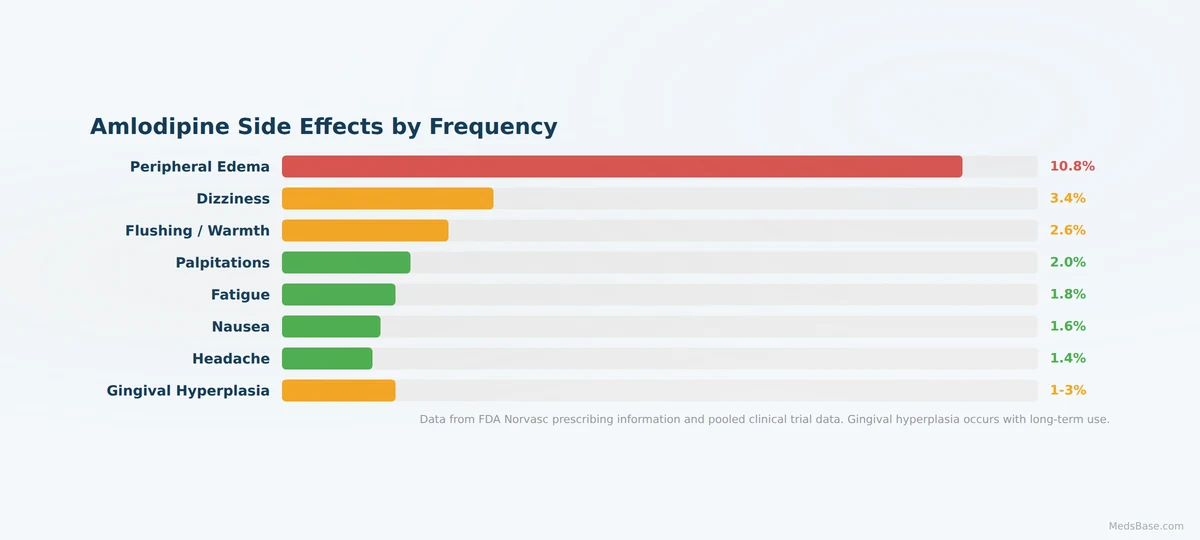
Based on pooled data from clinical trials and the FDA prescribing information, here are the most common amlodipine side effects, ranked by how frequently they occur:
| Side Effect | Approximate Frequency | Typical Severity | What To Do |
|---|---|---|---|
| Peripheral edema (ankle/foot swelling) | 5–15% (dose-dependent: ~8% at 5 mg, ~18% at 10 mg) | Mild to moderate | Elevate legs, reduce sodium, compression stockings, consider dose reduction or ARB/ACE inhibitor add-on |
| Dizziness / lightheadedness | 3–5% | Mild, often transient | Rise slowly from sitting/lying; usually improves after 1–2 weeks |
| Flushing / warmth | 2–4% | Mild, transient | Normal within first weeks; avoid alcohol initially; tell doctor if persistent |
| Palpitations (awareness of heartbeat) | 1–2% | Usually mild | Often harmless reflex tachycardia; tell doctor if rapid or irregular |
| Fatigue / tiredness | 1–2% | Mild to moderate | May improve over weeks; take at bedtime if daytime fatigue is an issue |
| Nausea | 1–2% | Mild | Take with food; usually improves |
| Headache | 1–2% | Mild | Usually transient in first weeks |
| Abdominal pain | ~1% | Mild | Take with food; tell doctor if persistent |
| Drowsiness | <1% | Mild | Take at bedtime if bothersome |
| Gingival hyperplasia (gum overgrowth) | 1–3% with long-term use (>3 months) | Can progress if unmanaged | Excellent oral hygiene; regular dental cleanings; reversible if caught early |
The Gum Overgrowth Connection (Most Patients Are Never Warned)
Gingival hyperplasia — a gradual overgrowth of gum tissue — is a side effect most amlodipine patients are never told about. It is uncommon, affecting roughly 1–3% of people who take amlodipine for more than 3 months, but it is worth knowing about because it is preventable and reversible when caught early.
The mechanism is not fully understood, but amlodipine appears to alter collagen metabolism in gum tissue and may interact with inflammatory signals from dental plaque. This is why excellent oral hygiene — brushing twice daily, flossing, and regular dental cleanings — significantly reduces the risk. In many cases, the gum overgrowth reverses within 1–3 months of amlodipine discontinuation, and even without stopping the medication, professional dental cleaning and meticulous home care can reduce it substantially.
If you notice your gums looking puffy, swollen, or growing over your teeth — especially between teeth — mention it to both your dentist and your prescribing doctor. This is not a dental emergency, but it should not be ignored.
Which Side Effects Are Normal vs. Concerning?
Most amlodipine side effects are mild, dose-dependent, and manageable without stopping the medication. But there are symptoms that should prompt a same-day call to your doctor — and a few that warrant emergency care.
Normal and manageable (mention at your next appointment):
- Mild ankle/foot swelling that improves overnight
- Mild dizziness when first standing up, especially in the first 1–2 weeks
- Facial flushing or feeling of warmth
- Mild fatigue
- Mild headache
- Mild nausea when first starting
Worth a call to your doctor this week:
- Ankle swelling that does not improve at all overnight
- Swelling that extends above the ankle into the calf
- Swelling in only ONE leg (asymmetrical swelling can signal a blood clot)
- Dizziness that causes you to nearly faint
- Palpitations that feel rapid, irregular, or are accompanied by chest discomfort
- Gum swelling or overgrowth you have not mentioned before
Seek urgent medical attention (emergency department or call emergency services):
- Severe shortness of breath, especially when lying flat
- Chest pain or pressure
- Rapid, irregular heartbeat with lightheadedness
- Swelling of the face, lips, tongue, or throat (signs of a rare allergic reaction — angioedema)
- Severe abdominal pain with nausea and vomiting (rare but can signal pancreatitis)
The important distinction: amlodipine ankle swelling is symmetrical — both feet and ankles swell roughly equally. If only one leg or ankle swells, that is not typical amlodipine edema and could indicate a deep vein thrombosis (DVT) — a blood clot that requires immediate medical evaluation.
Dosage Matters: 2.5 mg vs 5 mg vs 10 mg
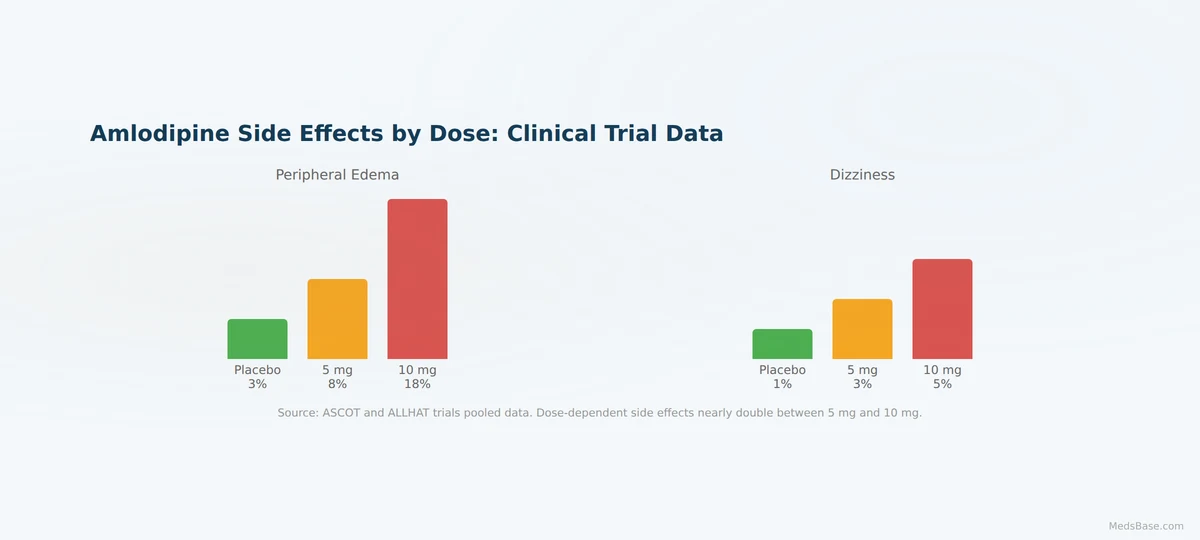
Amlodipine side effects are strongly dose-dependent. This is one of the most practical things to understand, because it means your doctor has room to adjust.
2.5 mg: The lowest therapeutic dose. Side effects are minimal — ankle swelling occurs in fewer than 5% of people at this dose. Blood pressure reduction is modest, typically 5–10 mmHg systolic. Often used as a starting dose for elderly patients or those with liver impairment.
5 mg: The standard starting dose for most adults. Expect approximately 10–15 mmHg systolic reduction. Ankle swelling occurs in roughly 5–8% of users. This is the dose at which most people find a good balance between blood pressure control and side-effect tolerability.
10 mg: The maximum recommended dose. Blood pressure reduction is roughly 15–20 mmHg systolic — but side effects roughly double. Ankle swelling occurs in approximately 15–18% of users at this dose. Dizziness, flushing, and fatigue also increase.
Here is where it gets interesting: research shows that 5 mg of amlodipine plus a low dose of another blood pressure medication class often provides BETTER blood pressure control with FEWER side effects than 10 mg of amlodipine alone. This is the principle behind combination therapy — using two medications at lower doses to achieve additive blood pressure lowering with subtractive side effects. A common and well-studied combination is amlodipine 5 mg plus an ARB like losartan 50 mg or valsartan 80 mg.
If you are on 10 mg of amlodipine and struggling with ankle swelling, ask your doctor whether reducing to 5 mg and adding a second medication from a different class might work for you. This is standard clinical practice, supported by multiple hypertension guidelines, and often results in better tolerability.
What the Research Says: Clinical Trial Evidence
| Study | Year | Finding | Source |
|---|---|---|---|
| ASCOT-BPLA (Anglo-Scandinavian Cardiac Outcomes Trial) | 2005 | Amlodipine ± perindopril reduced all-cause mortality and cardiovascular events vs. atenolol ± thiazide; peripheral edema in ~23% of amlodipine group (10 mg dose) | The Lancet |
| ALLHAT (Antihypertensive and Lipid-Lowering Treatment) | 2002 | Amlodipine was equivalent to lisinopril and chlorthalidone for preventing major cardiovascular events; edema rate ~10% vs ~4% in other arms | JAMA |
| CCB edema mechanism review | 2015 | Dihydropyridine CCBs cause arteriolar > venular dilation capillary hypertension fluid transudation; ARB/ACE inhibitor co-administration reduces edema by up to 50% | Hypertension |
| Gingival hyperplasia systematic review | 2015 | Amlodipine-associated gingival overgrowth prevalence ~1–3% with long-term use; strongly associated with poor oral hygiene and male sex; mostly reversible on discontinuation | Journal of Periodontology |
| Amlodipine tolerability meta-analysis | 2018 | Overall discontinuation rate due to side effects ~5.3% for amlodipine vs ~2.6% for placebo; most discontinuations driven by edema; dose reduction effective for managing edema |
What this means for you: the clinical trial evidence is clear that amlodipine is an effective blood pressure medication with a well-characterized side-effect profile. The most common reason people stop amlodipine — ankle swelling — is dose-dependent and often manageable through dose reduction, combination therapy, or conservative measures. Amlodipine has been studied in many thousands of people over decades, and serious side effects are rare.
How to Manage Amlodipine Side Effects: 7 Evidence-Backed Strategies
1. Reduce the starting dose. If you are on 10 mg and struggling with swelling, ask your doctor about reducing to 5 mg. In clinical practice, this is the single most effective strategy — ankle swelling rates roughly halve. Blood pressure lowering is reduced but often remains adequate, especially when combined with lifestyle measures. Never reduce your dose without your doctor’s approval.
2. Take amlodipine at bedtime. Taking amlodipine at bedtime rather than in the morning shifts the peak vasodilation to the overnight hours when you are lying down and gravity distributes fluid more evenly across your body rather than concentrating it in your ankles. Some studies suggest bedtime dosing may also provide better nighttime blood pressure control, though the evidence is mixed.
3. Reduce dietary sodium. Sodium promotes fluid retention and amplifies the edema from amlodipine. Aim for less than 2,300 mg of sodium per day — roughly one teaspoon of salt. The biggest sodium sources are not the salt shaker but processed foods, bread, deli meats, and restaurant meals. A low-sodium diet can reduce the ankle swelling noticeably within days.
4. Elevate your legs and consider compression stockings. Elevating your legs above heart level for 20–30 minutes, 2–3 times per day, allows gravity to drain the interstitial fluid back into your circulation. Compression stockings (15–20 mmHg, knee-high) provide external pressure that counteracts the capillary fluid leak. Both are low-risk, drug-free strategies.
5. Ask your doctor about adding an ARB or ACE inhibitor. Combining amlodipine with an angiotensin receptor blocker (like losartan or valsartan) or an ACE inhibitor (like lisinopil or ramipril) reduces ankle swelling by up to 50% through a complementary mechanism: ARBs and ACE inhibitors dilate venules, balancing the arteriolar dilation from amlodipine and reducing the capillary pressure gradient. This is a guideline-supported combination that offers better blood pressure control with fewer side effects than high-dose monotherapy.
6. Switch to a different dihydropyridine CCB. Not all calcium channel blockers cause equal amounts of edema. Lercanidipine and lacidipine, available in some countries, are associated with lower rates of ankle swelling compared to amlodipine, possibly because they have a more balanced arteriolar-to-venular dilation profile. If amlodipine is not tolerable and your doctor agrees, asking about an alternative CCB is reasonable.
7. Switch medication classes entirely. If side effects are intolerable despite dose reduction and conservative measures, switching to an entirely different class — an ARB, ACE inhibitor, or thiazide diuretic — may be appropriate. Each class has its own side-effect profile, and finding the right medication often takes some trial and error. The key is not to give up on blood pressure treatment — uncontrolled hypertension carries vastly greater health risks than any medication side effect.
Amlodipine and Other BP Medications: How It Compares

Amlodipine is not the only blood pressure medication, and which one is right for you depends on your age, other medical conditions, side-effect tolerance, and cost considerations. Here is how amlodipine compares to the other major classes:
| Medication Class | Example | Key Advantage | Common Side Effects | Edema Risk |
|---|---|---|---|---|
| Dihydropyridine CCB (amlodipine) | Amlodipine, nifedipine | Long half-life, no kidney monitoring, strong evidence base | Ankle swelling, flushing, headache | High (5–18%) |
| ACE Inhibitor | Lisinopil, ramipril | Kidney-protective in diabetes, no metabolic side effects | Dry cough (~10%), angioedema (rare) | Very low |
| ARB | Losartan, valsartan | Same benefits as ACE inhibitors without the cough | Dizziness, mild hyperkalemia | Very low |
| Thiazide Diuretic | Hydrochlorothiazide, chlorthalidone | Low cost, strong evidence for stroke reduction | Increased urination, electrolyte changes, gout precipitation | Low |
| Beta-Blocker | Metoprolol, bisoprolol | Indicated if also have heart failure, prior MI, or angina | Fatigue, cold hands, vivid dreams, bradycardia | Low |
Amlodipine is a particularly good first-line choice for people over 55, people of African or Afro-Caribbean descent (who tend to respond less well to ACE inhibitors as monotherapy), and people who do not want to worry about kidney function monitoring. However, if you are prone to ankle swelling from other causes — venous insufficiency, prolonged standing at work, pregnancy — an ARB or ACE inhibitor may be a better first choice.
For an in-depth comparison of blood pressure medication classes, read our full guide: Beta Blockers vs Calcium Channel Blockers.
Frequently Asked Questions
Q: Does amlodipine cause weight gain?
A: Amlodipine itself does not cause fat gain, but the ankle swelling can show up as 1–3 kg of extra fluid weight on the scale. This is fluid, not fat — it fluctuates through the day and typically drops within days of dose reduction or medication change. If you notice rapid weight gain (more than 2–3 pounds overnight or 5 pounds in a week), especially with shortness of breath, contact your doctor promptly to rule out fluid retention from other causes.
Q: Can I stop amlodipine suddenly?
A: No. Amlodipine should not be stopped abruptly without your doctor’s guidance. Sudden discontinuation can cause rebound hypertension — your blood pressure may spike higher than it was before you started treatment, potentially triggering a hypertensive urgency. If you and your doctor decide to stop amlodipine, it is typically tapered over 1–2 weeks while monitoring your blood pressure. If you are switching to a different medication, the new one is usually started before the amlodipine is fully discontinued.
Q: Does amlodipine cause erectile dysfunction?
A: The evidence on amlodipine and ED is reassuring. Unlike some older beta-blockers (particularly atenolol and propranolol), which are associated with an increased risk of ED, calcium channel blockers including amlodipine have a neutral effect on erectile function. In fact, by improving blood flow and lowering blood pressure, amlodipine may actually improve erectile function in men whose ED is related to hypertension-related vascular damage. If you are experiencing ED on amlodipine, do not assume the medication is the cause — uncontrolled high blood pressure itself is a major risk factor for ED.
Q: How long do amlodipine side effects last?
A: Most acute side effects — dizziness, flushing, headache, mild nausea — typically improve or resolve within the first 1–2 weeks as your body adjusts to the vasodilation. Ankle swelling that persists beyond 2–4 weeks at a given dose is likely to continue as long as you remain on that dose. Gingival hyperplasia develops over months and does not resolve spontaneously while on the medication. Fatigue may improve over weeks to months but is more variable.
Q: Can I take amlodipine while pregnant?
A: Amlodipine is generally not recommended during pregnancy. The FDA classifies it as a pregnancy category C medication (animal studies have shown adverse effects, but adequate human studies are lacking). If you are pregnant or planning to become pregnant, discuss alternative blood pressure medications with your doctor. Labetalol, nifedipine, and methyldopa are more commonly used during pregnancy and have more established safety data.
Q: Does amlodipine interact with grapefruit?
A: Yes, but the interaction is modest compared to some other calcium channel blockers like felodipine or nifedipine. Grapefruit inhibits the CYP3A4 enzyme that metabolizes amlodipine, which can increase blood levels of the medication. The effect is generally not clinically significant with occasional grapefruit consumption, but drinking large amounts of grapefruit juice daily could increase amlodipine levels by roughly 15–20%. A small glass occasionally is unlikely to cause problems for most people, but if you are a daily grapefruit juice drinker on 10 mg of amlodipine, discuss with your doctor.
Q: What should I do if I miss a dose of amlodipine?
A: Take the missed dose as soon as you remember, unless it is close to the time for your next dose. In that case, skip the missed dose and resume your normal schedule. Do not take two doses to make up for a missed one. Amlodipine has a long half-life (30–50 hours), so missing an occasional single dose is unlikely to cause a significant blood pressure spike.
The Bottom Line
Amlodipine is one of the most effective, well-studied, and widely used blood pressure medications available. It has kept millions of people’s blood pressure in a healthy range and prevented countless heart attacks and strokes. But effectiveness does not mean side-effect-free.
The ankle swelling that affects 1 in 10 people who take it — and roughly 1 in 5 people at the 10 mg dose — is real, it has a clear physiological mechanism, and it is the leading reason people stop a medication that is objectively working for them. The good news is that you do not have to choose between controlling your blood pressure and living with swollen ankles. Dose reduction, combination therapy (especially adding an ARB or ACE inhibitor), bedtime dosing, sodium reduction, and leg elevation are all evidence-backed strategies that work.
The most important thing you can do is talk to your doctor. Tell them about the swelling. Ask whether dose reduction or combination therapy might work. And do not stop the medication on your own — rebound hypertension is a real risk, and there are safer paths to relief.
Your immediate action: If you are bothered by amlodipine side effects, schedule a follow-up appointment specifically to discuss them. Write down when the swelling is worst (end of day? all day?), whether it improves overnight, and whether it is symmetrical. This information helps your doctor distinguish medication-related edema from other causes.
What to read next:
- Trying to decide between medication classes? Beta Blockers vs Calcium Channel Blockers — Which Is Right for You?
- On multiple blood pressure medications? Blood Pressure Medication Adherence: 7 Strategies That Actually Work
- Taking metoprolol and wondering about the IR vs ER difference? Metoprolol Tartrate vs Metoprolol Succinate: 7 Key Differences
Medical Disclaimer: This article is for informational purposes only and does not constitute medical advice. The information provided is not a substitute for professional medical diagnosis, treatment, or advice. Always consult your doctor before changing any prescribed medication dosage or regimen. Never discontinue blood pressure medication abruptly without medical supervision — rebound hypertension can occur.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.