








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
betahistine for vertigo — Betahistine for Vertigo: 7 Essential Facts Before You Start. Read on for an evidence-backed guide covering everything you need to know.
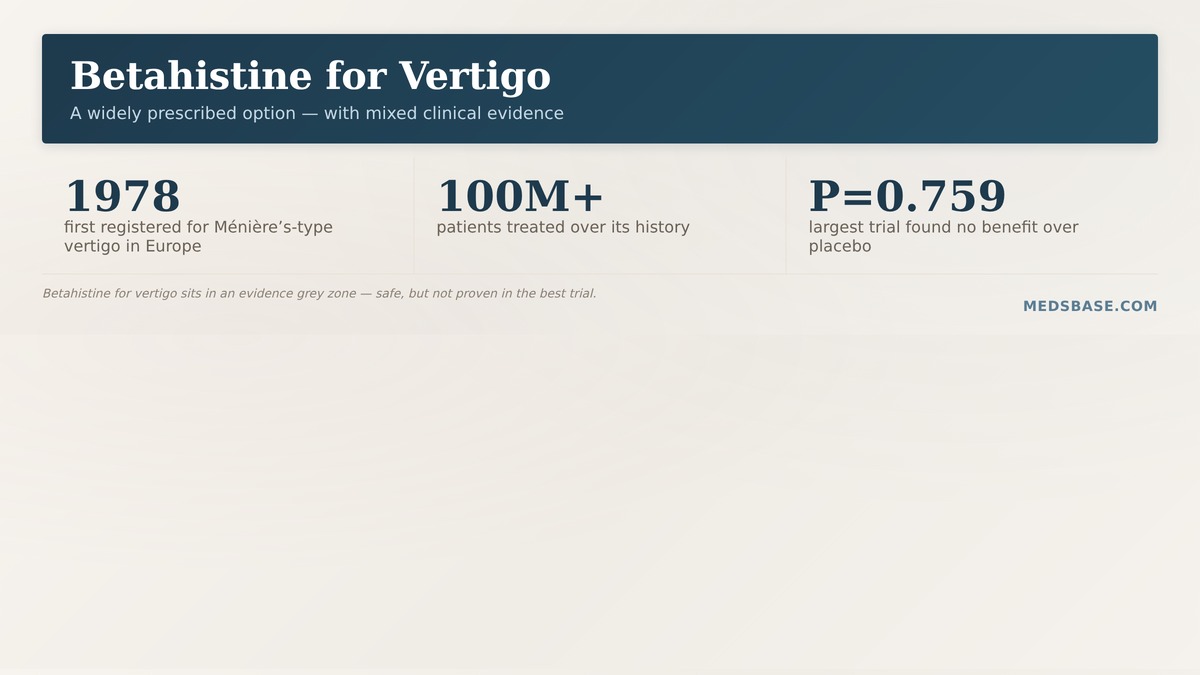
Most people assume betahistine for vertigo works because it is so widely prescribed. The largest rigorous trial ever run on the drug reached a different conclusion — and that tension is exactly why you should understand this medication before taking it. Betahistine (brand name Serc, and sold under names such as Betavert) has been used for Ménière’s disease and vertigo for decades, and it remains one of the most commonly prescribed vertigo medicines in Europe. Yet a landmark 2016 trial published in the BMJ found it no better than placebo at reducing Ménière’s attacks. This guide lays out what betahistine for vertigo is, how it is supposed to work, what the evidence honestly shows, and how to weigh it against your other options.
- Betahistine for vertigo is a histamine-analogue medicine used mainly for Ménière’s disease, where it aims to reduce the frequency and severity of spinning attacks.
- The landmark BEMED trial found betahistine no better than placebo at preventing Ménière’s attacks — a result that surprised many and is often missing from consumer coverage.
- Despite that, betahistine remains widely used and generally well tolerated, and many clinicians still prescribe it based on long experience and positive open-label data.
- Betahistine for vertigo is not approved in the United States but is available in much of Europe, the UK and elsewhere.
- The honest decision hinges on the cause of your vertigo — betahistine targets Ménière’s-type vertigo, not BPPV or a vestibular infection.
- One thing most people miss: even the placebo group in the BEMED trial improved a lot, which is a reminder that vertigo often settles on its own.
On this page:
- What Is Betahistine for Vertigo?
- How Does Betahistine for Vertigo Work?
- Key Uses & Who Is This For
- Safety, Side Effects & Dosage
- What Does the Research Say?
- Betahistine for Vertigo vs Alternatives
- How to Take Betahistine for Vertigo
- Frequently Asked Questions
- The Bottom Line
What Is Betahistine for Vertigo?
Betahistine for vertigo is a medicine that aims to reduce the spinning sensation, dizziness and associated nausea of inner-ear balance disorders — most notably Ménière’s disease. It is a structural analogue of histamine, which means it looks enough like the body’s own histamine to act on histamine receptors, but it is used for a very different job than an antihistamine. Despite decades of use, its mechanism is only partly understood, and its clinical benefit has been hotly debated.
Betahistine is available as betahistine dihydrochloride tablets in strengths such as 8 mg and 16 mg, and it is usually taken two or three times a day. In the UK it is a prescription medicine; in some countries it sits behind the counter. It is most commonly prescribed for Ménière’s disease — a condition of recurring vertigo attacks, fluctuating hearing loss, tinnitus and a feeling of fullness in the ear — but it is sometimes used for other causes of vertigo as well.
One reason a clear answer about betahistine for vertigo is hard to come by is that “vertigo” is not one condition — it is a symptom with many causes, and only some of them are relevant to this drug. Most adults will experience some dizziness in their lives, and the spinning type specifically breaks down into a handful of distinct inner-ear and brain disorders, each with its own treatment. Confusing them is the single biggest reason people end up on the wrong medicine. We will untangle that in the sections ahead, because getting the diagnosis right matters more than any tablet.
How Does Betahistine for Vertigo Work?
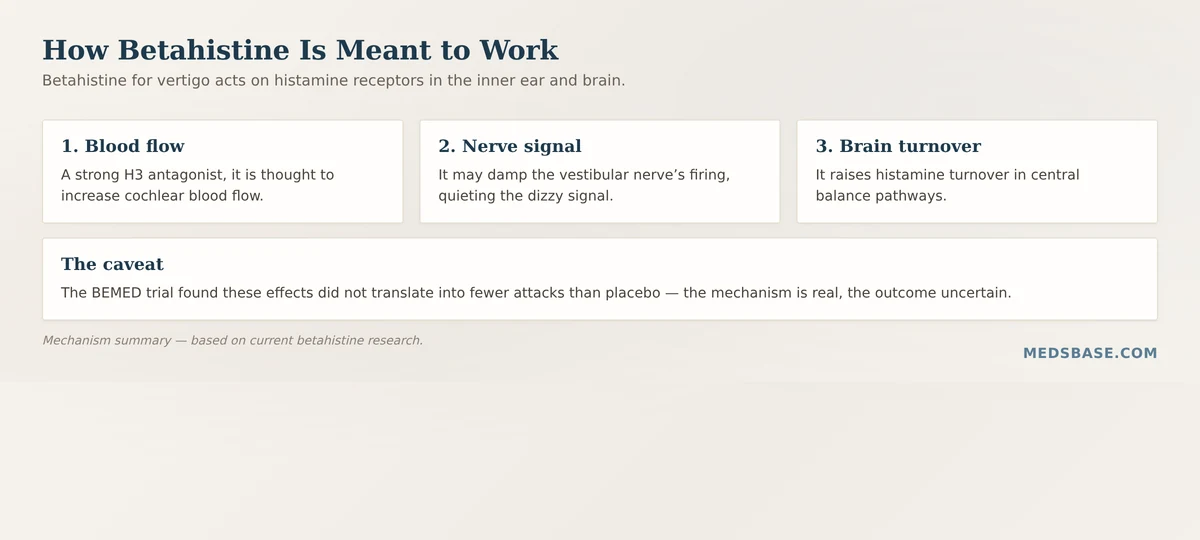
The short answer is that we understand the broad strokes better than the exact details. Betahistine for vertigo is thought to work in three overlapping ways, all centred on histamine receptors in the inner ear and brain.
First, it acts as a strong antagonist at H3 receptors and a weak agonist at H1 receptors. This combination is believed to increase blood flow to the inner ear (the cochlea), which may help the balance organs recover or function more normally. Second, it increases histamine turnover in the central vestibular system — the brain networks that process balance signals. Third, it is thought to dampen the firing of the vestibular nerve, reducing the intensity of the dizzy signal reaching the brain.
Think of it this way: if your inner ear is a spinning top that keeps sending “we are still moving” signals after you have stopped, betahistine is meant to quiet that oversignalling — partly by improving the local blood supply and partly by turning down the volume at the nerve level.
The metabolism matters too, and it is part of why the drug is fiddly in practice. Betahistine has a strong first-pass effect — most of it is broken down in the liver before it reaches the circulation — and one of its metabolites, aminoethylpyridine, is itself thought to be active at the same receptors. This means the amount of drug actually reaching the inner ear after a tablet is much lower than the dose on the box, and it is one of the reasons trial doses have crept upward over the years, from 16 mg a day in older studies to 144 mg a day in the high-dose arm of the BEMED trial. The wide dosing range you will see in real prescriptions — from a single 8 mg tablet to 48 mg three times daily — reflects genuine uncertainty about the optimal dose, not carelessness.
Key Uses of Betahistine for Vertigo
Ménière’s disease
This is the primary, licensed use. Ménière’s disease causes unpredictable attacks of rotational vertigo that can last from 20 minutes to many hours, alongside hearing loss and tinnitus. Betahistine is prescribed as a long-term preventive to try to reduce how often attacks occur, not as a rescue drug for an attack already underway.
Other inner-ear vertigo
Some doctors prescribe betahistine off-label for vestibular vertigo that does not fit a clear Ménière’s diagnosis, though the evidence here is even thinner.
What it is NOT for
It is worth being blunt: betahistine for vertigo is not the right tool for benign paroxysmal positional vertigo (BPPV), the common “room spins when I roll over” condition caused by loose crystals in the ear — that responds to repositioning manoeuvres, not medication. Nor is it a first-line treatment for vestibular neuritis or labyrinthitis, which are typically viral and settle with supportive care.
Safety, Side Effects & Dosage
Betahistine for vertigo is generally well tolerated, which is one reason it has stayed in use despite the weak efficacy evidence. Here is what to expect.
| Side Effect | Frequency | Severity | What To Do |
|---|---|---|---|
| Nausea or indigestion | Common | Mild | Take with or after food |
| Headache | Occasional | Mild | Usually settles; report if persistent |
| Stomach discomfort | Occasional | Mild | Lower dose or take with food |
| Skin rash or itching | Rare | Mild-moderate | Stop and report to your doctor |
| Worsening of asthma | Rare | Moderate | Avoid if you have reactive airways |
The usual adult dose is 8–16 mg taken two or three times daily, typically after meals. The BEMED trial tested much higher doses (48 mg three times a day) without finding extra benefit, and with the same generally good tolerance. There is no evidence of dependence, and the medicine has no significant interaction with alcohol beyond the general caution that alcohol can itself worsen dizziness.
What Does the Research Say?
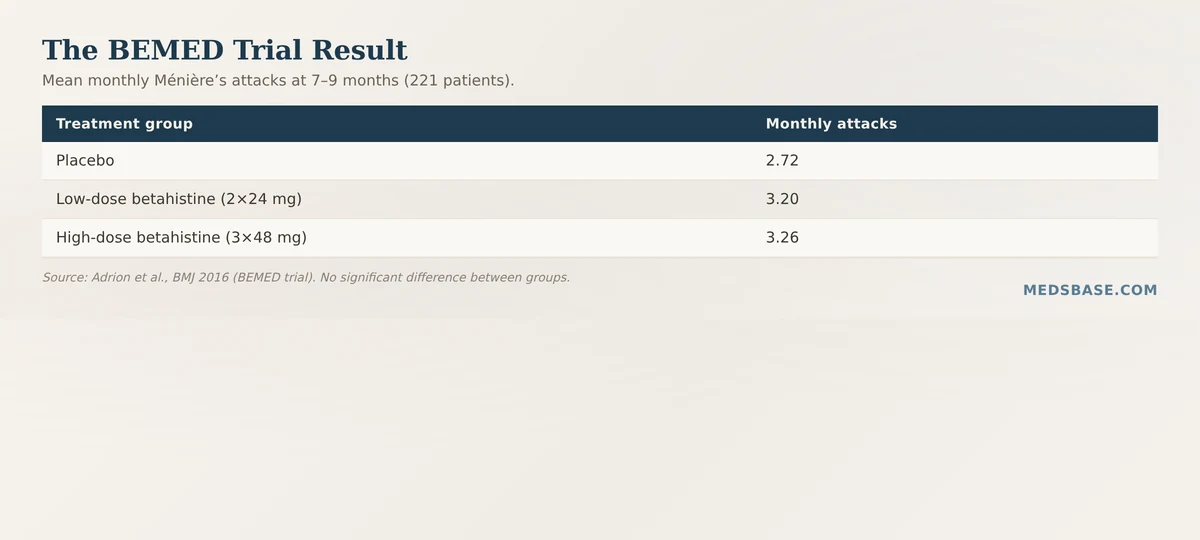
This is the section that separates an honest guide from a marketing leaflet. The evidence for betahistine for vertigo is genuinely mixed, and you deserve the real picture.
| Study | Year | Finding | Source |
|---|---|---|---|
| BEMED trial (221 patients) | 2016 | No difference in vertigo attacks vs placebo at 9 months | BMJ |
| BEMED — all three groups | 2016 | Attacks fell ~24% per month in all groups (placebo included) | BMJ |
| Earlier Cochrane review | 2010s | Insufficient evidence to confirm betahistine benefit | cited in BEMED |
What does this mean for you: the most rigorous trial we have did not show betahistine beating placebo. But the story is more nuanced than “it does not work.” The BEMED trial’s placebo group improved substantially — monthly attacks fell by a factor of 0.758 across all three arms — which tells us Ménière’s disease naturally fluctuates and that simply being in a trial, with careful monitoring, helps. Many clinicians argue that certain patients do respond, and some open-label and lower-quality studies have suggested benefit, particularly at higher doses in selected patients. The honest position is that betahistine for vertigo sits in an evidence grey zone: safe and widely used, but not proven better than placebo in the best study we have.
There is also a strong placebo-and-natural-history dimension that too few patients are told about. Ménière’s disease waxes and wanes; a startling number of people improve over months even without active treatment. That does not make real treatment worthless, but it does mean that attributing improvement to whichever tablet you happened to start is deeply unreliable — the very reason trials with a placebo arm matter so much for this condition.
Betahistine for Vertigo vs Alternatives
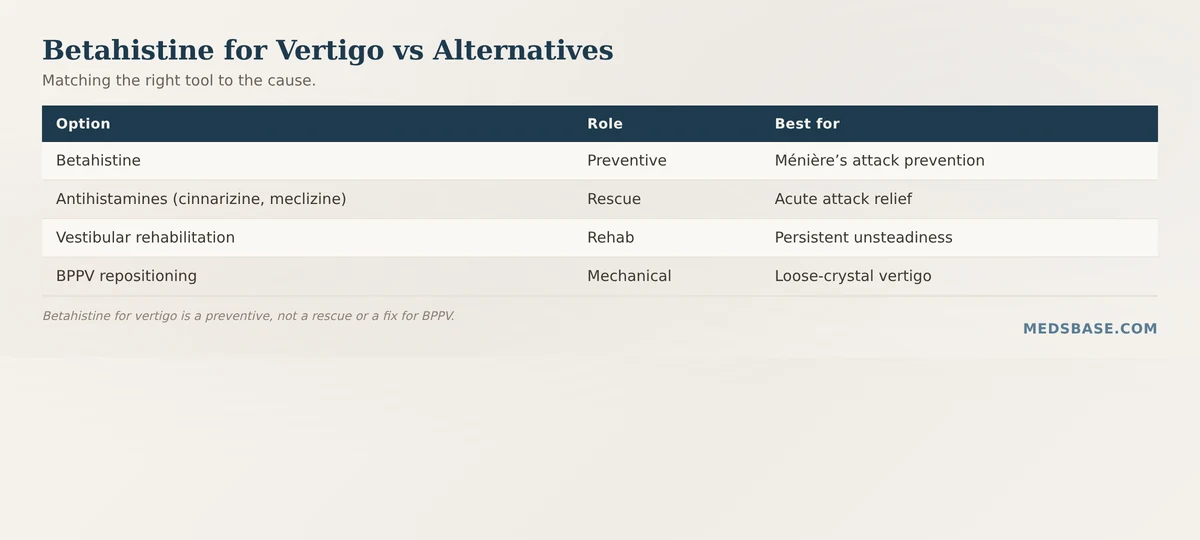
| Option | How it works | Best for | Caveat |
|---|---|---|---|
| Betahistine | Histamine analogue; aims to reduce attacks | Ménière’s preventive | Not proven better than placebo |
| Antihistamines (cinnarizine, meclizine) | Sedate the vestibular system | Acute attack relief | Drowsy; short-term use |
| Vestibular rehabilitation | Retrains the brain’s balance processing | Persistent imbalance | Takes weeks; needs commitment |
| BPPV repositioning manoeuvres | Move misplaced crystals back | BPPV | Specific, effective, not a drug |
| Dietary salt restriction + diuretic | Reduce inner-ear fluid pressure | Ménière’s adjunct | Modest effect; needs supervision |
Which one fits which situation? For an attack that is happening right now, a short course of a sedating antihistamine is usually more useful than betahistine, which is a preventive, not a rescue. For persistent unsteadiness between attacks, vestibular rehabilitation is the underused star — exercises that teach the brain to compensate are often more effective than any pill. For confirmed Ménière’s, betahistine remains a reasonable, low-risk preventive option that many specialists still choose, but it should be part of a conversation that is honest about the BEMED result rather than presented as a guaranteed fix.
A useful way to frame the decision is to separate acute from preventive treatment, and attack-specific from general vertigo. If your problem is a spinning episode that comes and goes, the two questions are: what can stop it once it starts (usually an antihistamine or anti-sickness drug), and what can make it happen less often (where betahistine, salt restriction and lifestyle changes sit). If instead your problem is constant background unsteadiness, none of the pills is likely to be the main answer — that is the territory of vestibular rehabilitation, which is consistently underrecommended. Patients who match the right tool to the right problem tend to do better than those who simply take “the vertigo tablet.”
How to Take Betahistine for Vertigo
- Take betahistine with or after food to minimise stomach upset.
- Space your doses evenly through the day (for example, morning, afternoon and evening).
- Give it time — betahistine is a preventive that is judged over weeks to months, not hours.
- Do not stop suddenly without advice if you have been on it long term; your doctor may prefer to taper.
- Report new symptoms — sudden hearing loss, worsening tinnitus or new headache — rather than assuming they are part of the illness.
Mistakes to avoid: expecting betahistine to stop an attack that is already happening; using it for BPPV instead of doing the repositioning manoeuvre your doctor showed you; and assuming “natural” means you can ignore red-flag symptoms like sudden deafness, which need urgent evaluation.
If you have a diagnosis and want to see what is available, you can browse vertigo treatment options or look at a specific betahistine product such as Betavert at MedsBase.
- Myopia Control Treatment — 7 proven ways to slow nearsightedness (today’s related post on evidence-led treatment choice)
- Best Laxative for Constipation — 7 types compared (another “how to choose a medication” guide)
- Browse vertigo treatment options at MedsBase
Frequently Asked Questions
Q: Does betahistine actually work for vertigo?
A: The evidence is genuinely mixed. The largest rigorous trial, the BEMED study of 221 people with Ménière’s disease, found betahistine no better than placebo at reducing vertigo attacks. Many clinicians still prescribe it based on long experience and some positive smaller studies, but it is not proven effective in the strongest trial.
Q: How long does betahistine take to work?
A: Betahistine is a preventive, not a fast-acting rescue drug. If it helps, the benefit is usually judged over several weeks to months of continuous use, not hours or days. It will not stop an attack that is already underway.
Q: What are the side effects of betahistine?
A: The most common side effects are mild and digestive — nausea, indigestion or headache — and they often improve if you take the tablets with food. More serious reactions such as a rash or worsened asthma are rare. Overall, betahistine is considered well tolerated.
Q: Is betahistine safe to take long term?
A: Betahistine has no evidence of dependence and is generally regarded as safe for long-term use under medical supervision, which is why it is prescribed as an ongoing preventive for Ménière’s disease. Regular review with your doctor is still advisable.
Q: Can you get betahistine over the counter?
A: In the UK and much of Europe, betahistine is a prescription-only medicine, so it is not available over the counter. Availability rules vary by country. You should use it only under medical guidance for a confirmed diagnosis.
Q: What is the best medicine for Ménière’s disease?
A: There is no single best medicine. Betahistine is a common, low-risk preventive, but the strongest trial found it no better than placebo. Acute attacks are often managed with sedating antihistamines or anti-nausea drugs, and long-term management may add dietary salt restriction and vestibular rehabilitation.
Q: Why is betahistine still prescribed if the trial was negative?
A: A few reasons. It is safe and well tolerated, decades of clinical experience and some smaller studies suggest a subset of patients benefit, and there are limited alternatives that are clearly better. Many specialists reason that a low-risk option is worth trying in an individual even when the group-level trial is neutral — but responsible prescribing now involves telling you about the BEMED result, which is not always done.
Q: Does betahistine help with tinnitus or hearing loss?
A: Not reliably. Betahistine is aimed at the vertigo attacks of Ménière’s disease, and the evidence does not support a meaningful effect on the associated tinnitus or the progressive hearing loss. Those symptoms tend to fluctuate on their own, so expectations should be set accordingly.
The Bottom Line
Betahistine for vertigo is a safe, well-tolerated medicine with decades of real-world use behind it — but the best available trial says it is no more effective than placebo at preventing Ménière’s attacks, and you deserve to know that before you take it. None of this means it is useless; it means the decision is more personal than the marketing suggests. The single most important step is getting the cause of your vertigo right, because betahistine, repositioning manoeuvres, antihistamines and vestibular rehabilitation all solve different problems, and using the wrong tool wastes time and money. Armed with an honest understanding of the evidence, you are in a far better position to make that call than someone who simply accepted a prescription on faith.
Your next action is simple: if you have recurrent spinning attacks, get a proper diagnosis — ideally from an ear, nose and throat or neurology specialist — before deciding on medication. Then weigh betahistine for vertigo honestly against the alternatives for your specific cause.
Wondering how betahistine for vertigo stacks up against vestibular rehabilitation for your particular balance problem? That comparison is worth reading before you fill a prescription. For other evidence-led medication guides, see our myopia control treatment and best laxative for constipation articles.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.