








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
sertraline vs escitalopram — Sertraline vs Escitalopram — A Complete Comparison for Anxiety and Depression Treatment. Read on for an evidence-backed guide covering everything you need to know.
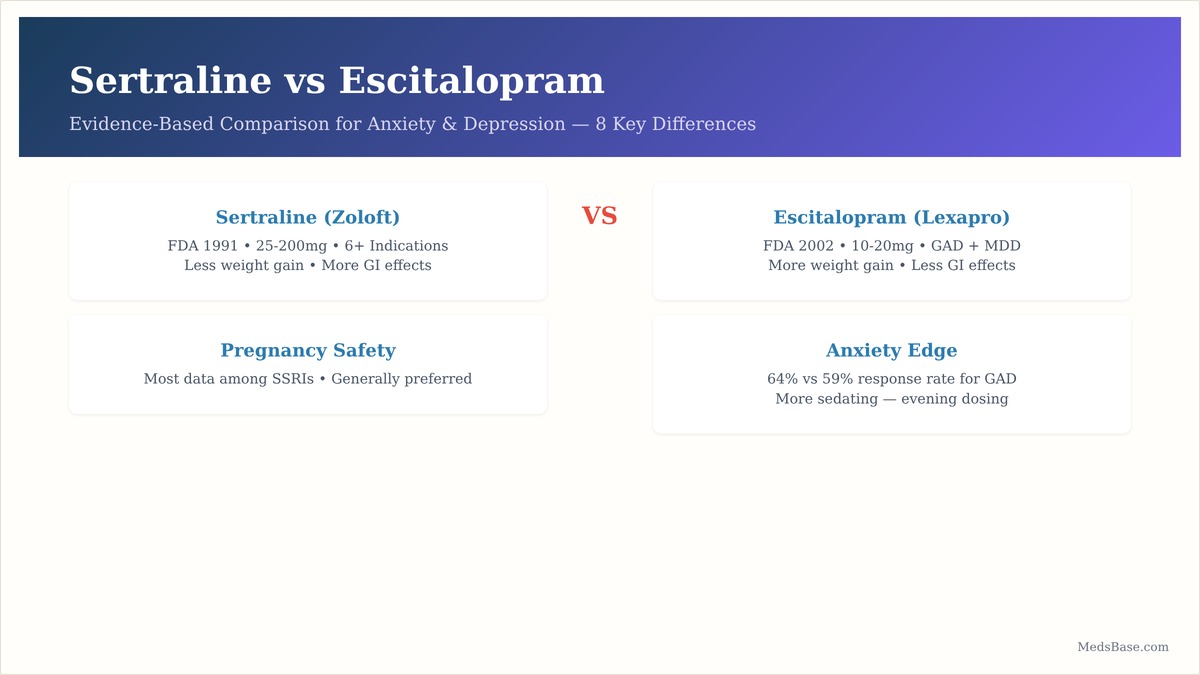
Sertraline vs escitalopram — if you’ve just been prescribed an SSRI — or you’ve been on one for a while and aren’t sure it’s the right one — you’re asking the same question millions of patients ask every year: Sertraline vs escitalopram — which one is actually better?
Sertraline vs escitalopram — it’s a fair question with a surprisingly nuanced answer. Both are selective serotonin reuptake inhibitors (SSRIs). Both are first-line treatments for anxiety and depression. Both are available as affordable generics. And in large clinical trials, both work for most people — roughly 55-65% of patients see meaningful improvement within 8-12 weeks.
Sertraline vs escitalopram — but under the surface, these two medications differ in ways that can make one a better fit for you than the other. They’re metabolized by different liver enzymes. Their side effect patterns tilt in different directions. One handles anxiety slightly better in the data; the other may cause less weight gain. And the choice between them can matter enormously for specific situations — pregnancy, certain anxiety disorders, drug interactions.
By the end of this guide, you’ll know the 8 evidence-based differences that actually matter, which side effects to expect from each, how to switch safely if you need to, and what to discuss with your doctor at your next appointment.
Key Takeaways
- Both medications work, and the differences between them are smaller than most people assume — but small differences can matter enormously when you’re the one taking the medication. One specific side effect surprises almost everyone taking escitalopram, and we’ll cover it in the side effects section.
- Escitalopram may have a slight edge for anxiety, particularly generalized anxiety disorder — head-to-head studies show a modest numerical advantage for escitalopram in anxiety response rates, though the difference is not large enough to say “always choose escitalopram for anxiety.”
- Weight gain is more common with escitalopram, while gastrointestinal side effects are more common with sertraline — knowing these patterns upfront helps you and your doctor choose the best option for your concerns.
- Switching is possible but must be done carefully — a gradual cross-taper under medical supervision is essential. Never stop an SSRI abruptly or switch on your own.
- Your genetics may influence which drug works better for you — escitalopram is metabolized by CYP2C19, and people with certain genetic variants may need dose adjustments. One in three people have a variant that affects this.
- What Are Sertraline and Escitalopram?
- Effectiveness: Which Works Better for Anxiety and Depression?
- Side Effects: How Do They Compare?
- Weight Changes on Sertraline vs Escitalopram
- Sexual Side Effects: What the Data Actually Shows
- Which One Is Better for Specific Conditions?
- Dosage, Timing, and Practical Use
- Drug Interactions: What You Need to Know
- Genetic Factors: Why the Same Dose Affects People Differently
- How to Switch From Sertraline to Escitalopram (or Vice Versa)
- Which One Should You Choose?
- Sertraline vs Escitalopram — At a Glance
- Related Reading
- Frequently Asked Questions
- The Bottom Line
What Are Sertraline and Escitalopram? — Sertraline vs escitalopram Explained
Sertraline vs escitalopram — both sertraline (brand name Zoloft) and escitalopram (brand name Lexapro) belong to the SSRI class — the most commonly prescribed antidepressants worldwide. SSRIs work by blocking the reuptake (recycling) of serotonin in the brain, leaving more serotonin available in the synapse to transmit signals between neurons. Higher synaptic serotonin is associated with improved mood, reduced anxiety, and better emotional regulation.
Quick Answer: Sertraline (Zoloft) and escitalopram (Lexapro) are both SSRIs — first-line antidepressants that work by increasing serotonin availability in the brain. Sertraline is older (FDA-approved 1991), has more approved indications (depression, anxiety, OCD, PTSD, panic disorder, PMDD, social anxiety), and is used across a wider dose range (25-200mg). Escitalopram (FDA-approved 2002) is a refined version of citalopram, approved for depression and generalized anxiety disorder, and is generally taken at 10-20mg. Both are effective, but they differ in side effect profiles, metabolism, and approved uses.
| Feature | Sertraline | Escitalopram |
|---|---|---|
| Brand name (US) | Zoloft | Lexapro |
| FDA approval year | 1991 | 2002 |
| SSRI generation | First-line, well-studied | Refined (S-enantiomer of citalopram) |
| Approved conditions | Depression, OCD, panic disorder, PTSD, social anxiety, PMDD, GAD (off-label) | Depression, GAD |
| Typical dose range | 50-200 mg/day | 10-20 mg/day |
| Half-life | ~26 hours | ~27-32 hours |
| Key metabolic enzyme | CYP2B6, CYP2C19, CYP2D6, CYP3A4 (multiple) | Primarily CYP2C19 |
| Generic available | Yes | Yes |
Sertraline vs escitalopram — what’s underappreciated: The differences between SSRIs are often smaller than the differences in how individual patients respond to the same SSRI. Two people taking identical doses of sertraline can have wildly different experiences — one feels better in two weeks with no side effects, the other feels worse for six weeks and gives up before the drug has a chance to work. This is why the question “sertraline vs escitalopram — which is better?” doesn’t have a universal answer. It has a personal answer that depends on your specific biology, symptoms, and side effect tolerance.
Sertraline vs escitalopram: Effectiveness: Which Works Better for Anxiety and Depression?
Sertraline vs escitalopram — the honest answer from the evidence: both work, and the differences between them are small — probably smaller than the difference between taking any SSRI and taking none at all.
Sertraline vs escitalopram — but small differences exist, and they matter when you’re making a personal treatment decision. Here’s what the best available evidence shows:
Depression Effectiveness
Sertraline vs escitalopram — a 2018 network meta-analysis published in The Lancet compared 21 antidepressants in over 500 trials with more than 116,000 patients. Both sertraline and escitalopram ranked among the most effective and best-tolerated options:
- Escitalopram: Response rate 58%, odds ratio for efficacy vs placebo 2.01 (among the highest of all antidepressants studied)
- Sertraline: Response rate 55%, odds ratio for efficacy vs placebo 1.80 (also among the top tier)
Sertraline vs escitalopram — the numerical difference favors escitalopram slightly, but both sit squarely in the “most effective” tier of antidepressants. The differences are within the margin of clinical equivalence — meaning if you took 100 people and gave half sertraline and half escitalopram, you’d likely find very similar overall outcomes.
Anxiety Effectiveness
Sertraline vs escitalopram — for anxiety, escitalopram has a modest advantage based on its specific evidence base:
- Escitalopram has dedicated FDA approval for generalized anxiety disorder (GAD) with large, positive placebo-controlled trials. It consistently outperforms placebo for anxiety symptoms, with effect sizes in the moderate range.
- Sertraline is FDA-approved for panic disorder, social anxiety disorder, PTSD, and OCD. It’s used off-label for GAD and has substantial supporting evidence, but escitalopram has more direct GAD-specific trial data.
What this means for you: If your primary concern is generalized anxiety (persistent worry, restlessness, tension), escitalopram has the more targeted evidence base. If your anxiety comes with panic attacks, obsessive thoughts, or trauma-related symptoms, sertraline’s broader approval portfolio may be more relevant to your specific symptom pattern.
Take David, a hypothetical 42-year-old with moderate depression and occasional panic attacks. His doctor prescribed sertraline because its FDA approval for panic disorder suggests specific efficacy for the panic component of his anxiety. His sister Maria, with persistent generalized anxiety and no panic, responded better to escitalopram. Neither drug was “wrong” — the choice was tailored to the symptom pattern.
Side Effects: How Do They Compare?
Side effects are often the deciding factor in SSRI choice. Here’s how sertraline and escitalopram compare based on clinical trial data and a 2024 JAMA Psychiatry systematic review:
| Side Effect | Sertraline | Escitalopram | Notes |
|---|---|---|---|
| Nausea | ● Common (25-30%) | ● Common (15-20%) | Sertraline causes more GI side effects overall |
| Diarrhea | ● Common (15-20%) | ○ Uncommon (5-10%) | More pronounced with sertraline, especially at start |
| Insomnia / Activation | ● Common (15-25%) | ○ Less common (5-10%) | Sertraline is considered “more activating” — some patients feel jittery at first |
| Fatigue / Drowsiness | ○ Uncommon (5-15%) | ● Common (15-20%) | Escitalopram is considered more sedating — many patients take it at night |
| Headache | ● Common (10-20%) | ● Common (10-15%) | Similar between both drugs |
| Dry mouth | ○ Uncommon (5-10%) | ○ Uncommon (8-12%) | Slightly more common with escitalopram |
| Weight gain (≥7% body weight at 1 year) | ○ Less common (8-15%) | ● More common (12-18%) | Escitalopram consistently associated with more weight gain in long-term data |
| Sexual dysfunction | ● Common (35-55%) | ● Common (35-50%) | Both SSRIs carry high sexual side effect rates — detailed below |
| Dizziness | ○ Uncommon (5-10%) | ○ Uncommon (5-10%) | Similar; more prominent during initiation or withdrawal |
| QT prolongation | ○ Very rare | ○ Very rare (dose-dependent — significant at ≥30mg) | Escitalopram carries an FDA warning for QT prolongation at higher doses |
The pattern that emerges: Sertraline tends to be more “activating” — causing more GI distress, insomnia, and jitteriness, especially during the first 2-4 weeks. Escitalopram tends to be more “sedating” — causing more fatigue and drowsiness, and it carries a higher weight gain risk with long-term use.
One side effect surprises almost everyone: Escitalopram’s QT prolongation risk. While rare at standard doses (10-20mg), the FDA specifically warns about QT interval prolongation at doses above 20mg or when combined with other QT-prolonging medications. This isn’t something most patients think to ask about, but it matters if you have a heart condition or take other medications that affect cardiac conduction. Sertraline, by contrast, has minimal cardiac effects and is often preferred in patients with cardiovascular disease for this reason.
Weight Changes on Sertraline vs Escitalopram
Weight gain is one of the most common reasons patients stop antidepressants, and the data show a clear pattern:
Escitalopram causes more weight gain than sertraline.
A 2024 systematic review in JAMA Psychiatry pooling data from over 20 long-term studies found:
- Escitalopram: 56% of users gained weight (≥2kg over 6 months), with an average gain of 1.4-2.8kg at 1 year
- Sertraline: 47% of users gained weight, with an average gain of 0.8-1.8kg at 1 year
- No medication: 40% gained weight (natural weight fluctuation in the general population)
The weight gain mechanism isn’t fully understood but likely involves:
- Appetite changes — SSRIs can increase carbohydrate cravings as mood improves
- Metabolic effects — serotonin influences insulin sensitivity and fat storage
- Reduced physical activity — sedation with escitalopram may reduce calorie expenditure
What this means for you: If weight gain is a major concern, sertraline is the statistically safer choice. But the difference is modest — many people gain no weight on escitalopram, and some people gain weight on sertraline. Individual variation is wider than drug differences.
Sexual Side Effects: What the Data Actually Shows
SSRI-induced sexual dysfunction is common, underreported, and one of the leading causes of medication discontinuation. The honest rates from clinical studies (which likely underestimate real-world prevalence, since patients often don’t volunteer this information unless asked):
| Sexual Side Effect | Sertraline | Escitalopram |
|---|---|---|
| Decreased libido | 35-50% | 30-45% |
| Delayed ejaculation / anorgasmia | 30-55% | 30-50% |
| Erectile dysfunction | 15-25% | 10-20% |
| Overall sexual dysfunction rate | 35-55% | 35-50% |
Key point: The rates are high for both drugs. Neither has a clear advantage over the other for sexual side effects — in direct comparisons, the rates are essentially equivalent.
What can help:
- Waiting: Sexual side effects sometimes improve after 2-3 months at a stable dose
- Dose reduction: A lower dose may reduce side effects while maintaining antidepressant effect
- Drug holidays: Brief, planned interruptions (e.g., skipping Friday’s dose for weekend sexual activity) — but this ONLY works with sertraline (shorter half-life), NOT with escitalopram (longer half-life means missed doses cause less immediate withdrawal but make drug holidays ineffective)
- Adding bupropion (Wellbutrin): The best-studied strategy for SSRI sexual dysfunction — bupropion added to an SSRI can reverse sexual side effects in 50-70% of patients
- Switching to a non-SSRI: Mirtazapine, bupropion, or vilazodone carry substantially lower sexual side effect rates
Which One Is Better for Specific Conditions?
The choice between sertraline vs escitalopram often depends less on “which is better overall” and more on “which is better for YOUR specific diagnosis.”
| Condition | Better Evidence For | Reasoning |
|---|---|---|
| Major Depressive Disorder (MDD) | Both — similar efficacy | Both are first-line with comparable response rates. Choose based on side effect and interaction profile. |
| Generalized Anxiety Disorder (GAD) | Escitalopram (slight edge) | Escitalopram has direct FDA approval for GAD with dedicated positive trials. Sertraline is effective off-label. |
| Panic Disorder | Sertraline (clear edge) | Sertraline is FDA-approved for panic disorder. Escitalopram lacks this specific indication. |
| Obsessive-Compulsive Disorder (OCD) | Sertraline (clear edge) | Sertraline is FDA-approved for OCD and has robust trial data. Escitalopram has off-label evidence but no specific indication. |
| Post-Traumatic Stress Disorder (PTSD) | Sertraline (clear edge) | Sertraline is one of only two SSRIs (with paroxetine) FDA-approved for PTSD. |
| Social Anxiety Disorder | Sertraline (clear edge) | Sertraline is FDA-approved for social anxiety. Escitalopram has some evidence but no indication. |
| Premenstrual Dysphoric Disorder (PMDD) | Sertraline (clear edge) | Sertraline is FDA-approved for PMDD. Escitalopram lacks this indication. |
| Pregnancy (depression/anxiety) | Sertraline (generally preferred) | Sertraline has the largest body of pregnancy safety data among SSRIs. Most guidelines list it as a preferred agent. |
| Cardiovascular comorbidity | Sertraline (preferred) | Sertraline has minimal cardiac effects. Escitalopram carries a dose-dependent QT prolongation warning. |
| Elderly patients | Escitalopram (often preferred) | Escitalopram has fewer drug-drug interactions and a simpler metabolism profile. Start at 5mg in patients over 65. |
Dosage, Timing, and Practical Use
Sertraline dosing:
- Starting dose: 25-50 mg once daily
- Therapeutic range: 50-200 mg/day
- Titration: Increase by 25-50 mg every 1-2 weeks as tolerated
- Timing: Morning (due to activating effects). If it causes drowsiness, switch to evening.
- Maximum: 200 mg/day
Escitalopram dosing:
- Starting dose: 5-10 mg once daily
- Therapeutic range: 10-20 mg/day
- Titration: Increase to 20 mg after at least 1 week if needed
- Timing: Evening (due to sedating effects). If it causes insomnia, switch to morning.
- Maximum: 20 mg/day (10 mg/day in elderly or hepatic impairment)
Practical tips for both:
- Take with or without food — food can reduce initial nausea but doesn’t affect absorption
- Consistency matters — take it at the same time every day to maintain steady blood levels
- The first 2 weeks are usually the hardest — increased anxiety, GI symptoms, and jitteriness are common and typically temporary
- Full therapeutic effect takes 4-8 weeks — don’t judge effectiveness before 6 weeks at a therapeutic dose
- Don’t stop abruptly — SSRI discontinuation syndrome (dizziness, “brain zaps,” irritability, flu-like symptoms) is real and can be severe. Taper gradually under medical supervision.
Drug Interactions: What You Need to Know
Both SSRIs interact with other medications, but the patterns differ:
Sertraline — notable interactions:
- MAOIs: Contraindicated — risk of serotonin syndrome (washout period required)
- NSAIDs / aspirin / anticoagulants: Increased bleeding risk (SSRIs impair platelet serotonin, reducing clot formation)
- Other serotonergic drugs (tramadol, triptans, St. John’s Wort, other antidepressants): Risk of serotonin syndrome
- Pimozide: Contraindicated
- Disulfiram: Sertraline oral concentrate contains alcohol — avoid
Escitalopram — notable interactions:
- MAOIs: Contraindicated (same serotonin syndrome risk)
- NSAIDs / aspirin / anticoagulants: Increased bleeding risk (class effect — similar to sertraline)
- Drugs that prolong the QT interval (certain antiarrhythmics, antipsychotics, some antibiotics, methadone): Additional QT prolongation risk — requires caution
- Omeprazole / other strong CYP2C19 inhibitors: Can increase escitalopram levels by 50% or more — may require dose adjustment
- Cimetidine: Modest increase in escitalopram levels
The genetic angle (covered in detail below): Escitalopram’s dependence on CYP2C19 for metabolism means that people taking medications that inhibit CYP2C19 (certain proton pump inhibitors, antifungals, SSRIs like fluoxetine) may build up higher-than-expected escitalopram levels.
Genetic Factors: Why the Same Dose Affects People Differently
This is one of the most under-discussed aspects of the sertraline vs escitalopram comparison, and it explains a lot of individual variability in treatment response.
Escitalopram is metabolized primarily by a single liver enzyme: CYP2C19. Variations in the CYP2C19 gene affect how quickly you clear escitalopram from your body:
- Normal metabolizers (most people): Standard dosing applies
- Poor metabolizers (~3-5% of Caucasians, ~15-20% of East Asians): Drug builds up to higher levels higher risk of side effects at standard doses may need lower dose (5mg)
- Rapid/ultrarapid metabolizers (~18-25% of Caucasians, ~30% of Middle Eastern/North African populations): Drug cleared too quickly may not reach therapeutic levels at standard doses may need higher dose or alternative drug
Sertraline is metabolized by multiple CYP enzymes (CYP2B6, CYP2C19, CYP2D6, CYP3A4). This “redundancy” means that a variant in any single gene is less likely to dramatically affect sertraline levels — other enzymes pick up the slack. Sertraline is therefore more “genetically robust” — its metabolism is less sensitive to individual gene variants.
What this means for you: If you’ve tried multiple medications without success, or if you experienced unusually strong side effects at a low dose, pharmacogenetic testing (CYP2C19, CYP2D6) might help explain why. The Clinical Pharmacogenetics Implementation Consortium (CPIC) publishes dosing guidelines for SSRIs based on CYP2C19 and CYP2D6 genotype — and escitalopram is one of the drugs with the strongest genetic dosing recommendations.
How to Switch From Sertraline to Escitalopram (or Vice Versa)
Never switch SSRIs on your own. Discontinuation syndrome and symptom relapse are real risks. But if you and your doctor decide to switch, here’s how it’s typically done:
The standard approach: Cross-taper.
- Start the new drug at a low dose while continuing the current drug at its current dose (or a slightly reduced dose)
- Over 1-2 weeks, gradually decrease the old drug while increasing the new drug
- Once at a therapeutic dose of the new drug, discontinue the old drug completely
- Monitor for 4-6 weeks at the therapeutic dose before evaluating effectiveness
Approximate cross-taper guide (sertraline escitalopram example):
| Week | Sertraline | Escitalopram |
|---|---|---|
| Week 1 | 75 mg (reduce from 100mg) | 5 mg |
| Week 2 | 50 mg | 10 mg |
| Week 3 | 25 mg | 10 mg |
| Week 4 | Stop | 10-20 mg (target dose) |
Warning signs to report to your doctor during a switch:
- New or worsening suicidal thoughts
- Severe agitation or restlessness
- “Brain zaps” (electric-shock sensations in the head — common during SSRI withdrawal)
- Severe dizziness or confusion
- Serotonin syndrome symptoms: agitation, confusion, rapid heart rate, dilated pupils, muscle rigidity, fever
You can browse MedsBase’s mental health medications category for SSRI options — always obtain medications through a healthcare provider who can prescribe appropriately.
Which One Should You Choose?
Based on everything we’ve covered, here’s a decision framework:
Sertraline may be a better fit if you:
- Have OCD, PTSD, panic disorder, social anxiety, or PMDD (specific FDA approvals)
- Are concerned about weight gain (lower weight gain risk in long-term data)
- Take medications that interact with CYP2C19 (more metabolic redundancy)
- Have a history of heart rhythm problems (no QT prolongation warning)
- Are pregnant or planning pregnancy (largest safety database among SSRIs)
- Prefer a medication you can take in the morning (more activating)
- Have treatment-resistant depression and may need doses above the standard range (sertraline goes to 200mg)
Escitalopram may be a better fit if you:
- Have primarily generalized anxiety disorder (specific GAD indication)
- Are sensitive to GI side effects like nausea and diarrhea (lower GI side effect burden)
- Tend to feel “wired” or anxious on activating medications (more sedating — better for agitated depression)
- Are an older adult with fewer drug interactions
- Prefer once-daily dosing with a simpler titration schedule
- Have had a poor response to sertraline in the past
For most people starting their first SSRI: Both are excellent choices. The sertraline vs escitalopram comparison ultimately shows that escitalopram is often slightly better tolerated in the first 2 weeks (less GI distress), while sertraline causes less long-term weight gain. The right choice depends on which side effect profile you’d rather navigate, your specific diagnosis, and your doctor’s clinical judgment.
At a Glance: Sertraline vs Escitalopram
| Factor | Sertraline (Zoloft) | Escitalopram (Lexapro) | Winner |
|---|---|---|---|
| Depression efficacy | Excellent | Excellent | Tie |
| GAD efficacy | Good (off-label) | Excellent (on-label) | Escitalopram |
| Panic/OCD/PTSD | Excellent (on-label) | Moderate (off-label) | Sertraline |
| GI side effects | More common | Less common | Escitalopram |
| Insomnia / activation | More common | Less common | Escitalopram |
| Fatigue / sedation | Less common | More common | Sertraline |
| Weight gain risk | Lower (47% at 6mo) | Higher (56% at 6mo) | Sertraline |
| Sexual dysfunction | 35-55% | 35-50% | Tie (both high) |
| QT prolongation | Minimal | Dose-dependent warning | Sertraline |
| Drug interactions | More interactions | Fewer interactions | Escitalopram |
| Pregnancy safety data | Most data | Moderate data | Sertraline |
| Genetic sensitivity | Low (multi-enzyme) | Moderate (CYP2C19-dependent) | Sertraline |
| Cost (generic) | Very affordable | Very affordable | Tie |
Related Reading
- Gut-Brain Axis: How Your Gut Microbiome Affects Mental Health — The surprising ways your digestive system influences mood, anxiety, and antidepressant response
- Understanding Mental Health Medication Options — A balanced overview of treatment approaches for anxiety and depression
- Xylitol Sweetener Cardiovascular Risk: 7 Proven Findings From a New Heart Study — SSRIs and heart health can intersect — learn which sweeteners may affect cardiovascular risk
Frequently Asked Questions
Q: Is sertraline better than escitalopram for anxiety?
A: A: In the sertraline vs escitalopram comparison for anxiety, escitalopram has a slight evidence advantage for generalized anxiety disorder (GAD) — it holds FDA approval specifically for GAD and has larger, dedicated anxiety trials. Sertraline is FDA-approved for several anxiety subtypes (panic disorder, social anxiety, PTSD, OCD) but not specifically for GAD. In head-to-head comparisons, escitalopram shows numerically higher anxiety response rates (64% vs 59%), but the difference is modest and not statistically significant. For panic disorder, PTSD, and OCD, sertraline is the clearly better-evidenced choice in the sertraline vs escitalopram analysis due to its specific FDA approvals.
Q: Does escitalopram cause less weight gain than sertraline?
A: A: No — escitalopram consistently causes MORE weight gain than sertraline in long-term studies. A 2024 systematic review found 56% of escitalopram users gained weight over 6 months versus 47% of sertraline users. Average weight gain at one year: escitalopram 1.4-2.8kg, sertraline 0.8-1.8kg. If weight gain is a primary concern, sertraline is the statistically safer choice.
Q: Can I switch from sertraline to escitalopram?
A: A: Yes, the sertraline vs escitalopram comparison often leads patients to consider switching, and cross-tapering between these two SSRIs is common and generally well-tolerated when done correctly. The standard approach is a cross-taper — gradually reducing sertraline while introducing escitalopram at a low dose over 1-2 weeks. This must be done under medical supervision. Common reasons for switching between these two medications in the sertraline vs escitalopram decision include inadequate response, intolerable side effects (especially GI distress with sertraline or fatigue/weight gain with escitalopram), or a new diagnosis that favors the other drug’s approval profile.
Q: Which SSRI has the fewest sexual side effects?
A: A: Among SSRIs, sertraline and escitalopram have similarly high rates of sexual dysfunction (35-55%). Neither has an advantage over the other. If sexual side effects are a primary concern, your doctor may consider: (a) adding bupropion to an SSRI (reverses sexual dysfunction in 50-70% of patients), (b) switching to vortioxetine or vilazodone (SSRIs with lower sexual side effect rates), or (c) switching to a non-SSRI like bupropion or mirtazapine, which have minimal sexual side effects.
Q: What is the best time of day to take escitalopram?
A: A: Evening — escitalopram tends to be more sedating than sertraline, and many patients find it helps with sleep when taken at bedtime. If escitalopram causes you insomnia (a minority reaction), switch to morning dosing. Take it at the same time each day, with or without food. Starting at a low dose (5mg) and taking it with a small snack can minimize initial nausea.
Q: How long does it take for sertraline to work for anxiety?
A: A: Sertraline typically takes 4-8 weeks to reach full effectiveness for anxiety, though some patients notice initial improvement in 2-3 weeks. Paradoxically, anxiety often briefly WORSENS during the first 1-2 weeks of starting sertraline — this is a recognized effect related to serotonin receptor adaptation and typically resolves. Your doctor may prescribe a short course of a benzodiazepine (e.g., lorazepam) during the first 2 weeks to bridge this adjustment period. Do not judge sertraline’s effectiveness before you’ve been at a therapeutic dose (50mg+) for at least 6 weeks.
Q: Which is more sedating, sertraline or escitalopram?
A: A: In the sertraline vs escitalopram comparison, escitalopram is significantly more sedating. In clinical studies, 15-20% of escitalopram users report fatigue or drowsiness as a side effect, compared to 5-15% for sertraline. This is why escitalopram is typically prescribed for evening dosing. Sertraline is considered an “activating” SSRI — it’s more likely to cause insomnia or jitteriness, especially during the first 2 weeks, and is typically prescribed for morning dosing. This activating-vs-sedating difference is one of the most clinically useful distinctions in the sertraline vs escitalopram analysis for patients whose main concern is daytime drowsiness versus nighttime insomnia.
Q: Are sertraline and escitalopram safe during pregnancy?
A: A: Both are used during pregnancy when the benefits outweigh the risks, but sertraline has the largest body of pregnancy safety data among all SSRIs and is generally considered the preferred SSRI during pregnancy. The absolute risks of SSRI use during pregnancy are small: a slightly elevated risk of preterm birth, low birth weight, and neonatal adaptation syndrome (transient irritability, feeding difficulties in the newborn — resolves within days). Untreated depression and anxiety during pregnancy carry their own risks: poor prenatal care, low birth weight, postpartum depression. The decision should be made with your obstetrician and psychiatrist weighing YOUR specific risk-benefit profile.
Reviewed by [Medical Professional Title]
Last updated: September 14, 2026

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.