








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
metoprolol tartrate vs metoprolol succinate — Metoprolol Tartrate vs Metoprolol Succinate: 7 Key Differences for Blood Pressure Control. Read on for an evidence-backed guide covering everything you need to know.
Metoprolol tartrate vs metoprolol succinate — you have been taking metoprolol for months. Your blood pressure is stable, you have adjusted to the medication, and your routine is set. Then you pick up your refill, glance at the label, and notice something different: the label says “metoprolol succinate” instead of “metoprolol tartrate.”
Metoprolol tartrate vs metoprolol succinate — same pharmacy. Same medication name. Different word at the end.
Metoprolol tartrate vs metoprolol succinate — is this the same drug? Is it a generic substitution? Should you be calling your doctor or your pharmacist right now?
Metoprolol tartrate vs metoprolol succinate — here is the short answer: metoprolol tartrate and metoprolol succinate contain the exact same active ingredient — metoprolol — but they release it into your body in fundamentally different ways. The tartrate version is immediate-release, which means it enters your bloodstream quickly and requires dosing two or even three times per day. The succinate version is extended-release, designed to deliver a steady amount of medication over 24 hours from a single daily dose.
Metoprolol tartrate vs metoprolol succinate — the difference is not cosmetic. It affects how often you take the medication, how your body responds through the day, which medical conditions each formulation is specifically approved to treat, whether you need to take it with food, and — in many cases — whether your insurance covers one version and not the other.
Metoprolol tartrate vs metoprolol succinate — if your pharmacy switched your formulation without explanation, you are right to be curious. And if your doctor recommended a switch, understanding why can make the transition smoother.
Metoprolol tartrate vs metoprolol succinate — by the end of this article, you will know exactly how the two formulations differ across seven critical dimensions in the metoprolol tartrate vs metoprolol succinate comparison, when each version is the better choice, what to expect if you are switching, and the safety rules that apply regardless of which metoprolol you take.
Key Takeaways
- Metoprolol tartrate and metoprolol succinate are the same active drug with different release mechanisms: immediate-release (twice daily) versus extended-release (once daily)
- Tartrate must be taken with food to maximize absorption by up to 40%; succinate’s absorption is not affected by food
- Only succinate is FDA-approved for stable heart failure — based on the landmark MERIT-HF trial that showed a 34% reduction in all-cause mortality
- Tartrate is preferred for angina because the peak-and-trough release better matches the intermittent nature of angina episodes
- When switching formulations, the total daily dose is roughly equivalent — but the dosing schedule changes (once-daily vs twice-daily), and you need blood pressure monitoring for the first week
- Never stop either formulation abruptly — beta-blocker withdrawal can cause rebound tachycardia, chest pain, and in susceptible people, heart attack
- What Is Metoprolol? The Same Drug, Two Different Delivery Systems
- How Does Metoprolol Work?
- 7 Key Differences: Tartrate vs Succinate
- #1 Immediate-Release vs Extended-Release
- #2 Dosing Frequency: Twice Daily vs Once Daily
- #3 Approved Conditions: What Each Formulation Treats
- #4 Food Interaction: Why Tartrate Must Be Taken With Food
- #5 Side-Effect Profiles
- #6 Generic Cost Comparison
- #7 Availability and Insurance Coverage
- Switching Between Formulations: What to Expect
- What the Research Says
- Metoprolol vs Other Beta-Blockers: Quick Comparison
- Frequently Asked Questions
- The Bottom Line
What Is Metoprolol? The Same Drug, Two Different Delivery Systems — Metoprolol tartrate vs metoprolol succinate Explained
Metoprolol tartrate vs metoprolol succinate — metoprolol belongs to a class of medications called beta-blockers — specifically, it is a cardioselective beta-1 blocker. This means at therapeutic doses, it preferentially blocks beta-1 receptors, which are concentrated in the heart, rather than beta-2 receptors, which are found in the lungs and blood vessels. This cardioselectivity gives metoprolol an advantage over older, non-selective beta-blockers like propranolol: it is less likely to trigger bronchospasm in people with asthma or COPD and less likely to cause cold hands and feet from peripheral vasoconstriction.
Quick Answer: Metoprolol is a cardioselective beta-blocker used to treat high blood pressure, angina, and heart failure. The tartrate salt is immediate-release (dosed 2–3 times daily); the succinate salt is extended-release (dosed once daily). Both contain the identical active drug molecule — metoprolol — but release it at different rates.
The word after “metoprolol” — tartrate or succinate — refers to the salt form. The salt determines the physical properties of the tablet, including how quickly it dissolves and how it is absorbed. Metoprolol tartrate dissolves rapidly in the stomach, producing a quick peak in blood levels followed by a decline. Metoprolol succinate is formulated as a controlled-release pellet system: the tablet contains hundreds of tiny pellets, each with a polymer coating that dissolves at a controlled rate, releasing metoprolol steadily over approximately 20 hours.
This is not an unusual arrangement in medicine. Many drugs come in both immediate-release and extended-release forms: metformin IR vs ER, bupropion SR vs XL, venlafaxine IR vs XR, carbamazepine IR vs ER. The principle is always the same — the IR version works quickly and wears off quickly; the ER version provides a smoother, more sustained effect with less frequent dosing.
How Does Metoprolol Work? — Metoprolol tartrate vs metoprolol succinate Explained
To understand why the two formulations are used differently, it helps to understand what metoprolol is doing in your body.
Your heart rate and the force with which your heart contracts are controlled partly by the sympathetic nervous system — your body’s “fight or flight” system. When you are stressed, exercising, or simply going about your day, your sympathetic nerves release norepinephrine, which binds to beta-1 receptors on your heart muscle cells. This binding triggers a cascade that increases your heart rate and the strength of each contraction — raising your cardiac output and, consequently, your blood pressure.
Metoprolol sits on those same beta-1 receptors and blocks norepinephrine from binding. The result: your heart beats more slowly and with less force. Your cardiac output drops. Your blood pressure drops. And because your heart is working less hard, it needs less oxygen — which is why metoprolol also helps prevent angina (chest pain caused by insufficient oxygen supply to the heart muscle).
Research Spotlight: Metoprolol also reduces renin release from the kidneys, which lowers angiotensin II and aldosterone — two hormones that raise blood pressure through vasoconstriction and sodium retention. This adds a second, complementary mechanism to metoprolol’s blood pressure-lowering effect beyond simply slowing the heart.
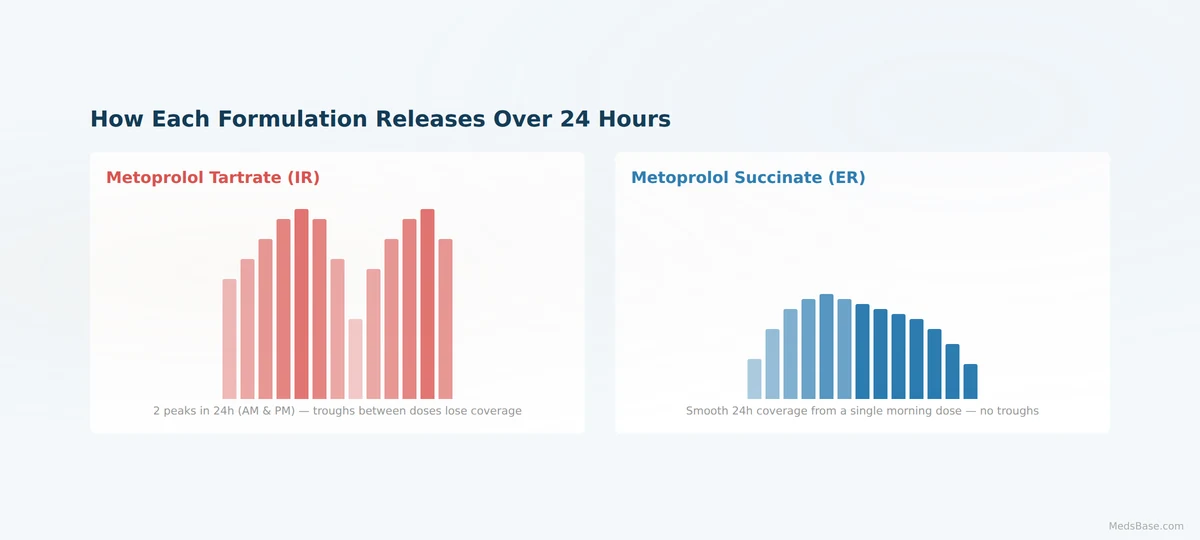
The immediate-release formulation (tartrate) reaches peak blood levels in about 1.5–2 hours and has a half-life of roughly 3–4 hours. This is why it is typically dosed twice daily — sometimes three times daily for angina. The extended-release formulation (succinate) produces a much flatter concentration curve, reaching a lower and broader peak at 4–6 hours and maintaining therapeutic levels for roughly 24 hours. This is why a single daily dose suffices.
Metoprolol tartrate vs metoprolol succinate: 7 Key Differences: Tartrate vs Succinate
Difference #1: Immediate-Release vs Extended-Release
The metoprolol tartrate vs metoprolol succinate question is fundamentally about release mechanism — immediate versus extended — and that single difference cascades into every practical aspect of how these medications are used.
Metoprolol tartrate tablets dissolve quickly. Within minutes of reaching your stomach, the tablet disintegrates and the drug enters your bloodstream relatively rapidly. Blood levels peak at 1.5–2 hours and then decline at a rate determined by the drug’s short half-life of 3–4 hours. By 8–12 hours after a dose, blood levels have dropped significantly.
Metoprolol succinate uses a multi-particulate controlled-release system. The tablet contains hundreds of tiny drug-containing pellets, each coated with an ethylcellulose polymer membrane. When the tablet reaches the stomach, it disintegrates into individual pellets. Stomach fluid slowly penetrates the polymer coating, dissolving the metoprolol inside at a controlled rate. The pellets release the drug over approximately 20 hours as they travel through the gastrointestinal tract.
The clinical consequence is straightforward: tartrate gives you peaks and troughs; succinate gives you a steady therapeutic level. For conditions where around-the-clock beta-blockade is desirable — like hypertension and heart failure — the steady level of succinate is generally preferred. For conditions where episodes of beta-blockade tied to activity are desirable — like angina triggered by exertion — the controllable peaks of tartrate may actually be an advantage.
Difference #2: Dosing Frequency — Twice Daily vs Once Daily
The metoprolol tartrate vs metoprolol succinate dosing comparison is one of the most practical differences patients encounter.
Because metoprolol tartrate has a short duration of action, it is typically dosed twice daily, with examples being 25 mg or 50 mg in the morning and the same dose again 12 hours later. For angina, some patients require three-times-daily dosing to maintain adequate beta-blockade throughout the day.
Metoprolol succinate is dosed once daily. The most common starting dose for hypertension is 25–50 mg once daily, titrated up to a maximum of 200 mg once daily. For heart failure, the starting dose is typically 12.5–25 mg once daily, slowly uptitrated to a target of 200 mg once daily over several weeks or months.
The once-daily dosing of succinate has an important real-world advantage: medication adherence. Studies consistently show that once-daily medications are taken more reliably than twice-daily medications. A meta-analysis published in the Archives of Internal Medicine found that adherence rates were approximately 20% higher for once-daily compared to twice-daily dosing regimens across cardiovascular medications. For a medication where missed doses can lead to rebound tachycardia and blood pressure spikes, this difference matters.
Difference #3: Approved Conditions — What Each Formulation Treats
The metoprolol tartrate vs metoprolol succinate question becomes critically important when you look at what each formulation is actually approved to treat.
This is where the clinical evidence diverges sharply, and it is arguably the most important difference to understand.
Metoprolol tartrate (immediate-release) is FDA-approved for:
- Hypertension (high blood pressure)
- Angina pectoris (chest pain due to coronary artery disease)
- Post-myocardial infarction (after a heart attack, to reduce the risk of another one)
Metoprolol succinate (extended-release) is FDA-approved for:
- Hypertension
- Angina pectoris
- Stable symptomatic heart failure (NYHA Class II–III) — this is the critical distinction
The heart failure indication for metoprolol succinate is based on the landmark MERIT-HF trial (Metoprolol CR/XL Randomized Intervention Trial in Congestive Heart Failure), published in 1999 in The Lancet. This study randomized nearly 4,000 patients with stable heart failure (NYHA Class II–IV) to metoprolol succinate or placebo on top of standard therapy. The result: a 34% reduction in all-cause mortality in the metoprolol group. The trial was stopped early because the benefit was so clear that it would have been unethical to continue giving placebo.
Metoprolol tartrate has never demonstrated a mortality benefit in heart failure in a large randomized trial. It is not interchangeable with the succinate formulation for this indication. If you have heart failure and are prescribed “metoprolol,” it must be the succinate (extended-release) formulation. This is not a minor distinction — it is a guideline-level recommendation backed by trial evidence.
For angina, metoprolol tartrate taken twice or three times daily may actually be preferred because the peaks in blood levels can be timed to anticipated periods of exertion. The succinate formulation provides steady background beta-blockade, which is also effective for stable angina but may not be as tailored to intermittent episodes.
Difference #4: Food Interaction — Why Tartrate Must Be Taken With Food
This is a practical aspect of the metoprolol tartrate vs metoprolol succinate difference that surprises many patients.
Metoprolol tartrate should be taken with food or immediately after a meal. The reason is pharmacokinetic: food increases the bioavailability of metoprolol tartrate by roughly 30–40%, meaning your body absorbs significantly more of the medication when it is taken with food. If you take it on an empty stomach, you may be getting only 60–70% of the intended dose — which could translate to less effective blood pressure control.
Metoprolol succinate, by contrast, has food-independent absorption. You can take it with or without food, and your body will absorb a consistent amount of the drug either way. The controlled-release mechanism, not stomach contents, governs the rate of absorption.
In practice: if you take metoprolol tartrate, have it with breakfast and dinner. If you take metoprolol succinate, pick a time of day you will remember consistently — with or without food, morning or evening, as long as it is the same time each day.
Difference #5: Side-Effect Profiles
The side effects of both formulations are similar because they involve the same drug, but the metoprolol tartrate vs metoprolol succinate experience differs in how these side effects are perceived through the day.
Tartrate: The rapid peak in blood levels can produce a noticeable early side-effect window — for example, feeling more tired or lightheaded 1–2 hours after taking the tablet. Then, as levels drop between doses, side effects may ease — but so may blood pressure control. The peaks and troughs mean you are more likely to notice the medication “wearing off” in the hours before your next dose.
Succinate: Side effects tend to be more even through the day because drug levels are more even. You are less likely to feel the medication “kick in” and less likely to feel it wear off. This smoother profile is generally better tolerated, particularly by people sensitive to the fatigue or lightheadedness that beta-blockers can cause.
Common side effects of both formulations include fatigue, dizziness, slow heart rate (bradycardia), cold hands and feet, and sleep disturbances (including vivid dreams and nightmares — see Post 1 in today’s cluster for more on beta-blockers and REM sleep). Both formulations can cause bronchospasm in susceptible individuals, though the cardioselectivity of metoprolol makes this less likely than with non-selective beta-blockers.
One side effect that is sometimes more noticeable with the tartrate formulation is rebound symptoms between doses — a temporary increase in heart rate or blood pressure as the medication’s effect wanes. This can feel like the medication is “not lasting.” The extended-release formulation largely eliminates this pattern.
Difference #6: Generic Cost Comparison
In the metoprolol tartrate vs metoprolol succinate cost analysis, both formulations are widely available as generics and are typically affordable. Exact prices vary by pharmacy, insurance plan, and location, but the general pattern is:
- Metoprolol tartrate 25 mg, 60 tablets (one month at twice daily): typically $4–15 without insurance
- Metoprolol succinate 25 mg, 30 tablets (one month at once daily): typically $10–25 without insurance
The succinate formulation is generally slightly more expensive because the extended-release technology is more costly to manufacture. However, both are on virtually all insurance formularies and are among the most affordable blood pressure medications available. For most patients, the cost difference between the two formulations is modest — typically less than $10 per month.
Difference #7: Availability and Insurance Coverage
The metoprolol tartrate vs metoprolol succinate insurance landscape is worth understanding before you fill your prescription. However, pharmacy substitution is not automatic — metoprolol tartrate and metoprolol succinate are NOT considered therapeutically equivalent by the FDA. This means a pharmacy cannot substitute one for the other without explicit prescriber approval. The FDA’s Orange Book assigns them different therapeutic equivalence codes because they have different release mechanisms, dosing schedules, and approved indications.
Your insurance may prefer one formulation over the other. Some plans require a prior authorization for metoprolol succinate when tartrate is available as a lower-cost alternative, particularly for hypertension (where both are approved). If your doctor specifically prescribes succinate for heart failure, this is rarely challenged because the evidence base for succinate in heart failure is so strong. If you encounter a coverage issue, your doctor can usually resolve it by documenting the medical necessity — particularly if the indication is heart failure or if you have experienced side effects on the tartrate formulation.
Switching Between Formulations: What to Expect
If your doctor recommends switching you from one formulation to the other — or if your insurance requires it — understanding the metoprolol tartrate vs metoprolol succinate conversion matters for your safety. Here is what you need to know.
Switching from tartrate to succinate: The total daily dose is roughly equivalent. If you take metoprolol tartrate 50 mg twice daily (100 mg total per day), the equivalent succinate dose is typically 100 mg once daily. The switch is usually smooth — you stop the tartrate and start the succinate the next morning. The main advantage you will notice is the convenience of once-daily dosing. The main difference you might notice is a smoother side-effect profile — less of a “medication wearing off” feeling in the evening.
Switching from succinate to tartrate: The total daily dose is the same, but it is split in half and taken twice daily. If you take metoprolol succinate 100 mg once daily, the equivalent tartrate regimen is typically 50 mg twice daily — once in the morning and once in the evening, roughly 12 hours apart, both doses with food. The main challenge is remembering the second daily dose. Setting a phone alarm can help.
In both cases: Monitor your blood pressure and heart rate daily for the first 1–2 weeks after switching. Check your resting heart rate before your morning dose — if it drops below 50 beats per minute, or if you feel dizzy, unusually fatigued, or lightheaded, contact your doctor. A dose adjustment may be needed.
Do not switch formulations on your own. Even though the total daily dose is roughly equivalent, the release profile changes mean your body needs time to adjust. Always make the switch under medical supervision, with follow-up blood pressure monitoring scheduled.
What the Research Says

| Study | Year | Finding | Source |
|---|---|---|---|
| MERIT-HF | 1999 | Metoprolol succinate reduced all-cause mortality by 34% in stable heart failure (NYHA II–IV); trial stopped early for overwhelming benefit | The Lancet |
| COMET | 2003 | Metoprolol tartrate not equivalent to carvedilol in heart failure; highlights that only certain beta-blockers (succinate, carvedilol, bisoprolol) have HF mortality evidence | The Lancet |
| Pharmacokinetic IR vs ER | 1989 | Metoprolol succinate produces 24-hour coverage with once-daily dosing; peak-to-trough ratio significantly flatter than IR | European Journal of Clinical Pharmacology |
| Metoprolol food interaction | 1985 | Food increases bioavailability of metoprolol tartrate by 30–40%; succinate absorption food-independent | Clinical Pharmacology & Therapeutics |
| Once-daily vs twice-daily adherence meta-analysis | 2009 | Once-daily dosing associated with ~20% higher adherence across cardiovascular medications | Archives of Internal Medicine |
What this means for you: the evidence around the metoprolol tartrate vs metoprolol succinate comparison supports metoprolol succinate as the preferred formulation for heart failure and for anyone who values the convenience and adherence advantage of once-daily dosing. Metoprolol tartrate remains an excellent and affordable option for hypertension and angina, particularly when the condition benefits from the peak-and-trough release pattern. Both formulations are effective for blood pressure control; the choice is often driven by饠condition, tolerability, and practical factors.
Metoprolol vs Other Beta-Blockers: Quick Comparison

Metoprolol is not the only beta-blocker, and which one is right for you depends on your specific condition. Here is how metoprolol compares to the other commonly prescribed beta-blockers:
| Beta-Blocker | Formulations | Dosing Frequency | Key Indications | Notable Features |
|---|---|---|---|---|
| Metoprolol | Tartrate (IR), Succinate (ER) | 1–3× daily | HTN, angina, HF (succinate only) | Cardioselective; most prescribed beta-blocker globally |
| Bisoprolol | IR only | Once daily | HTN, HF | Highly cardioselective; long half-life (~11 hours); once-daily even as IR |
| Carvedilol | IR, ER | 1–2× daily | HTN, HF, post-MI | Non-selective; also blocks alpha-1 receptors (vasodilation); strong HF evidence |
| Atenolol | IR only | Once daily | HTN, angina | Hydrophilic (less CNS penetration fewer sleep/dream side effects); declining use due to weaker outcomes data |
| Propranolol | IR, ER | 1–3× daily | HTN, angina, migraine prevention, essential tremor, anxiety | Non-selective; lipophilic (CNS penetration vivid dreams common); many non-cardiac uses |
| Nebivolol | IR only | Once daily | HTN | Highly cardioselective; also stimulates nitric oxide release (vasodilation); newer |
For a detailed comparison of metoprolol and bisoprolol specifically, read: Bisoprolol vs Metoprolol: 7 Key Differences.
Frequently Asked Questions
Q: Can metoprolol tartrate and succinate be taken together?
A: No. There is no rationale for combining the two formulations in the metoprolol tartrate vs metoprolol succinate landscape, and doing so would risk excessive beta-blockade (dangerously slow heart rate, low blood pressure). If you need additional blood pressure control while on metoprolol, your doctor will add a medication from a different class — such as an ACE inhibitor, ARB, calcium channel blocker, or diuretic — rather than a second metoprolol product.
Q: Which formulation is better for blood pressure control — tartrate or succinate?
A: For pure blood pressure control in the metoprolol tartrate vs metoprolol succinate debate, both formulations are effective. The choice usually comes down to tolerability and convenience. Metoprolol succinate’s once-daily dosing and smoother side-effect profile make it the more commonly prescribed option for hypertension in current practice. However, metoprolol tartrate is equally effective when taken consistently twice daily and is often less expensive.
Q: Is it safe to take metoprolol at bedtime instead of in the morning?
A: Yes, bedtime dosing of metoprolol is safe and may have advantages. Some studies suggest that taking blood pressure medications at bedtime improves nighttime blood pressure control and may reduce cardiovascular events. With metoprolol succinate, the sustained 24-hour release makes the exact timing less critical as long as it is consistent. With metoprolol tartrate, bedtime dosing for one of the two daily doses is common (e.g., morning + bedtime). If you switch to bedtime dosing, monitor for bradycardia during sleep — a resting heart rate below 50 bpm should be discussed with your doctor.
Q: Does metoprolol cause weight gain?
A: Beta-blockers, including metoprolol, are associated with a modest weight gain of 1–3 kg (2–7 lbs) on average in some studies. The mechanism is thought to involve a slight reduction in metabolic rate (beta-blockers reduce the body’s energy expenditure by approximately 5–10%) and possibly increased fatigue leading to reduced physical activity. This effect is modest and does not occur in everyone. Weight gain from metoprolol is generally less than that seen with older beta-blockers like propranolol.
Q: Can metoprolol be used for anxiety?
A: Yes, metoprolol — particularly the tartrate formulation — is sometimes used off-label for performance anxiety or situational anxiety. In the metoprolol tartrate vs metoprolol succinate context, the tartrate version’s faster onset makes it more suitable for situational use. It works by blocking the physical symptoms of the fight-or-flight response: rapid heart rate, trembling, and sweating. However, metoprolol is not FDA-approved for anxiety disorders, and it does not treat the psychological symptoms of anxiety. It is most commonly used for specific situational anxiety — public speaking, musical performances, important meetings — taken as a single dose 30–60 minutes before the event. Propranolol is more commonly prescribed for this purpose because it is non-selective and crosses the blood-brain barrier more readily.
Q: What happens if I stop metoprolol suddenly?
A: Sudden discontinuation of metoprolol — either formulation in the metoprolol tartrate vs metoprolol succinate comparison — can cause a beta-blocker withdrawal syndrome. This includes rebound tachycardia (heart rate speeds up beyond baseline), rebound hypertension, increased angina frequency, and in susceptible individuals, heart attack or arrhythmia. This happens because chronic beta-blockade causes your beta receptors to upregulate — your heart becomes more sensitive to adrenaline. When the blocker is suddenly removed, that sensitized heart is exposed to normal adrenaline levels, and it overreacts. Always taper metoprolol gradually — typically over 1–2 weeks — under your doctor’s supervision.
Q: Can I drink alcohol while taking metoprolol?
A: Moderate alcohol consumption (up to 1 drink per day for women, up to 2 for men) is generally considered acceptable while taking metoprolol, but alcohol can lower blood pressure further and may worsen the dizziness or lightheadedness beta-blockers can cause. Heavy alcohol use is not recommended — it can raise blood pressure over time and reduces the effectiveness of blood pressure treatment. If you drink alcohol, do so in moderation and be aware that you may feel the effects more strongly while on metoprolol.
The Bottom Line

The metoprolol tartrate vs metoprolol succinate distinction is ultimately about release mechanism, and that single difference determines everything — from how many times a day you take the pill to whether your prescription is appropriate for heart failure. Tartrate is immediate-release, dosed twice daily, must be taken with food, and is approved for hypertension, angina, and post-heart attack protection. Succinate is extended-release, dosed once daily, can be taken with or without food, and carries the additional critically important indication for stable heart failure — backed by a trial that showed a 34% reduction in death.
The choice between them in the metoprolol tartrate vs metoprolol succinate decision should be driven by your specific medical condition, not by which one your pharmacy happens to have in stock. If you have heart failure, you need the succinate formulation. If you have angina that follows a predictable pattern, the tartrate formulation’s peak-and-trough pattern may actually serve you better. If you simply want the convenience and adherence advantage of a once-daily pill, succinate is the practical choice.
If your pharmacy has switched your formulation without explanation, ask your pharmacist and call your doctor. The metoprolol tartrate vs metoprolol succinate switch may be medically reasonable, but you need to know the dosing rules for the new formulation.
Your immediate action: Check your metoprolol bottle right now. The metoprolol tartrate vs metoprolol succinate label difference is subtle but important. If it says “metoprolol tartrate,” confirm you are taking it twice daily and with food. If it says “metoprolol succinate,” confirm the once-daily dosing. If something does not match — for example, you are taking “tartrate” once daily or “succinate” twice daily — call your pharmacist today to clarify.
What to read next:
- Wondering whether amlodipine might be a better fit for you than metoprolol? Amlodipine Side Effects: 10 Common Issues and How to Manage Them
- Curious how metoprolol compares to another widely prescribed beta-blocker? Bisoprolol vs Metoprolol: 7 Key Differences
- On multiple blood pressure medications? Blood Pressure Medication Adherence: 7 Strategies That Actually Work
Medical Disclaimer: This article is for informational purposes only and does not constitute medical advice. The information provided is not a substitute for professional medical diagnosis, treatment, or advice. Always consult your doctor before changing any prescribed medication dosage or regimen. Never stop a beta-blocker abruptly — withdrawal can cause dangerous heart rate and blood pressure increases.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.