








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
menopause hormone therapy cardiovascular disease — Menopause Hormone Therapy Cardiovascular Disease: 7 Proven Timing Facts. Read on for an evidence-backed guide covering everything you need to know.

For nearly two decades, millions of women were told that hormone replacement therapy was dangerous for their hearts. New research — including a landmark 2026 study — suggests the truth is far more nuanced, and the timing of when you start may make all the difference.
If you have spent years weighing the risks and benefits of menopause hormone therapy cardiovascular disease protection, confused by conflicting headlines and well-meaning but outdated advice, you are not alone. The conversation around HRT and heart health has shifted dramatically — and the latest evidence offers clarity that simply did not exist a decade ago.
A September 2026 analysis published in JAMA Internal Medicine, drawing on 20 years of data from the Study of Women’s Health Across the Nation (SWAN), found that women who started menopause hormone therapy cardiovascular disease protection early — during perimenopause or within 10 years of their final period — had a 22% to 27% lower risk of developing heart disease compared to women who never used HRT. For Black women, the protective association reached 49%.
This post unpacks what that study actually found, why timing matters more than anyone realized, how estradiol works to protect your blood vessels, and — most importantly — how to use this information in a real conversation with your own doctor.
Key Takeaways
- Starting menopause hormone therapy cardiovascular disease protection early matters. The SWAN study found a 22% lower CVD risk when MHT began during perimenopause or early postmenopause — and 27% lower when started within 10 years of the final period.
- Black women saw the largest protective signal at 49%. The stratified data revealed a stronger association in Black participants, though the researchers caution this needs confirmation in controlled trials.
- The “timing hypothesis” explains why WHI got it wrong in 2002. The Women’s Health Initiative tested HRT on women averaging 63 years old — far past the window where cardiovascular benefit appears. Reanalysis confirmed younger women near menopause do benefit.
- Estradiol works through multiple heart-protective pathways. It lowers LDL cholesterol, reduces APOB and Lp(a) subparticles, improves nitric oxide signaling in blood vessels, and dampens systemic inflammation — all mechanisms that slow atherosclerosis.
- Vasomotor symptoms are not just uncomfortable — they are risk markers. Frequent or severe hot flashes and night sweats correlate with higher future cardiovascular event risk, making symptom relief a legitimate heart-health conversation.
- This is not a one-size-fits-all decision. A risk-benefit framework, including personal and family history, age, time since menopause, and baseline cardiovascular health, determines whether MHT for heart protection makes sense for you.
Table of Contents
- What Is Menopause Hormone Therapy and Cardiovascular Disease Risk?
- The WHI Scare: Why Women Stopped Menopause Hormone Therapy
- The 2026 SWAN Study: Menopause Hormone Therapy Cardiovascular Disease Protection
- How Menopause Hormone Therapy Protects Against Cardiovascular Disease
- Menopause Hormone Therapy Cardiovascular Disease: Who Benefits Most?
- Types of Menopause Hormone Therapy for Cardiovascular Disease Protection
- What Does the Research Say?
- How to Talk to Your Doctor About Menopause Hormone Therapy and Cardiovascular Disease
- Frequently Asked Questions About Menopause Hormone Therapy Cardiovascular Disease
- The Bottom Line on Menopause Hormone Therapy Cardiovascular Disease
What Is Menopause Hormone Therapy and Cardiovascular Disease Risk?
Menopause hormone therapy cardiovascular disease risk refers to the relationship between taking prescription estrogen (with or without progestin) during the menopausal transition and the likelihood of developing heart attack, stroke, atherosclerosis, or other cardiovascular conditions. The connection is not straightforward — it depends heavily on when you start therapy relative to your final menstrual period, which formulation you use, and your individual baseline risk profile.
Before menopause, estrogen protects your blood vessels by keeping them flexible, supporting healthy cholesterol levels, and reducing inflammation. When your ovaries slow production — starting in perimenopause and continuing for years after — that protection fades. Cardiovascular disease becomes the leading cause of death for postmenopausal women, overtaking even breast cancer.
Menopause hormone therapy (MHT) — also called hormone replacement therapy (HRT) — aims to replace what your body stops making. For heart health specifically, the evidence now points toward a critical concept called the timing hypothesis: starting MHT early, before significant vascular damage accumulates, appears protective. Starting it late, after arteries have already stiffened and plaque has formed, may not help and could carry risk.
Quick Answer: Menopause hormone therapy and cardiovascular disease risk are closely linked through the timing of when you start treatment. A 2026 SWAN analysis found that women who initiated MHT during perimenopause or within 10 years of menopause had 22–27% lower CVD risk — and up to 49% lower among Black women. The key variable is NOT whether you take hormones, but when you begin relative to your body’s vascular aging trajectory.
The WHI Scare: Why Women Stopped Menopause Hormone Therapy
To understand why the conversation around menopause hormone therapy cardiovascular disease protection is making headlines again in 2026, you need to know what happened in 2002.
That summer, the Women’s Health Initiative (WHI) — the largest randomized controlled trial of hormone therapy ever conducted — halted its estrogen-plus-progestin arm early. The preliminary data suggested a small but statistically significant increase in heart attacks, strokes, and breast cancer among women taking combined HRT compared to placebo. The news dominated headlines worldwide. Within months, millions of women discontinued their prescriptions, many without consulting their doctors.
What the headlines missed — and what researchers spent the next two decades untangling — was the age of the women in the study. The average WHI participant was 63 years old, more than a decade past menopause. Many already had subclinical atherosclerosis — plaque silently building in their arteries — even if they had no diagnosed heart disease at enrollment.
By the time those women started estrogen, their blood vessels had already changed. The endothelial lining had stiffened. Estrogen receptors in the arterial wall had downregulated. Adding hormones to arteries that were no longer responsive produced a different biological result than adding them to younger, more elastic vessels that still contained functional estrogen receptors.
This insight — now called the timing hypothesis — reshaped menopause medicine. Reanalysis of WHI data by age group found that women who started HRT within 10 years of menopause showed a trend toward lower cardiovascular risk, not higher. The older group drove the risk signal that scared everyone.
The timing hypothesis forms the foundation of every modern guideline on menopause hormone therapy cardiovascular disease risk assessment. The North American Menopause Society, the Endocrine Society, and multiple international consensus statements now recognize that the benefit-risk ratio depends heavily on the age and health of the blood vessels at the time hormones are introduced.
The 2026 SWAN Study: Menopause Hormone Therapy Cardiovascular Disease Protection

The most compelling evidence yet for the timing hypothesis arrived in September 2026, when researchers published a landmark analysis in JAMA Internal Medicine. Led by Samar R. El Khoudary, PhD, MPH, BPharm, FAHA of Virginia Commonwealth University, the study analyzed 20 years of health data from the Study of Women’s Health Across the Nation (SWAN) — one of the longest-running longitudinal studies of midlife women in the United States.
The analysis included more than 2,700 women with no prior history of heart disease. All participants self-reported their vasomotor symptoms (hot flashes, night sweats) and their use of menopause hormone therapy across multiple study visits spanning two decades. The researchers then tracked cardiovascular disease events — heart attacks, strokes, coronary revascularization procedures, and cardiovascular deaths — to measure the association between MHT timing and heart outcomes.
What they found reshapes the menopause hormone therapy cardiovascular disease conversation:
| Group | CVD Risk Reduction | Timing Condition |
|---|---|---|
| Perimenopause / Early Postmenopause Starters | 22% lower | Initiated MHT during perimenopause or within 3–5 years of final period |
| Within 10 Years of Menopause Onset | 27% lower | Initiated MHT within a decade of the last menstrual period |
| Black Women (Early Starters) | 49% lower | Stratified analysis showing the strongest protective signal overall |
| Late Starters (>10 Years Past Menopause) | No significant reduction | Null or neutral effect — the protective window appears to close after a decade |
Source: El Khoudary et al., JAMA Internal Medicine, September 2026. Observational data from SWAN cohort (n = 2,700+).
The 49% figure for Black women deserves careful reading. Black women in the United States experience disproportionately high rates of cardiovascular disease and more severe vasomotor symptoms during menopause compared to white women. The stronger protective association in this subgroup may reflect a larger margin for improvement — meaning the women at highest baseline risk showed the largest apparent benefit from early MHT. The SWAN researchers emphasize that this finding, while striking, comes from an observational design and requires confirmation in a prospective trial that includes adequate representation of Black participants.
Jennifer Wong, MD, a cardiologist at MemorialCare Heart and Vascular Institute, contextualized the findings: “The study suggests that starting hormone therapy earlier in the menopausal transition may have cardiovascular benefits.” She added that “frequent or severe vasomotor symptoms have been associated with a higher risk of future cardiovascular events” — a connection that makes treating those symptoms through MHT relevant beyond comfort alone.
Dr. Wong’s observation highlights an important clinical shift. Hot flashes and night sweats are not merely quality-of-life complaints to endure — they may signal underlying vascular changes that deserve attention. When you treat vasomotor symptoms with properly timed MHT, you may be addressing two problems simultaneously: symptom relief and cardiovascular protection.
How Menopause Hormone Therapy Protects Against Cardiovascular Disease

Understanding the menopause hormone therapy cardiovascular disease connection requires looking at what happens inside your blood vessels when estrogen levels fall — and what happens when you restore them at the right time.
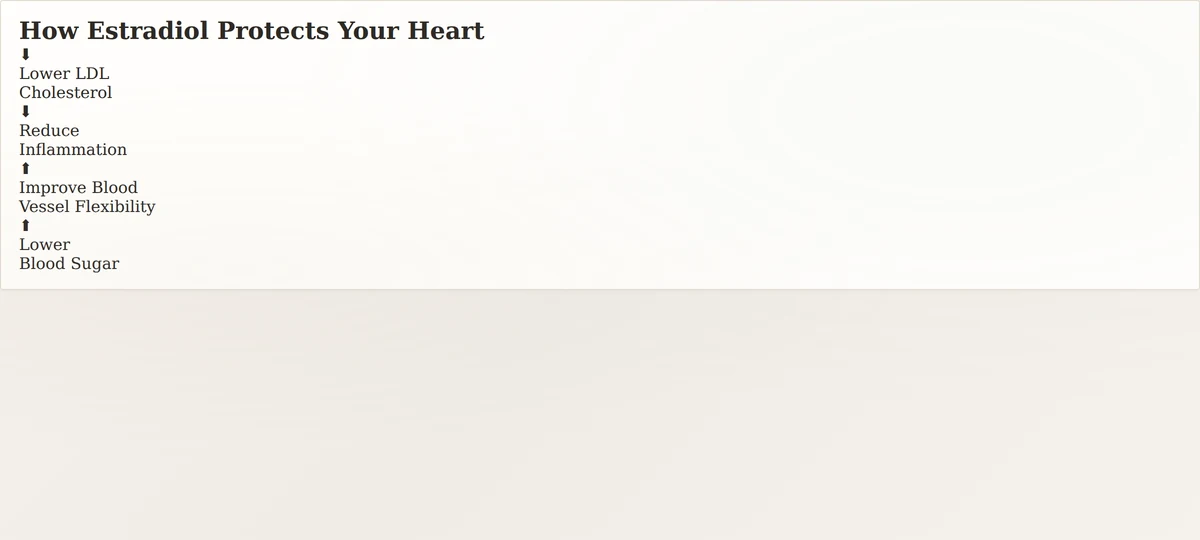
During your reproductive years, estradiol — the most potent form of estrogen your ovaries produce — acts as a multitarget cardiovascular protector. Research on estrogen’s vascular mechanisms shows it operates through at least four distinct pathways:
Research Spotlight: Estradiol’s Four Heart-Protective Pathways
- Lipid Regulation. Estradiol lowers low-density lipoprotein (LDL) cholesterol — the “bad” cholesterol that builds arterial plaque — and reduces atherogenic subparticles including apolipoprotein B (APOB) and lipoprotein(a) [Lp(a)]. Menopause-driven cholesterol changes are among the earliest measurable cardiovascular risk shifts, often detectable within 12 months of the final period.
- Anti-Inflammatory Action. Systemic inflammation accelerates atherosclerosis. Estradiol suppresses pro-inflammatory cytokines — signaling molecules that drive plaque formation and destabilization — and reduces C-reactive protein levels when initiated early in the menopausal transition.
- Nitric Oxide and Vascular Flexibility. Estrogen receptors in the endothelial lining of your arteries trigger nitric oxide production. Nitric oxide relaxes the smooth muscle inside blood vessel walls, keeping arteries flexible and responsive to changes in blood flow. Blood vessel stiffening accelerates after menopause, and early estradiol administration appears to slow this process.
- Metabolic and Blood Sugar Regulation. Estradiol improves insulin sensitivity and glucose metabolism. The metabolic changes that accompany menopause — including central weight gain, rising fasting glucose, and altered lipid partitioning — increase cardiovascular risk through pathways that estradiol partially offsets.
Here is the critical detail most discussions miss: these four pathways do not shut down at the same speed. LDL cholesterol rises first, often within months of the final period. Vascular stiffening takes years. Plaque accumulation takes decades. When you start MHT early, you intercept the process at multiple points before significant damage accumulates. When you wait 15 or 20 years, the vessels have already remodeled — and adding estrogen to scarred, stiffened arteries does not produce the same beneficial signaling.
Women face a significantly higher cardiovascular disease burden after menopause compared to their premenopausal years — a gap that narrows when you account for the timing of hormone decline rather than age alone. This mechanism-centered view explains why the timing hypothesis holds up biologically, not just statistically.
Menopause Hormone Therapy Cardiovascular Disease: Who Benefits Most?
The SWAN data points toward specific subgroups that appear to derive the largest cardiovascular benefit from early menopause hormone therapy cardiovascular disease protection. The pattern is consistent: women at higher baseline risk, and women who start earlier, show the strongest protective associations.
Who Is This For?
- Women in perimenopause or within 10 years of their final menstrual period
- Women experiencing moderate to severe vasomotor symptoms (hot flashes, night sweats) — especially if frequent
- Women with no personal history of heart attack, stroke, or venous thromboembolism
- Women with normal or mildly elevated baseline cardiovascular risk who want to preserve vascular health through the transition
Who Should Approach With Caution (or Avoid MHT for CVD Indication)?
- Women more than 10 years past menopause without prior MHT use — the protective window appears closed
- Women with a personal history of estrogen-sensitive breast cancer
- Women with a history of deep vein thrombosis, pulmonary embolism, or clotting disorders
- Women with active liver disease or uncontrolled hypertension
- Women over 60 initiating MHT for the first time solely for cardiovascular prevention — the risk-benefit ratio shifts unfavorably
The timeline is the single most important individual variable. A 52-year-old woman in perimenopause with bothersome hot flashes and no cardiovascular contraindications sits in the ideal window for potential heart protection from MHT. A 68-year-old woman who has been postmenopausal for 18 years, even with excellent baseline health, should not initiate MHT for cardiovascular prevention alone — the clinical trial data simply does not support it, and the risks (venous thromboembolism, stroke) may outweigh the theoretical benefit.
Ethnicity and baseline cardiovascular risk also matter. The 49% risk reduction observed in Black women in the SWAN analysis does not mean MHT works differently based on race — it likely reflects the higher baseline CVD burden in this population, creating a larger measurable effect when a protective intervention is applied at the right time. This pattern mirrors what researchers observe in other preventive interventions: those at highest absolute risk often show the largest relative benefit.
One more factor worth tracking: prior research on HRT timing and cardiovascular outcomes consistently shows that younger, healthier women near menopause derive benefit from estrogen, while older women with established vascular disease do not. SWAN 2026 is not an outlier — it is the largest and most statistically robust confirmation of a pattern researchers have been documenting for over a decade.
Types of Menopause Hormone Therapy for Cardiovascular Disease Protection

Not all menopause hormone therapy formulations are equal when it comes to menopause hormone therapy cardiovascular disease outcomes. Your choice of estrogen type, whether you need progestin, and how you take the medication all influence the cardiovascular risk-benefit calculation.
| MHT Type | Who It Is For | Cardiovascular Considerations |
|---|---|---|
| Estrogen-Only Therapy (ET) | Women who have had a hysterectomy (no uterus = no progestin needed for endometrial protection) | Most favorable cardiovascular profile in timing-hypothesis studies. WHI estrogen-only arm showed a trend toward reduced coronary heart disease in women aged 50–59. |
| Estrogen + Progestin (EPT) | Women with an intact uterus (progestin protects the endometrium from estrogen-driven hyperplasia and cancer) | Some progestins may partially offset estrogen’s vascular benefits. Micronized progesterone appears more neutral than synthetic progestins like medroxyprogesterone acetate. Transdermal routes may carry lower venous thromboembolism risk than oral. |
| Bioidentical Hormones | Women seeking molecularly identical estradiol and progesterone (as opposed to synthetic analogs) | 17-beta estradiol is chemically identical to what your ovaries produced. Micronized progesterone (oral) has a more favorable metabolic profile than older synthetic progestins. FDA-approved bioidentical products exist — “compounded” bioidenticals lack the same quality control. |
| Conjugated Equine Estrogens (CEE) | The formulation used in WHI; still prescribed but less common as first-line today | Derived from pregnant mare urine. Contains multiple estrogen types, not just estradiol. Most WHI data reflects CEE + MPA, so the cardiovascular risk signals from 2002 are tied to this specific combination in older women. |
The delivery route also matters for cardiovascular risk. Transdermal estradiol — delivered through a patch, gel, or spray applied to the skin — bypasses first-pass liver metabolism. Oral estrogen passes through the liver before entering systemic circulation, which increases clotting factor production and raises triglycerides. Transdermal routes avoid this hepatic effect, which is why current MHT guidelines often prefer transdermal estrogen for women with elevated baseline clotting risk or hypertriglyceridemia.
If you need combined estrogen-progestin therapy, micronized progesterone (brand name Prometrium or generic) carries a more favorable cardiovascular and metabolic profile than the synthetic progestin medroxyprogesterone acetate (Provera) used in the original WHI trial. This distinction matters because the WHI cardiovascular risk signal — the one that caused millions of women to stop HRT in 2002 — was observed specifically with the CEE + MPA combination in older women, not with estradiol plus micronized progesterone in women near menopause.
Several estradiol-based products exist internationally, including Progynova (estradiol valerate), which provides a predictable estradiol dose. Our Progynova HRT guide covers dosing, administration, and what to expect when starting oral estradiol therapy. If you are weighing bioidentical versus synthetic options, see our comparison of estriol vs estradiol — two estrogen types with different receptor affinities, potencies, and clinical roles.
What Does the Research Say?
The menopause hormone therapy cardiovascular disease relationship has generated a substantial evidence base over three decades — and the story has evolved considerably as methodology improved and timing-specific analysis became standard.
| Study / Year | Design | Key Finding on MHT & CVD |
|---|---|---|
| WHI (2002) | RCT, n=16,608, mean age 63 | Small increase in CHD events with CEE + MPA. Subsequent age-stratified reanalysis showed neutral-to-favorable trend in women aged 50–59. |
| WHI Estrogen-Only Arm (2004) | RCT, n=10,739, mean age 63.6 | No increase in CHD. Trend toward reduced coronary events in women aged 50–59. Established that progestin type and timing both matter. |
| KEEPS (2012) | RCT, n=727, women within 3 years of menopause | No cardiovascular harm with early MHT initiation. Slower progression of carotid intima-media thickness in the estradiol group — a proxy for reduced atherosclerosis. |
| ELITE (2016) | RCT, n=643, stratified by time since menopause (<6 yrs vs ≥10 yrs) | Less atherosclerosis progression (p = 0.008) in women starting within 6 years of menopause. No benefit in the ≥10-year group. Direct trial evidence for the timing hypothesis. |
| Danish Osteoporosis Prevention Study (2012, 16-year FU) | Open-label RCT, n=1,006, mean age 50 | Reduced composite endpoint of mortality, heart failure, or MI (HR 0.61) in women starting HRT near menopause. Open-label design limits certainty but direction matches timing hypothesis. |
| SWAN / El Khoudary et al. (2026) | Observational, n=2,700+, 20-year follow-up | 22–27% lower CVD risk with early MHT start; 49% in Black women. Largest and longest observational dataset confirming the timing window. |
The pattern across all six landmark studies is unmistakable: early MHT consistently trends toward cardiovascular benefit or neutrality, while late initiation — particularly with synthetic progestins in older women — trends toward harm. The American Heart Association acknowledges menopause as a sex-specific cardiovascular risk factor and recommends that women discuss individualized MHT risk-benefit with their clinicians, particularly in the context of bothersome vasomotor symptoms and the perimenopausal window.
None of these studies — including SWAN 2026 — proves that MHT prevents heart disease in a causal sense. What they show, with growing consistency, is that the relationship between menopause hormone therapy cardiovascular disease risk depends overwhelmingly on when you start, what formulation you use, and who you are in terms of baseline vascular health.
How to Talk to Your Doctor About Menopause Hormone Therapy and Cardiovascular Disease
You have read the research. You understand the timing hypothesis. You want to know whether menopause hormone therapy cardiovascular disease protection applies to your situation. The next step is a focused conversation with your clinician — and walking into that appointment with the right questions changes the quality of the discussion.
Five Points to Raise With Your Doctor
- Where am I in the menopause timeline? Ask your doctor to confirm whether you are in perimenopause, early postmenopause (within 10 years), or late postmenopause. If your last period was more than 5 years ago but you are not sure of the exact date, an FSH blood test can help establish where you are in the transition. Timing fundamentally changes the risk-benefit calculus for MHT.
- What is my personal cardiovascular risk profile? Request a lipid panel (LDL, HDL, triglycerides, and — if available — APOB and Lp(a)), blood pressure assessment, and fasting glucose or HbA1c. If you have a family history of early heart disease (parent or sibling with a cardiac event before age 55 in men or 65 in women), mention it explicitly — family history shifts baseline risk in ways that affect the MHT decision.
- Would transdermal estradiol work for my situation? Transdermal patches, gels, and sprays bypass liver metabolism and carry a lower venous thromboembolism risk than oral estrogen. If you have any clotting risk factors — migraine with aura, obesity, smoking history, or a family history of DVT — transdermal delivery may be the safer route. Ask your doctor whether this applies to you.
- Which progestin (if I need one) has the best cardiovascular profile? If you have a uterus, you need progestin to protect against endometrial cancer. Micronized progesterone carries a more favorable metabolic and cardiovascular profile than older synthetic progestins. Ask whether this distinction matters for your specific risk factors.
- Are my hot flashes and night sweats telling me something about my heart? Frequent or severe vasomotor symptoms correlate with higher future cardiovascular risk. Framing your symptoms as potential cardiovascular markers — not just discomfort — may shift the clinical conversation from “is HRT worth the risk for symptom relief?” to “could treating these symptoms also protect my long-term heart health?”
You do not need to arrive with a decision already made. The goal of this conversation is shared decision-making: you bring the questions and your personal preferences, your doctor brings the clinical risk assessment and prescribing expertise. Together, you determine whether menopause hormone therapy cardiovascular disease risk reduction is a relevant consideration in your treatment plan, or whether the risks outweigh the potential benefit in your individual case.
If your doctor dismisses the conversation — “HRT is too dangerous,” “we stopped using that years ago” — you have the right to seek a second opinion from a menopause specialist certified by the North American Menopause Society (NAMS). The evidence has moved forward considerably since 2002. Not every clinician has moved with it.
Frequently Asked Questions About Menopause Hormone Therapy Cardiovascular Disease
Does menopause hormone therapy prevent heart disease?
No clinical trial has demonstrated that menopause hormone therapy cardiovascular disease protection works as a guaranteed preventive. What the evidence shows — across WHI reanalysis, ELITE, KEEPS, the Danish study, and now SWAN 2026 — is an association between early MHT initiation and lower subsequent cardiovascular risk. Associations are not the same as causal proof. For women in the perimenopausal window with bothersome symptoms and no contraindications, the cardiovascular data are reassuring and lean toward benefit. For women starting MHT solely for heart disease prevention without other indications, current guidelines do not recommend it.
What is the “timing hypothesis” in menopause hormone therapy?
The timing hypothesis states that the cardiovascular effects of menopause hormone therapy cardiovascular disease depend on when you start relative to menopause. Early initiation — during perimenopause or within roughly 10 years of the final period — appears protective or neutral, because your blood vessels still have functional estrogen receptors and minimal accumulated damage. Late initiation — more than 10 years past menopause — may be harmful or at best neutral, because arteries have already stiffened and plaque has accumulated beyond what estrogen signaling can reverse.
How much does MHT reduce cardiovascular risk?
The SWAN 2026 analysis found a 22% lower risk when MHT started during perimenopause or early postmenopause, 27% when started within 10 years of the final period, and 49% among Black women who started early. These are relative risk reductions from observational data — not absolute risk differences. For a woman with a low baseline 10-year CVD risk (e.g., 5%), a 27% relative reduction translates to roughly a 1.35 percentage-point absolute reduction. For a woman at higher baseline risk (e.g., 15%), the same relative reduction represents a more clinically meaningful 4 percentage points.
Is estrogen-only HRT safer for the heart than combined HRT?
Estrogen-only therapy generally shows a more favorable cardiovascular signal than combined estrogen-progestin therapy in the available research. The WHI estrogen-only arm (women with hysterectomy) showed no increase in coronary events and a trend toward reduction in younger women. The progestin component — particularly medroxyprogesterone acetate — may partially offset estrogen’s vascular benefits. Micronized progesterone and transdermal delivery routes appear to have less metabolic impact than oral synthetic progestins.
Can I start MHT if I am 10+ years past menopause?
For menopause hormone therapy cardiovascular disease protection specifically, the evidence does not support initiating MHT more than a decade after menopause — the protective window appears closed, and the risk of venous thromboembolism and stroke increases with both age and time since menopause. That said, you and your doctor may still consider MHT for other indications (osteoporosis prevention, persistent vasomotor symptoms) after weighing the risks carefully. A cardiology consultation before initiating late MHT is prudent.
Does the type of estrogen matter for heart protection?
Yes. 17-beta estradiol — the molecularly identical form your ovaries produced — is the most studied and likely the most cardioprotective estrogen. Conjugated equine estrogens (CEE), used in the WHI, contain multiple estrogen types with different receptor-binding profiles. Research on estrogen receptor subtypes suggests that estradiol’s specific affinity for estrogen receptor alpha in vascular tissue is key to the nitric oxide-mediated vasodilation effect. Transdermal estradiol may offer additional cardiovascular safety advantages by avoiding first-pass liver metabolism.
Are hot flashes a sign of heart disease risk?
Hot flashes and night sweats are not heart disease, but frequent or severe vasomotor symptoms are associated with higher future cardiovascular event risk in multiple cohort studies. The mechanism is not fully understood, but may involve sympathetic nervous system overactivity, endothelial dysfunction, or shared underlying vascular pathology. If you experience frequent, disruptive hot flashes, discussing both symptom relief and cardiovascular risk assessment with your doctor is reasonable — these conversations are connected, not separate.
Does MHT cause blood clots?
Oral estrogen therapy increases the risk of venous thromboembolism (VTE) — deep vein thrombosis and pulmonary embolism — by approximately 2- to 3-fold compared to non-use. The absolute risk remains low: roughly 2–3 additional VTEs per 1,000 women per year of use. Transdermal estradiol appears to carry substantially lower or no elevated VTE risk compared to oral formulations, likely because it avoids the hepatic first-pass effect that increases clotting factor synthesis. If you have personal or family history of clotting disorders, transdermal delivery is strongly preferred if MHT is used at all.
The Bottom Line on Menopause Hormone Therapy Cardiovascular Disease
The menopause hormone therapy cardiovascular disease story is not the one most women heard in 2002. It is more nuanced, more optimistic, and — critically — more personal than the WHI headlines suggested two decades ago.
The evidence now stacks clearly in one direction: timing is the dominant variable. Start MHT within 10 years of your final period, while your blood vessels still have functional estrogen receptors and minimal accumulated damage, and the data suggest cardiovascular protection — 22% to 27% lower risk in the largest observational analysis to date. Wait 15 or 20 years, after arteries have stiffened and plaque has calcified, and estrogen may not help — and could even add risk through clotting or plaque destabilization.
For Black women, who face disproportionately high cardiovascular disease burden and more severe menopausal symptoms, the 49% risk reduction signal from SWAN — while observational and in need of prospective confirmation — represents one of the largest potential cardiovascular benefits associated with any menopausal intervention studied to date.
The practical implications are straightforward:
- If you are in perimenopause or early postmenopause, pay attention to your vasomotor symptoms — not just for comfort, but as potential cardiovascular risk markers.
- If you are considering MHT, have the five-point conversation with your doctor outlined above. Come prepared with questions about timing, formulation, delivery route, and your personal risk profile.
- If you started MHT years ago and are now past the 10-year window, do not panic — but do have a reassessment conversation with your clinician about whether continuing still makes sense for your current risk profile.
- MHT is not a cardiovascular medication. It is a hormone therapy with cardiovascular implications that depend heavily on individual factors. Diet, exercise, blood pressure control, lipid management, and smoking cessation remain the foundation of heart disease prevention — for every woman, at every age.
Your action step: If you are within 10 years of menopause and experiencing hot flashes or night sweats, book a 20-minute appointment with your primary care provider or gynecologist. Bring this article. Ask the five questions. You do not need a decision — you need an informed conversation. The window of opportunity for cardiovascular protection may be time-limited, but the window for a good clinical discussion is always open.
What to Read Next
- Estriol vs Estradiol: A Complete Comparison — Understand the pharmacology behind the two estrogen types most commonly prescribed for menopause
- Browse Woman’s Health Resources — Evidence-based guides on HRT options, symptom management, and menopause wellness
Medical Disclaimer
The information in this article is for educational purposes only and does not constitute medical advice. Menopause hormone therapy carries real risks including venous thromboembolism, stroke, and — with some formulations — breast cancer. The decision to start, continue, or stop MHT must be made in consultation with a qualified healthcare provider who knows your personal and family medical history. Never start or stop prescription hormone therapy without medical supervision. If you experience chest pain, shortness of breath, severe headache, vision changes, or leg swelling while taking MHT, seek emergency medical attention immediately.
Reviewed by [Medical Professional Title] • Last updated: September 17, 2026

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.