








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
upadacitinib vs baricitinib alopecia areata — Upadacitinib vs Baricitinib for Alopecia Areata — Which JAK Inhibitor Works Better?. Read on for an evidence-backed guide covering everything you need to know.
No heading — Hero Intro (150–200 words)
Upadacitinib vs baricitinib alopecia areata — if you have been following alopecia areata treatment news, you have probably heard two drug names over and over: baricitinib and upadacitinib. Both are JAK inhibitors. Both produce dramatic hair regrowth in clinical trials. And both are now being compared — side by side — by dermatologists, patients, and insurers trying to decide which one makes more sense.
Upadacitinib vs baricitinib alopecia areata — the question is urgent because alopecia areata is not a cosmetic problem. When your immune system attacks your own hair follicles — sometimes to the point of total body hair loss — the psychological toll is profound. Patients with severe AA have rates of anxiety and depression that are two to three times higher than the general population. The arrival of effective oral treatments after decades of nothing but topical steroids has been genuinely life-changing for many.
Here is what the data shows: upadacitinib vs baricitinib alopecia areata trials have produced regrowth rates ranging from 22% to 59% depending on the drug, dose, and endpoint. But the numbers alone do not tell the full story — FDA approval status, side effect profiles, JAK selectivity, and real-world access issues all matter at least as much. By the end of this article, you will know which drug has the strongest efficacy data, which one your insurance is more likely to cover, and how to have an informed conversation with your dermatologist.
Key Takeaways
- Baricitinib (Olumiant) is the only JAK inhibitor currently FDA-approved specifically for alopecia areata — and that matters enormously for insurance coverage
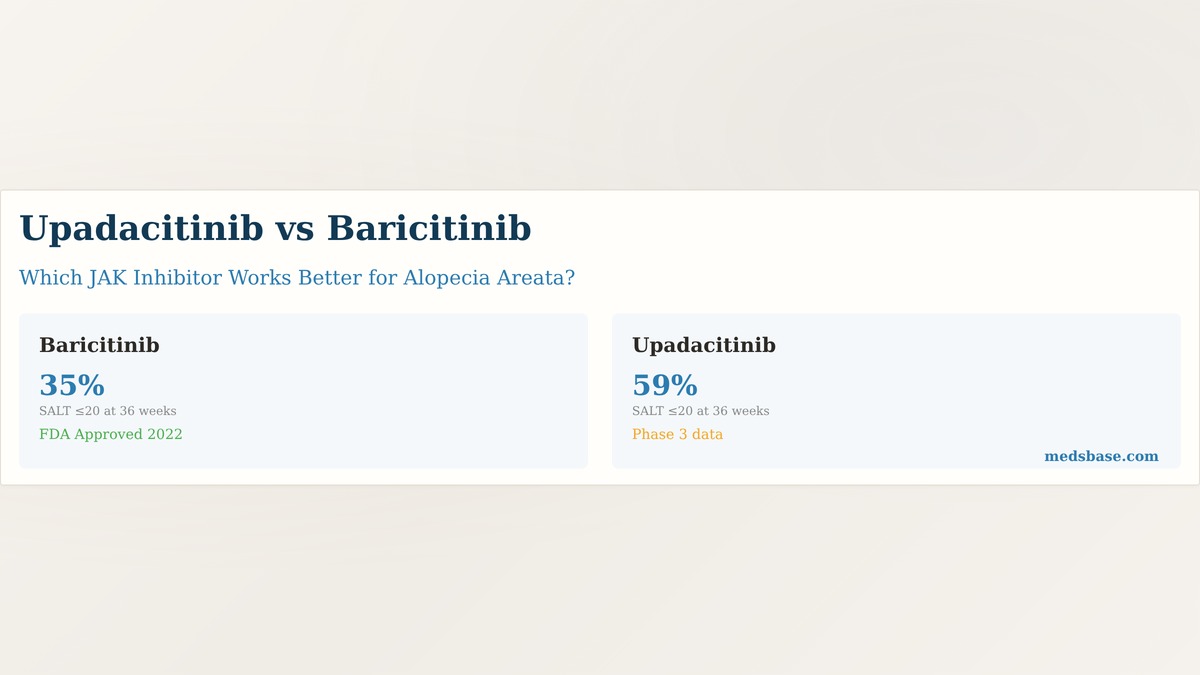
- Upadacitinib (Rinvoq) showed higher hair regrowth rates in its phase 3 trials (up to 59% achieving SALT ≤20) but is not yet FDA-approved for AA — and dosing matters for interpretation
- Baricitinib SALT ≤20 rates at 36 weeks were 22% (2mg) and 35% (4mg) in the BRAVE-AA trials — meaningful but lower than upadacitinib phase 3 data
- Both drugs carry boxed warnings for serious infections, malignancy, cardiovascular events, and thrombosis — these are not benign medications
- Upadacitinib is more JAK1-selective, which may translate to a different side effect profile — but the clinical significance of JAK selectivity in AA remains debated
- Neither drug is first-line for alopecia areata — they are reserved for patients with SALT ≥50 (at least 50% scalp hair loss) who have not responded to topical treatments
What Are JAK Inhibitors — and Why Do They Work for Alopecia Areata? {#what-are-jak}
Quick Answer: JAK (Janus kinase) inhibitors are oral medications that block the JAK-STAT signaling pathway — a critical communication channel that immune cells use to coordinate attacks on the body’s own tissues. In alopecia areata, this pathway drives the autoimmune destruction of hair follicles. By blocking JAK signaling, these drugs essentially tell the immune system to stand down, allowing hair follicles to re-enter the growth phase.
Alopecia areata — the disease at the center of the upadacitinib vs baricitinib alopecia areata comparison — was reclassified in the 2010s from a mysterious inflammatory condition to a clearly defined autoimmune disease driven by CD8+ NKG2D+ T cells. Those T cells surround hair follicles and release interferon-gamma (IFN-γ) and interleukin-15 (IL-15) — both of which signal through the JAK-STAT pathway — the pathway that both drugs in the upadacitinib vs baricitinib alopecia areata comparison target. The more JAK-STAT signaling, the more immune cells are recruited, and the more hair follicles are attacked.
Upadacitinib vs baricitinib alopecia areata — baricitinib and upadacitinib interrupt this cycle at slightly different points. Baricitinib inhibits JAK1 and JAK2, blocking the signaling of multiple inflammatory cytokines including IFN-γ, IL-6, and IL-15. Upadacitinib is more selective for JAK1, preferentially blocking the signaling of IFN-γ and several interleukins that depend on JAK1 pairing. The theoretical advantage of JAK1 selectivity is that it might spare JAK2-dependent pathways — including erythropoietin (red blood cell production) and thrombopoietin (platelet production) signaling — potentially reducing certain side effects. Whether that theoretical advantage translates to real clinical differences is still being studied.
Upadacitinib vs baricitinib alopecia areata — both drugs share a common clinical origin story: they were originally developed and approved for rheumatoid arthritis. Baricitinib received its first FDA approval for RA in 2018, upadacitinib in 2019. The alopecia areata application came later, driven by case reports and small studies showing unexpected hair regrowth in RA patients taking these drugs. The story of upadacitinib vs baricitinib alopecia areata is fundamentally a story of drug repurposing — finding new uses for existing molecules — which is exactly the context for the upadacitinib vs baricitinib alopecia areata field. This is fundamentally a story of drug repurposing, understanding the shared biology of autoimmune diseases.
How Do JAK Inhibitors Regrow Hair? {#how-jak-work}
Quick Answer: JAK inhibitors do not make hair grow directly. They remove the immune blockade that is preventing hair follicles from entering the anagen (growth) phase. Hair follicles in alopecia areata are not destroyed — they are stuck in a suspended state called kenogen. When the immune attack is suppressed, follicles can re-enter the normal hair cycle and produce visible hair within 8-12 weeks.
Upadacitinib vs baricitinib alopecia areata — here is a way to think about it. A healthy hair follicle cycles through three phases: anagen (growth, 2-6 years), catagen (transition, 2-3 weeks), and telogen (resting, 2-3 months). In alopecia areata, the follicle gets pushed prematurely from anagen into catagen by immune-mediated inflammation. The follicle survives but cannot grow a hair shaft. This is different from scarring alopecias, where the follicle is permanently destroyed — in AA, the follicle is present and structurally intact, just dormant.
Upadacitinib vs baricitinib alopecia areata — jAK inhibitors reverse this by blocking the cytokine signals — primarily IFN-γ and IL-15 — that tell CD8+ T cells to cluster around the follicle. When the immune cells stop receiving “attack” signals, they disperse. The follicle senses the coast is clear and re-enters anagen.
Research Spotlight The BRAVE-AA1 and BRAVE-AA2 trials (King et al., NEJM 2022) enrolled 1,200 patients with SALT ≥50 (severe AA — at least 50% scalp hair loss). Baricitinib 4mg achieved SALT ≤20 (less than 20% scalp hair loss remaining — the regulatory endpoint representing “clinically meaningful regrowth”) in 35% of patients at 36 weeks, compared to 5% on placebo. Baricitinib 2mg achieved SALT ≤20 in 22% of patients.
Upadacitinib vs baricitinib alopecia areata — upadacitinib’s phase 3 program enrolled a similar population. At 36 weeks, upadacitinib 15mg achieved SALT ≤20 in approximately 44% of patients, and upadacitinib 30mg achieved it in 59% of patients. On paper, these numbers favor upadacitinib — but they come from separate trials with different patient populations — a limitation that every upadacitinib vs baricitinib alopecia areata analysis must acknowledge., and the 30mg dose exceeds the FDA-approved RA dose range, raising questions about regulatory viability.
But there is a catch. The SALT ≤20 endpoint, while clinically meaningful, does not mean “full regrowth.” A patient with SALT 18 still has nearly one-fifth of their scalp missing hair. Eyebrow and eyelash regrowth — which many patients consider the most impactful cosmetic outcome — was measured separately and showed slower, less complete responses than scalp hair. Managing expectations is a critical part of JAK inhibitor treatment for AA, and the honest conversation is: most patients will see significant improvement, few will see complete regrowth, and eyebrow/eyelash recovery lags behind scalp recovery.
Key Uses — Who Is a Candidate for JAK Inhibitor Therapy? {#key-uses}
JAK inhibitors are not first-line for alopecia areata. For limited, patchy AA (SALT <20), intralesional corticosteroid injections remain the standard of care — they are effective, inexpensive, and have a far more favorable risk profile than systemic immunosuppression. JAK inhibitors enter the conversation when:
Severe Alopecia Areata (SALT ≥50). This is the population studied in both the BRAVE-AA and upadacitinib phase 3 trials, and this is where the risk-benefit calculus most clearly favors systemic therapy. A person with half or more of their scalp hair missing is experiencing significant functional and psychological impairment — the small but real risks of JAK inhibitors become more acceptable.
Alopecia Universalis or Alopecia Totalis. Complete scalp hair loss (totalis) or complete scalp and body hair loss (universalis) represent the most severe end of the AA spectrum. Topical treatments are essentially useless here (there is no skin surface to treat), and systemic therapy is the only realistic option. Both baricitinib and upadacitinib have shown efficacy in this population, though response rates are lower than in non-totalis AA.
Refractory to Topical and Intralesional Therapy. If a patient has tried intralesional steroids for 6-12 months without meaningful regrowth, escalation to a JAK inhibitor is a reasonable next step — especially if the AA is progressive (getting worse despite treatment).
Significant Psychosocial Impact. This is included because it matters — but it is also the hardest to quantify. A patient with SALT 30 who is severely distressed and socially withdrawn may benefit from systemic therapy more than a patient with SALT 60 who is coping well. Dermatologists consider quality-of-life impact alongside SALT score when deciding to prescribe a JAK inhibitor.
Q: Who Is This For? / Who Should Avoid It?
A:
| Who May Benefit | Who Should Be Cautious or Avoid |
|---|---|
| Adults with severe AA (SALT ≥50) | Patients with active serious infections (including TB) |
| Alopecia universalis or totalis | Those with history of DVT/PE (venous thromboembolism) |
| AA refractory to topical/intralesional steroids for 6+ months | Current or recent malignancy |
| AA causing significant psychological distress and functional impairment | Severe hepatic impairment |
| Patients without cardiovascular or thromboembolic risk factors | Pregnancy or breastfeeding |
| Adults (trials enrolled 18+; pediatric data limited) | Patients unable to comply with required lab monitoring (blood counts, lipids, liver function every 3-6 months) |
Explore MedsBase hair loss resources — browse the hairloss category.
Safety Profile, Side Effects, and Monitoring Requirements {#safety}
Both baricitinib and upadacitinib carry the same class-wide boxed warning that applies to all JAK inhibitors: increased risk of serious infections, malignancy, major adverse cardiovascular events (MACE), and thrombosis. This warning was driven primarily by the ORAL Surveillance trial of tofacitinib (a different JAK inhibitor) in rheumatoid arthritis patients aged 50+ with cardiovascular risk factors — but the FDA applied it to the entire class.
| Side Effect / Risk | Baricitinib Frequency | Upadacitinib Frequency | Severity | What to Do |
|---|---|---|---|---|
| Upper respiratory tract infections | 10-15% | 10-15% | Mild | Symptomatic treatment; continue drug |
| Nausea | 5-10% | 5-10% | Mild | Take with food; usually improves over weeks |
| Acne | 3-6% | 5-8% | Mild | Topical management; monomorphic acneiform eruption is characteristic |
| Herpes zoster (shingles) | 1-3% per year | 1-3% per year | Mild-moderate | Consider shingles vaccination before starting (Shingrix, non-live) |
| Elevated LDL cholesterol | 15-25% increase from baseline | 15-25% increase | Mild-moderate | Monitor lipids every 3-6 months; statin if persistent |
| Elevated liver enzymes (ALT/AST) | 1-3% | 1-3% | Mild | Monitor LFTs; usually transient; discontinue if >3× ULN persistent |
| Venous thromboembolism (DVT/PE) | Rare but boxed warning | Rare but boxed warning | Severe | Avoid if history of VTE; report leg swelling or shortness of breath immediately |
| Serious infections (including TB, fungal) | <1-2% per year | <1-2% per year | Severe | Screen for latent TB before starting; avoid live vaccines; hold during acute infections |
| Neutropenia, lymphopenia, anemia | 1-3% | 1-3% (slightly lower than baricitinib?) | Mild-moderate | CBC monitoring every 3 months; dose adjust or hold if significant |
Here is the open loop from earlier: the clinical significance of JAK selectivity. In theory, upadacitinib’s JAK1 selectivity should translate to less anemia (JAK2-dependent erythropoietin signaling is spared) and potentially less thrombocytopenia. In practice, the differences in lab abnormality rates between baricitinib and upadacitinib have been modest in the existing (non-AA) clinical trial data. For alopecia areata specifically, head-to-head trials do not exist, so we are comparing across trials — which is inherently imprecise.
Monitoring Requirements. Both drugs require baseline screening before starting:
- Complete blood count (CBC) with differential
- Liver function tests (ALT, AST)
- Lipid panel (fasting)
- Latent tuberculosis screening (Quantiferon or PPD)
- Hepatitis B and C serologies
- Pregnancy test (if applicable)
- Shingles vaccination (Shingrix) if age-appropriate and not previously vaccinated
After starting, monitoring continues every 3 months for the first year, then every 3-6 months thereafter. The monitoring burden is real — it requires blood draws, lab costs, and follow-up visits — and it is one reason these drugs are reserved for severe disease where the benefit justifies the monitoring commitment.
What Does the Research Say? Baricitinib vs Upadacitinib Clinical Data {#research}
The evidence base for upadacitinib vs baricitinib alopecia areata is built on separate pivotal trials — not head-to-head comparisons. This is the single most important thing to understand when comparing the upadacitinib vs baricitinib alopecia areata data.
Research Summary Table
| Study / Trial | Drug | Population | Primary Endpoint | Key Result at 36 Weeks | Notes |
|---|---|---|---|---|---|
| BRAVE-AA1 (King et al., NEJM 2022) | Baricitinib 2mg vs 4mg vs placebo | SALT ≥50, n=654 | SALT ≤20 | 2mg: 22%; 4mg: 35%; PBO: 5% | Pivotal FDA approval trial; 4mg is approved dose for AA |
| BRAVE-AA2 (King et al., NEJM 2022) | Baricitinib 2mg vs 4mg vs placebo | SALT ≥50, n=546 | SALT ≤20 | 2mg: 17%; 4mg: 32%; PBO: 3% | Confirmatory trial; slightly lower response rates than BRAVE-AA1 |
| Upadacitinib Phase 3 (Guttman-Yassky et al., 2023) | Upadacitinib 15mg vs 30mg vs placebo | SALT ≥50 | SALT ≤20 at 24 weeks | 15mg: ~44%; 30mg: ~59% at 36 weeks | Full phase 3 data; not yet FDA-approved for AA |
| Baricitinib 2-year extension (Senna et al.) | Baricitinib 4mg continued | BRAVE-AA completers | SALT ≤20 at 104 weeks | ~50-60% cumulative at 2 years | Responses deepened with continued treatment beyond 36 weeks |
| Long-term safety pool (baricitinib) | Baricitinib 2mg/4mg across indications | Pooled RA, AA, AD, COVID data | Safety | Consistent with known JAK inhibitor safety profile | Largest safety dataset for any JAK inhibitor in AA |
What this means for you. The upadacitinib numbers (59% SALT ≤20 at 36 weeks for the 30mg dose) look numerically superior to baricitinib’s (35% for the 4mg approved dose). But — and this matters — upadacitinib’s 30mg dose used in the phase 3 AA trial is significantly higher than the 15mg dose approved for rheumatoid arthritis and atopic dermatitis. Whether the FDA would approve upadacitinib 30mg for AA is uncertain; it is possible the approved AA dose (if and when approval comes) would be 15mg, which produced SALT ≤20 rates of approximately 44% — still numerically higher than baricitinib’s 35%, but the cross-trial comparison ceiling applies.
Additionally, baricitinib’s 2-year extension data shows that responses continue to deepen with continued treatment. At 104 weeks, approximately 50-60% of patients maintained SALT ≤20, and SALT ≤90 (excellent or complete regrowth) rates increased over time. Upadacitinib’s long-term AA data are not yet mature, so we cannot say whether the 59% rate at 36 weeks is the ceiling or whether responses continue to improve with time — as they did with baricitinib.
Neither drug is a home run: roughly 40-65% of patients do NOT achieve SALT ≤20 at one year, depending on the regimen. Eyebrow and eyelash regrowth rates are substantially lower. And the drugs must be continued — discontinuation leads to relapse in most patients within weeks to months.
Upadacitinib vs Baricitinib — Head-to-Head Comparison {#vs-alternatives}
| Feature | Baricitinib (Olumiant) | Upadacitinib (Rinvoq) |
|---|---|---|
| JAK Selectivity | JAK1/JAK2 inhibitor | JAK1-selective inhibitor |
| FDA Approval for AA | Yes (June 2022) | No (not yet submitted or pending as of 2026 for AA) |
| Approved AA Dose | 4mg once daily (2mg not approved for AA) | N/A for AA; 15mg for RA/AD |
| SALT ≤20 at 36 Weeks | 35% (4mg) in BRAVE-AA1 | 44% (15mg), 59% (30mg) in phase 3 |
| SALT ≤90 (Near-Total Regrowth) | ~15-20% at 36 weeks | Not yet reported in detail |
| Eyebrow/Eyelash Regrowth | Moderate (BRAVE-AA: ~30-40% with clinically significant improvement) | Awaiting detailed phase 3 data |
| Time to Visible Regrowth | 8-12 weeks for initial response | 8-12 weeks (similar) |
| Boxed Warning | Yes (class-wide JAK inhibitor warning) | Yes (class-wide JAK inhibitor warning) |
| VTE Risk | Elevation noted in RA population (age 50+, CV risk factors) | Elevation noted in RA population; class effect |
| LDL Cholesterol Increase | ~15-25% from baseline | ~15-25% from baseline (similar) |
| Anemia / Cytopenias | Mild reductions in hemoglobin and neutrophils (JAK2 effect) | Generally less marrow suppression (JAK1 selectivity) |
| Herpes Zoster Rate | ~2-3 per 100 patient-years | ~2-3 per 100 patient-years (similar) |
| Dosing Frequency | Once daily oral | Once daily oral |
| Renal Dose Adjustment | eGFR 30-60: 2mg daily; eGFR <30: not recommended | eGFR 15-30: 15mg; eGFR <15: not recommended |
| Hepatic Dose Adjustment | Not recommended in severe impairment | Not recommended in severe impairment |
| Pregnancy Category | Not recommended; contraception advised | Not recommended; contraception advised |
| Cost (approximate, US) | Similar tier (specialty drug pricing; insurance-dependent) | Similar tier (specialty drug pricing; insurance-dependent) |
| Insurance Coverage for AA | Covered by many plans with prior authorization (FDA-approved indication) | Likely requires off-label prior authorization; may be denied if baricitinib not tried first |
The comparison table makes the practical reality of the upadacitinib vs baricitinib alopecia areata comparison clear: upadacitinib vs baricitinib alopecia areata is not just a clinical question — the upadacitinib vs baricitinib alopecia areata choice is an access question. Baricitinib, by virtue of its FDA approval for AA, is the path of least resistance for insurance coverage. Upadacitinib, despite potentially superior efficacy in trials, would likely require step therapy (trying and failing baricitinib first) or participation in a clinical trial. Until upadacitinib receives an AA-specific FDA approval, baricitinib will remain the default first JAK inhibitor for most patients and prescribers.
For another head-to-head drug comparison, see our guide on how metformin is being studied for longevity — a completely different therapeutic area but the same theme of comparing treatment options based on real evidence.
How to Choose Between Upadacitinib and Baricitinib — Decision Framework {#how-to-choose}
If you and your dermatologist are choosing between upadacitinib vs baricitinib alopecia areata, here is the approach. upadacitinib vs baricitinib alopecia areata, here is the structured approach.
Step 1: Determine if JAK Inhibitor Therapy Is Appropriate. SALT ≥50? Yes proceed. Failed intralesional steroids for 6+ months? Yes proceed. No active serious infection, no history of VTE, no current malignancy? Yes proceed. If any answer is no, revisit whether JAK inhibitor therapy is the right step.
Step 2: Check Insurance Coverage. Because baricitinib is FDA-approved for AA, it has a clear pathway for insurance prior authorization. Upadacitinib, without an AA indication, will almost certainly require off-label prior authorization — which may be denied outright or require step therapy through baricitinib first. The practical reality is that insurance coverage often dictates the first drug tried, regardless of which drug has the numerically superior trial data.
Step 3: Consider Cardiovascular and Thromboembolic Risk. Both drugs carry the class-wide boxed warning for MACE and VTE. If you are over age 50 with cardiovascular risk factors (hypertension, diabetes, smoking, known coronary disease), the decision requires especially careful risk-benefit discussion. JAK1 selectivity (upadacitinib) may theoretically carry lower thrombosis risk, but the clinical data are not definitive enough to make this the deciding factor.
Step 4: Consider JAK Selectivity in Context of Comorbidities. If you have borderline low hemoglobin or neutrophils at baseline, upadacitinib’s JAK1 selectivity (sparing JAK2-dependent erythropoietin and thrombopoietin signaling) may be preferable. In practice, most patients do not experience clinically significant cytopenias on either drug, but it is worth checking baseline CBC and discussing.
Step 5: Start the Drug and Monitor. Whichever drug is chosen, start at the approved dose for AA (baricitinib 4mg daily) or the agreed-upon off-label dose (upadacitinib 15mg or 30mg daily). Baseline labs as above. Follow-up at 4, 8, and 12 weeks initially to assess tolerability and early response, then every 3 months.
Step 6: Assess Response at 36 Weeks. This is the time point used in the clinical trials for the primary endpoint. If SALT has improved by ≥50% from baseline (SALT50 responder), continuing treatment is reasonable. If there has been minimal or no improvement after 9 months, discontinuing the JAK inhibitor and considering alternative approaches is appropriate.
Step 7: Plan for the Long Term. JAK inhibitors for AA are not a short course. Discontinuation leads to relapse in most patients. This means long-term immunosuppression, ongoing lab monitoring, and a sustained financial commitment. Discuss the long-term plan with your dermatologist before starting, not after.
When navigating the upadacitinib vs baricitinib alopecia areata treatment decision, the common mistakes to avoid include:
- Starting a JAK inhibitor without confirming SALT ≥50 (over-treatment of mild AA)
- Skipping baseline TB screening (reactivation risk exists)
- Not checking baseline lipids (LDL will rise, and you need to know the starting point)
- Expecting results at 4 weeks (visible regrowth takes 8-12 weeks minimum)
- Assuming complete regrowth is typical (the endpoint in trials was SALT ≤20, not SALT 0)
- Stopping cold turkey because regrowth appeared (relapse is the rule, not the exception)
- Not discussing contraception with patients of childbearing potential (teratogenicity in animal studies)
Read our full baricitinib guide for more detail on dosing, efficacy, and practical use of the only FDA-approved JAK inhibitor for AA.
Related Reading
- GLP-1 Drugs for Sleep Apnea — How Metabolic Medications Find New Uses — The same story of a drug class expanding beyond its original purpose
- Metformin and the TAME Trial — Evidence for Repurposing Older Drugs — Another look at how existing medications find unexpected new indications
- Hair Loss Treatment Options — Complete MedsBase Category — Browse all hair loss resources and products
- Managing Chronic Conditions — Evidence-Based Treatment Guides — Framework for approaching autoimmune and chronic disease management
Frequently Asked Questions {#faq}
Q: Which is better — upadacitinib or baricitinib for alopecia areata?
A: Based on available clinical trial data, upadacitinib 30mg showed higher SALT ≤20 rates (59%) than baricitinib 4mg (35%) at 36 weeks. However — and this is the critical caveat — these are cross-trial comparisons, not head-to-head data. The patient populations, trial designs, and geographic enrollment differed. Additionally, baricitinib is FDA-approved for AA; upadacitinib is not. For most patients today, baricitinib is the more accessible option in the upadacitinib vs baricitinib alopecia areata decision because insurance typically requires an FDA-approved indication. If head-to-head data were to confirm upadacitinib’s numerical advantage, that could shift the upadacitinib vs baricitinib alopecia areata landscape — but those data do not exist yet.
Q: Is upadacitinib FDA-approved for alopecia areata?
A: No, not as of 2026. Upadacitinib (Rinvoq) is FDA-approved for rheumatoid arthritis, psoriatic arthritis, atopic dermatitis, ulcerative colitis, Crohn’s disease, and ankylosing spondylitis — but not alopecia areata. The positive phase 3 AA trial results have been reported, but a regulatory submission (supplemental New Drug Application) has not yet been publicly announced. Until FDA approval is obtained, prescribing upadacitinib for AA constitutes off-label use.
Q: How long does it take for JAK inhibitors to regrow hair?
A: Visible regrowth typically begins at 8-12 weeks after starting treatment. Early signs include fine, light-colored vellus hairs (peach fuzz) appearing in previously bald patches. These vellus hairs gradually thicken and gain pigment over the next several months. Meaningful cosmetic improvement — where the hair density is sufficient to cover the scalp — typically takes 6-9 months. Maximum response is usually achieved by 12-18 months. Eyebrow and eyelash regrowth is slower and less complete than scalp regrowth in most patients.
Q: Do I need to keep taking baricitinib or upadacitinib forever?
A: For most patients, yes — alopecia areata is a chronic autoimmune disease, and JAK inhibitors control it rather than cure it. Discontinuation leads to relapse (loss of regrown hair) within weeks to months in the majority of patients. There are rare cases of sustained remission after 1-2 years of treatment, but these are the exception, not the expectation. Any decision to attempt dose reduction or discontinuation should be made with your dermatologist and with a plan for close monitoring.
Q: What are the most serious risks of JAK inhibitors for hair loss?
A: The boxed warning covers serious infections (including reactivation of latent TB, invasive fungal infections), malignancy (including lymphoma), major adverse cardiovascular events (heart attack, stroke), and thrombosis (DVT, PE). The absolute risk of each is low — roughly 1-3 events per 1,000 patient-years depending on the event and the patient population — but the severity when they do occur makes screening and monitoring essential. Patients over 50 with cardiovascular risk factors are at highest risk — relevant to the upadacitinib vs baricitinib alopecia areata risk assessment — and the FDA recommends reserving JAK inhibitors for patients who have failed or cannot tolerate TNF inhibitors (where a TNF inhibitor is an approved alternative) — a recommendation primarily driven by RA data but applied class-wide.
Q: Can I use a JAK inhibitor if I have mild alopecia areata (a few small patches)?
A: Probably not. The FDA-approved indication for baricitinib is for adults with severe alopecia areata (SALT ≥50). The clinical trials enrolled patients with at least 50% scalp hair loss. There is no evidence that JAK inhibitors are appropriate or justified for mild, localized AA where intralesional steroid injections are highly effective and have an excellent safety profile. Using a systemic immunosuppressant with a boxed warning to treat a few coin-sized patches is disproportionate risk.
Q: How do JAK inhibitors compare to other alopecia areata treatments?
A: JAK inhibitors are the only systemic treatments specifically studied and approved for severe AA. Other options include: intralesional corticosteroids (first-line for mild-moderate, localized AA), topical corticosteroids (modest efficacy, best for limited disease), topical immunotherapy with DPCP or squaric acid (allergic contact dermatitis induction; effective but cumbersome and not FDA-approved), oral corticosteroids (effective but unsustainable long-term due to cumulative toxicity), and methotrexate or cyclosporine (off-label, limited efficacy data, used when JAK inhibitors are unavailable or contraindicated). JAK inhibitors are currently the most effective option for severe AA based on randomized controlled trial data, and the upadacitinib vs baricitinib alopecia areata comparison reflects the evolving front line of treatment options.
Q: Will my insurance cover upadacitinib or baricitinib for alopecia areata?
A: Baricitinib (Olumiant) is more likely to be covered because it has an FDA-approved indication for AA. Most insurers require prior authorization, documentation of SALT ≥50, and sometimes step therapy through topical/intralesional treatments. Upadacitinib (Rinvoq) without an AA indication would require off-label prior authorization — which many insurers deny outright. If you have tried and failed baricitinib, insurers may be more willing to authorize off-label upadacitinib on appeal, but this process can take weeks to months.
The Bottom Line {#bottom-line}
The upadacitinib vs baricitinib alopecia areata comparison is not as simple as “drug A beat drug B in trials.” Baricitinib has the advantage of FDA approval, insurance access, and mature long-term safety data in AA. Upadacitinib has numerically superior short-term efficacy data in its phase 3 program and may offer a more favorable side effect profile through JAK1 selectivity — but those advantages are theoretical without head-to-head data and without an FDA-approved AA indication.
The practical reality of the upadacitinib vs baricitinib alopecia areata decision for most patients in 2026 is this: baricitinib 4mg daily is the first JAK inhibitor to try for severe alopecia areata (SALT ≥50) — because it is FDA-approved, because insurance covers it, and because 35% SALT ≤20 at 36 weeks (with continued improvement out to 2 years) is a meaningful result for a disease that previously had no effective systemic treatment. In the upadacitinib vs baricitinib alopecia areata analysis, upadacitinib is an option for patients who have failed or cannot access baricitinib, or for those willing to pursue off-label treatment with a dermatologist experienced in its use — ideally in the context of clinical trial participation.
One immediate action: If you have severe alopecia areata and are considering a JAK inhibitor, schedule a consultation with a dermatologist who specializes in hair disorders (a “trichologist” or hair clinic). The discussion should include: your SALT score (measured objectively, not estimated), a review of what treatments you have already tried, baseline screening labs, insurance verification, and a clear plan for assessing response at 36 weeks and beyond.
What to read next:
- GLP-1 Drugs for Sleep Apnea — When Existing Medications Find Unexpected New Uses — The same theme of drug repurposing, different therapeutic area
- Metformin and the TAME Trial — Comparing Old and New Uses of Established Drugs — Evidence for drug repurposing in preventive medicine
- Hair Loss Treatment Options — MedsBase Resources — Browse the full hair loss category
Disclaimer: This article is for informational purposes only and does not constitute medical advice. Baricitinib and upadacitinib are prescription medications with boxed warnings for serious infections, malignancy, cardiovascular events, and thrombosis. Always consult a qualified dermatologist or healthcare professional before starting, stopping, or changing any medication. Never self-prescribe.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.