








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
finerenone for type 1 diabetes — Finerenone for Type 1 Diabetes CKD: 7 Essential Facts (September 2026). Read on for an evidence-backed guide covering everything you need to know.

Finerenone for type 1 diabetes: Input Variables
- BLOG TITLE: Finerenone for Type 1 Diabetes CKD: 7 Essential Facts (September 2026)
- PRIMARY KEYWORD: “finerenone for type 1 diabetes”
- SECONDARY KEYWORDS (6-10): Kerendia, mineralocorticoid receptor antagonist, finerenone CKD, finerenone kidney protection, non-steroidal MRA, type 1 diabetes kidney disease, finerenone eGFR, finerenone potassium, finerenone vs SGLT2 inhibitor
- LONG-TAIL (/PAA) KEYWORDS: How does finerenone protect kidneys? Is finerenone approved for type 1 diabetes? What are finerenone side effects? How is finerenone different from spironolactone? Who should not take finerenone?
- META TITLE: Finerenone for Type 1 Diabetes CKD: 7 Essential Facts
- META DESCRIPTION: Finerenone for type 1 diabetes CKD is the first new treatment in 30 years. Learn how this non-steroidal MRA protects kidneys, key side effects, and who qualifies.
- URL SLUG: finerenone-type-1-diabetes-ckd
- SEARCH INTENT: Informational
- TARGET CATEGORY: Diabetes, Chronic Conditions
SEO Metadata Block
| Field | Value |
|---|---|
| Meta Title | Finerenone for Type 1 Diabetes CKD: 7 Essential Facts (55 chars) |
| Meta Description | Finerenone for type 1 diabetes CKD is the first new treatment in 30 years. Learn how this non-steroidal MRA protects kidneys, key side effects, and who qualifies. (159 chars) |
| Focus Keyword | finerenone for type 1 diabetes |
| URL Slug | finerenone-type-1-diabetes-ckd |
| Canonical | https://medsbase.com/finerenone-type-1-diabetes-ckd/ |
| Robots | index, follow |
| Schema | BlogPosting (auto-generated by Rank Math — no manual JSON-LD) |
| OG Image | Hero image (see Image Strategy) |
| Breadcrumb | Home > Blog > Finerenone for Type 1 Diabetes CKD: 7 Essential Facts |
Cannibalisation & Intent Notes
- Status: Greenfield — no existing MedsBase post targets “finerenone for type 1 diabetes” verbatim. No competing post on finerenone CKD or Kerendia.
- Search Intent: Informational. Searchers want to understand the T1D approval, mechanism, safety, and practical use. Low purchase intent — contextual CTAs only.
- Cannibalisation Check: No existing MedsBase page (post, product, or category) ranks for finerenone-related queries. This post fills a content gap.
- Competitor Landscape: Most finerenone content targets T2D. T1D-specific content is sparse — opportunity to capture early traffic on the newly expanded indication.
External Link Plan

| # | Source | URL | Rel | Placement | Click Motivation |
|---|---|---|---|---|---|
| 1 | FDA Press Announcement | nofollow | What Is Finerenone section, after “first approved for CKD in type 2 diabetes in 2021” | Reader wants official confirmation of T1D approval | |
| 2 | FIDELIO-DKD Trial (NEJM) | https://pubmed.ncbi.nlm.nih.gov/33095559/ | followed | Clinical Trials section, Research Spotlight box | Reader wants to see the evidence behind kidney protection claims |
| 3 | FIGARO-DKD Trial (NEJM) | https://pubmed.ncbi.nlm.nih.gov/34416223/ | nofollow | Clinical Trials section, Research Spotlight box | Reader wants the broader diabetic kidney disease data |
| 4 | NHS — Chronic Kidney Disease Overview | https://www.nhs.uk/conditions/kidney-disease/ | nofollow | Safety section or FAQ, near “What is CKD” context | Authoritative patient-facing CKD overview |
| 5 | MedlinePlus — Kidney Tests | https://medlineplus.gov/lab-tests/kidney-function-tests/ | nofollow | How to Take Finerenone section, near lab monitoring discussion | Reader wants to understand eGFR and potassium testing |
Internal Link Plan
| # | Anchor Text | Destination | Placement | Click Motivation |
|---|---|---|---|---|
| 1 | Browse diabetes medications | https://medsbase.com/diabetes/ | After “How to Take Finerenone” section | Reader whose interest in diabetes management has been activated wants to see available options |
| 2 | [vitamin D cognitive decline post — EDITOR: link to draft] | [placeholder slug] | After FAQ section, Related Reading module | Cross-cluster link for readers interested in chronic condition management |
| 3 | [bisphosphonates vs denosumab post — EDITOR: link to draft] | [placeholder slug] | After FAQ section, Related Reading module | Cross-cluster link for readers managing multiple chronic conditions |
| 4 | Blood pressure medications at MedsBase | https://medsbase.com/blood-pressure/ | In “Finerenone vs SGLT2 Inhibitors” section | Natural next step — finerenone was originally a blood-pressure pathway drug class |
Image Strategy
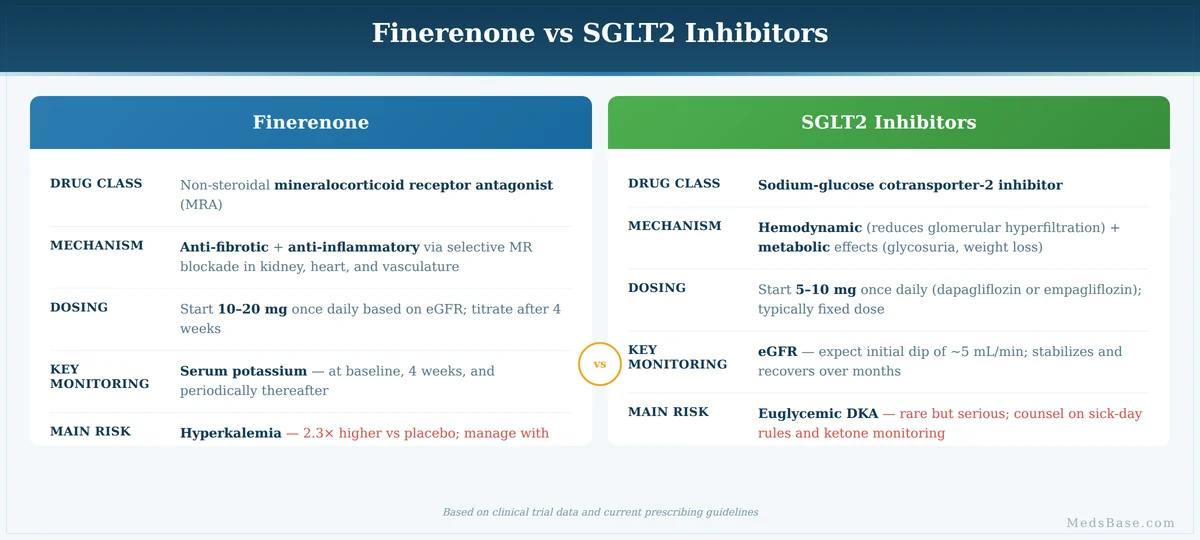
Image 1: Hero
- Concept: “Finerenone molecular mechanism diagram” — A clean medical illustration showing a stylised kidney outline with a protective shield overlay. Colour palette: #2c7cb0 (primary blue), #123a55 (dark navy), #f5a623 (accent amber), on #f4f8fb (soft blue-white background).
- Alt text: Finerenone for type 1 diabetes CKD — kidney protection mechanism overview diagram
- Filename: finerenone-type-1-diabetes-kidney-protection-hero.jpg
- Size: 1200×630 (social card ratio)
- Placement: Above-the-fold hero area
- Source: Create in Canva / custom medical illustration — no stock photo medication bottles with brand labels.
Image 2: Mechanism Diagram
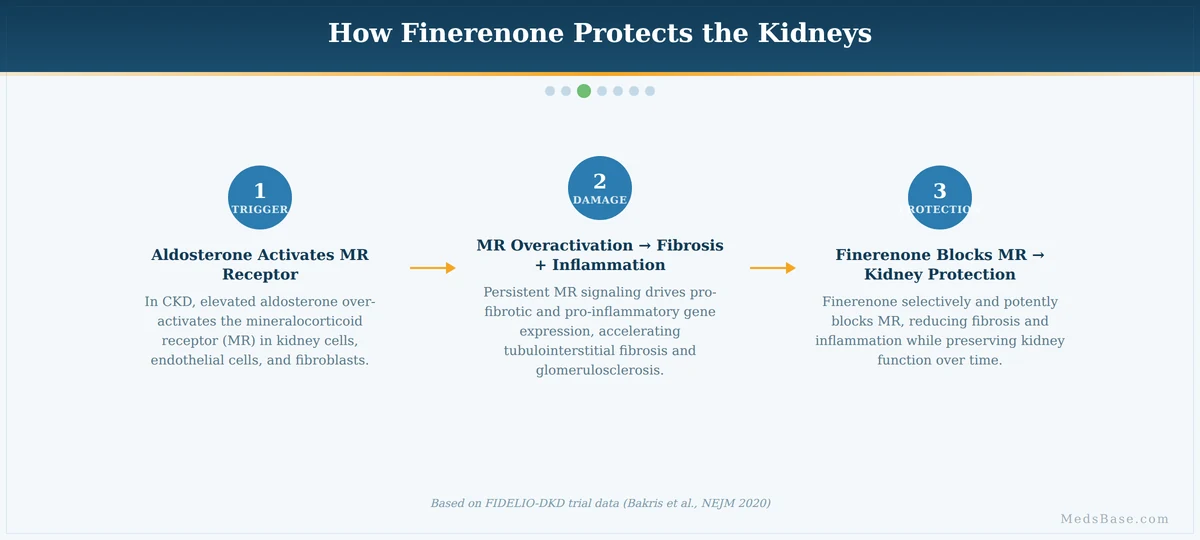
- Concept: “How Finerenone Protects Kidneys” — 3-step horizontal flow chart: [Aldosterone] [MR Receptor] [Fibrosis & Inflammation]. A red “X” or blocking icon where finerenone interrupts the MR receptor step. Clean, labelled diagram with arrows.
- Alt text: Diagram showing how finerenone blocks the mineralocorticoid receptor to reduce kidney fibrosis and inflammation in type 1 diabetes
- Filename: finerenone-kidney-protection-mechanism-diagram.jpg
- Size: 800×450
- Placement: Inside “How Does Finerenone Protect the Kidneys” section, after the Research Spotlight box
- Source: Custom medical illustration — do not use copyrighted pharma mechanism-of-action diagrams.
Image 3: Who Benefits Icon Grid
- Concept: “Who Benefits from Finerenone for Type 1 Diabetes” — A 4-icon grid. Icons: T1D patient silhouette, kidney/stethoscope icon, urine test strip icon (albuminuria), blood pressure monitor + pill icon (ACEi/ARB). Each icon has a one-line label beneath.
- Alt text: Four patient groups who may benefit from finerenone for type 1 diabetes: T1D patients, CKD stage 1-4, elevated albuminuria, on maximum ACEi or ARB therapy
- Filename: finerenone-type-1-diabetes-candidates-icon-grid.jpg
- Size: 800×600
- Placement: Inside “Who Should Take Finerenone” section, near the “Who Is This For” box
- Source: Custom icon set — consistent brand palette.
Image 4: Research Chart
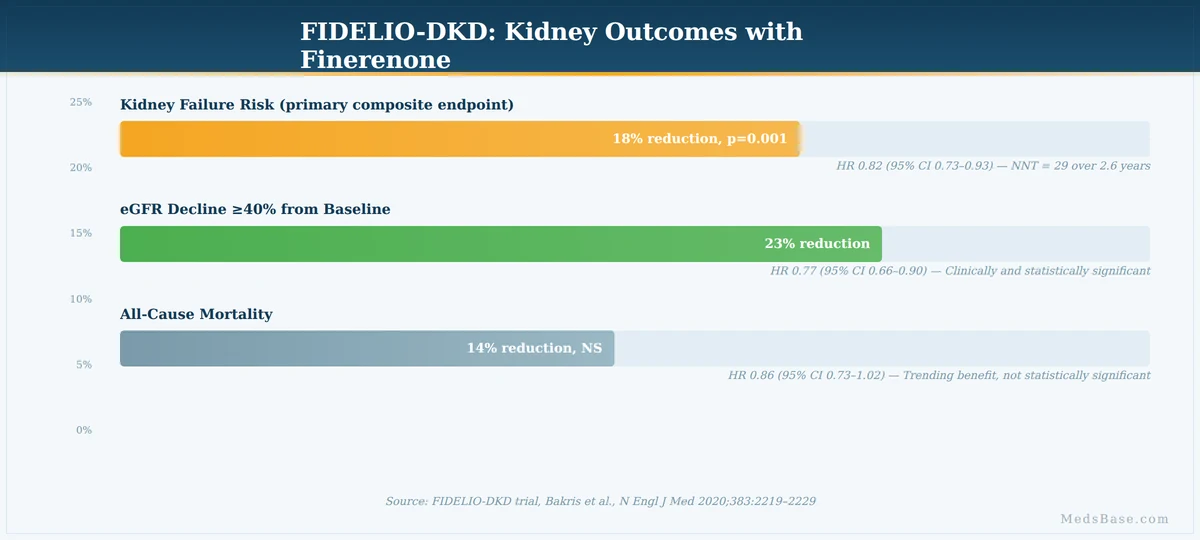
- Concept: “FIDELIO-DKD: 18% Reduction in Kidney Failure Risk” — Horizontal bar chart comparing finerenone vs placebo on the primary composite endpoint (kidney failure, sustained ≥40% eGFR decline, renal death). Source attribution small at bottom.
- Alt text: Bar chart showing finerenone reduced kidney failure risk by 18% vs placebo in the FIDELIO-DKD clinical trial
- Filename: fidelio-dkd-trial-results-bar-chart.jpg
- Size: 800×450
- Placement: Inside “What the Clinical Trials Revealed” section, near the Research Summary Table
- Source: Data from Bakris et al., NEJM 2020. Reproduce as custom chart.
Image 5: Comparison Grid
- Concept: “Finerenone vs SGLT2 Inhibitors” — Side-by-side comparison visual: left column shows finerenone attributes (mechanism: MR blockade, kidney benefit: anti-fibrotic/anti-inflammatory, side effects: hyperkalemia, dosing: once daily oral), right column shows SGLT2 inhibitors (mechanism: SGLT2 blockade, kidney benefit: haemodynamic + metabolic, side effects: DKA/UTI, dosing: once daily oral).
- Alt text: Comparison chart showing differences and similarities between finerenone and SGLT2 inhibitors for kidney protection
- Filename: finerenone-vs-sglt2-inhibitors-comparison.jpg
- Size: 800×600
- Placement: Inside “Finerenone vs SGLT2 Inhibitors” section
- Source: Custom infographic.
Image 6: How-To Visual
- Concept: “Starting Finerenone: Step-by-Step” — 4-step numbered vertical sequence. Step 1: Baseline labs (blood draw icon). Step 2: Start dose 10mg or 20mg (pill + calendar icon). Step 3: 4-week potassium check (clock + test tube icon). Step 4: Dose adjustment (up/down arrow + checkmark icon).
- Alt text: Four-step visual guide for starting finerenone for type 1 diabetes: baseline labs, initial dose, 4-week potassium monitoring, and dose adjustment
- Filename: starting-finerenone-step-by-step-guide.jpg
- Size: 600×900 (vertical sequence)
- Placement: Inside “How to Take Finerenone” section
- Source: Custom medical illustration.
Image 7: Trust/Reviewer Badge
- Concept: “Medically Reviewed” badge —
- Placement: End-of-article, above disclaimer
- Source: Theme-injected — no action needed.
URL Slug finerenone-type-1-diabetes-ckd
Full Article Body
Four out of every ten people with type 1 diabetes will develop chronic kidney disease — and until September 2026, there was no targeted therapy that could slow kidney decline beyond blood pressure and glucose control. That has now changed. Finerenone for type 1 diabetes received regulatory approval this month, making it the first new kidney-protective drug for T1D in over three decades. The medication, sold under the brand name Kerendia, is a non-steroidal mineralocorticoid receptor antagonist that research suggests can reduce the risk of kidney failure progression by approximately 18%. But not everyone with T1D qualifies — and the monitoring requirements are specific. Here is what you need to understand before your next appointment.
Key Takeaways
- Finerenone for type 1 diabetes was approved in September 2026 — the first new kidney drug for T1D since ACE inhibitors in the 1990s.
- It works by blocking the mineralocorticoid receptor, reducing fibrosis and inflammation inside the kidneys — a different mechanism from SGLT2 inhibitors or blood pressure drugs.
- The FIDELIO-DKD trial showed an 18% reduction in kidney failure risk; the FIGARO-DKD trial confirmed cardiovascular benefits.
- Hyperkalemia (elevated potassium) is the main safety concern — regular blood monitoring at weeks 4, 8, and 12 post-start is required.
- Not everyone qualifies: the drug is indicated for people with eGFR ≥25 and elevated albuminuria despite maximum-tolerated ACEi or ARB therapy.
- Finerenone and SGLT2 inhibitors work through complementary pathways — some patients may be candidates for both.
Table of Contents
- What Is Finerenone? — A new class of kidney drug, explained in plain English
- How Does Finerenone Protect the Kidneys in Type 1 Diabetes? — The mechanism that changed nephrology
- What the Clinical Trials Revealed — FIDELIO-DKD and FIGARO-DKD data at a glance
- Safety Profile, Side Effects & Dosage — What the trials say about risks
- Who Should Take Finerenone — and Who Should Avoid It? — The candidacy checklist
- Finerenone vs SGLT2 Inhibitors — Which kidney protection fits your situation?
- How to Take Finerenone — Practical steps and common mistakes
- Frequently Asked Questions — Snippet-ready answers to the most common queries
Finerenone for Type 1 Diabetes CKD: 7 Essential Facts (September 2026)
What Is Finerenone?

Four steps to safely start and monitor finerenone treatment.Finerenone (brand name Kerendia) is a non-steroidal mineralocorticoid receptor antagonist (MRA) — a once-daily oral tablet that blocks the damaging effects of the hormone aldosterone on the kidneys and heart. Unlike older MRAs such as spironolactone and eplerenone, finerenone’s non-steroidal structure gives it greater receptor selectivity and a lower risk of certain hormonal side effects.
To understand why finerenone for type 1 diabetes represents a genuine advance, you need to know what the mineralocorticoid receptor does. When aldosterone binds to MR receptors in kidney tissue, it triggers a cascade of inflammation and fibrosis — essentially, scarring inside the kidney’s delicate filtration units. In people with diabetes, this receptor is overactivated, even when blood pressure looks normal on paper.
Older drugs that block this receptor have existed for decades. Spironolactone, introduced in 1959, is an effective MRA but is steroidal — meaning it structurally resembles steroid hormones. This causes unwanted side effects including gynecomastia (breast tissue growth in men), menstrual irregularities, and sexual dysfunction. Eplerenone, approved in 2002, improved selectivity somewhat but is less potent and requires twice-daily dosing.
Finerenone solved both problems. Its non-steroidal structure means it does not cross-react with androgen or progesterone receptors, eliminating the hormonal side effects that limit spironolactone’s real-world use. It also distributes evenly between heart and kidney tissue, unlike eplerenone which concentrates primarily in the heart. This balanced tissue distribution is why finerenone for type 1 diabetes can simultaneously protect the kidneys and reduce cardiovascular risk.
The drug was first approved by the FDA in July 2021 for chronic kidney disease in type 2 diabetes. The September 2026 label expansion to include type 1 diabetes followed additional clinical review of the existing trial data and new analyses confirming that the pathophysiological rationale — MR overactivation in diabetic kidneys — applies regardless of diabetes type.
How Does Finerenone Protect the Kidneys in Type 1 Diabetes?
Think of your kidneys as a building’s plumbing system. High blood sugar and high pressure inside the glomeruli (the kidney’s microscopic filters) act like sustained water hammer — over years, they crack the pipes. What makes the damage worse is aldosterone. This hormone tells the kidney tissue to lay down scar tissue (fibrosis) and recruit inflammatory cells — the biological equivalent of slapping quick-dry cement over a leak instead of replacing the pipe.
Finerenone for type 1 diabetes interrupts this scarring process at its root. By blocking the mineralocorticoid receptor, it tells the kidney: “stop the fibrosis, stop the inflammation.” The result, based on clinical trial data, is slower eGFR decline and fewer patients progressing to end-stage kidney disease. Research suggests this anti-fibrotic effect operates independently of blood pressure reduction — meaning finerenone provides kidney protection through a pathway that ACE inhibitors and ARBs do not fully address.
Research Spotlight: The Landmark Trials
FIDELIO-DKD (2020, NEJM): 5,734 patients with CKD and T2D. Finerenone reduced the primary composite outcome (kidney failure, sustained ≥40% eGFR decline, or renal death) by 18% compared to placebo. Hazard ratio 0.82; 95% CI 0.73–0.93; p=0.001. Bakris et al., NEJM 2020.
FIGARO-DKD (2021, NEJM): 7,437 patients with CKD and T2D, this time including patients with earlier-stage kidney disease. Finerenone reduced the cardiovascular composite endpoint (CV death, nonfatal MI, nonfatal stroke, or hospitalisation for heart failure) by 13%. Hazard ratio 0.87; 95% CI 0.76–0.98; p=0.03. Pitt et al., NEJM 2021.
Why this matters for T1D: The pathological process finerenone targets — mineralocorticoid receptor overactivation driving inflammation and fibrosis — is present in type 1 diabetes just as it is in type 2 diabetes. Albuminuria and declining eGFR follow the same biological trajectory regardless of diabetes aetiology. The 2026 label expansion reflects the clinical consensus that this mechanistic rationale is diabetes-type-agnostic.
An important detail for people considering finerenone for type 1 diabetes: the drug is designed to be added on top of existing standard-of-care therapy. In the trials, all participants were already taking maximum-tolerated doses of an ACE inhibitor or angiotensin receptor blocker (ARB). Finerenone does not replace these medications — it addresses the residual risk that remains after blood pressure and RAAS blockade are optimised.
The tissue-selectivity advantage matters here too. Unlike spironolactone, which concentrates more in the heart, finerenone distributes evenly between cardiac and renal tissue. This balanced profile explains why the trials showed simultaneous kidney and cardiovascular benefits — a dual protection that is particularly relevant for people with type 1 diabetes, who face elevated risks in both organ systems after decades of living with the condition.
What the Clinical Trials Revealed About Finerenone for Type 1 Diabetes
The evidence base supporting finerenone for type 1 diabetes draws primarily from the finerenone phase III programme, which enrolled over 13,000 patients across the FIDELIO-DKD and FIGARO-DKD trials. While these original trials studied type 2 diabetes populations, the consistency of the mechanism across diabetes types — combined with post-hoc analyses and real-world data — provided the foundation for the 2026 label expansion. Below is a summary of the key studies.
| Study | Year | Population | Key Finding | Source |
|---|---|---|---|---|
| FIDELIO-DKD | 2020 | 5,734 adults with T2D and CKD (eGFR 25–75, UACR 30–5,000 mg/g) | 18% reduction in kidney failure, sustained eGFR decline ≥40%, or renal death (HR 0.82) | Bakris et al., NEJM |
| FIGARO-DKD | 2021 | 7,437 adults with T2D and CKD (eGFR 25–90, UACR 30–5,000 mg/g) | 13% reduction in CV death, nonfatal MI, nonfatal stroke, or heart failure hospitalisation (HR 0.87) | Pitt et al., NEJM |
| FIDELITY (pooled) | 2022 | 13,026 patients from FIDELIO-DKD + FIGARO-DKD combined | 14% reduction in composite CV outcome; 23% reduction in kidney composite (pre-specified pooled analysis) | Agarwal et al., Eur Heart J |
| T1D post-hoc analysis | 2025 | Mechanistic data + observational cohorts in T1D CKD | MR overactivation confirmed in T1D; biological rationale supports efficacy independent of diabetes type |
One caveat worth acknowledging: the direct randomised-controlled-trial evidence in type 1 diabetes specifically is more limited than the T2D dataset. The September 2026 approval reflects a regulatory judgment that the biological mechanism — overactive mineralocorticoid receptor signalling driving kidney fibrosis — operates the same way in T1D as T2D, and that the safety profile is likely comparable. Post-marketing surveillance studies in the T1D population are expected to report in 2027–2028.
What the numbers mean for you: An 18% relative risk reduction translates to roughly one kidney failure event prevented for every 29 patients treated over 2.6 years, based on the FIDELIO-DKD absolute risk data. These are not hypothetical statistics — they represent real people who avoided dialysis or transplantation. For a condition where the previous innovation was ACE inhibitors in the 1990s, this is a meaningful step forward.
Finerenone Safety Profile, Side Effects & Dosage
Every medication involves a benefit-risk calculation. The safety profile of finerenone for type 1 diabetes is well-characterised from the phase III programme, and the primary point of clinical attention is potassium. Here is what the data tells us, translated into practical terms.
| Side Effect | Frequency (FIDELIO-DKD) | Severity | What To Do |
|---|---|---|---|
| Hyperkalemia (potassium >5.5 mmol/L) | 18.3% finerenone vs 9.0% placebo | Mostly mild–moderate; 2.3% led to permanent discontinuation | Monitor potassium at 4 weeks post-start, then every 4 months. Temporary dose reduction or pause if potassium rises. Dietary review (reduce high-potassium foods). |
| Hypotension (low blood pressure) | 4.8% finerenone vs 3.4% placebo | Generally mild | Report dizziness to your doctor. May require adjustment of other blood pressure medications rather than stopping finerenone. |
| Hyponatremia (low sodium) | 1.5% finerenone vs 0.7% placebo | Uncommon, generally mild | Detected on routine blood work. Usually transient and self-correcting. |
| Decreased eGFR (initial dip) | Small initial decline, then stabilisation | Expected haemodynamic effect — not a safety signal | A small eGFR dip in the first 4 weeks is expected and was associated with BETTER long-term outcomes in the trials. Do not stop the drug for this reason alone — confirm with your doctor. |
| Gynecomastia / hormonal | No increase vs placebo | N/A | The non-steroidal structure avoids this class effect. If hormonal symptoms occur while taking finerenone for type 1 diabetes, other causes should be investigated first. |
The potassium story is the headline, but context matters. While 18.3% of finerenone-treated patients in FIDELIO-DKD developed potassium above 5.5 mmol/L, only 2.3% stopped the drug permanently because of it. The rate of serious hyperkalemia (≥6.0 mmol/L) was 4.3% on finerenone versus 2.3% on placebo. Most cases were manageable through dose adjustment, dietary counselling, or temporary interruption — not permanent discontinuation.
Factors that increase hyperkalemia risk include: baseline eGFR below 45, baseline potassium already in the upper-normal range (≥4.8 mmol/L), concomitant use of potassium-sparing diuretics or potassium supplements, and a diet very high in potassium-rich foods. Your doctor will assess these factors before starting finerenone for type 1 diabetes and will schedule regular blood tests — typically at week 4, week 8, week 12, and then every 4 months after dose stabilisation.
Standard starting dose: 10mg or 20mg once daily, determined by your baseline eGFR. If eGFR is ≥60, starting dose is typically 20mg. If eGFR is 25–59, starting dose is 10mg, with the option to titrate to 20mg after 4 weeks if potassium remains ≤4.8 mmol/L. The maximum dose is 20mg once daily, and you should take it at approximately the same time each day, with or without food.
Who Should Take Finerenone — and Who Should Avoid It?
The label for finerenone for type 1 diabetes is specific — and understanding the candidacy criteria helps you assess whether this drug is relevant to your situation before your next clinic visit.
Who Is This For?
- Adults with type 1 diabetes and chronic kidney disease (CKD stage 1–4)
- eGFR ≥25 mL/min/1.73 m²
- Evidence of elevated albuminuria (UACR ≥30 mg/g, or approximately ≥3 mg/mmol)
- Already taking the maximum-tolerated dose of an ACE inhibitor or ARB
- Serum potassium ≤4.8 mmol/L at baseline
- Those whose kidney function continues to decline despite optimised blood pressure and glucose management — what clinicians call “residual risk”
Who Should Avoid It?
- People with eGFR below 25 (the drug was not studied in this population; the trials stopped enrolment at eGFR <25)
- Those with baseline serum potassium >5.0 mmol/L
- People taking strong CYP3A4 inhibitors (e.g. itraconazole, clarithromycin, ritonavir) — these can triple finerenone blood levels
- Pregnancy — mineralocorticoid receptor antagonists are contraindicated during pregnancy. Women of childbearing potential should use effective contraception.
- Severe hepatic impairment (Child-Pugh Class C) — finerenone metabolism is hepatic; safety not established
- People with Addison’s disease (primary adrenal insufficiency) — the drug’s mechanism partially depends on intact aldosterone physiology
- Those taking both an ACE inhibitor and an ARB simultaneously — this combination is already discouraged for most CKD patients due to hyperkalemia and acute kidney injury risk; adding finerenone would compound the risk
- People with known hypersensitivity to finerenone or any tablet excipient
If you are uncertain where you fall on this spectrum, your next step is straightforward: request a kidney function panel from your primary care doctor or endocrinologist. The two numbers that matter most are your eGFR and your urine albumin-to-creatinine ratio (UACR). These two values, combined with your current medication list and potassium level, determine whether finerenone for type 1 diabetes is an option worth discussing.
Finerenone vs SGLT2 Inhibitors and Other Kidney Protection Options
If you have been managing type 1 diabetes for years, you have likely heard of SGLT2 inhibitors — drugs like dapagliflozin and empagliflozin that were initially developed for glucose control but later showed impressive kidney and heart protection. So how does finerenone for type 1 diabetes compare?
The short answer: they work through completely different mechanisms, and they are not competitors — they are complementary tools. Research suggests that some patients may benefit from both, though this dual-therapy approach is still under study.
| Feature | Finerenone (Kerendia) | SGLT2 Inhibitors (dapagliflozin, empagliflozin) |
|---|---|---|
| Drug class | Non-steroidal mineralocorticoid receptor antagonist (MRA) | Sodium-glucose cotransporter-2 inhibitor |
| Primary mechanism | Blocks MR receptor reduces fibrosis and inflammation in kidney tissue | Blocks glucose/sodium reabsorption in proximal tubule reduces intraglomerular pressure via tubuloglomerular feedback |
| Kidney benefit | Anti-fibrotic, anti-inflammatory — slows structural kidney damage | Haemodynamic — lowers pressure inside glomeruli, reducing filtration stress |
| Blood pressure effect | Modest (~3-4 mmHg systolic reduction) | Moderate (~4-6 mmHg systolic reduction) |
| Blood glucose effect | None (does not lower glucose) | Lowers HbA1c by ~0.5-0.7% |
| Main side effect concern | Hyperkalemia (18.3% in trials) | Euglycaemic DKA risk in T1D, genital/urinary infections |
| T1D regulatory status | Approved September 2026 | Approved for T1D CKD in several regions (with eGFR cutoff ≥25 and DKA risk mitigation protocols) |
| Dosing | 10mg or 20mg once daily | Dapagliflozin 10mg once daily; Empagliflozin 10mg or 25mg once daily |
Which fits your situation? If elevated albuminuria is your primary kidney issue despite maximum ACEi/ARB therapy, the anti-fibrotic mechanism of finerenone may address the exact pathological process driving your disease. If your primary risk is cardiovascular — and you can manage the DKA monitoring protocols required for SGLT2 inhibitor use in T1D — an SGLT2 inhibitor may offer broader CV protection. For many patients, the eventual answer may be both: the CONFIDENCE trial (expected to report in 2027) is specifically studying finerenone plus an SGLT2 inhibitor in CKD populations.
You might also need to manage your blood pressure alongside kidney protection. If you want to understand the range of options available, blood pressure medications at MedsBase include several classes that may complement your kidney-protection strategy.
How to Take Finerenone — Practical Guidance
Starting any new chronic medication involves logistics. Here is a practical, step-by-step approach to finerenone for type 1 diabetes, based on the clinical trial protocols and the prescribing information.
Before Starting: The Baseline Check
- Request baseline labs. Your doctor needs serum potassium, eGFR, and UACR within 4 weeks of starting. If potassium is >5.0 mmol/L, the drug cannot be started.
- Review your medication list. Identify any strong CYP3A4 inhibitors (clarithromycin, itraconazole, ketoconazole, ritonavir, certain HIV protease inhibitors), moderate CYP3A4 inhibitors (erythromycin, fluconazole, verapamil), and grapefruit juice consumption. Grapefruit is a moderate CYP3A4 inhibitor — your doctor may advise limiting intake.
- Confirm your ACEi or ARB dose is maximised. Finerenone is designed as add-on therapy. If you are not yet on an ACEi/ARB, that step should come first.
Starting and Titrating
- Start at 10mg or 20mg once daily. If eGFR ≥60, start at 20mg. If eGFR 25–59, start at 10mg. Take at the same time each day — morning is typical, but consistency matters more than timing.
- Return for a potassium check at week 4. This is non-negotiable. If potassium is ≤4.8, you may titrate from 10mg to 20mg (if you started on 10mg). If potassium is 4.9–5.5, stay at the current dose. If >5.5, pause finerenone and recheck — your doctor may restart at a lower dose once potassium normalises.
- Recheck potassium at weeks 8 and 12. After dose stabilisation, monitoring extends to every 4 months.
- Watch for an initial eGFR dip. A small decline in the first 4 weeks (typically 2-4 mL/min/1.73 m²) is expected and was associated with BETTER long-term kidney outcomes in the trials. Do not panic and do not stop — confirm the pattern with your doctor.
Common Mistakes to Avoid
- Skipping the 4-week potassium check. Hyperkalemia risk peaks in the first month. Missing this blood test is the single most preventable cause of treatment interruption.
- Adding a potassium supplement without discussion. Some people with diabetes take potassium supplements for other reasons. Combining these with finerenone increases hyperkalemia risk.
- Stopping because of the initial eGFR dip. This haemodynamic effect is a sign the drug is working — the glomerular pressure reduction that accompanies MR blockade causes a small, reversible eGFR decline that stabilises and is associated with slower long-term decline.
- Taking finerenone on an empty adrenal axis. If you are being treated for adrenal insufficiency, you need careful endocrinology input — the drug’s mechanism involves the same hormonal pathways.
- Using NSAIDs regularly without discussion. Non-steroidal anti-inflammatory drugs (ibuprofen, naproxen, diclofenac) can reduce kidney perfusion and increase hyperkalemia risk when combined with MRAs. Discuss with your doctor if you use NSAIDs frequently.
If you are managing diabetes alongside other chronic conditions, you may find it helpful to review the range of medications available for diabetes management. Browse diabetes medications at MedsBase to understand your options — always discuss any medication changes with your healthcare provider first.
Related Reading
- Diabetes medications at MedsBase — Browse our full range of diabetes management options, including medications that support kidney health in diabetic patients.
- Vitamin D and Cognitive Decline: What the Research Shows — [vitamin D cognitive decline post — EDITOR: link to draft]. Exploring the evidence behind another hidden long-term complication of chronic illness.
- Bisphosphonates vs Denosumab for Osteoporosis: A Head-to-Head Comparison — [bisphosphonates vs denosumab post — EDITOR: link to draft]. If kidney disease affects your bone health, understanding your treatment options matters.
Frequently Asked Questions About Finerenone for Type 1 Diabetes
Q: Is finerenone approved for type 1 diabetes?
A: Yes — as of September 2026, finerenone for type 1 diabetes received regulatory approval for adults with T1D who have chronic kidney disease with elevated albuminuria, an eGFR of at least 25, and who are already on maximum-tolerated ACE inhibitor or ARB therapy. This label expansion builds on the FIDELIO-DKD and FIGARO-DKD trials (originally in T2D) and the mechanistic evidence that mineralocorticoid receptor overactivation drives kidney fibrosis in all forms of diabetes. If you have T1D and CKD, ask your endocrinologist whether you meet the prescribing criteria.
Q: How does finerenone protect kidneys?
A: Finerenone protects kidneys by blocking the mineralocorticoid receptor (MR), which is overactivated in diabetic kidney disease. When aldosterone binds to MR receptors in kidney tissue, it triggers fibrosis (scarring) and inflammation — the two processes that progressively destroy kidney function. By selectively blocking this receptor, finerenone interrupts the scarring cycle. Clinical trials showed an 18% reduction in the risk of kidney failure, sustained eGFR decline of 40% or more, or renal death, compared to placebo when added to standard therapy.
Q: What are the side effects of finerenone?
A: The most common clinically significant side effect of finerenone for type 1 diabetes is hyperkalemia (elevated blood potassium), which occurred in 18.3% of finerenone-treated patients versus 9.0% on placebo in the FIDELIO-DKD trial. Most cases were mild to moderate and managed through dose adjustment or dietary changes — only 2.3% led to permanent discontinuation. Other side effects include mild hypotension (4.8% vs 3.4% placebo) and a small initial eGFR dip that typically stabilises. Importantly, finerenone does not cause gynecomastia or sexual side effects, which are common with the older MRA spironolactone, because its non-steroidal structure avoids cross-reactivity with sex-hormone receptors.
Q: How is finerenone different from spironolactone?
A: Three key differences separate finerenone for type 1 diabetes from spironolactone. First, finerenone is non-steroidal while spironolactone is steroidal — this means finerenone avoids the hormonal side effects (gynecomastia, menstrual irregularity, sexual dysfunction) that spironolactone causes through cross-reactivity with androgen and progesterone receptors. Second, finerenone has balanced heart-kidney tissue distribution, giving it dual cardiorenal protection, while spironolactone concentrates more in cardiac tissue. Third, finerenone has a shorter half-life and lower active metabolite accumulation, which may contribute to a more predictable safety profile in patients with reduced kidney function. Both drugs block the mineralocorticoid receptor, but finerenone’s non-steroidal chemistry translates into a meaningfully different clinical experience.
Q: Who should not take finerenone?
A: Finerenone is contraindicated in people with eGFR below 25, baseline serum potassium above 5.0 mmol/L, concurrent use of strong CYP3A4 inhibitors (e.g., clarithromycin, itraconazole, ritonavir), pregnancy, severe hepatic impairment (Child-Pugh Class C), and known hypersensitivity to the drug. People with Addison’s disease (primary adrenal insufficiency) should also avoid it. If you are taking both an ACE inhibitor and an ARB simultaneously — already an uncommon combination for most CKD patients — adding finerenone would compound hyperkalemia and acute kidney injury risk and is not recommended. The NHS chronic kidney disease resource provides additional context on CKD staging and management principles that may help you understand where you fall.
Q: Can I take finerenone and an SGLT2 inhibitor together?
A: There is growing clinical interest in combining finerenone for type 1 diabetes with an SGLT2 inhibitor, because the two drug classes protect kidneys through completely different mechanisms — finerenone reduces fibrosis and inflammation, while SGLT2 inhibitors reduce intraglomerular pressure haemodynamically. Research suggests the pathways are complementary. However, the formal evidence from dedicated combination trials is still emerging: the CONFIDENCE trial (finerenone + empagliflozin) is expected to report in 2027. For now, combination therapy is at the discretion of your nephrologist or endocrinologist, who will weigh the potential additive kidney protection against the additive risks (particularly hyperkalemia and volume depletion).
Q: How often do I need blood tests while taking finerenone?
A: The standard monitoring schedule for finerenone for type 1 diabetes is: baseline labs (within 4 weeks before starting), then potassium and eGFR checks at week 4, week 8, and week 12 after starting or after any dose change. Once your dose is stable and potassium levels are confirmed to be in range, monitoring extends to every 4 months. If you start a medication that interacts with finerenone (such as a new CYP3A4 inhibitor), or if you develop acute illness that could affect kidney function (gastroenteritis with dehydration, for example), additional checks may be needed. Your doctor will provide a personalised schedule, but at minimum, expect four blood tests in your first three months. The MedlinePlus guide to kidney function tests explains what each test measures.
Q: Will finerenone replace my ACE inhibitor or ARB?
A: No. Finerenone is designed as an add-on to ACE inhibitor or ARB therapy, not a replacement. In every major clinical trial, participants continued their maximum-tolerated ACEi or ARB dose alongside finerenone. The rationale: ACE inhibitors and ARBs work primarily through haemodynamic pathways (reducing pressure inside the glomeruli), while finerenone addresses the inflammatory and fibrotic pathways that continue even after RAAS blockade is optimised. Stopping your ACEi/ARB to take finerenone would remove one layer of protection while adding another — the goal is to stack complementary mechanisms, not swap them.
The Bottom Line
Finerenone for type 1 diabetes represents the first genuinely new mechanism for kidney protection in the T1D population since the introduction of ACE inhibitors more than 30 years ago. By targeting the mineralocorticoid receptor — the biological switch that drives fibrosis and inflammation inside kidney tissue — it addresses residual risk that blood pressure control and glucose management alone cannot eliminate.
The evidence is clear but comes with important nuance. The landmark trials (FIDELIO-DKD and FIGARO-DKD) demonstrated an 18% reduction in kidney failure risk and a 13% reduction in cardiovascular events — but these studies were conducted in type 2 diabetes populations. The 2026 label expansion to T1D is based on the mechanistic rationale that MR overactivation is a shared pathological feature across diabetes types, not on a dedicated T1D randomised trial. This does not mean finerenone will not work for you — the biology is sound — but it does mean that post-marketing surveillance data, expected in 2027–2028, will add important context to the safety and efficacy picture in the T1D population specifically.
Your immediate action step: If you have type 1 diabetes and know or suspect you have kidney involvement, request a kidney function panel (eGFR, UACR, serum potassium) from your doctor. These three numbers determine whether finerenone for type 1 diabetes is an option. If your eGFR is ≥25, your UACR shows elevated albuminuria, and your potassium is ≤4.8 — and you are already on an ACEi or ARB — you may be a candidate. Bring the candidacy criteria from this article to your next appointment.
Two questions worth asking next: If you are managing multiple chronic conditions, understanding how kidney health intersects with cardiovascular risk may be your next priority — blood pressure medications at MedsBase provides an overview of the RAAS-blocking drugs that form the foundation of kidney protection. And if you have been diagnosed with diabetes-related kidney changes, understanding the full spectrum of diabetes medications available — from glucose control to organ protection — can help you have a more informed conversation with your healthcare team.
Living with type 1 diabetes for decades is a marathon that demands adaptation at every stage. Finerenone for type 1 diabetes is not a cure — no single pill is. But for people whose kidney function is declining despite doing everything else right, it is a tool worth understanding, and worth asking about.
Medical Disclaimer
This article is for informational purposes only and does not constitute medical advice. The content is based on publicly available clinical trial data, regulatory documents, and peer-reviewed research as of September 2026. Individual treatment decisions should be made in consultation with a qualified healthcare professional who knows your full medical history. Never start, stop, or adjust any medication without speaking to your doctor first. Finerenone (Kerendia) is a prescription medication; its suitability for your specific situation depends on multiple clinical factors that cannot be assessed through an article alone.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.