








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
ibuprofen vs acetaminophen — Ibuprofen vs Acetaminophen: 8 Key Differences That Determine Which Pain Reliever Is Right for You. Read on for an evidence-backed guide covering everything you need to know.
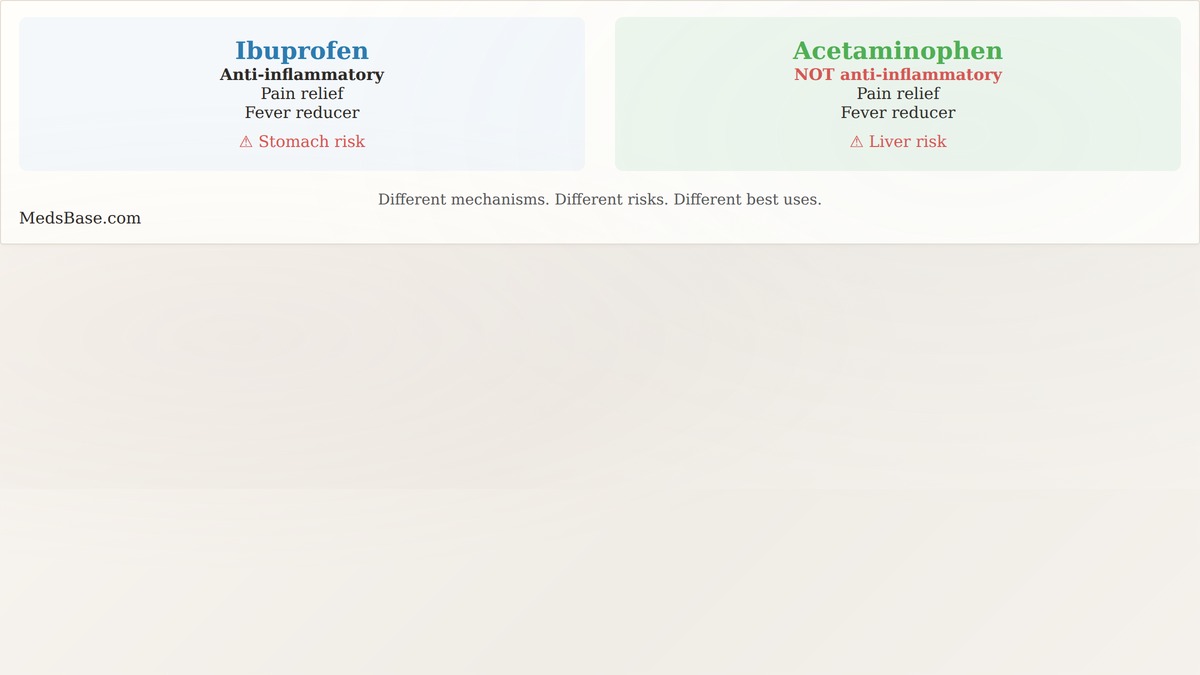
# Ibuprofen vs Acetaminophen: 8 Key Differences That Determine Which Pain Reliever Is Right for You
Ibuprofen vs acetaminophen — you are standing in the pharmacy aisle, pain radiating from your lower back or throbbing behind your eyes, staring at two bottles that both promise relief. One says ibuprofen. The other says acetaminophen. They cost roughly the same, sit next to each other on the shelf, and are both labeled “pain reliever.” So which one do you grab? The ibuprofen vs acetaminophen decision is one that millions of people make every day — often incorrectly — and the wrong choice can mean the difference between effective relief and a medication that barely touches your pain, or worse, one that puts an organ you did not even know was vulnerable at risk. Getting the ibuprofen vs acetaminophen choice right every time means understanding not just which drug “works,” but how your specific pain type, medical history, and other medications interact with each option.
Ibuprofen vs acetaminophen — by the end of this guide, you will know exactly how these two medications differ — not just that one reduces inflammation and the other does not, but how they affect your stomach, liver, kidneys, and heart, which types of pain each treats best, what the research actually says about their effectiveness head-to-head, and the safe-dosing rules that could save you from a preventable medication injury. One of these rules — never exceed 4,000 milligrams of acetaminophen in a day, but ideally cap it at 3,000 — is something an estimated 30 percent of regular users do not follow.
Key Takeaways
Ibuprofen vs acetaminophen — ibuprofen is an NSAID that blocks inflammation at its source — making it the better choice for sprains, strains, back pain, arthritis, menstrual cramps, and dental pain.
Ibuprofen vs acetaminophen — acetaminophen works primarily in the brain and spinal cord — it is equally effective for headaches and fever, but does NOT reduce swelling or inflammation anywhere in the body.
Ibuprofen vs acetaminophen — ibuprofen’s main risks are stomach ulcers, kidney damage, and (with long-term use) increased cardiovascular risk. Acetaminophen’s main risk is liver damage — and the toxic dose is closer to the therapeutic dose than most people realize.
Ibuprofen vs acetaminophen — you CAN take ibuprofen and acetaminophen together (alternating doses) for severe pain — this combination is more effective than either alone and is often used after dental surgery and other acute procedures.
Ibuprofen vs acetaminophen — the “right” choice depends on your type of pain, your age, your existing health conditions, and which other medications you take — there is no universal “ibuprofen is better” or “acetaminophen is safer” answer.
- How Ibuprofen Works vs How Acetaminophen Works
- Which Pain Reliever Works Best for Which Type of Pain?
- Effectiveness Comparison: What the Research Says
- 8 Key Differences Between Ibuprofen and Acetaminophen
- Organ Safety: What Each Medication Does to Your Body
- Special Populations: Age, Pregnancy, and Medical Conditions
- How to Take Each Safely — Dosing Rules That Matter
- Can You Take Ibuprofen and Acetaminophen Together?
- Frequently Asked Questions
- The Bottom Line
How Ibuprofen Works vs How Acetaminophen Works — Ibuprofen vs acetaminophen Explained
The ibuprofen vs acetaminophen distinction starts at the molecular level, and once you understand the mechanism, almost everything else about their differences makes sense.
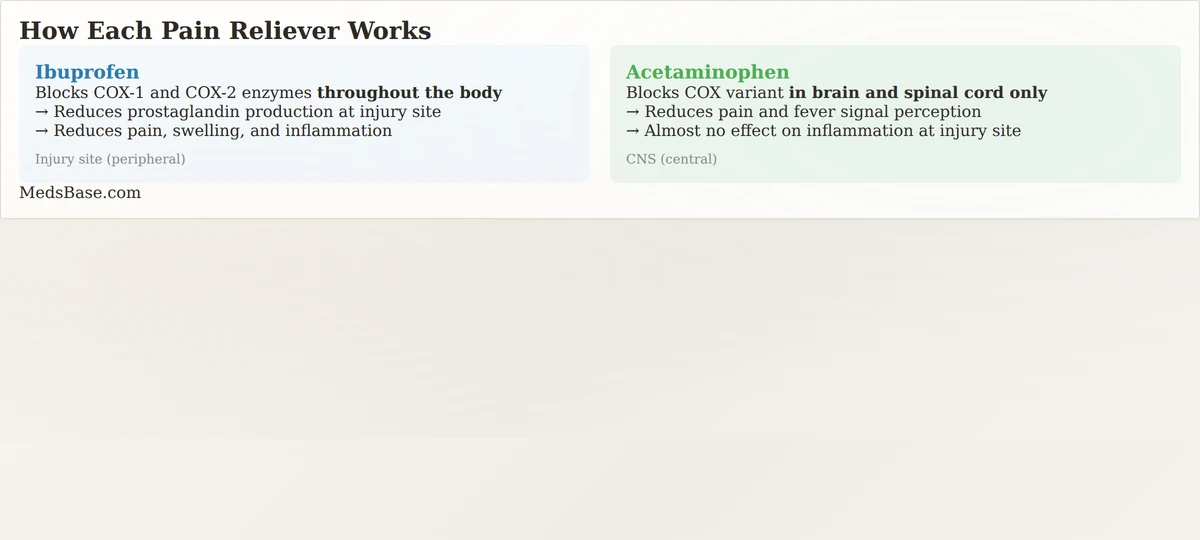
Ibuprofen belongs to a class of medications called nonsteroidal anti-inflammatory drugs, or NSAIDs. It works by inhibiting two enzymes — cyclooxygenase-1 (COX-1) and cyclooxygenase-2 (COX-2) — that produce prostaglandins, which are chemical messengers that signal pain, fever, and inflammation throughout the body. By blocking COX enzymes at the site of an injury or inflammatory process, ibuprofen reduces the production of prostaglandins right where the problem is — in your sprained ankle, your arthritic knee, or your inflamed dental socket. This is why ibuprofen not only relieves pain but also reduces swelling, redness, and heat.
Acetaminophen (known as paracetamol outside the United States) works differently — and remarkably, scientists still do not fully agree on its exact mechanism. The leading theory is that acetaminophen primarily inhibits a variant of the COX enzyme in the central nervous system — the brain and spinal cord — while having very little effect on COX enzymes in peripheral tissues. This means acetaminophen reduces pain and fever signals in the brain, but it does almost nothing to reduce inflammation at the site of the injury. Your ankle still swells; you just perceive less pain from it.
What this means for you: If your pain is inflammatory — a sprained muscle, an arthritic joint, a dental procedure, menstrual cramps — ibuprofen addresses the root cause (prostaglandin-driven inflammation) while acetaminophen only masks the pain signal. If your pain is non-inflammatory — a tension headache, a fever, general body aches from a cold — the two medications are more comparable in effectiveness. The ibuprofen vs acetaminophen performance gap is largest for inflammatory pain and narrowest for headache and fever, which is why understanding your pain type should drive the decision.
Ibuprofen vs acetaminophen: Which Pain Reliever Works Best for Which Type of Pain?
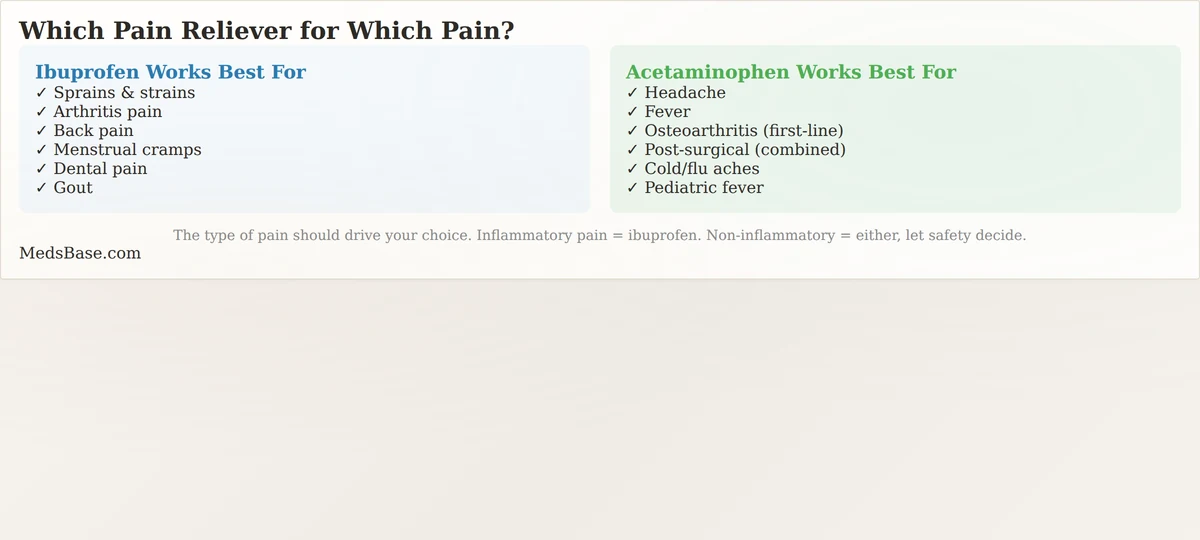
Here is your practical guide to the ibuprofen vs acetaminophen decision based on pain type:
| Pain Type | Better Choice | Reason |
|---|---|---|
| Tension headache | Either — both effective | Acetaminophen and ibuprofen are similarly effective for tension-type headaches. Ibuprofen may work slightly faster. |
| Migraine | Ibuprofen | The anti-inflammatory component helps with the neurogenic inflammation involved in migraine. Higher doses (400-600mg) are typically needed. |
| Back pain (muscular) | Ibuprofen | Muscle strain involves local inflammation. Ibuprofen addresses this directly. |
| Back pain (nerve/disk) | Ibuprofen preferred | If inflammation is contributing to nerve compression, ibuprofen reduces this component. |
| Arthritis (osteoarthritis) | Ibuprofen | Joint inflammation responds to COX inhibition. However, for elderly patients or those with GI/kidney concerns, acetaminophen may be the safer first choice. |
| Arthritis (rheumatoid) | Ibuprofen | This is an inflammatory arthritis — ibuprofen treats the inflammatory component directly. |
| Menstrual cramps | Ibuprofen | Prostaglandins drive uterine cramping. Ibuprofen blocks prostaglandin production at the source. Start at the first sign of cramps. |
| Dental pain | Ibuprofen | Post-procedure dental pain is highly inflammatory. Ibuprofen outperforms acetaminophen consistently in dental pain studies. |
| Sprains and strains | Ibuprofen | Acute soft-tissue injuries have a strong inflammatory component. |
| Fever | Either — both effective | Both reduce fever by acting on the brain’s temperature-regulating center. |
| Cold/flu body aches | Either | The aches are more pain-signal than inflammation. Both work. |
| Post-surgical pain | Ibuprofen + Acetaminophen | The combination is more effective than either alone and reduces opioid need. |
An important nuance: just because ibuprofen is the “better” choice for inflammatory pain does not mean it is the safer choice for you specifically. The best medication is the one that works for your type of pain AND that your body can tolerate. If you have a history of stomach ulcers, kidney disease, or are on blood thinners, acetaminophen may be the safer option even for inflammatory pain, because the small effectiveness gap is worth avoiding the much larger safety risk. The ibuprofen vs acetaminophen trade-off is never purely about effectiveness — safety always weighs in the balance, and for many people, safety tips the scale.
Ibuprofen vs acetaminophen: Effectiveness Comparison: What the Research Says
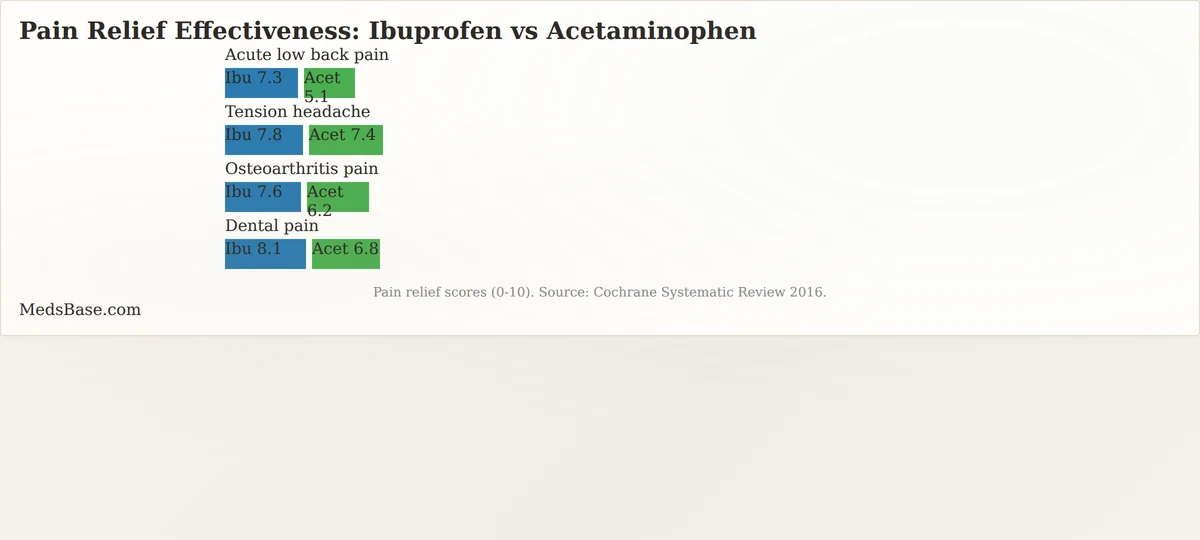
Ibuprofen vs acetaminophen — a Cochrane systematic review — the gold standard in evidence-based medicine — compared ibuprofen and acetaminophen head-to-head across multiple pain conditions. Here is what the data showed:
- Dental pain: Ibuprofen 400 mg provided significantly better pain relief than acetaminophen 1,000 mg. The number needed to treat (NNT) — how many patients need to receive the drug for one to achieve at least 50% pain relief — was 2.3 for ibuprofen vs 4.6 for acetaminophen. Lower is better; ibuprofen was approximately twice as effective per patient.
- Tension headache: Both medications were effective, with ibuprofen showing a modest but statistically significant advantage. The difference was smaller than for dental pain or musculoskeletal pain — a few percentage points of additional relief.
- Osteoarthritis: Ibuprofen was superior to acetaminophen for pain relief, but the advantage was less dramatic than for acute inflammatory pain. For many osteoarthritis patients, acetaminophen remains the recommended first-line pharmacologic treatment — not because it works better, but because its safety profile for long-term daily use is generally more favorable.
- Acute low back pain: Ibuprofen consistently outperformed acetaminophen, with the anti-inflammatory effect being particularly relevant given the inflammatory component of acute back strain.
- Postoperative pain: The combination of ibuprofen and acetaminophen together was more effective than either drug alone — and reduced the need for opioid rescue medication by approximately 30 to 40 percent.
What this means for you: For inflammatory pain, ibuprofen wins on effectiveness in the ibuprofen vs acetaminophen comparison. For non-inflammatory pain (headache, fever), the two are close enough that safety considerations should drive your choice. And for severe acute pain, the combination may work better than either alone.
8 Key Differences Between Ibuprofen and Acetaminophen
Here are the 8 differences that matter most when choosing between ibuprofen vs acetaminophen:
1. Drug Class
- Ibuprofen: NSAID (nonsteroidal anti-inflammatory drug)
- Acetaminophen: Analgesic (pain reliever) and antipyretic (fever reducer); NOT an NSAID
2. Anti-inflammatory Effect
- Ibuprofen: YES — reduces swelling, redness, and inflammation at the site of injury
- Acetaminophen: NO — almost no peripheral anti-inflammatory effect
This is the biggest practical difference in the ibuprofen vs acetaminophen comparison. If you twisted your ankle and it is visibly swollen, ibuprofen treats both the pain and the swelling. Acetaminophen only addresses the pain. For any injury where you can see or feel swelling, the ibuprofen vs acetaminophen choice favors ibuprofen for its dual mechanism: pain relief plus inflammation reduction.
3. Mechanism Target
- Ibuprofen: Peripheral tissues (COX-1 and COX-2 enzymes throughout the body)
- Acetaminophen: Central nervous system (brain and spinal cord COX variant)
4. Best Indications
- Ibuprofen: Inflammatory pain — arthritis, sprains, strains, menstrual cramps, dental pain, gout
- Acetaminophen: Non-inflammatory pain — headache, fever, osteoarthritis (first-line), cold/flu aches
5. Stomach Safety
- Ibuprofen: Higher risk — inhibits COX-1, which protects the stomach lining. Can cause gastritis, ulcers, and GI bleeding, especially with long-term or high-dose use.
- Acetaminophen: Stomach-safe — does not affect COX-1 in the stomach. The preferred choice for anyone with gastritis, ulcers, GERD, or taking other GI-irritating medications.
Stomach safety is often the deciding factor in the ibuprofen vs acetaminophen comparison for older adults and anyone with a history of GI issues. When stomach protection matters more than anti-inflammatory power, acetaminophen is the clear winner.
6. Liver Safety
- Ibuprofen: Generally liver-safe at therapeutic doses, though rare cases of liver injury have been reported.
- Acetaminophen: The primary safety concern. Acetaminophen is metabolized in the liver, and exceeding the recommended dose — or taking it with alcohol — can cause severe, sometimes fatal, liver damage. The toxic dose is only about 3-4 times the maximum daily therapeutic dose — a much narrower safety margin than most over-the-counter medications.
7. Kidney Safety
- Ibuprofen: Reduces blood flow to the kidneys by inhibiting prostaglandins that dilate renal blood vessels. Long-term or high-dose use can cause kidney injury, especially in people with pre-existing kidney disease, dehydration, or those taking other nephrotoxic medications (ACE inhibitors, diuretics).
- Acetaminophen: Generally kidney-safe at therapeutic doses, though very high doses or chronic heavy use have been associated with kidney damage in some studies.
For anyone with reduced kidney function, the ibuprofen vs acetaminophen decision tilts strongly toward acetaminophen, especially when combined with ACE inhibitors or diuretics.
8. Cardiovascular Safety
- Ibuprofen: NSAIDs as a class are associated with a modest increase in cardiovascular risk (heart attack, stroke) with long-term, high-dose use. A large Danish cohort study found that ibuprofen at doses above 1,200 mg/day was associated with increased cardiovascular event risk. Short-term, occasional use at standard OTC doses carries minimal risk.
- Acetaminophen: No established cardiovascular risk at therapeutic doses. Some observational studies have suggested a possible link between very high-dose chronic acetaminophen use and elevated blood pressure, but the evidence is weaker than for NSAIDs.
Organ Safety: What Each Medication Does to Your Body

Ibuprofen and Your Stomach
Ibuprofen vs acetaminophen — ibuprofen’s most common serious side effect is gastrointestinal injury. By inhibiting COX-1 — the enzyme that produces prostaglandins that protect the stomach lining from its own acid — ibuprofen can cause erosions, ulcers, and bleeding even at over-the-counter doses, especially when taken frequently or for extended periods.
Ibuprofen vs acetaminophen — according to the American College of Gastroenterology’s clinical guidelines, risk factors for NSAID-related GI complications include: age over 65, history of peptic ulcer disease, concomitant use of aspirin (including low-dose), anticoagulants (warfarin, apixaban, rivaroxaban), corticosteroids (prednisone), or SSRIs (fluoxetine, sertraline, etc.), and high-dose or long-term NSAID use.
Protective strategy: If you need ibuprofen and have any GI risk factor, take it with food, use the lowest effective dose for the shortest possible duration, and discuss with your doctor whether you should also take a proton-pump inhibitor (omeprazole, esomeprazole) to protect your stomach lining. The GI risk differential is one of the most significant factors in the ibuprofen vs acetaminophen decision for anyone with existing stomach issues.
Acetaminophen and Your Liver
Acetaminophen liver toxicity is the leading cause of acute liver failure in the United States and several other countries — not because the drug is inherently dangerous at therapeutic doses, but because its toxic threshold is relatively close to the therapeutic range, and many people inadvertently exceed it.
The FDA has taken multiple regulatory actions to reduce acetaminophen toxicity, including limiting prescription combination products to 325 mg of acetaminophen per tablet and requiring boxed warnings about liver injury.
The critical number to remember: 4,000 milligrams is the maximum daily dose — and many experts recommend capping it at 3,000 milligrams for anyone who takes it regularly. A single extra-strength tablet contains 500 mg; two tablets (1,000 mg) taken four times a day brings you to the 4,000 mg maximum. Add a cold medicine that also contains acetaminophen, and you can exceed the limit without realizing it.
Ibuprofen and Your Kidneys
NSAIDs reduce kidney blood flow by blocking prostaglandin-mediated vasodilation in the renal arteries. In healthy, well-hydrated people taking standard OTC doses for a few days, this effect is usually clinically insignificant. But in vulnerable populations — older adults, people with chronic kidney disease, those who are dehydrated, or those taking ACE inhibitors (lisinopril, ramipril) or ARBs (losartan, valsartan) plus a diuretic (the “triple whammy” of nephrotoxicity) — ibuprofen can precipitate acute kidney injury.
Ibuprofen and Your Heart
A large Danish cohort study examining NSAID use and cardiovascular outcomes found that ibuprofen was associated with a 31 percent increased risk of cardiac arrest when used at doses above 1,200 mg/day — but no significant increase at lower OTC doses. This risk is primarily relevant to people taking prescription-level doses (1,800-2,400 mg/day) for chronic conditions like arthritis, not to someone taking 200-400 mg occasionally for a headache.
Special Populations: Age, Pregnancy, and Medical Conditions
Pregnancy: Acetaminophen is the preferred pain reliever during all trimesters of pregnancy. Ibuprofen and other NSAIDs are generally avoided, particularly in the third trimester, because they can cause premature closure of the ductus arteriosus (a fetal blood vessel) and reduce amniotic fluid levels. In the first and second trimesters, ibuprofen should only be used if clearly needed and under medical guidance.
Breastfeeding: Both ibuprofen and acetaminophen are considered compatible with breastfeeding at standard doses, with minimal transfer into breast milk. Ibuprofen is often preferred for postpartum pain because it addresses uterine cramping in addition to general pain relief.
Children: Both medications have pediatric formulations, but dosing is weight-based, and the age cutoffs differ. Ibuprofen is generally approved for infants 6 months and older; acetaminophen can be used in younger infants. For fever in children, both are effective, and alternating doses of the two medications is sometimes used for high or persistent fevers — but this should only be done with clear pediatrician guidance to avoid dosing errors.
Older adults (65+): The safety calculus shifts with age. Older adults are at higher risk for ibuprofen’s GI and kidney side effects, and for acetaminophen’s cumulative toxicity (due to age-related changes in liver metabolism). For chronic pain in older adults, acetaminophen is generally the recommended first-line OTC analgesic, not because it works better, but because the risk-benefit ratio is more favorable when used as directed. The ibuprofen vs acetaminophen balance pivots with age — what works safely at 35 may carry different risks at 75.
People with high blood pressure: NSAIDs, including ibuprofen, can raise blood pressure by an average of 3-5 mmHg (and sometimes more), an effect that is more pronounced in people with existing hypertension. Acetaminophen does not have this effect and is generally preferred for people whose blood pressure is difficult to control.
People on blood thinners: Acetaminophen is strongly preferred over ibuprofen for anyone taking warfarin, apixaban, rivaroxaban, clopidogrel, or aspirin. NSAIDs increase bleeding risk through both their antiplatelet effect (ibuprofen reversibly inhibits platelet aggregation) and their GI-toxicity potential (an upper GI bleed is far more dangerous when you are anticoagulated).
How to Take Each Safely — Dosing Rules That Matter
Ibuprofen Safe-Dosing Rules
- Standard adult OTC dose: 200-400 mg every 4-6 hours as needed
- Maximum OTC daily dose: 1,200 mg (six 200-mg tablets) per 24 hours
- Always take with food — even a glass of milk or a small snack significantly reduces stomach irritation
- Do not take for more than 10 days without consulting a doctor (pain) or 3 days (fever)
- Avoid ibuprofen if you: have had a stomach ulcer or GI bleed, have kidney disease (eGFR below 60), are taking blood thinners, are in the third trimester of pregnancy, or are dehydrated (especially after intense exercise or during illness)
- Stop ibuprofen before surgery — tell your surgeon you are taking it; NSAIDs increase surgical bleeding risk
Acetaminophen Safe-Dosing Rules
- Standard adult OTC dose: 325-1,000 mg every 4-6 hours as needed
- Maximum daily dose: 4,000 mg (recommended cap: 3,000 mg for regular use)
- Check ALL sources: Many prescription pain medications (Percocet, Vicodin, Tylenol with Codeine) and over-the-counter cold/flu products contain acetaminophen. Add up the total from all sources — do not exceed 4,000 mg combined.
- Avoid or reduce dose if you: consume more than 3 alcoholic drinks per day, have liver disease, or take other medications metabolized by the liver
- Acetaminophen overdose symptoms may not appear for 24-48 hours — if you suspect you have taken too much, get emergency medical help immediately, even if you feel fine. N-acetylcysteine (the antidote) is most effective within 8 hours of ingestion.
The Most Common Acetaminophen Mistake
The scenario: you have a bad cold. You take two extra-strength acetaminophen tablets (1,000 mg) every 6 hours for the body aches (4,000 mg/day). You also take a dose of NyQuil or a similar multi-symptom cold medicine, which contains another 650 mg of acetaminophen per dose. You have now exceeded 4,000 mg — and you may not feel any symptoms until your liver is already injured. Always read the active ingredients on every medication you take, and never exceed 4,000 mg from all sources combined.
Can You Take Ibuprofen and Acetaminophen Together?
Yes — and for certain types of pain, the combination works better than either medication alone.
Because ibuprofen and acetaminophen work through different mechanisms and are metabolized through different pathways, they can be safely combined for short-term use in people without contraindications to either drug. The combination is more effective than doubling the dose of either drug alone, and it is routinely used in postoperative pain management, dental procedures, and acute musculoskeletal injuries.
The standard alternating protocol: Take ibuprofen, then 3 hours later take acetaminophen, then 3 hours later take ibuprofen again, and so on. This gives you a pain-relief dose every 3 hours (rather than every 6 hours with either alone) while keeping the daily total of each drug within safe limits. For example:
- 8:00 a.m. — ibuprofen 400 mg
- 11:00 a.m. — acetaminophen 1,000 mg
- 2:00 p.m. — ibuprofen 400 mg
- 5:00 p.m. — acetaminophen 1,000 mg
- 8:00 p.m. — ibuprofen 400 mg
- 11:00 p.m. — acetaminophen 1,000 mg (if needed)
This protocol provides round-the-clock pain coverage while keeping each drug at half its maximum daily dose. It should only be used for 2-3 days for acute pain — it is not designed for chronic daily use.
Frequently Asked Questions
Q: Which is better for headache, ibuprofen or acetaminophen?
A:
A: For tension-type headaches, ibuprofen and acetaminophen are similarly effective — the difference in pain relief between the two is small. Ibuprofen may work slightly faster and may have a modest advantage, but many people find acetaminophen works just as well for their typical headache. If you get frequent headaches, choose the medication that feels more effective for you — and if headaches occur more than twice a week, talk to your doctor about preventive treatment options rather than relying on daily analgesics.
Q: Is ibuprofen safer than acetaminophen for long-term use?
A:
A: Neither is “safe” for unmonitored long-term daily use — they have different but equally serious risk profiles. Long-term ibuprofen use increases your risk of stomach ulcers, GI bleeding, kidney damage, and cardiovascular events. Long-term high-dose acetaminophen use increases your risk of liver damage, particularly if combined with alcohol. The choice for chronic pain should be made with your doctor, considering your specific risk factors. For many older adults, acetaminophen is preferred because its risk profile, at recommended doses, is considered more favorable for chronic use than NSAIDs.
Q: Can I take ibuprofen and Tylenol together?
A:
A: Yes, for short-term acute pain (2-3 days), you can alternate ibuprofen and acetaminophen (Tylenol). They work through different mechanisms and are metabolized through different pathways, so they are safe to combine for short periods in people without contraindications to either drug. The alternating protocol (taking one, then the other 3 hours later) provides more consistent pain coverage and may be more effective than either alone. Do not use the combination for more than 3 days for self-treated pain without consulting a doctor.
Q: Why can’t I take ibuprofen if I have stomach problems?
A:
A: Ibuprofen inhibits the COX-1 enzyme, which produces prostaglandins that protect your stomach lining. Without that protective prostaglandin layer, stomach acid can damage the lining, causing gastritis, erosions, and ulcers — and these can bleed. If you have GERD, gastritis, a history of peptic ulcer disease, or are taking blood thinners, the risk of a serious GI bleed from ibuprofen is significantly higher. Acetaminophen does not affect the stomach lining and is the safer choice if GI safety is a concern.
Q: Does acetaminophen reduce inflammation?
A:
A: No. Acetaminophen has almost no anti-inflammatory effect in peripheral tissues. It reduces pain and fever by acting primarily on COX enzymes in the central nervous system, but it does not block prostaglandin production at sites of inflammation. If you have a visibly swollen joint or injury, acetaminophen will relieve your perception of pain but will not reduce the swelling. Ibuprofen addresses both.
Q: What is the maximum safe dose of ibuprofen per day?
A:
A: For over-the-counter use, the maximum is 1,200 mg per day (six 200-mg tablets in 24 hours). For prescription use, under medical supervision, doses up to 3,200 mg per day have been used for conditions like rheumatoid arthritis, but these higher doses significantly increase the risk of gastrointestinal, renal, and cardiovascular side effects. OTC ibuprofen should not be taken for more than 10 days for pain or 3 days for fever without consulting a doctor.
Q: What happens if you take too much acetaminophen?
A:
A: Acetaminophen overdose causes liver damage that can be fatal. The toxic metabolite NAPQI builds up when the liver’s normal detoxification pathways are overwhelmed, causing oxidative damage to liver cells. Early symptoms (first 24 hours) may be mild or absent — nausea, vomiting, abdominal pain — which is dangerously misleading. Liver failure develops over the next 24-72 hours. If you suspect you have taken too much acetaminophen (over 4,000 mg in 24 hours, or any amount if you have liver disease), get emergency medical help immediately. The antidote, N-acetylcysteine, is most effective when given within 8 hours.
Q: Can I give my child ibuprofen and acetaminophen at the same time?
A:
A: For children with high or persistent fever, alternating ibuprofen and acetaminophen (every 3-4 hours between the two, rather than giving both at the exact same time) is sometimes used under pediatrician guidance. However, the risk of dosing errors is significant — parents can accidentally give too much of one or both medications. Always dose by the child’s weight (not age), use the measuring device that came with the medication (not a kitchen spoon), and keep a written log of exactly what and when you gave. Never exceed the recommended dose for your child’s weight, and consult your pediatrician before starting an alternating regimen.
The Bottom Line
The ibuprofen vs acetaminophen decision comes down to three questions you should ask yourself every time you reach for a pain reliever:
- What kind of pain do I have? If it is inflammatory — an injury with swelling, arthritis, menstrual cramps, dental pain — ibuprofen is the more effective choice. If it is non-inflammatory — headache, fever, general aches — either works, so let safety guide you.
- What are my personal risk factors? If you have stomach issues, kidney disease, high blood pressure, or take blood thinners, acetaminophen is probably the safer choice. If you have liver disease or drink more than 3 alcoholic drinks a day, ibuprofen may be safer. If you are over 65 or pregnant, acetaminophen is generally preferred. Your medical history should drive the decision when effectiveness is comparable.
- How long will I be taking it? For a day or two of acute pain — a sprained ankle, a post-procedure toothache, a bad headache — the risk of either medication is very low if you stay within the recommended dose. For ongoing daily use, the risks accumulate, and you need to discuss a plan with your doctor that balances effectiveness and safety. No OTC pain reliever is designed for unmonitored daily use indefinitely.
For most people, most of the time, having both ibuprofen and acetaminophen in your medicine cabinet — and knowing when to use each — is the optimal approach. The ibuprofen vs acetaminophen question does not have to be answered just once. For inflammatory pain, reach for ibuprofen. For headache or fever with GI concerns, reach for acetaminophen. For severe acute pain, consider alternating both. And for any pain that persists beyond 10 days, see your doctor — because the medication is managing a symptom, not treating the cause.
Looking for more detailed medication comparisons? Read our guide to aspirin vs ibuprofen or explore the full Pain Management category at MedsBase to understand all your treatment options.
Medical Disclaimer: This article is for informational purposes only and does not constitute medical advice. Ibuprofen and acetaminophen are medications with real risks, and the choice between them should account for your personal medical history, current medications, and specific health conditions. Never exceed recommended doses. Always consult your doctor or pharmacist before starting any new medication, especially if you have liver disease, kidney disease, stomach problems, heart conditions, high blood pressure, or are pregnant or breastfeeding.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.