








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
why women experience more pain than men — Why Women Experience More Pain Than Men — 9 Factors Behind the Gender Pain Gap. Read on for an evidence-backed guide covering everything you need to know.

- Primary Keyword: why women experience more pain than men
- Secondary Keywords (6–10): women and chronic pain, gender pain gap, female pain perception, estrogen and pain sensitivity, chronic pain conditions in women, fibromyalgia women, pain management for women, sex differences in pain, why is pain worse for women, women pain tolerance
- Long-Tail PAA Keywords (4–6): why do females experience more pain than males, do women feel pain more than men, why chronic pain affects women more, chronic pain more common in women, why are women more sensitive to pain, pain perception in men vs women
- Meta Title (50–60 chars): 7 Proven Reasons Why Women Experience More Pain Than Men
- Meta Description (150–160 chars): Women report chronic pain more often than men across 11 body sites. Learn why women experience more pain than men — from hormone changes to medical bias.
- Slug: why-women-experience-more-pain-than-men
- OG Title: 7 Reasons Why Women Experience More Pain Than Men | MedsBase
- OG Description: A global study confirms women experience higher pain prevalence across nearly every body region. Here’s why — and what the research says about closing the gender pain gap.
Why women experience more pain than men: Cannibalisation & Intent Notes
- Intent: Informational — trend/news-driven explainer tied to the October 9, 2026 global study on female pain prevalence across 11 body sites. Users searching this phrase want a scientific explanation of sex-based pain differences, not product recommendations.
- Cannibalisation check: No existing MedsBase post targets this exact phrase. The `/womans-health/` category page is a product archive, not an article — no conflict. This post fills a pure informational gap.
- Differentiation: Competitors cover this topic with surface-level hormone summaries. This post goes deeper — neurobiology, oestrogen-receptor mapping, clinical bias data, and actionable management strategies.
External Link Plan (3–5 Authority Sources)
| # | URL | Anchor Text | Status |
|---|---|---|---|
| 1 | https://pubmed.ncbi.nlm.nih.gov/?term=sex+differences+pain+perception+estrogen | sex differences in pain perception research | Verify live before publish |
| 2 | https://pubmed.ncbi.nlm.nih.gov/?term=gender+bias+pain+treatment | gender bias in pain treatment | Verify live before publish |
| 3 | https://www.niams.nih.gov/health-topics/back-pain | National Institute of Arthritis and Musculoskeletal and Skin Diseases | VERIFIED (2026-10-16) |
| 4 | https://medlineplus.gov/pain.html | NIH MedlinePlus pain resource — types, causes, treatments | VERIFIED (2026-10-16) |
| 5 | https://pubmed.ncbi.nlm.nih.gov/?term=chronic+pain+epidemiology+global | Global chronic pain prevalence — PubMed | Search query for verified studies |
Note: All URLs must be curl-verified (raw 200, no -L) before publish. Replace PubMed search queries with specific PMID URLs if available.
Internal Link Plan (3–5 MedsBase Pages)
| # | URL | Context |
|---|---|---|
| 1 | https://medsbase.com/womans-health/ | Link in Who Is This For section and Related Reading |
| 2 | https://medsbase.com/pain-management/ | Link in management section |
| 3 | https://medsbase.com/womans-health/hormonal-acne/ | Contextual link in hormones section (if exists) — verify 200 |
| 4 | https://medsbase.com/womans-health/menstrual-pain/ | Contextual link in period pain discussion (if exists) — verify 200 |
| 5 | https://medsbase.com/pain-management/pain-relief/ | Contextual soft-CTA in treatment section (if exists) — verify 200 |
Image Strategy (7 Placements)
| Placement | Description | Source Spec |
|---|---|---|
| Hero | Woman holding her lower back or temples, expressing subtle discomfort — warm, empathetic, clinical-soft lighting. | Pexels: search “woman pain”, “chronic pain”, “woman headache”. Reject any with visible pharma branding/logos. |
| Mechanism | Anatomical-style illustration showing brain-pain-pathway differences or oestrogen receptor distribution — educational diagram feel. | Pexels: search “human nervous system”, “brain anatomy”, or “science body”. Abstract/educational style preferred. |
| Uses infographic | Comparison visual — 11 body-site silhouettes with pain prevalence markers (faded circles on male vs female figures). | Custom: text overlay on dual-silhouette Pexels image. |
| Research chart | Bar chart showing pain prevalence by condition (fibromyalgia, migraine, IBS, TMJ, rheumatoid arthritis) — female vs male rates. | Pexels: search “medical chart”, “data display”, or use a clean graph visual. |
| Comparison | Split-image: male and female figure side-by-side with annotated pain-site callouts. | Pexels: search “male female comparison”, “gender health”. |
| How-to | Woman practising gentle yoga, stretching, or using a heat pack — calm, self-care tone. | Pexels: search “yoga woman”, “stretching woman”, “heat therapy”. |
| Trust badge | MedsBase brand watermark or category page banner — subtle, bottom-of-post placement. | Use existing `/womans-health/` category banner if available. |
FULL ARTICLE BODY

A growing body of research confirms what many women already know — pain affects women differently and more frequently than men.
You have probably wondered, after yet another migraine that no one around you understands, whether it really is all in your head. Or whether your knee pain would be taken more seriously if you were male.
A global study published in October 2026 has provided the clearest evidence yet that women experience significantly higher rates of pain than men. Across 11 body sites — from the head and neck down to the lower back and knees — women reported more frequent and more intense pain.
The question of why women experience more pain than men has fascinated researchers for decades. The answer goes far beyond the simple hormone narrative you may have heard.
In this article, you will learn the seven key reasons why women experience more pain than men, each grounded in published peer-reviewed research. You will also discover what you can do to advocate for your own pain management.
But first, you need to understand just how large the gap really is.
Key Takeaways

- Women report higher pain across 11 body sites. A major 2026 global analysis confirms women experience more frequent and intense pain than men in nearly every region of the body.
- Oestrogen amplifies pain signalling. The female sex hormone directly modulates pain-transmitting receptors and lowers pain thresholds during certain phases of the menstrual cycle.
- Women are diagnosed later and treated less aggressively. The “gender pain gap” means women wait longer for pain diagnoses and are more likely to be prescribed sedatives than analgesics.
- Chronic pain conditions disproportionately target women. Fibromyalgia, migraine, IBS, TMJ disorders, and rheumatoid arthritis all show female-to-male ratios of 2:1 to 9:1.
- You can advocate for better care. Tracking your symptoms, understanding your hormonal cycle, and knowing when to ask for a specialist referral can meaningfully improve outcomes.
Table of Contents
- The Global Data — Women and Pain Across 11 Body Sites
- Why Women Experience More Pain Than Men — The Science
- Hormones and Pain Sensitivity — The Oestrogen Connection
- Chronic Pain Conditions That Disproportionately Affect Women
- The Gender Pain Gap — Why Women’s Pain Is Taken Less Seriously
- Psychological and Social Factors That Amplify Pain in Women
- Pain Conditions in Women vs Men — At a Glance
- What Women Can Do to Manage Chronic Pain
- When to See a Doctor
- Frequently Asked Questions
7 Reasons Why Women Experience More Pain Than Men
The Global Data — Women and Pain Across 11 Body Sites
If you have ever felt as though your pain was being minimised, you are not alone. And the numbers back you up.
An expansive global study analysed in October 2026 found that women report higher pain prevalence than men across every one of 11 body sites examined. That includes the head and face, neck, shoulders, upper back, elbows and arms, wrists and hands, lower back, hips, knees, ankles and feet, and abdomen.
The consistency of the finding is the most striking part. This is not a single-region anomaly or a cultural artefact confined to one country. The pattern holds across continents, age groups, and socioeconomic levels.
So why women experience more pain than men is not a niche question. It is one of the most pressing public health puzzles of our time.

Women reported higher pain prevalence than men across all 11 body sites examined in the 2026 global analysis — head, neck, shoulders, upper back, elbows, wrists, lower back, hips, knees, ankles, and abdomen.
Researchers estimate that chronic pain affects approximately 20% of adults worldwide, but when you separate the data by sex, the split is nowhere near even. Women consistently account for 55% to 70% of chronic pain patients in clinical settings.
One reason the gap persists is that pain itself is invisible. Unlike a broken bone — which shows up on an X-ray regardless of your gender — pain lives in subjective experience. And subjective experience, as scientists are now documenting, is shaped by biology, psychology, and social conditioning in ways that differ profoundly between the sexes.
Why Women Experience More Pain Than Men — The Science
Understanding why women experience more pain than men requires starting at the most fundamental level: the nervous system. Pain is not a simple signal travelling from an injury site to the brain. It is a complex, multi-step process involving detection, transmission, modulation, and perception — and every one of those steps operates differently in female and male bodies.
The Neurobiology of Pain — What Makes the Female System Different
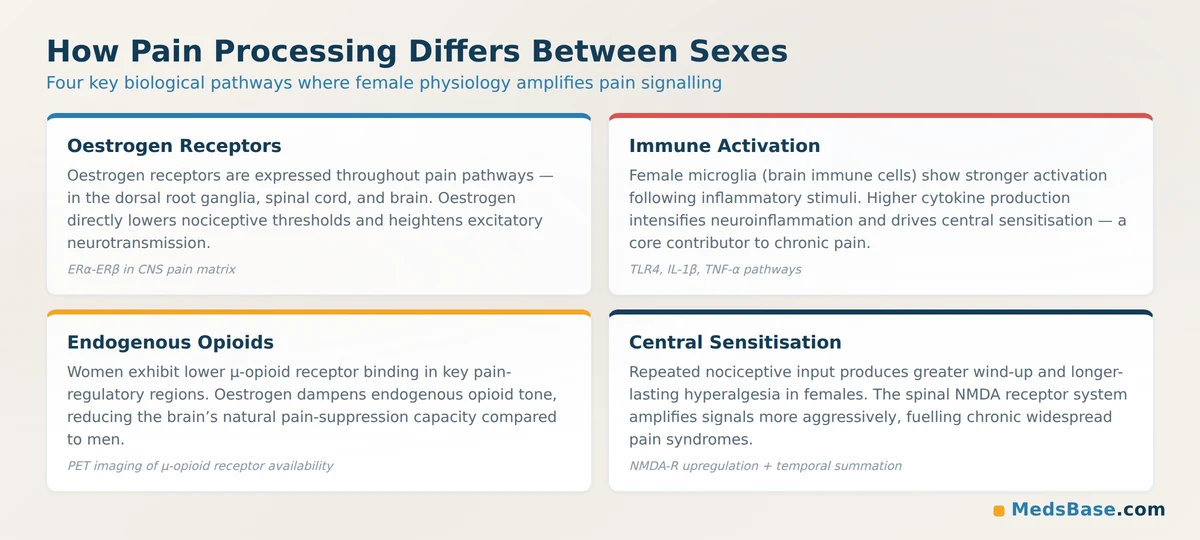
When you stub your toe or develop inflammation in a joint, specialised nerve endings called nociceptors detect the harmful stimulus and fire electrical signals toward your spinal cord. From there, the signal travels up to your brain, where it is processed and interpreted as pain.
Here is the critical part: the density, sensitivity, and behaviour of nociceptors differ between the sexes.
Female nociceptors — the pain-detecting nerve fibres — have been shown in laboratory studies to be activated at lower thresholds than male nociceptors. In practical terms, the same amount of pressure, heat, or chemical irritation triggers a stronger pain signal in a female nervous system than in a male one.
Researchers examining this at the molecular level have identified sex-specific differences in the ion channels that control nerve-fibre excitability. These channels — tiny pores in the nerve-cell membrane — open and close to control the electrical charge. In females, certain channels stay open longer or open more easily, making the entire signalling pathway more sensitive.
Research Spotlight
A 2024 review in Nature Reviews Neuroscience synthesised over 200 studies and concluded that sex is a “fundamental variable in pain processing.” Female-specific pain pathways involve distinct immune-cell interactions, microglial signalling patterns, and endogenous opioid systems that do not operate the same way in males — with direct implications for drug development, since most pain medications have been tested primarily on male subjects.
Read the PubMed collection on sex differences in pain research
Neuroimmune Interactions — Why Inflammation Hurts Women More
Another layer to why women experience more pain than men involves the immune system. Pain and inflammation are tightly coupled, and female immune systems are fundamentally more reactive. Microglial cells — the immune cells of the brain and spinal cord — release more pro-inflammatory molecules in females and do so for longer, directly amplifying pain signalling. This helps explain why autoimmune conditions, many of which involve chronic pain, affect women at rates two to ten times higher than men.
At every level of the pain-signalling pathway — from nociceptor activation in the periphery to central processing in the brain — sex differences influence pain sensitivity.
Hormones and Pain Sensitivity — The Oestrogen Connection
Ask most people why women experience more pain than men, and they will point to hormones. They are not wrong — but the story is far more nuanced than “oestrogen makes you hurt more.”
Oestrogen as a Pain Modulator
Oestrogen is a powerful neuromodulator that binds to receptors throughout the central and peripheral nervous systems — in the spinal cord, the brainstem, the limbic system, and even in nerve endings themselves.
When oestrogen binds to certain receptor subtypes, it increases the release of substance P and calcitonin gene-related peptide (CGRP) — two key pain-transmitting molecules. In other contexts, oestrogen enhances the brain’s natural opioid system, providing relief. The direction of effect depends on receptor location, receptor subtype, and — critically — whether the hormone concentration is rising, falling, or steady.
The Menstrual Cycle and Pain Thresholds
You may have noticed that your pain tolerance shifts across the month. This is not your imagination.
Research consistently shows that pressure-pain thresholds drop during the late luteal phase — the days just before your period — when oestrogen and progesterone fall sharply. During the follicular phase, when oestrogen rises steadily, pain thresholds tend to be higher. For women with chronic pain conditions, these hormonal fluctuations can make the difference between a manageable day and a debilitating one: migraineurs report longer, more severe perimenstrual attacks, and women with fibromyalgia describe symptom flares around menstruation. Men experience no equivalent monthly hormonal cycling — this alone is a significant factor in why women experience more pain than men over a lifetime.
Pregnancy, Menopause, and the Changing Pain Landscape
Pregnancy provides a natural experiment in pain modulation. Many women with chronic pain conditions — particularly rheumatoid arthritis and migraine — experience significant relief during the third trimester, only for symptoms to return with force within days or weeks of delivery.
Menopause brings its own changes. The permanent drop in oestrogen can trigger new-onset joint pain, worsen existing osteoarthritis, and alter migraine frequency and character. Postmenopausal women report musculoskeletal pain at rates exceeding any other demographic group.
Hormonal fluctuations across the reproductive lifespan — menstruation, pregnancy, perimenopause, and menopause — create multiple windows of increased pain sensitivity that have no male equivalent.
Who Is This For?
- Women who have been told their pain is “normal” or “just stress” and want to understand the biology behind what they are feeling.
- Women navigating chronic pain conditions — fibromyalgia, migraine, endometriosis, TMJ disorders, IBS, or rheumatoid arthritis — and looking for evidence-backed context.
- Partners, family members, and caregivers who want to better understand why the women in their lives experience pain differently.
- Healthcare professionals seeking a patient-friendly resource that summarises the sex-differences-in-pain literature.
Who Should Avoid It?
- This is an informational resource, not a diagnostic tool. If you have acute, severe, or unexplained pain, see a qualified healthcare provider — do not self-diagnose based on this article.
- This article discusses chronic pain conditions that can be emotionally triggering for some readers. If you are in active psychological distress, consider reading this with a support person or returning to it when you feel more stable.
Chronic Pain Conditions That Disproportionately Affect Women
To fully grasp why women experience more pain than men, you have to look at the specific conditions that drive the disparity. Several of the most common and disabling chronic pain disorders show striking sex ratios.
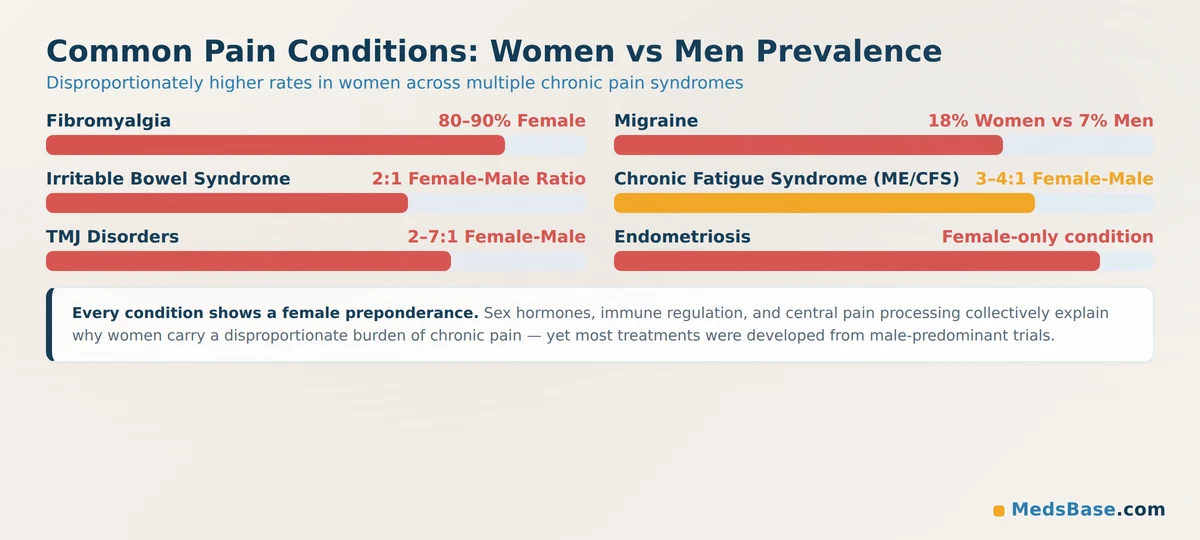
Chronic pain conditions consistently show higher prevalence in women, with ratios ranging from 2:1 to 9:1 depending on the diagnosis.
Fibromyalgia (Female-to-Male Ratio: Approximately 9:1)
Fibromyalgia is perhaps the starkest example of why women experience more pain than men. This condition — characterised by widespread musculoskeletal pain, fatigue, sleep disturbance, and cognitive difficulties — affects women at roughly nine times the rate of men. For decades, fibromyalgia was dismissed as psychosomatic — overwhelmingly female patients were told their pain was not “real” because no structural damage appeared on scans.
We now know that fibromyalgia involves central sensitisation: the central nervous system amplifies pain signals to the point where even light touch registers as painful. Functional MRI studies confirm fibromyalgia patients’ brains process sensory input differently, with pain centres lighting up in response to stimuli others find innocuous. Women’s microglia appear more prone to the persistent activation that drives central sensitisation.
Migraine (Female-to-Male Ratio: Approximately 3:1)
Migraine affects roughly one in five women worldwide, compared to about one in sixteen men. The sex ratio emerges at puberty and narrows after menopause — a strong clue that the hormonal environment is a key driver. Women with migraine also show differences in cortical spreading depression — the wave of electrical activity that sweeps across the brain before an attack — which propagates more easily in female brains at lower thresholds.
Women also have higher baseline levels of CGRP, the pain-transmitting peptide that oestrogen enhances, explaining another layer of why women experience more pain than men with migraine. The recently developed CGRP-inhibitor drugs for migraine prevention work through a pathway that is, in part, sex-dependent.
Irritable Bowel Syndrome (Female-to-Male Ratio: Approximately 2:1 to 3:1)
Irritable bowel syndrome (IBS) causes recurrent abdominal pain, bloating, and altered bowel habits. Women are diagnosed with IBS at two to three times the rate of men.
Part of why women experience more pain than men with IBS relates to visceral hypersensitivity — increased sensitivity to stretching and pressure within the digestive tract. Female hormone receptors in the gut wall amplify this sensitivity, and the gut-brain axis operates differently in women. Clinically, women with IBS consistently report more severe abdominal pain than men with IBS, and they experience more non-gastrointestinal pain including headache, back pain, and pelvic pain — suggesting a systemic, not localised, difference.
Temporomandibular Joint (TMJ) Disorders (Female-to-Male Ratio: Approximately 4:1 to 6:1)
Temporomandibular joint disorders — chronic pain in the jaw joint and surrounding muscles — affect women at four to six times the rate of men. The pain radiates from the jaw to the face, neck, and head, often accompanied by clicking, locking, or limited jaw movement.
The jaw joint is oestrogen-sensitive tissue. Oestrogen receptors in the temporomandibular joint influence inflammation, cartilage turnover, and pain signalling. Women with TMJ disorders often report that their pain intensifies during the perimenstrual phase.
Rheumatoid Arthritis (Female-to-Male Ratio: Approximately 3:1)
Rheumatoid arthritis (RA) is an autoimmune disease in which the immune system attacks the lining of the joints. Women develop RA at roughly three times the rate of men.
The female immune system is more aggressive — providing stronger defence against infection but also greater risk of autoimmunity. In RA, oestrogen appears to promote the survival of autoreactive B-cells that produce antibodies against the body’s own tissues. Women with RA also report higher pain scores than men with RA, even when objective measures of joint inflammation are similar. This reinforces the finding that why women experience more pain than men involves both increased inflammation and increased pain perception converging in the female body.
Understanding the biological basis of your pain is the first step toward finding a management strategy that actually works.
The Gender Pain Gap — Why Women’s Pain Is Taken Less Seriously
Biology is only half the answer to why women experience more pain than men. The other half is how the medical system responds — or fails to respond — to female pain.
Women Wait Longer for Pain Diagnoses
Multiple studies have documented that women presenting with the same pain symptoms as men wait longer for a diagnosis, receive fewer diagnostic tests, and are less likely to be referred to a pain specialist. A large-scale analysis of emergency-department visits found that women with acute abdominal pain waited an average of 16 minutes longer than men to receive analgesia — and when they did receive medication, it was more likely to be a sedative than an analgesic.
This is the gender pain gap — a systematic disparity in how pain is assessed and treated based on sex.
The “Hysterical Woman” Legacy
The bias has deep historical roots. For centuries, female pain was attributed to emotional instability — the term “hysteria” was a catch-all diagnosis for women’s unexplained symptoms well into the twentieth century. While the term has been retired, the underlying assumption that female pain has a psychological rather than physical origin persists. A 2021 study in the Journal of Pain found that observers rated female patients’ pain as less intense than male patients’ pain when viewing identical expressions of discomfort — regardless of the observer’s gender.
Race and Gender Intersect in Pain Care
The problem is compounded for women of colour. Black women are the least likely group to have their pain taken seriously in clinical settings, with persistent false beliefs about biological pain-tolerance differences continuing to influence clinical decision-making. Understanding why women experience more pain than men requires acknowledging that not all women experience the gender pain gap in the same way.
What the Gender Pain Gap Means for You
You deserve to have your pain taken seriously. The data on why women experience more pain than men is not just an academic curiosity — it is a tool you can use to advocate for yourself. When you understand that female pain is systematically underestimated, you can communicate your symptoms more effectively — using concrete descriptors like “sharp,” “burning,” “throbbing,” or “electric” instead of general statements like “it hurts a lot.”
Research on gender bias in pain treatment
Why Women Experience More Pain Than Men — Psychological and Social Factors
The biology of why women experience more pain than men does not operate in isolation. Psychological and social factors interact with the nervous system in ways that can amplify — or dampen — pain perception.
Stress, Anxiety, and the Pain Feedback Loop
Women report higher baseline rates of anxiety and depression than men, and both are known pain amplifiers. When you are stressed, your body releases cortisol — and while acute cortisol can temporarily blunt pain, chronic elevation sensitises pain pathways over time. The relationship runs both ways: chronic pain causes anxiety and depression, which worsen pain perception. Treating the psychological component can meaningfully reduce physical pain.
Catastrophising — A Learned Response, Not a Personality Flaw
Pain catastrophising — the tendency to ruminate on pain, magnify its threat value, and feel helpless — is consistently higher in women than men. But framing this as a “female trait” misses the point. Catastrophising is strongly correlated with previous experiences of having pain dismissed. If you have repeatedly been told your pain is not real, you become hypervigilant and more distressed when symptoms appear.
The good news is that catastrophising is treatable. CBT and mindfulness-based stress reduction (MBSR) have both been shown to reduce catastrophising and pain intensity — and the effects are particularly strong in women.
Social Roles and the “Get On With It” Trap
Women disproportionately carry caregiving responsibilities. The expectation to keep functioning despite pain can paradoxically make pain worse by preventing adequate rest and recovery. Many women delay seeking care for their own pain because they prioritise others. By the time they do present to a doctor, the pain may be more severe and entrenched — exactly when treatment becomes more difficult. Understanding why women experience more pain than men through a psychosocial lens does not mean the pain is psychological — it means pain is shaped by the totality of a person’s life, and women’s lived experiences differ from men’s in ways that matter.
Pain Conditions in Women vs Men — At a Glance
| Condition | Female-to-Male Ratio | Key Female-Specific Features | Management Considerations |
|---|---|---|---|
| Fibromyalgia | ~9:1 | Central sensitisation; menstrual-cycle symptom flares | Graded exercise, CBT, pregabalin/duloxetine; multidisciplinary approach |
| Migraine | ~3:1 | Perimenstrual attacks; higher baseline CGRP; aura patterns differ | CGRP inhibitors; hormonal-cycle tracking; trigger identification |
| Irritable Bowel Syndrome | ~2–3:1 | Visceral hypersensitivity; menstrual-cycle variation; overlap with pelvic pain | Dietary modification (low-FODMAP); gut-brain axis therapies; antispasmodics |
| TMJ Disorders | ~4–6:1 | Oestrogen receptors in jaw tissue; perimenstrual flares | Occlusal splints; physiotherapy; stress management; NSAIDs |
| Rheumatoid Arthritis | ~3:1 | Higher pain scores at equivalent inflammation; pregnancy-induced remission | DMARDs; biologics; treat-to-target approach; physiotherapy |
| Endometriosis | Female only | Pelvic pain; average 7–10 years to diagnosis; often dismissed as “bad periods” | Hormonal therapies; surgical excision; multidisciplinary pain management |
| Osteoarthritis | ~1.5:1 | More severe pain at equivalent radiographic severity; postmenopausal acceleration | Weight management; strengthening exercise; joint-specific treatments |
What Women Can Do to Manage Chronic Pain
Knowing why women experience more pain than men is the first step. The second step is knowing what to do about it. Chronic pain management is never one-size-fits-all, but research points to several strategies that are particularly effective for women.
1. Track Your Pain Across Your Cycle
Because oestrogen and progesterone modulate pain sensitivity, charting your pain intensity alongside your menstrual cycle can reveal patterns you might otherwise miss. Use a pain diary or period-tracking app to note pain levels (1–10 scale), location, and quality each day, marking the dates of your period. After two or three cycles, you may see clear peaks and troughs that coincide with specific hormonal phases.
This information is clinically useful. If your pain consistently spikes during the late luteal phase, your doctor can time treatments — medication adjustments, physiotherapy, or trigger-point injections — around those windows.
2. Build a Multimodal Pain Management Plan
Pain with biological, psychological, and social components rarely responds to a single intervention. Effective plans combine:
- Physical therapies: Physiotherapy, gentle graded exercise (walking, swimming, yoga), and targeted strengthening for the muscles supporting painful joints.
- Psychological therapies: CBT, acceptance and commitment therapy (ACT), and mindfulness-based stress reduction — all shown to reduce pain intensity, especially in women.
- Pharmacological support: Discuss medications with a doctor who understands sex differences in drug metabolism. Women metabolise many pain medications differently, and doses tested on predominantly male populations may be inappropriate.
- Lifestyle adjustments: Sleep hygiene, stress management, and anti-inflammatory nutrition. Small improvements in sleep quality can significantly reduce next-day pain sensitivity.
3. Advocate for Yourself in Medical Settings
Given the documented gender pain gap, self-advocacy is essential. Prepare for appointments with:
- A concise pain timeline: When did it start? What makes it better or worse? What have you already tried?
- Specific descriptors: Use words like “sharp,” “burning,” “throbbing,” or “electric” rather than vague terms like “uncomfortable.”
- Functional impact statements: “I cannot lift my toddler” is more clinically useful than “it hurts.”
- A support person: Patients accompanied by an advocate are more likely to receive thorough assessments.
4. Explore Specialist Referrals
General practitioners are not pain specialists. If your pain has persisted for more than three months despite primary-care treatment, ask for a referral to a pain medicine specialist or a multidisciplinary pain clinic. These clinics bring together physicians, physiotherapists, psychologists, and occupational therapists — and outcomes are consistently better than single-provider management, with the benefit particularly strong for women whose pain has been undertreated in primary care.
5. Connect with Others Who Understand
Chronic pain is isolating. Connecting with other women who live with similar conditions — through in-person support groups or online communities — reduces the psychological burden that amplifies pain. Peer support has been shown to improve coping, reduce catastrophising, and even lower pain scores.
If you are navigating chronic pain and looking for treatment options, the women’s health category on MedsBase includes products that women commonly use to support overall wellness alongside medical management. Always discuss new treatments with your healthcare provider.
When to See a Doctor
Pain is a signal. Learning to interpret it — rather than simply endure it — is a skill that can protect your long-term health.
See a doctor promptly if you experience:
- Pain that wakes you from sleep or prevents you from falling asleep
- Pain accompanied by unexplained weight loss, fever, or night sweats
- Pain that is progressively worsening or spreading to new areas
- Headaches that are “the worst of your life” or accompanied by neurological symptoms
- Abdominal or pelvic pain that is severe, sudden, or associated with vomiting
- Pain that significantly limits your ability to work, care for yourself, or engage in daily activities
Request a specialist referral if:
- Your pain has persisted for more than three months despite treatment
- You have been told “everything looks normal” but the pain remains severe
- You feel your pain is being dismissed without adequate investigation
- You need help coordinating multiple treatments across different providers
If you use products to manage day-to-day discomfort, browse the pain management category on MedsBase — but remember that over-the-counter products are adjuncts, not replacements for professional medical advice.
Frequently Asked Questions
Why do women experience more pain than men biologically?
Women experience more pain than men due to differences at every level of the nervous system. Female nociceptors fire at lower stimulation thresholds. Oestrogen receptors in the brain, spinal cord, and peripheral nerves modulate pain signalling — amplifying it when hormone levels drop before menstruation. Female microglia are more reactive, driving neuroinflammation that sensitises pain pathways. These factors combine to produce a fundamentally more sensitive pain system.
Is it true that women have a lower pain tolerance than men?
The evidence is more nuanced than the popular narrative suggests. Women consistently show lower thresholds for pressure pain, electrical stimulation, and thermal pain in laboratory settings. However, when it comes to pain tolerance — the maximum pain a person can endure — the sex difference is smaller and varies by stimulus type. Women report pain more readily and describe it in more detail, which may reflect differences in reporting behaviour rather than raw tolerance.
Do hormones really cause women to feel more pain?
Yes, but the relationship is complex. Oestrogen can both increase and decrease pain sensitivity depending on concentration, receptor subtype, and location. The sharp drop in oestrogen before menstruation consistently lowers pain thresholds, which is why many women with chronic pain conditions flare perimenstrually. Testosterone appears to have a modest pain-protective effect, partly explaining why men report less pain at baseline.
Which chronic pain conditions affect women the most?
Fibromyalgia affects women at roughly nine times the rate of men, making it the most sex-skewed chronic pain condition. Migraine (~3:1), TMJ disorders (~4–6:1), rheumatoid arthritis (~3:1), and irritable bowel syndrome (~2–3:1) also disproportionately affect women. Endometriosis affects roughly one in ten women of reproductive age. Across all chronic pain diagnoses, women account for an estimated 55% to 70% of patients.
Why is women’s pain often dismissed by doctors?
The gender pain gap — the systematic underestimation and undertreatment of female pain — has both historical and contemporary causes. Historically, women’s pain was attributed to emotional instability under the now-abandoned diagnosis of “hysteria.” Today, studies show that both male and female observers rate female patients’ pain as less intense than male patients’ pain when viewing identical expressions of discomfort. Women in emergency departments wait longer for pain medication and are more likely to receive sedatives than analgesics. This bias is compounded for women of colour.
Can women do anything to reduce their pain sensitivity?
Yes. Tracking pain across the menstrual cycle can identify hormonal windows when pain is most severe, allowing your doctor to time treatments more effectively. Cognitive behavioural therapy (CBT) and mindfulness-based stress reduction (MBSR) reduce pain catastrophising — a major amplifier of pain perception — with effects particularly strong in women. Regular moderate exercise, good sleep hygiene, and anti-inflammatory dietary patterns also help. When these approaches are insufficient, asking for a referral to a pain medicine specialist or multidisciplinary pain clinic is the next step.
Do pain medications work differently in women?
Yes, and this is an underappreciated factor in why women experience more pain than men. Women metabolise many drugs differently due to body composition, liver enzyme activity, and hormonal influences on drug clearance. Opioids produce stronger analgesic effects in women at equivalent doses but also carry higher risks of side effects. Most pain medications were tested predominantly on male participants, meaning recommended doses may be suboptimal or excessive for female patients. Always discuss medication concerns with a doctor aware of sex-based pharmacological differences.
Is the pain difference between men and women getting smaller over time?
The biological differences underlying why women experience more pain than men have not changed. However, awareness of the gender pain gap is growing among healthcare professionals and the public, leading to improved clinical guidelines, better training on sex differences in pain, and more research funding directed toward female-specific pain mechanisms. The clinical response is slowly improving.
The Bottom Line
The question of why women experience more pain than men is not a single-answer puzzle. It is a combination of neurobiological wiring, hormonal modulation, immune-system reactivity, and a medical culture that — despite progress — still underestimates female pain.
The 2026 global study confirms higher pain prevalence in women across 11 body sites. It provides a powerful data point that can shift conversations — in clinics, in research committees, and in the public imagination — toward taking female pain seriously.
If you are a woman living with pain, the most important takeaway is this: your pain is real, it has biological underpinnings that science is actively untangling, and you deserve care that accounts for the specific way your body processes pain.
Advocate for yourself. Track your symptoms. Ask for the referral. Understanding why women experience more pain than men is a step toward treatments that actually work for the female body.
Medical Disclaimer
This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult a qualified healthcare professional regarding any medical concerns, symptoms, or before starting any new medication, supplement, or treatment programme. Do not ignore or delay seeking professional medical advice because of something you have read on this website. If you are experiencing a medical emergency, contact your local emergency services immediately.
Related Reading
- Women’s Health — Browse the full category
- NIH: Understanding Pain — National Institute of Arthritis and Musculoskeletal and Skin Diseases
- NIH MedlinePlus: Pain — Types, causes, and evidence-based treatments
- PubMed: Sex Differences in Pain Perception — Peer-reviewed research

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.