








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
type 2 diabetes remission diet and exercise — Type 2 Diabetes Remission with Diet and Exercise: What the 2026 Research Really Means. Read on for an evidence-backed guide covering everything you need to know.

Key Takeaways
- Type 2 diabetes remission — defined as HbA1c below 6.5% (48 mmol/mol) without glucose-lowering medication for at least 3 months — is achievable for many people, especially those diagnosed within the last 5 years.
- The landmark DiRECT trial showed that a low-energy total diet replacement (825-853 kcal/day for 3-5 months) produced remission in 46% of participants at 1 year — and 36% remained in remission at 2 years.
- New 2026 data from EASD shows that combining a low-energy diet with structured, supervised exercise boosts remission rates further, particularly in early-onset type 2 diabetes.
- The biological mechanism is now well understood: excess fat in the liver and pancreas impairs beta-cell function. Removing that fat — through calorie restriction AND exercise — can restore insulin production in many cases.
- Remission is not a cure. Weight regain brings the diabetes back. Long-term maintenance requires sustained dietary change, regular exercise, and periodic monitoring.
Type 2 diabetes remission diet and exercise — you have probably been told — by a well-meaning doctor, a family member, or the internet — that type 2 diabetes is a lifelong, progressive disease. And for decades, that was the standard teaching. Once you have it, the thinking went, you manage it. You take your metformin, maybe add a GLP-1, watch your HbA1c creep up over the years, and eventually move to insulin.
Type 2 diabetes remission diet and exercise — then came the DiRECT trial, and everything changed.
Type 2 diabetes remission diet and exercise — in 2018, a UK-based research team published results that shook the diabetes world: nearly half of participants with type 2 diabetes who followed a structured, low-energy diet for 3 to 5 months achieved full remission — normal blood glucose without any medication. The finding was so striking that the UK’s National Health Service began rolling out a nationwide remission programme based on the protocol.
Type 2 diabetes remission diet and exercise — now, 2026 data from the EASD conference adds a crucial new layer: combining that low-energy diet with structured exercise produces even higher remission rates, particularly in people diagnosed with early-onset type 2 diabetes.
By the end of this article, you will understand what type 2 diabetes remission diet and exercise actually requires — not the headlines, but the specifics: how many calories, what kind of exercise, who it works for, how long it lasts, and what happens to your medications along the way. The evidence for type 2 diabetes remission diet and exercise has matured to the point where national health services are building programmes around it.
Type 2 diabetes remission diet and exercise: What Does “Diabetes Remission” Actually Mean?
Type 2 diabetes remission diet and exercise — the word “remission” carries different meanings in different conditions, so let us define it precisely as the medical community does.
Quick Answer Box: Diabetes remission means your HbA1c stays below 6.5% (48 mmol/mol) for at least 3 months without any glucose-lowering medication. It is not a cure — the underlying metabolic vulnerability remains — but it means your blood sugar control is normal without drugs. This is distinct from “reversal,” which implies the condition is permanently gone, and from “well-controlled,” which means normal numbers on medication.
Type 2 diabetes remission diet and exercise — the American Diabetes Association formalised this definition in a 2021 consensus statement, establishing three categories: partial remission (HbA1c <6.5%, fasting glucose 100-125 mg/dL, for at least 1 year without medication), complete remission (HbA1c <5.7%, fasting glucose <100 mg/dL, for at least 1 year without medication), and prolonged remission (complete remission lasting at least 5 years).
Type 2 diabetes remission diet and exercise — here is what this means for you: remission is a measurable, evidence-backed state — not wishful thinking. Thousands of people in controlled trials have achieved it. The question is not whether type 2 diabetes remission diet and exercise can work; the question is whether the specific approach matches your specific situation. For those ready to commit, a structured type 2 diabetes remission diet and exercise programme offers a realistic path to normal blood glucose without medication.
How Does Diet and Exercise Reverse Type 2 Diabetes? — Type 2 diabetes remission diet and exercise Explained
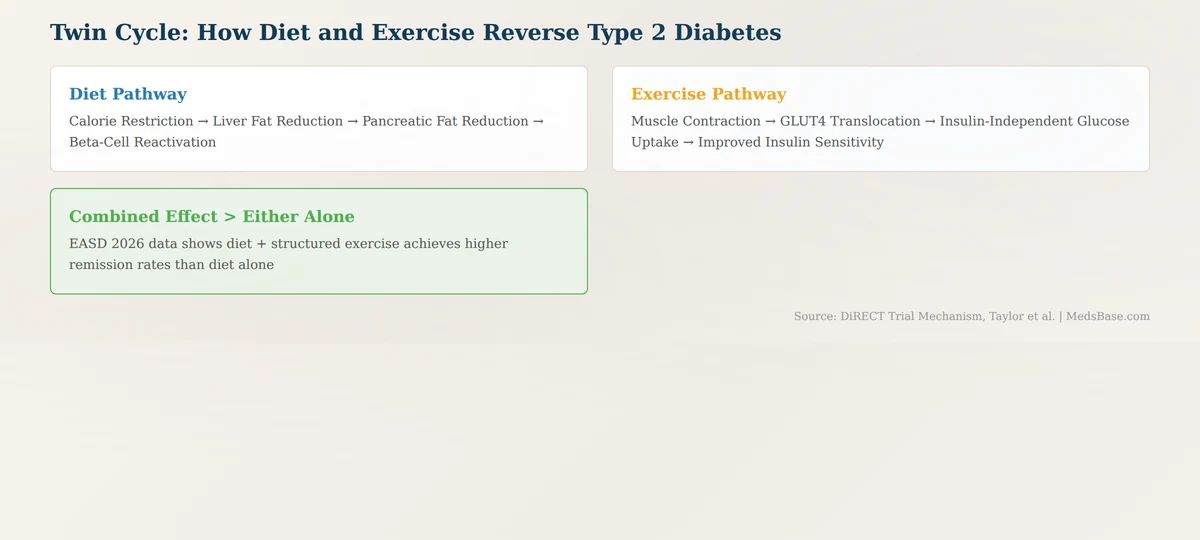
The biological mechanism underlying type 2 diabetes remission through diet and exercise is no longer mysterious. It centres on one organ, one tissue, and one hormone that gets its second chance.
The Twin Cycle Hypothesis Professor Roy Taylor and his team at Newcastle University proposed — and then proved — that type 2 diabetes is driven by excess fat accumulation in two places: the liver (Cycle 1) and the pancreas (Cycle 2). When you consume more energy than you burn over years, fat accumulates not just under your skin but inside your organs. In the liver, this causes insulin resistance — your liver keeps pumping out glucose even when it should not. In the pancreas, the fat infiltrates the insulin-producing beta cells, impairing their ability to secrete insulin in response to rising blood sugar.
The critical insight from Taylor’s work is that this process is reversible. When you create a substantial energy deficit — through a very low-calorie diet, significant exercise, or ideally both — the body begins to burn its internal fat stores. Liver fat drops within days. Pancreatic fat drops within weeks. And as the ectopic fat clears, beta-cell function can recover — sometimes fully.
Research Spotlight: The DiRECT trial’s mechanistic arm used MRI scans to track what happened inside participants’ bodies as they lost weight. The findings were striking: liver fat fell by approximately 30% within the first week of the low-energy diet, and pancreatic fat decreased progressively over the 8-week intervention period. Beta-cell function — measured by first-phase insulin response — improved in direct proportion to the amount of weight lost, with the biggest improvements seen in those who lost 15 kg (33 lbs) or more.
Where exercise fits in The diet component clears the ectopic fat. The exercise component does something different but complementary. When your muscles contract during exercise, they pull glucose from the bloodstream through a pathway (GLUT4 translocation) that does not depend on insulin. This is why even a single bout of moderate exercise can lower blood glucose for hours afterward — the muscles are acting as a glucose sink independent of whatever is happening with your insulin signalling.
The American Diabetes Association consensus on the topic notes that combining calorie restriction with exercise produces greater improvements in insulin sensitivity than either intervention alone. The exercise does not just burn calories; it remodels muscle tissue at the cellular level, increasing mitochondrial density and improving the muscle’s ability to oxidise fat — which, in turn, reduces the ectopic fat accumulation that drives the disease.
Take the combined approach: diet clears the liver and pancreas, exercise improves peripheral glucose disposal and prevents fat from re-accumulating. This is why the 2026 EASD finding — that adding structured exercise to a low-energy diet significantly boosts remission rates — makes biological sense. It is not magic; it is two complementary mechanisms working on the same problem from different angles.
Type 2 diabetes remission diet and exercise: Who Is a Candidate for Diabetes Remission?
Type 2 diabetes remission diet and exercise is not for everyone — but the people it works for are more numerous than most patients and even some doctors realise. The strongest predictors of success come from the DiRECT trial and subsequent real-world programmes. Approaching type 2 diabetes remission diet and exercise with realistic expectations and medical support is the difference between a clinical-trial result and a personal disappointment.
Q: Who Is This For?
A: – People diagnosed with type 2 diabetes within the last 5 years. The shorter the duration, the less cumulative damage to beta cells, and the more likely they are to recover function when ectopic fat is cleared. In DiRECT, remission rates were highest among those with diabetes duration under 4 years. – Individuals with a BMI of 27 or higher. The mechanism is fat-driven; if you carry excess weight, you have the substrate to lose — and the biological leverage to reverse the process. – People who are motivated and supported. Remission requires sustained behavioural change. In the DiRECT trial, participants had regular visits with a dietitian or nurse. Real-world programmes that include structured support — coaching, group sessions, digital tracking — consistently outperform solo attempts. – Those without advanced complications. If you have established diabetic kidney disease, advanced neuropathy, or proliferative retinopathy, the risks of rapid weight loss and intensive exercise shift. It does not mean remission is impossible, but it requires much closer medical supervision.
Q: Who Should Be Cautious?
A: – Individuals with diabetes duration over 10 years. Beta-cell function may have declined beyond the point of recovery — though some data shows even long-duration patients can achieve remission with substantial weight loss, the probability drops. – People who are lean at diagnosis (BMI <25). This is a different subtype of type 2 diabetes, often driven more by genetic beta-cell dysfunction than by ectopic fat. Remission through weight loss is less applicable here. Exercise may still help, but the evidence is weaker. – Anyone taking insulin or sulfonylureas. These medications can cause hypoglycaemia if food intake drops suddenly. Tapering must be managed by a healthcare provider — never self-adjust insulin doses during a low-energy diet. – Individuals with a history of eating disorders. A structured low-energy diet can trigger restrictive-eating patterns in vulnerable individuals. The NHS Type 2 Diabetes Path to Remission programme explicitly screens for eating-disorder history before enrollment.
Contextual product mention: If you are exploring type 2 diabetes remission diet and exercise alongside medication management, MedsBase offers a range of diabetes medications that may be part of your tapering conversation with your provider. Browse the Diabetes category to understand your options.
What the Evidence Says
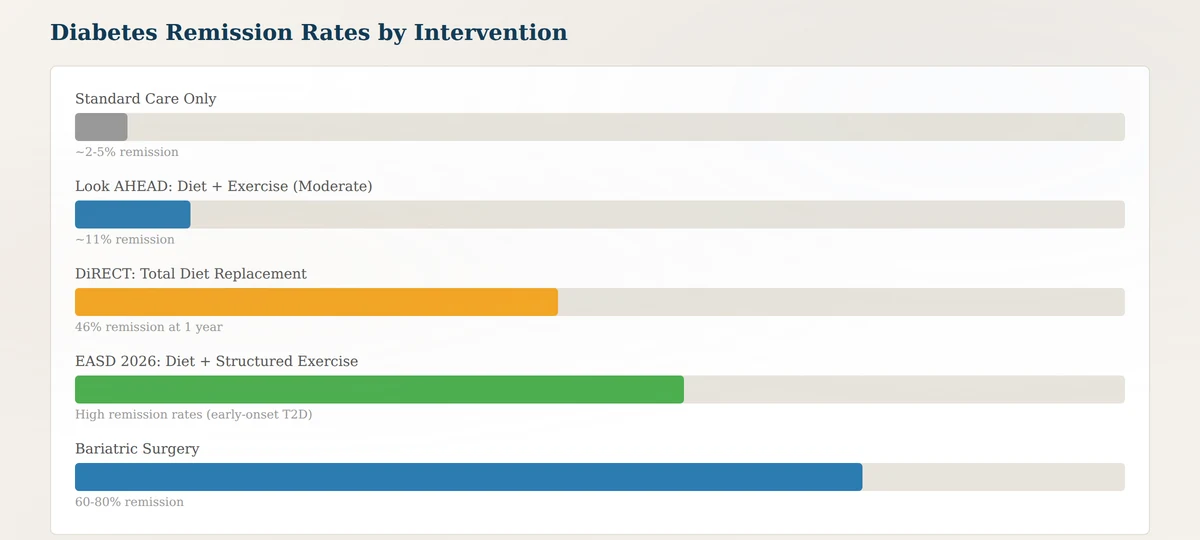
The evidence base for diabetes remission has grown from a landmark trial to a robust programme of research. Here is what the major studies tell us, including the newest 2026 data.
Research Summary Table
| Study / Programme | Year | Intervention | Remission Rate | Key Detail |
|---|---|---|---|---|
| DiRECT (UK) | 2018 | Total diet replacement (825-853 kcal/day, 3-5 months) + food reintroduction + maintenance support | 46% at 1 year; 36% at 2 years | Higher remission with >15 kg weight loss (86% of those who lost >15 kg achieved remission) |
| DiRECT extension | 2024 | Same protocol, 5-year follow-up | ~25% sustained at 5 years | Weight regain was the main predictor of relapse |
| Look AHEAD (US) | 2013 | Intensive lifestyle intervention (diet + 175 min/week exercise) | ~11% partial remission at 1 year | Less aggressive calorie restriction than DiRECT; more emphasis on exercise |
| EASD 2026 Combined Intervention | 2026 | Low-energy diet + structured supervised exercise in early-onset T2D | High remission rates (exact figures presented at EASD) | Adding structured exercise to low-energy diet improved outcomes significantly; presented at EASD 2026 |
| Bariatric surgery meta-analysis | 2020 | Roux-en-Y gastric bypass or sleeve gastrectomy | 60-80% remission at 1-2 years | Most effective but invasive; reserved for BMI ≥35 with comorbidities |
What this means for you: The DiRECT trial provides the strongest evidence that a structured, supervised low-energy diet can put type 2 diabetes into remission — and a growing number of programmes now offer type 2 diabetes remission diet and exercise as a first-line treatment option rather than a last resort — and the 5-year data shows that maintenance is possible but requires continued effort. The 2026 EASD data suggests that adding structured exercise to the dietary intervention raises the ceiling — particularly for people with early-onset diabetes, who may have the most beta-cell reserve to recover.
The gap between DiRECT’s 46% remission and Look AHEAD’s 11% is instructive: it reflects the difference between an aggressive, medically supervised total diet replacement and a more moderate lifestyle programme. Remission is dose-dependent: the more weight you lose, and the faster you lose it, the more likely your beta cells are to recover. But the faster approach also requires more medical supervision because of medication adjustment and the risk of hypoglycaemia.
Diet Approaches Compared
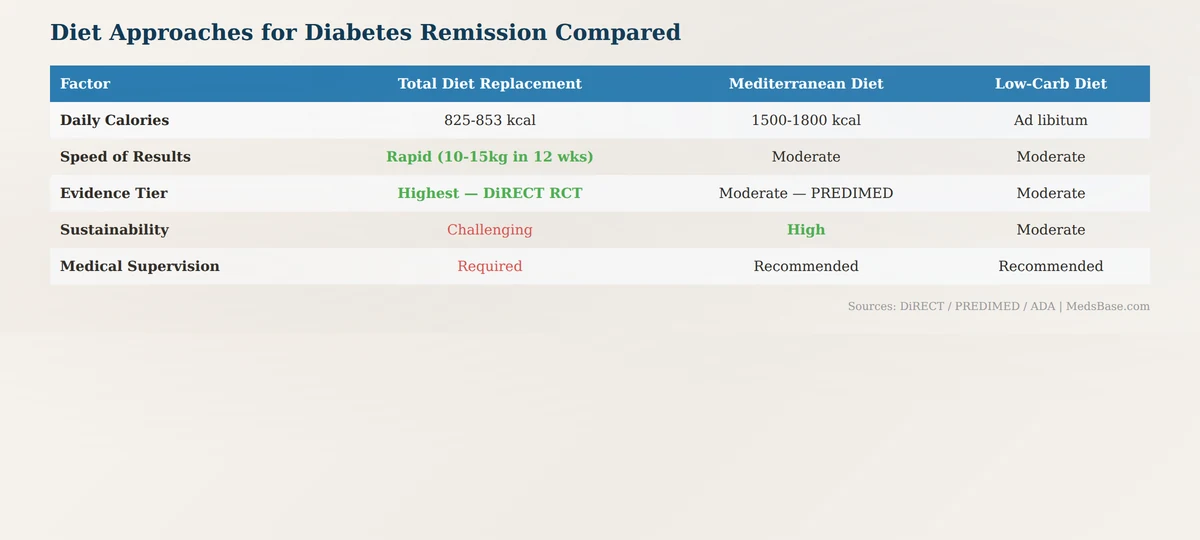
There is no single “remission diet.” Three evidence-backed approaches exist, each with different trade-offs.
| Feature | Total Diet Replacement (DiRECT-style) | Mediterranean Diet | Low-Carbohydrate Diet (<130g/day) |
|---|---|---|---|
| Daily calories | 825-853 kcal (formula-based) | 1500-1800 kcal | Ad libitum (no calorie counting) |
| Composition | Balanced macronutrients in liquid formula | 40% carbs, 40% fat, 20% protein | <130g carbs, moderate protein, higher fat |
| Speed of weight loss | Rapid (10-15 kg in 12 weeks) | Moderate (0.5-1 kg/week) | Variable (depends on spontaneous calorie reduction) |
| Evidence tier | Highest — DiRECT RCT | Moderate — PREDIMED + general cardiovascular data | Moderate — multiple RCTs show HbA1c improvement; remission data less robust |
| Sustainability | Challenging — requires transition to real food | High — flexible, culturally adaptable | Moderate — restrictive but allows satiating foods |
| Medical supervision | Required — medication adjustment essential | Recommended | Recommended |
| Best for | Motivated individuals with recent diagnosis who want rapid results | People who want a sustainable, heart-healthy lifestyle change | People who struggle with hunger on calorie-restricted diets |
Which approach fits which situation? If your goal is remission and you are within 5 years of diagnosis with a BMI over 27, the total diet replacement approach — done under medical supervision — offers the highest probability. But if the idea of drinking formula for 3 months feels unsustainable, the Mediterranean diet produces meaningful, durable improvements in blood glucose, even if complete remission is less likely. The low-carbohydrate approach can be a strong compromise — particularly for people who find calorie restriction difficult — but the remission evidence specifically is thinner than for total diet replacement.
The Exercise Prescription

Exercise alone rarely produces remission. But exercise combined with dietary change? That is where the 2026 data gets interesting.
Structured exercise for a type 2 diabetes remission diet and exercise programme should include three components — each of which contributes to the metabolic improvements that make remission possible:
1. Aerobic exercise — 150+ minutes per week The standard recommendation — 150 minutes of moderate-intensity aerobic activity per week — is the floor, not the ceiling. The EASD 2026 combined-intervention programme used supervised exercise sessions of 45-60 minutes, 3-4 times per week, including brisk walking, cycling, or swimming at a heart-rate target of 60-75% of maximum. This volume reliably improves insulin sensitivity and cardiovascular fitness. Start where you are: if you currently do zero exercise, 10-minute walks after meals are an evidence-backed starting point that directly lowers post-meal glucose spikes.
2. Resistance training — 2 sessions per week Muscle is the largest glucose-disposal tissue in the body. Two sessions of resistance exercise per week — using body weight, resistance bands, free weights, or machines — increase muscle mass and improve insulin-independent glucose uptake. Compound movements (squats, push-ups, rows, lunges) that engage multiple muscle groups produce the greatest metabolic benefit per minute. Start with 1-2 sets of 8-12 repetitions per exercise at a weight where the last 2 repetitions are challenging but doable.
3. Daily movement — reduce sitting time Prolonged sitting independently worsens insulin resistance, even in people who exercise. Breaking up sitting time with 2-3 minute movement breaks every 30-60 minutes — a walk to the kitchen, standing while on a phone call, light stretching — improves post-meal glucose handling. A practical target: fewer than 8 hours of sitting per day, with movement breaks every hour.
The key from the 2026 EASD data is that the exercise must be structured and consistent — not “I walk when I feel like it.” The supervised programme component matters because adherence to independent exercise drops steeply without accountability. If you cannot access a supervised programme, use a fitness tracker, schedule sessions like appointments, or exercise with a partner to replicate the accountability effect.
How to Start: A Step-by-Step Plan
Pursuing type 2 diabetes remission diet and exercise is a significant undertaking — but one that thousands of people have successfully navigated in structured clinical programmes. Here is a framework for starting safely. The key to success with type 2 diabetes remission diet and exercise is medical supervision from day one.
Step 1: Get baseline labs Before changing anything, know your starting point: HbA1c, fasting glucose, lipid panel, kidney function (eGFR, urine albumin-to-creatinine ratio), and liver function. These are your objective markers — they tell you whether the approach is working and provide safety monitoring. If you are on glucose-lowering medication, also check your medication list and discuss with your provider the tapering plan BEFORE beginning calorie restriction.
Step 2: Choose your dietary approach Pick one of the three evidence-backed approaches from the comparison table above. Total diet replacement is the highest-efficacy path but requires medical supervision. Mediterranean offers sustainability. Low-carb is a middle ground. Whatever you choose, commit to it for at least 12 weeks — jumping between approaches undermines adherence and makes it hard to know what is working.
Step 3: Build your exercise routine Week 1-2: 10-15 minute walks after meals. Week 3-4: increase to 20-30 minute walks plus 1 resistance session. Week 5-8: 30-45 minute aerobic sessions 3-4x/week + 2 resistance sessions. Week 9-12: 45-60 minute sessions + progressive resistance overload. The ramp-up prevents injury and builds the habit before the intensity.
Step 4: Monitor and adjust medications This is the non-negotiable step. As your calorie intake drops and your weight decreases, your blood glucose will fall — sometimes rapidly. If you are taking sulfonylureas (glipizide, glyburide, glimepiride) or insulin, the risk of hypoglycaemia is real. Your provider should reduce these medications proactively as you start the programme. Metformin, SGLT2 inhibitors, and GLP-1 receptor agonists are generally safer to continue during calorie restriction but may also need adjustment as weight loss progresses. Never self-adjust insulin or sulfonylureas.
Step 5: Maintain and prevent relapse This is the hardest part — and the reason only about 25% of DiRECT participants remained in remission at 5 years. Weight regain is the primary driver of relapse. After the initial weight-loss phase, transition to a maintenance diet that is sustainable and satisfying — Mediterranean-style eating is the most studied and arguably the most liveable. Continue exercise at the maintenance volume (150+ minutes aerobic, 2x resistance per week). Get your HbA1c checked every 3-6 months. If it starts to rise, act early — a brief return to calorie restriction can pull it back before medications become necessary again.
Second contextual product mention: During your remission journey, you may still need medication support — and if weight regain occurs, having affordable access to your previous medications matters. Explore MedsBase’s Diabetes collection to understand the options available if and when medication becomes part of your plan again.
Related Reading
- GLP-1 Medications Beyond Weight Loss: Liver, Heart, and Brain Benefits — How GLP-1 drugs fit into a comprehensive metabolic health strategy
- Increasing Ozempic Dose vs Switching to Mounjaro: A Clinical Decision Guide — Today’s companion post: if remission through lifestyle alone is not your path, here is how to optimise your medication approach
- Metformin Gastrointestinal Side Effects: What Helps and What Does Not — Practical guidance for the most common diabetes medication
Frequently Asked Questions
Q: Can type 2 diabetes go into remission?
A: Yes, and the evidence is robust. The DiRECT trial — a randomised controlled trial published in The Lancet — demonstrated that 46% of participants achieved remission at 1 year using a structured low-energy diet. A 2026 EASD study extended this finding by showing that adding structured exercise to the dietary intervention further improves remission rates, particularly in early-onset type 2 diabetes. Remission is defined as HbA1c below 6.5% without medication for at least 3 months.
Q: How much weight do you need to lose to reverse diabetes?
A: The DiRECT trial showed a clear dose-response relationship: the more weight lost, the higher the chance of remission. Of participants who lost more than 15 kg (33 lbs), 86% achieved remission at 1 year. Even losing 5-10% of body weight significantly improves insulin sensitivity and blood glucose control, though full remission becomes more likely above 10-15% weight loss. The critical threshold appears to be about 15 kg, regardless of starting weight.
Q: What diet is best for diabetes remission?
A: The strongest evidence supports total diet replacement (825-853 kcal/day using formula meal replacements for 3-5 months), which produced the highest remission rates in the DiRECT trial. Less aggressive approaches — Mediterranean diet and low-carbohydrate diet — produce meaningful improvements in blood glucose but have not been shown to match total diet replacement’s remission rates in controlled trials. The best diet is ultimately the one you can adhere to: a total diet replacement that you abandon after 2 weeks is worse than a Mediterranean diet you sustain for years.
Q: How long does diabetes remission last?
A: Remission is durable as long as weight loss is maintained. DiRECT’s 5-year follow-up showed that approximately 25% of participants sustained remission, with weight regain being the primary predictor of relapse. Think of it this way: the metabolic vulnerability does not disappear — the beta-cell impairment was caused by fat, and fat can re-accumulate. People who kept the weight off stayed in remission. People who regained weight saw their blood glucose rise again.
Q: Can exercise alone reverse diabetes?
A: Exercise alone rarely produces full remission because it does not generate the magnitude of weight loss needed to clear ectopic fat from the liver and pancreas. However, exercise independently improves insulin sensitivity, lowers blood glucose acutely, and reduces cardiovascular risk. The 2026 EASD data shows that exercise significantly boosts remission rates when combined with dietary intervention — but exercise alone, without substantial calorie reduction, is unlikely to achieve remission in most people.
Q: What happens to medications during diabetes remission?
A: As your weight drops and blood glucose normalises, your healthcare provider should taper your glucose-lowering medications. Metformin is often continued during the weight-loss phase and stopped once HbA1c stabilises below the diabetic range. Sulfonylureas and insulin MUST be reduced proactively — continuing full doses during calorie restriction can cause dangerous hypoglycaemia. GLP-1 receptor agonists and SGLT2 inhibitors may be tapered gradually. The key: medication adjustment during a type 2 diabetes remission diet and exercise programme is a medical decision, not a do-it-yourself task. Anyone pursuing type 2 diabetes remission diet and exercise must work with a provider who can safely adjust medications as blood glucose normalises.
Q: Is diabetes remission the same for everyone?
A: No. Duration of diabetes is the strongest predictor: people diagnosed within 5 years have the highest chance. BMI matters: those with more weight to lose have more biological leverage. Age matters: younger people tend to have greater beta-cell reserve. Genetics matters: some people have a form of type 2 diabetes driven more by beta-cell dysfunction than by ectopic fat, and they respond less dramatically to weight loss. And the presence of complications matters: if kidney disease, neuropathy, or retinopathy are advanced, the risk-benefit calculus shifts.
Q: What is the EASD 2026 combined intervention study?
A: Presented at the European Association for the Study of Diabetes 2026 conference, this study combined a low-energy diet with structured, supervised exercise in patients with early-onset type 2 diabetes. The key finding: the combined approach produced higher remission rates than dietary intervention alone. The structured exercise component — supervised sessions 3-4 times per week — appeared to be the differentiating factor. Full publication is pending, but the topline data were widely reported at the EASD 2026 conference and covered by multiple health news outlets in early October 2026.
The Bottom Line
Type 2 diabetes remission diet and exercise is not a headline — it is a medical reality backed by randomised controlled trials, mechanistic studies, and now 2026 data showing that the combined approach outperforms diet alone. The growing body of evidence for type 2 diabetes remission diet and exercise has changed how leading health systems approach diabetes care, moving from indefinite medication management to remission as a treatment goal. The DiRECT trial proved that nearly half of people with type 2 diabetes can achieve remission through aggressive calorie restriction. The 2026 EASD data shows that adding structured exercise moves that number higher.
Verdict: If you were diagnosed with type 2 diabetes within the last 5 years and carry excess weight, remission is a realistic goal — not a long shot. The path requires 3-5 months of disciplined calorie restriction (800-900 kcal/day under supervision), 150+ minutes per week of structured exercise, and medication tapering managed by your healthcare provider. After remission, lifelong maintenance — sustainable eating, regular exercise, and periodic HbA1c checks — is essential.
Your next step: Schedule a conversation with your healthcare provider. Bring the DiRECT trial data. Ask about supervised low-energy diet programmes available in your area. Get your baseline labs drawn. And then decide whether a structured type 2 diabetes remission diet and exercise programme — with all the commitment it demands — is the right move for you right now. For those who are ready, a type 2 diabetes remission diet and exercise approach offers something that medication alone cannot: the possibility of normal blood glucose without drugs.
What to read next:
- Wondering how GLP-1 medications fit into the remission picture, or whether they can help you lose the weight that triggers remission? Read: GLP-1 Medications Beyond Weight Loss: Liver, Heart, and Brain Benefits
- If remission through lifestyle alone is not your path, and you are weighing medication options, today’s companion post can help: Increasing Ozempic Dose vs Switching to Mounjaro
Medical Disclaimer: This article is for informational purposes only and does not constitute medical advice. Pursuing diabetes remission through diet and exercise — particularly any programme involving severe calorie restriction — must be done under medical supervision. Never adjust or discontinue diabetes medications without consulting your healthcare provider. Hypoglycaemia can be life-threatening.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.