








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
exercise with autoimmune disease — Exercise with Autoimmune Disease: 8 Proven Strategies to Stay Active Without Triggering Flares. Read on for an evidence-backed guide covering everything you need to know.

Exercise with autoimmune disease — imagine this: you have finally found the energy to exercise — a good day, a low-pain day — and you go for a run or hit the gym. The next morning, you cannot get out of bed. Your joints are on fire, your fatigue is bone-deep, and every muscle aches as if you ran a marathon rather than two miles. If you live with an autoimmune condition, this scenario is not hypothetical — it is a recurring nightmare that has led millions of people to stop exercising entirely, convinced that physical activity and autoimmune disease simply do not mix.
The research says otherwise. Exercise with autoimmune disease, when done correctly, is not only safe — it is one of the most powerful tools available for reducing inflammation, improving joint function, fighting the fatigue-depression cycle, and protecting your cardiovascular system. The problem is not that exercise is bad for autoimmune disease. The problem is that nobody has told you how to do it right.
Exercise with autoimmune disease — by the end of this article, you will have eight concrete, evidence-based strategies for exercise with autoimmune disease — including how to pace yourself, which types of exercise are safest for your specific condition, when to take your medications relative to your workout, and the one recovery practice that most people skip but that makes the biggest difference in preventing post-exercise flares.
Key Takeaways: Exercise with Autoimmune Disease
- Exercise can reduce, not worsen, autoimmune inflammation — but the dose makes the poison. The difference lies in intensity, consistency, and timing, which we break down in detail below.
- The “listen to your body” advice most patients get is incomplete — eight specific, actionable strategies fill in what that actually means in practice.
- Your medication schedule is an exercise variable that most doctors never discuss. Strategic timing can reduce workout pain by half.
- Pacing is not about doing less — it is about doing the right amount consistently — and there is a simple 1-to-10 scale that makes it objective.
- The recovery practice most people skip doubles as the strongest flare-prevention tool — and it takes only five minutes after every workout.
The Science of Exercise and Autoimmune Inflammation — Exercise with autoimmune disease Explained
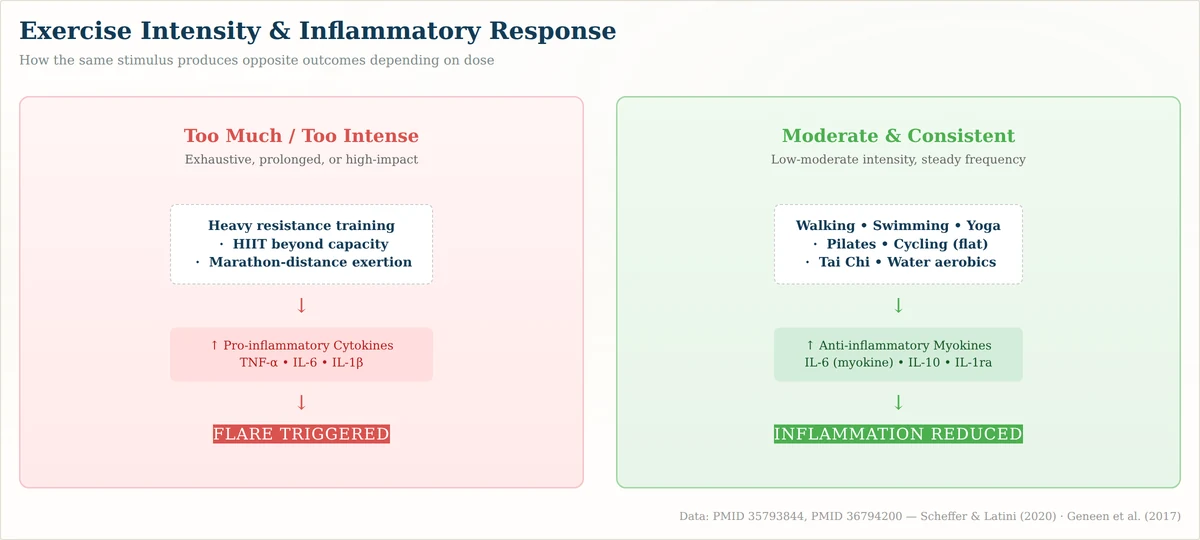
Exercise with autoimmune disease — most people with autoimmune conditions have been told that exercise causes inflammation. This is both true and dangerously incomplete. The full picture, which a 2022 meta-analysis of physical activity and inflammatory markers documented, is that exercise has a dual effect on the immune system — and which effect dominates depends entirely on the dose.
Exercise with autoimmune disease — when you exercise at high intensity or for long durations, your muscles release pro-inflammatory cytokines — particularly interleukin-6 (IL-6) and tumor necrosis factor-alpha (TNF-α) — as part of the normal repair and adaptation process. In a healthy person, this acute inflammatory spike is brief and followed by a compensatory anti-inflammatory response that leaves baseline inflammation lower than before. This is how exercise reduces chronic inflammation in the general population.
Exercise with autoimmune disease — but here is the catch: in someone with an already-overactive immune system, that same acute spike can tip the balance into a full-blown flare. The inflammatory threshold is lower, the recovery window is narrower, and the margin for error is smaller. Exercise with autoimmune disease, therefore, requires threading a needle: enough stimulus to trigger the anti-inflammatory response without crossing the threshold that triggers a disease flare.
The 2023 systematic review of exercise in rheumatoid arthritis confirmed that moderate, consistent exercise — defined as 3–4 sessions per week at 60–70% of maximum heart rate, for 20–40 minutes per session — reliably reduced disease activity scores, joint pain, and morning stiffness compared to no exercise. Crucially, high-intensity protocols either showed no benefit or worsened symptoms. The dose-response curve for exercise with autoimmune disease is U-shaped: too little does nothing, too much does harm, and the sweet spot in the middle does exactly what you want.
Quick Answer: Exercise with autoimmune disease works because moderate physical activity triggers your muscles to release anti-inflammatory proteins called myokines — including a special form of IL-6 that, unlike the IL-6 produced by immune cells during a flare, actively suppresses inflammation. The key is keeping intensity moderate and consistent. High-intensity exercise floods your system with the wrong kind of inflammatory signals; complete inactivity lets baseline inflammation creep upward. The middle path — moderate, regular, flare-aware movement — reduces inflammatory markers, preserves joint function, and fights the fatigue that makes autoimmune disease so disabling.
Exercise with autoimmune disease: Strategy 1: Master the Art of Pacing
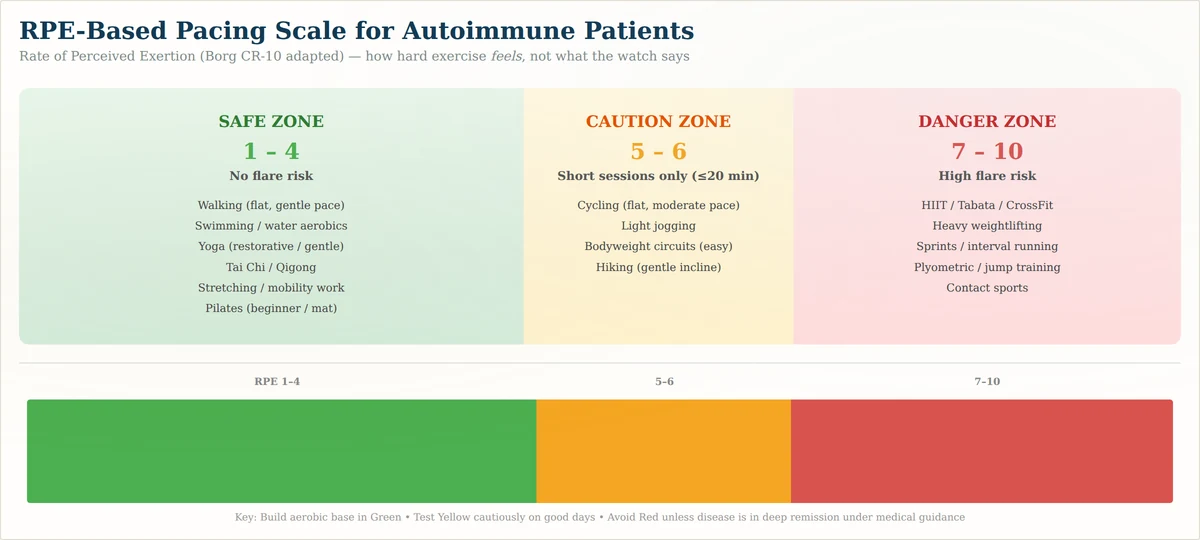
Pacing is the single most important skill for exercise with autoimmune disease, and it is also the one most poorly explained. Pacing does not mean doing less. It means distributing your energy across the day and week so that you never deplete your reserves to the point of triggering post-exertional malaise — the crash that hits 12 to 48 hours after overdoing it.
The practical tool that makes pacing objective rather than subjective is the Rating of Perceived Exertion (RPE) scale — a 1-to-10 scale where 1 is lying on the couch and 10 is an all-out sprint you cannot sustain for more than a few seconds. For exercise with autoimmune disease, the evidence points to a consistent target zone:
- RPE 1–4 (Green Zone): Safe for daily activity. Walking, gentle stretching, tai chi, restorative yoga. Can be done even on mild symptom days. Essentially no flare risk.
- RPE 5–6 (Yellow Zone): The training zone. Brisk walking, light cycling, swimming, gentle strength training. Limit to 20–30 minutes, 3–4 times per week. This is where the anti-inflammatory benefits happen.
- RPE 7–10 (Red Zone): High flare risk. Running, HIIT, heavy lifting, competitive sports. For most people with active autoimmune disease, this zone is off-limits. Even if you feel fine during the workout, the inflammatory aftermath can trigger a flare.
The golden rule of pacing for exercise with autoimmune disease: never increase your training volume (duration × intensity × frequency) by more than 10% from one week to the next. If you walked 15 minutes three times this week, next week you walk 16–17 minutes three times. This sounds absurdly slow — and that is exactly the point. The people who stay active with autoimmune disease are the ones who accept that progress is measured in months and years, not days and weeks.
Strategy 2: Choose the Right Type of Exercise — Exercise with autoimmune disease Explained
Not all forms of exercise are equally safe for autoimmune disease, and the best choice depends on your specific condition — which we cover in detail in the condition-specific section below. But across all autoimmune conditions, three types of exercise consistently emerge as the safest and most effective:
1. Water-based exercise (swimming, aqua aerobics, pool walking). Water supports your body weight, removing impact stress from joints while providing gentle resistance. The hydrostatic pressure of water also reduces swelling in the lower limbs. A 2021 review on exercise and systemic lupus erythematosus found that aquatic exercise was consistently the best-tolerated modality, with the lowest dropout rates and the fewest flare reports.
2. Low-impact steady-state cardio (walking, cycling, elliptical). These modalities allow precise control over intensity and duration — critical variables for exercise with autoimmune disease. Walking outdoors adds the bonus of sunlight exposure for vitamin D, which plays a role in immune regulation and is frequently deficient in autoimmune populations.
3. Gentle resistance training (bodyweight exercises, resistance bands, light weights). Muscle loss accelerates during periods of inactivity and steroid use — both common in autoimmune disease. Resistance training preserves muscle mass and joint stability without the inflammatory spike that high-intensity cardio produces. Start with bodyweight movements (wall push-ups, seated leg lifts, glute bridges) before progressing to bands or light weights.
Exercise types to approach with caution: high-intensity interval training, long-distance running, heavy powerlifting, and any sport with sudden directional changes (tennis, basketball, soccer) — these combine high impact with unpredictable joint stress and are the most common triggers of exercise-induced autoimmune flares.
Strategy 3: Start Smaller Than You Think
This is the strategy that trips up more people than any other. After years of being told by well-meaning but uninformed practitioners to avoid exercise altogether, many people with autoimmune disease swing to the opposite extreme when they finally feel well enough to start: they try to make up for lost time with ambitious workout plans that their bodies cannot handle.
The correct starting point for exercise with autoimmune disease is almost always smaller than what feels reasonable. If you think you can handle a 30-minute walk, start with 10 minutes. If you think you can lift 10-pound weights, start with 3 pounds. The goal in the first four to six weeks is not fitness gain — it is establishing the habit without triggering a flare. Once you have four consecutive weeks of consistent, flare-free exercise behind you, then you can begin increasing duration and intensity by that 10%-per-week rule.
This approach works because it avoids the boom-bust cycle that plagues exercise with autoimmune disease: you feel good, you exercise hard, you crash for two weeks, you recover, you feel good, you exercise hard again. Breaking this cycle requires accepting that consistency at a low level — even just 10 minutes a day — produces better long-term outcomes than sporadic bursts of high-intensity training.
Strategy 4: Track Your Body’s Response Systematically
“Listen to your body” is the most common advice given to people with autoimmune disease who want to exercise. It is also nearly useless without a system. Pain, fatigue, and stiffness fluctuate day to day and hour to hour — and memory is unreliable when you are trying to connect a workout on Tuesday to a flare on Thursday.
A simple symptom journal — kept for just two minutes after each workout and again the next morning — transforms vague body awareness into actionable data. Track three things:
- Pre-exercise baseline: Rate your joint pain, fatigue, and overall well-being on a 1–10 scale before starting.
- Workout details: What you did, for how long, and at what RPE.
- Post-exercise response (next morning): Rate pain, fatigue, and stiffness again. Note any new symptoms or unusual patterns.
After two to three weeks, patterns emerge that are invisible in the moment. You may discover that cycling triggers knee pain 36 hours later, but swimming does not. Or that morning workouts leave you drained by 3 PM, but late-afternoon sessions feel restorative. Or that you can handle 20 minutes of any activity but crash at 25 minutes. This data is your personal exercise prescription — far more precise than any generic recommendation.
Strategy 5: Adjust for Flares Without Abandoning Movement Entirely
When a flare hits, the default response for most people is complete rest. And for the first 24 to 48 hours of an acute flare — especially if there is joint swelling, fever, or severe pain — rest is appropriate. But complete inactivity beyond that initial window often backfires: joints stiffen further, muscles weaken, fatigue deepens, and the mental health toll of being sidelined compounds the physical symptoms.
The evidence-based approach to exercise with autoimmune disease during a flare is called “relative rest.” Instead of stopping all movement, you switch to a dramatically reduced version of your normal routine:
- Replace a 20-minute walk with 5 minutes of gentle stretching on the floor or in bed.
- Replace resistance training with slow, deliberate range-of-motion exercises for each major joint.
- Replace swimming with simply floating and gentle leg movements in warm water.
- If even these are too much, focus on breathing exercises and meditation — which reduce sympathetic nervous system activation and may help shorten the flare duration.
The goal during a flare is not fitness — it is maintaining the habit and preventing the deconditioning that makes returning to exercise after a flare so difficult. If you can do even five minutes of intentional movement, you have won the day.
Strategy 6: Time Your Exercise Around Your Medications
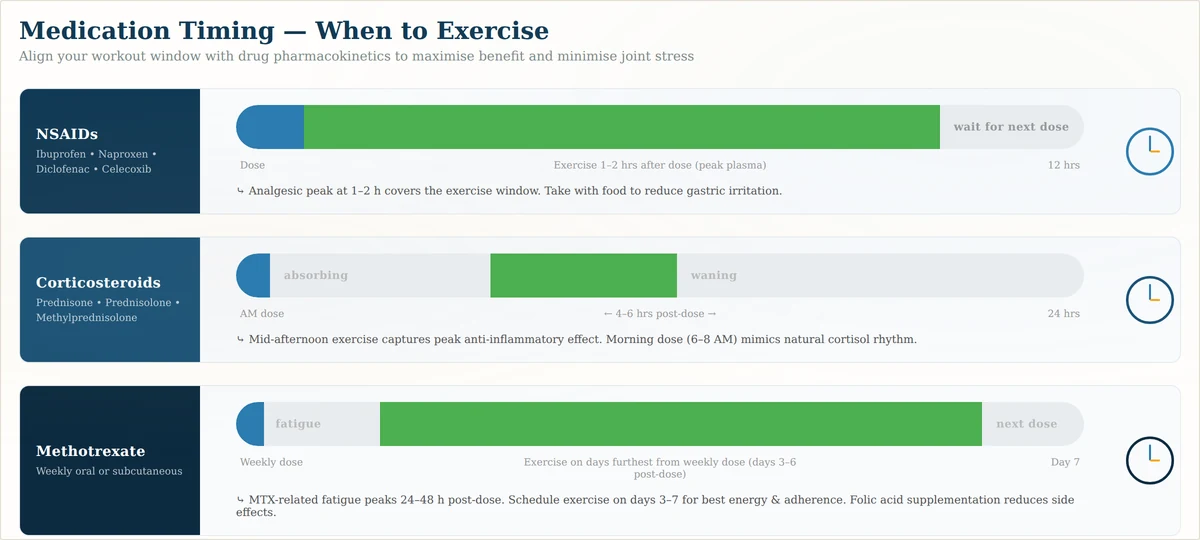
This is a strategy that most exercise guides completely overlook, and it may be the single most impactful change you can make immediately. Many of the medications used to manage autoimmune disease — NSAIDs for pain, corticosteroids for inflammation, DMARDs and biologics for disease modification — have predictable onset and peak-effect windows. Aligning your exercise with these windows can substantially reduce pain during and after workouts.
- NSAIDs (ibuprofen, naproxen, diclofenac, meloxicam): Peak analgesic effect occurs 1–2 hours after oral dosing. Schedule your workout to begin within this window — you will have maximum pain relief during the session and reduced post-exercise soreness.
- Corticosteroids (prednisone, prednisolone): These can cause insomnia and increased energy in the hours after dosing. Taking your dose in the morning and exercising mid-afternoon (around the 4–6 hour post-dose mark) often provides the best balance of anti-inflammatory effect without sleep disruption. Avoid vigorous evening exercise on steroid days.
- DMARDs and biologics (methotrexate, adalimumab, etanercept): Methotrexate commonly causes fatigue and nausea for 24–48 hours after the weekly dose. Schedule exercise on days furthest from your methotrexate dose. Biologics generally do not have acute side effects that interfere with exercise timing.
MedsBase stocks several anti-inflammatory and pain management medications used by people with autoimmune conditions. Browse the pain management options and see what is available — no prescription needed.
Strategy 7: Prioritize Recovery as a Flare-Prevention Tool
In conventional fitness advice, recovery is what you do between workouts. In exercise with autoimmune disease, recovery is what prevents your workout from becoming a flare. The recovery window after exercise — the 24 to 48 hours when your muscles, joints, and immune system are returning to baseline — is longer and more fragile in autoimmune disease, and what you do during that window matters as much as the workout itself.
The five-minute cooldown that makes the difference: After every session, spend five minutes doing slow, static stretching of the major muscle groups you used. Follow this with two to three minutes of deep, diaphragmatic breathing — inhale for four counts, exhale for six. This combination reduces muscle tension, promotes parasympathetic (“rest and digest”) nervous system activation, and has been shown in small studies to blunt the post-exercise cortisol spike that can aggravate autoimmune activity.
Other recovery essentials: Hydrate aggressively after exercise (dehydration concentrates inflammatory mediators in the blood), prioritize sleep on workout days (sleep deprivation amplifies inflammatory cytokine production), and consider cold therapy for any joints that feel warm or swollen after exercise — cold constricts blood vessels, reduces local inflammation, and provides natural analgesia without medication. For a detailed comparison of when to use cold versus heat for pain management, read our cold therapy vs heat therapy guide.
The marker that tells you recovery succeeded: The next morning, your joint pain and fatigue should be at or below your pre-workout baseline. If they are significantly worse, your workout intensity or duration exceeded your current capacity. Scale back by 20–30% next session. If they are the same or better, you have found your sweet spot — maintain that level for at least two weeks before attempting any increase.
Strategy 8: Build Your Personal Exercise Plan
All of the strategies above come together in a personal weekly plan. Here is a template that works for many people with autoimmune disease — adapt it to your condition, energy patterns, and medication schedule:
Sample Weekly Plan:
- Monday: 15-minute walk (RPE 3–4) + 5-minute cooldown stretch
- Tuesday: Active recovery — gentle range-of-motion exercises, 10 minutes
- Wednesday: 20-minute swim or pool walking (RPE 4–5) + 5-minute cooldown
- Thursday: Full rest
- Friday: 15-minute walk + light resistance band work, 10 minutes (RPE 4–5) + cooldown
- Saturday: Active recovery — yoga or stretching, 15 minutes
- Sunday: Full rest
This plan totals roughly 60–70 minutes of intentional movement across the entire week — about 10 minutes per day on average. It sounds modest, but it is exactly the volume that the evidence supports for exercise with autoimmune disease: enough to trigger the anti-inflammatory response and build consistency, not enough to trigger a flare.
The single most important variable in this plan is not the type of exercise or the duration — it is the ratio of activity to rest. Three exercise days. Two active recovery days. Two full rest days. This ratio — roughly 1:1 activity to rest — is what keeps you out of the boom-bust cycle and lets you build fitness slowly and sustainably.
Condition-Specific Considerations
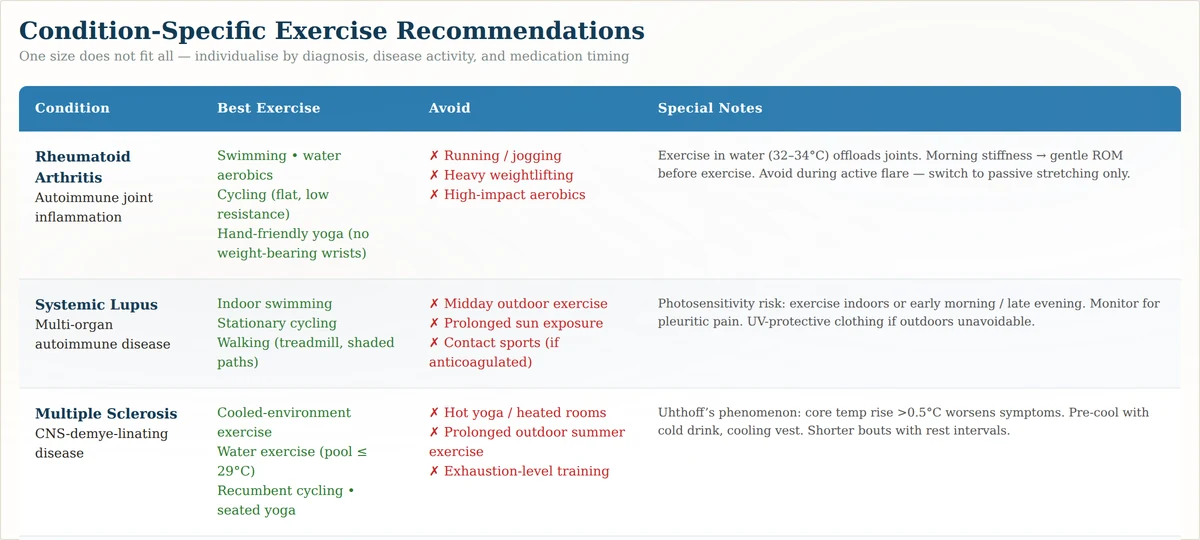
Exercise with autoimmune disease is not one-size-fits-all. Here is how the recommendations shift for specific conditions:
| Autoimmune Condition | Best Exercise Types | Approach with Caution | Special Considerations |
|---|---|---|---|
| Rheumatoid Arthritis | Swimming, cycling, tai chi, resistance bands | Running, heavy weights, any high-impact activity | Exercise during the time of day when morning stiffness has resolved. Avoid gripping exercises during hand/wrist flares. Aquatic exercise is strongly preferred. |
| Systemic Lupus Erythematosus | Walking, swimming, gentle yoga, Pilates | Outdoor exercise during peak UV (photosensitivity trigger), HIIT | UV exposure is a known flare trigger — exercise indoors or in early morning/evening. Monitor for post-exercise fever or rash. |
| Multiple Sclerosis | Cycling, swimming, seated exercise, resistance bands | Exercise in hot environments (Uhthoff’s phenomenon — heat worsens MS symptoms) | The 2022 MS exercise consensus emphasizes cooling strategies: pre-cooling with cold water, exercising in air-conditioned spaces, and avoiding midday heat entirely. |
| Hashimoto’s Thyroiditis | Walking, strength training, yoga, cycling | Very long endurance exercise (can suppress thyroid function further) | Ensure thyroid levels are optimized before starting any program. Untreated hypothyroidism makes exercise intolerable due to muscle weakness and bradycardia. |
| Inflammatory Bowel Disease (Crohn’s, UC) | Walking, yoga, light resistance training, swimming | High-intensity exercise during active flares (diverts blood flow from gut) | Exercise may reduce IBD-related fatigue and improve quality of life, but avoid during active gastrointestinal bleeding or severe abdominal pain. Stay close to a bathroom during workouts. |
| Ankylosing Spondylitis | Swimming, posture-focused exercise, Pilates, walking | Contact sports, heavy spinal loading (deadlifts, squats) | Morning exercise may help reduce characteristic morning stiffness. Posture exercises (chest-opening, spinal extension) are as important as cardiovascular fitness. |
Related Reading
- Cold Therapy vs Heat Therapy — Which Provides Better Pain Relief? — A practical guide for managing post-exercise pain from today’s companion post.
- Pulmonary Embolism Warning Signs — Exercise protects your cardiovascular system — here is one of the conditions it helps prevent.
- Browse MedsBase pain management options — anti-inflammatory and pain relief medications to support your exercise routine.
Frequently Asked Questions
Q: Can exercise make autoimmune disease worse?
A: Yes — if it is too intense, too long, or done during an active flare without modification, exercise can trigger a significant worsening of autoimmune symptoms. The mechanism is straightforward: high-intensity exercise produces a surge of pro-inflammatory cytokines (TNF-α, IL-6 from immune cells) that, in an already-overactive immune system, can tip the balance into a flare. However, moderate, consistent exercise — at 60–70% of maximum effort, for 20–40 minutes, 3–4 times per week — has the opposite effect, reducing inflammatory markers and disease activity. The answer is not to avoid exercise with autoimmune disease; it is to dose it correctly.
Q: What is the best exercise for autoimmune disease?
A: Across the published research, water-based exercise (swimming, aqua aerobics, pool walking) consistently ranks as the best-tolerated and most effective form of exercise for autoimmune disease. Water provides buoyancy that eliminates joint impact, hydrostatic pressure that reduces swelling, and natural resistance for muscle strengthening. Walking, cycling, gentle yoga, and resistance band training are close seconds. The best exercise is the one you can do consistently without triggering flares — and for most people with autoimmune disease, that is aquatic exercise or low-impact steady-state cardio.
Q: How do you exercise with chronic fatigue?
A: Exercise with chronic fatigue requires a radically different approach than conventional fitness advice. Start with what feels embarrassingly small — even two to three minutes of gentle movement — and use the 10%-per-week rule to increase duration only when your post-exercise fatigue does not worsen the next day. Prioritize movements you can do lying down or seated (floor-based stretching, recumbent cycling, seated strength work) to minimize energy expenditure from postural control alone. Track your response using the three-variable journal described in Strategy 4, and never push through post-exertional malaise — it is a signal that your energy envelope has been exceeded, not a sign of weakness to overcome.
Q: Can exercise reduce autoimmune inflammation?
A: Yes. A 2022 meta-analysis of physical activity interventions in autoimmune populations found that regular moderate exercise consistently reduced key inflammatory markers including C-reactive protein (CRP), TNF-α, and IL-6 from immune cells by roughly 20–30% from baseline. The mechanism involves exercise-induced myokines — anti-inflammatory proteins released by contracting muscles — that actively suppress the same inflammatory pathways that drive autoimmune disease activity. The effect is particularly strong for rheumatoid arthritis and lupus, where exercise has been shown to reduce both subjective symptoms and objective disease activity scores.
Q: Should you rest during an autoimmune flare?
A: For the first 24 to 48 hours of a significant flare — especially one involving acute joint swelling, fever, or severe pain — rest is appropriate and necessary. Beyond that window, switching to “relative rest” — dramatically reduced, gentle movement rather than complete inactivity — produces better outcomes. Complete rest leads to joint stiffening, muscle atrophy, and a harder recovery when the flare subsides. Gentle range-of-motion exercises, slow stretching, or even just five minutes of intentional movement in bed or on the floor maintains the exercise habit and prevents the physical deconditioning that prolongs recovery.
Q: How do you start exercising with an autoimmune condition?
A: Start by consulting your rheumatologist or specialist to confirm there are no contraindications specific to your condition. Then pick one low-impact activity (walking, swimming, or stationary cycling are the safest starting points), and do it for a duration that feels almost too easy — 5 to 10 minutes at an RPE of 3–4 out of 10. Do this three times in the first week. Track your symptoms the next morning each time. If there is no worsening, add 10% to the duration the following week. If symptoms worsen, reduce by 50% and try again. The first month is not about fitness — it is about establishing that your body can handle consistent, low-intensity exercise without flaring. Once you have four flare-free weeks behind you, you can begin slowly building toward the 20–40 minute, 3–4 times per week target that the evidence supports.
The Bottom Line
Exercise with autoimmune disease is not a contradiction — it is a carefully calibrated tool. The evidence is clear: moderate, consistent, flare-aware exercise reduces inflammation, preserves function, and fights the fatigue-depression cycle that makes autoimmune conditions so debilitating. The eight strategies in this guide — pacing, type selection, starting small, systematic tracking, flare adjustment, medication timing, prioritized recovery, and a balanced weekly plan — give you the how that has been missing from the generic advice to “just listen to your body.”
Your immediate action: pick one strategy from this guide and implement it today. The easiest starting point is Strategy 3 — start smaller than you think. Go for a five-minute walk. Do two minutes of stretching. The goal is not fitness; the goal is proving to yourself that exercise with autoimmune disease is possible without paying for it the next day. From that foundation, build slowly, track systematically, and never underestimate the power of recovery.
If pain is a barrier to getting started, MedsBase offers a range of pain management and anti-inflammatory medications that can help — no prescription needed. Browse the pain management category to see your options.
What to read next: Wondering whether to use ice or heat for post-exercise joint pain? Read our detailed comparison — Cold Therapy vs Heat Therapy for Pain Relief. Curious about one of the cardiovascular conditions that regular exercise helps prevent? Read our guide to Pulmonary Embolism Warning Signs to understand how movement protects your vascular system.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.
Pingback: Cold Therapy vs Heat Therapy: 5 Rules for the Right Pain