








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
hormone therapy menopause brain fog — Hormone Therapy for Menopause Brain Fog and Mood — Does It Work? 8 Key Comparisons. Read on for an evidence-backed guide covering everything you need to know.

You walk into the kitchen to grab your reading glasses, and by the time you reach the counter you have forgotten what you came for. You lose your keys three times a week. In meetings, the word you want is right there — on the tip of your tongue — and then it is gone, mid-sentence, while four colleagues wait politely. Someone has probably told you, with a smile that lands like dismissal, that “it’s just menopause, it’ll pass.” But it has not passed, and you are done being patient.
Here is the part that matters: hormone therapy menopause brain fog is not a myth, and it is not “all in your head.” New research published in October 2026 reports that hormone therapy can measurably improve the memory lapses, fogginess, and low mood that so many women hit hard during perimenopause and early menopause. The real questions are subtler — which type, how soon, at what trade-off, and whether you even need hormones at all to feel like yourself again.
By the end of this guide, you will be able to compare estrogen-only against combined therapy, bioidentical against conventional, and hormone therapy against the non-hormonal alternatives — with realistic timelines and honest risks. When you sit down with your doctor, you will know exactly what to ask.
Key Takeaways
- New research (Oct 2026) reports that hormone therapy menopause brain fog and low mood respond to treatment — it is not “just menopause”
- Estrogen supports the brain through three pathways: glucose metabolism, neurotransmitter regulation (serotonin, dopamine, acetylcholine), and cerebral blood flow
- Timing matters: the “critical window” hypothesis suggests starting HT within 10 years of menopause yields better cognitive outcomes than starting later
- Brain fog typically improves more slowly than hot flushes — often weeks 4–12, so realistic expectations prevent premature quitting
- You do not need hormones to see relief: SSRIs/SNRIs, cognitive behavioral therapy, and lifestyle changes are evidence-backed alternatives
- The risks of hormone therapy menopause brain fog treatment are real but small for most women starting in their 50s — a doctor conversation is essential
Table of Contents
- What Is Menopause Brain Fog?
- How Does Hormone Therapy Menopause Brain Fog Relief Work?
- Hormone Therapy Menopause Brain Fog: 8 Essential Comparisons
- Hormone Therapy Menopause Brain Fog: Types and How Fast They Work
- Who Is Hormone Therapy Right For?
- Non-Hormonal Alternatives for Menopause Brain Fog
- What Does the Research Say?
- How to Talk to Your Doctor About Hormone Therapy for Brain Fog
- Frequently Asked Questions
- The Bottom Line
What Is Menopause Brain Fog?
Menopause brain fog is the cluster of cognitive symptoms — short-term memory lapses, difficulty finding words, reduced focus and concentration, and a general feeling of mental sluggishness — that many women report as estrogen levels decline during perimenopause and menopause. It is commonly described as a “cotton-wool” feeling in the head. While it is not a formal medical diagnosis, it is a real and frequently reported experience, and it is one of the symptoms most strongly associated with the hormonal changes of the menopause transition.
Studies suggest up to two-thirds of women going through the menopause transition report some degree of cognitive difficulty, with word-finding problems and short-term memory complaints among the most common. For many, the symptoms are temporary and improve as the body adapts to its new hormonal state. For others, they persist and meaningfully affect work performance and confidence.
How Does Hormone Therapy Menopause Brain Fog Relief Work?

To understand why hormone therapy menopause brain fog treatment can work, it helps to understand what estrogen actually does in the brain. Estrogen is not only a reproductive hormone — it is a neuroactive hormone with direct effects on the regions that govern memory, attention, and mood. When estrogen levels drop, several brain processes can falter at once:
1. Glucose metabolism. The brain runs almost entirely on glucose, and estrogen enhances the brain’s ability to take up and metabolise that fuel. When estrogen falls, regions such as the prefrontal cortex and hippocampus — which are central to working memory and short-term recall — can become metabolically sluggish, contributing to that “foggy” feeling.
2. Neurotransmitter regulation. Estrogen modulates key neurotransmitters. It supports serotonin (mood, emotional wellbeing), dopamine (motivation, focus, and reward), and acetylcholine (attention, learning, and memory). A decline in estrogen can disrupt all three, which is why brain fog and low mood often arrive together.
3. Cerebral blood flow. Estrogen is a mild vasodilator that supports healthy blood flow to the brain. Reduced cerebral circulation can leave the brain feeling underpowered precisely when the demand for cognitive effort is highest.
By restoring estrogen levels, hormone therapy aims to re-stabilise these three systems. This is also why the effect is gradual rather than instant: the brain is not being “stimulated” like a stimulant would; it is being supplied with a hormone it had been missing, and the downstream systems take time to rebalance. The NHS describes hormone replacement therapy as replacing the hormones your body no longer produces, which can relieve a wide range of symptoms — including, for many women, the cognitive ones.
Importantly, when women report that hormone therapy menopause brain fog improvement came on slowly, they are describing the biology accurately. Rebalancing glucose metabolism, neurotransmitter tone, and blood flow is not an overnight switch.
Hormone Therapy Menopause Brain Fog: 8 Essential Comparisons
Choosing whether to pursue hormone therapy menopause brain fog treatment means weighing eight distinct decisions. Here they are, one at a time.
1. Estrogen-Only vs Combined (Estrogen + Progestogen)
The single biggest fork in the road is whether you take estrogen alone or in combination. Estrogen-only therapy (ET) is usually reserved for women who have had a hysterectomy, because unopposed estrogen raises the risk of endometrial (womb-lining) cancer. Combined hormone therapy (EPT) — estrogen plus a progestogen — protects the lining and is the standard for women who still have a uterus. From a brain-fog standpoint, estrogen is the primary active ingredient for cognition, but the progestogen component matters for sleep and can have its own (mildly sedating, sometimes mood-influencing) effects. Your uterine status determines which path is medically available to you.
2. Oral vs Transdermal
Oral estrogen passes through the liver first, which raises clotting factors and carries a small but real increased risk of blood clots (deep vein thrombosis and pulmonary embolism). Transdermal estrogen (patches, gels, sprays) bypasses the liver and is associated with a lower clot risk, making it a common first choice for women who are older, overweight, or have cardiovascular concerns. For brain fog, both deliver estrogen to the brain; the difference is primarily about cardiovascular safety rather than cognitive efficacy.
3. Early Start vs Late Start (The “Critical Window” Hypothesis)
This is the comparison that shapes outcomes most. The critical-window hypothesis proposes that estrogen is most protective for the brain when started early — roughly within 10 years of menopause or before the mid-50s-60s — while brain cells still respond robustly to the hormone. Starting hormone therapy years or decades later appears to offer less cognitive benefit and, in some studies, may even be associated with harm. If brain fog is your primary concern and you are recently menopausal, timing is on your side; if you are well past menopause, the risk-benefit maths shifts.
4. Bioidentical vs Conventional
Bioidentical hormones are chemically identical to the body’s own hormones; conventional HT may use synthetic or other non-identical compounds. In regulated, pharmaceutical-grade forms, bioidentical estradiol and progesterone are well studied and are, for many clinicians, the default. The caution around “bioidentical” — and specifically around custom-compounded bioidentical therapy — is that compounded products are not regulated for the same consistency and dosing precision as licensed products. The “safer” reputation of bioidentical hormones is not supported by strong evidence that they are actually lower-risk than conventional licensed HT; what matters more is standardisation and dosing.
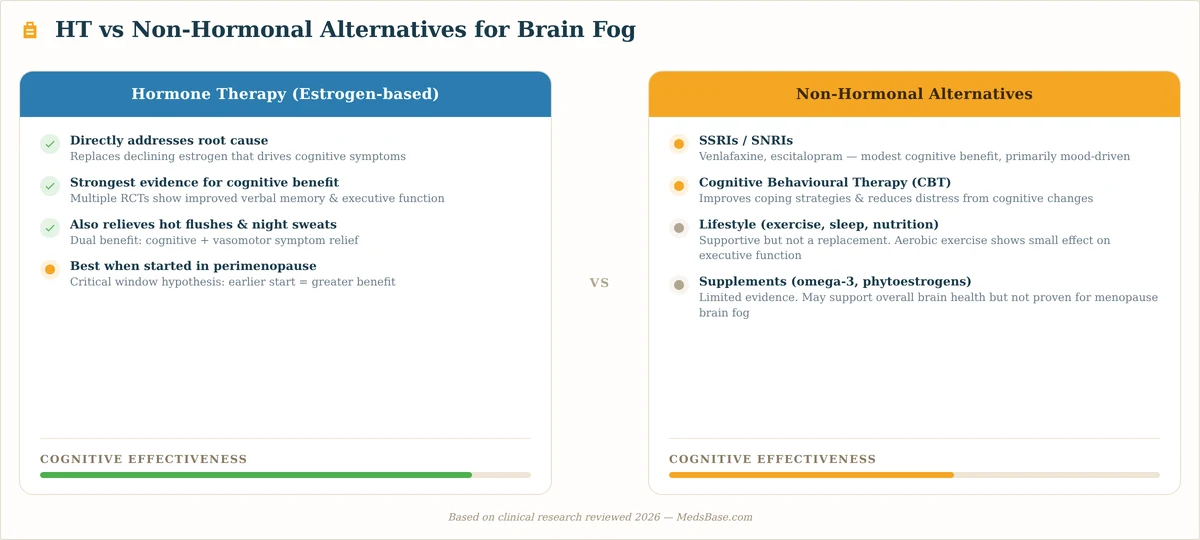
5. HT vs Antidepressants (SSRIs/SNRIs) for Mood
For the mood component — irritability, tearfulness, feeling flat — hormone therapy and antidepressants are both evidence-based but work differently. Hormone therapy addresses the hormonal root cause; SSRIs/SNRIs (such as sertraline, fluoxetine, or venlafaxine) alter serotonin and norepinephrine signalling directly. For women whose mood symptoms are strongly linked to hot flushes and sleep loss, HT may resolve mood by resolving those drivers. For women with a history of depression or whose mood symptoms dominate, an antidepressant may be the faster, more targeted lever. These two are not mutually exclusive — they are sometimes used together under specialist guidance.
6. HT vs Lifestyle for Cognition
Lifestyle interventions are the quiet underdog of the brain-fog conversation. Regular aerobic exercise, strength training, prioritised sleep, stress reduction, and a Mediterranean-style diet have genuine, trial-supported effects on cognition — without any hormonal side effects. For a woman with early, mild brain fog, a structured lifestyle programme may be a perfectly reasonable first step. Hormone therapy tends to shine when symptoms are more disruptive or when lifestyle measures have not been enough.
7. Short-Term vs Long-Term Use
The evidence and guidelines generally favour using the lowest effective dose for the shortest needed duration. Short-term HT (on the order of a few years) to bridge the menopause transition carries a favourable risk profile for most women starting in their 50s. Long-term use changes the calculus because the small increases in risks (notably a modest rise in breast-cancer diagnosis with long-term combined therapy) accumulate over time. Brain fog specifically tends to improve within the first year, so many women do not need indefinite therapy to address cognition.
8. Brain Fog Benefit vs Other Benefits (Bone, Sleep, Heart)
The final comparison is about perspective. Hormone therapy menopause brain fog relief does not exist in isolation — hormone therapy also helps with hot flushes, night sweats, sleep, bone-density preservation, and genitourinary symptoms. When you weigh whether HT is “worth it” for brain fog alone, remember that the same intervention may simultaneously be protecting your bones and restoring your sleep. Conversely, if brain fog is your only symptom, non-hormonal options may carry a cleaner risk-benefit picture.
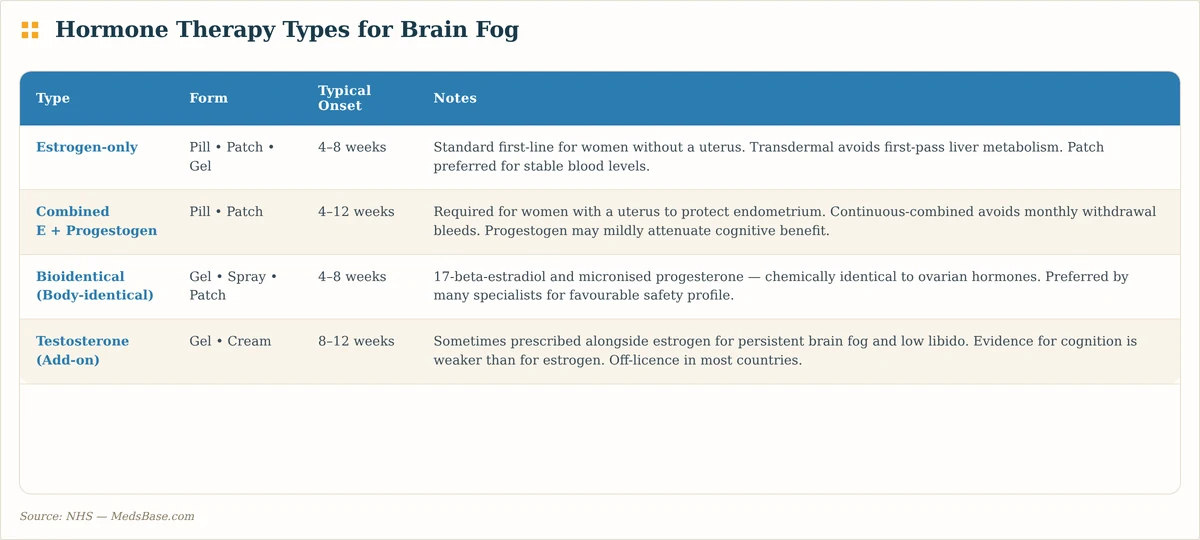
Hormone Therapy Menopause Brain Fog: Types and How Fast They Work
The single question women ask most is not will it work but when. The honest answer for hormone therapy menopause brain fog is that it is slower than you hope and faster than many people expect — and slow enough that women commonly quit before the benefit appears. Here is a realistic timeline, organised by therapy type:
| Hormone Therapy Type | Typical Onset for Brain Fog | Notes |
|---|---|---|
| Estrogen-only (transdermal or oral) | Often 4–12 weeks | Mood shifts can come first (weeks 1–4); memory and word-finding tend to follow |
| Combined estrogen + progestogen | Often 4–12 weeks | Sleep improvements from progestogen may aid cognition indirectly; some women feel sedated at first |
| Bioidentical estradiol (licensed) | Similar, 4–12 weeks | Timeline depends on dose and route, not on the “bioidentical” label itself |
| Low-dose / local preparations | Limited for cognition | Vaginal/local estrogen targets genitourinary symptoms; systemic brain effects are minimal |
Two practical implications fall out of this table. First, do not judge hormone therapy after two weeks. The systems that produce brain fog are rebalanced over weeks to months, and quitting early is the most common reason women conclude “HT did not work for my brain.” Second, hot flushes and sleep often improve first, and better sleep alone can lift a surprising amount of the fog — so part of the cognitive benefit may be indirect.
If you are weighing your options and want to compare specific hormone formulations, our guide to estriol vs estradiol walks through the estrogen types in detail.
Who Is Hormone Therapy Right For?
Hormone therapy menopause brain fog treatment is not a universal prescription. The women most likely to benefit from it, and to do so safely, share a few characteristics:
- They are in perimenopause or early menopause — ideally within 10 years of their final period, consistent with the critical-window hypothesis
- Their brain fog is moderate to severe and is measurably affecting work, relationships, or quality of life
- They have other troublesome menopausal symptoms (hot flushes, sleep disruption, mood changes) for which HT is also indicated
- They are under 60 and generally in good cardiovascular health, without a history of hormone-sensitive cancer
Who Should Avoid Hormone Therapy — Or Proceed With Caution
- Women with a history of breast, endometrial, or ovarian cancer, or unexplained vaginal bleeding
- Women with a personal history of blood clots, stroke, or heart attack, or uncontrolled high blood pressure — for whom transdermal estrogen and close monitoring are usually favoured over oral
- Women with active liver disease
- Women who are well past menopause (roughly age 60+ or more than 10 years since the last period), where the risk-benefit balance shifts
- Pregnant women, or those with a confirmed pregnancy
This list is not exhaustive, and your personal risk depends on your full medical history. The decision to start hormone therapy for menopause brain fog must be individualised with a clinician.
If cardiovascular safety is a central concern for you, read our breakdown of menopause hormone therapy and cardiovascular disease for a deeper, evidence-based look at timing and risk.
Non-Hormonal Alternatives for Menopause Brain Fog

Not everyone wants — or is able — to take hormones. Fortunately, non-hormonal menopause brain fog treatment is a genuine, evidence-backed category, not a consolation prize. Three approaches stand out:
1. Antidepressants (SSRIs/SNRIs)
For mood-driven brain fog and the irritability that can accompany it, SSRIs and SNRIs are a first-line non-hormonal option. They do not directly replicate estrogen’s cognitive support, but by stabilising mood and (in the case of certain SNRIs such as venlafaxine) reducing hot flushes, they can indirectly clear a significant share of the mental haze — and they are unrelated to any cancer risk.
2. Cognitive Behavioral Therapy (CBT)
CBT for menopause helps women reframe unhelpful beliefs about their symptoms, manage stress, and build practical strategies for memory and organisation — externalising the load that a foggy brain struggles to hold. It also improves sleep and mood. CBT carries zero pharmacological risk and is supported by a growing body of menopause-specific evidence.
3. Lifestyle: Exercise, Sleep, Diet, Stress
This is the option with the broadest evidence base relative to its safety. Regular aerobic exercise improves cerebral blood flow and promotes neuroplasticity; strength training supports overall metabolic health; consistent sleep protects memory consolidation; and a Mediterranean-style eating pattern has been associated with better cognitive aging. Managing stress — where mindfulness practices and adequate social support help — reduces the cortisol load that can worsen cognitive symptoms. For many women, a committed 8–12 week lifestyle programme produces noticeable improvement on its own.
The honest framing: for some women, lifestyle and psychological interventions will be enough. For others, they will complement — not replace — hormone therapy menopause brain fog treatment. The two are not rivals so much as different points on the same spectrum.
What Does the Research Say?
The evidence base around hormone therapy menopause brain fog has matured considerably in the last two decades, and the picture is clearer than the headlines sometimes suggest. Here is what the key studies actually found:
| Study / Source | Year | Finding on Cognition & Mood |
|---|---|---|
| Healthline news report on HT & brain fog/mood | Oct 2026 | Reports that hormone therapy can improve menopause-related brain fog and mood changes, based on new research |
| WHI — Women’s Health Initiative (estrogen + progestin arm) | 2002 | The large landmark trial did not find cognitive benefit in older women starting HT late; risks of combined long-term therapy were highlighted and reshaped prescribing |
| KEEPS — Kronos Early Estrogen Prevention Study | 2012 | In recently menopausal women, starting HT early showed a more neutral-to-positive cognitive and mood profile than the older-WHI cohort, supporting the critical-window concept |
| Estrogen & prefrontal glucose-metabolism studies | 2000s | Found estrogen modulates glucose utilisation in brain regions governing memory and executive function, providing a biological basis for brain-fog relief |
| NHS menopause guidance | ongoing | Confirms hormone replacement therapy is an effective treatment for menopausal symptoms and describes the conditions under which it is recommended, with risks that vary by preparation |
What this means for you: The evidence supports two firm conclusions. First, hormone therapy menopause brain fog relief is real and biologically plausible — the mechanism is well established, and a growing body of research confirms that hormone therapy can improve both mood and cognitive symptoms during the menopause transition. Second, timing is everything. The disappointing early cognitive findings came largely from older women starting HT late; the more encouraging signals come from women starting early. If you are at or near menopause and brain fog is disrupting your life, the current evidence leans in favor of a conversation with your doctor rather than resignation.
For the formal, landmark data that reshaped how clinicians think about hormone therapy and cognition, the Women’s Health Initiative findings on pubmed remain the foundational reference.
How to Talk to Your Doctor About Hormone Therapy for Brain Fog
“Just menopause” is not a treatment plan. If brain fog is hurting your life, you deserve a real conversation — and the difference between a dismissive appointment and a productive one is often preparation. Here is how to approach it:
- Name the specific, objective impact. Instead of “I feel foggy,” say “I lose words mid-sentence in meetings, I forget appointments unless they are in my phone, and it is affecting my performance review.” Concrete detail is harder to wave away.
- Bring your symptom timeline. When did the fog start, and does it track with your periods, hot flushes, or sleep? A clear link to the menopause transition strengthens the case that hormones are involved.
- State your goals up front. “I want to understand whether hormone therapy menopause brain fog treatment is an option for me, and what my risks would be” — this frames the conversation around a decision, not a vague complaint.
- Ask the five key questions:
- Is my brain fog most likely hormonal, or should we rule out other causes first?
- Which type of hormone therapy — estrogen-only or combined, oral or transdermal — fits my age and risk factors?
- What timeline should I realistically expect for my memory and mood?
- What are my specific risks given my personal and family history?
- When should we reassess, and what non-hormonal options should I consider alongside or instead?
- Know your “must-rule-out” list. Thyroid dysfunction, B12 or vitamin D deficiency, sleep apnoea, iron deficiency, and depression can all masquerade as brain fog. A good clinician will want to rule these out — and so should you.
If your clinician is unwilling to engage, seeking a second opinion — ideally from a menopause specialist or a practitioner with specific training in the menopause transition — is a reasonable and increasingly common step.
Frequently Asked Questions
Does hormone therapy help with menopause brain fog?
Yes — for many women it does. Hormone therapy menopause brain fog relief is supported both by biology (estrogen supports brain glucose metabolism, neurotransmitters, and blood flow) and by recent reporting, including a Healthline study summary in October 2026. The benefit is not universal or instant, and it is strongest for women who start treatment relatively early in the menopause transition. Realistic expectation-setting is key: most women who respond notice meaningful change over weeks to months, not days.
How long does it take for HRT to improve brain fog?
Most of the time, hormone therapy menopause brain fog improvement is measured in weeks rather than days. Mood shifts can appear in the first one to four weeks; memory, word-finding, and focus typically improve over roughly 4 to 12 weeks. Some women report faster change, others slower, and a minority feel no clear cognitive difference at all. The most common mistake is quitting after two weeks — which is usually too soon to judge.
What is the best hormone therapy for menopause mood swings?
There is no single “best” across the board, but a few patterns hold. Estrogen is generally the more important hormone for mood in the menopause transition, so its steady delivery via transdermal route (patch or gel) is a common and well-tolerated starting point. For women whose mood swings are driven primarily by sleep loss and hot flushes, treating those drivers with any well-matched HT often resolves the mood symptoms. For women with a history of depression, an SSRI/SNRI may be the more targeted choice — and the two approaches can be combined. The “best” option is the one matched to your individual symptoms and risk profile.
Can you treat menopause brain fog without hormones?
Yes. Non-hormonal menopause brain fog treatment is a legitimate category. Cognitive behavioral therapy (CBT) builds practical memory and organisation strategies; SSRIs/SNRIs address the mood component; and an 8–12 week programme of aerobic exercise, strength training, prioritised sleep, and a Mediterranean-style diet has genuine evidence behind it. Many women manage mild-to-moderate brain fog entirely without hormones, and these approaches also layer well alongside HT if you choose it later.
Is brain fog during menopause permanent?
For most women, no. Menopause brain fog tends to be worst during the perimenopausal transition and the first year or two after the final period, then improves as the brain adapts to its new, lower-estrogen state. Some women do continue to notice persistent word-finding or memory lapses, which is exactly when exploring hormone therapy menopause brain fog options — or the non-hormonal alternatives — becomes worthwhile. The takeaway is optimistic but honest: it usually improves, and help exists if it does not.
Are bioidentical hormones safer?
Not automatically. Bioidentical hormones — those chemically identical to your body’s own estradiol and progesterone — are well-studied in licensed, pharmaceutical-grade forms and are a perfectly good choice. The problem is with the safety claim attached to custom-compounded bioidentical products: because compounding is not regulated for the same consistency and dosing accuracy as licensed medicines, “bioidentical” does not by itself mean “lower risk.” The licensed, standardised versions of bioidentical hormones are the evidence-based default; be cautious of clinics selling “safer” custom-compounded versions at a premium without supporting data.
Will treating my hot flushes also help my brain fog?
Frequently, yes — and this is one of the most under-appreciated facts about hormone therapy menopause brain fog. Sleep disruption from night sweats is itself a major cause of daytime cognitive fog, and hot flushes can interrupt concentration directly. When hormone therapy calms the flushes and restores sleep, a substantial share of the “fog” often lifts as an indirect benefit — before or even without a direct cognitive effect of estrogen itself. This is why realistic trials need several weeks: the improvements can cascade.
The Bottom Line
Hormone therapy menopause brain fog is real, treatable, and — for many women — worth a serious conversation with a doctor. The October 2026 research reporting improvements in memory, focus, and mood is not hype; it reflects a mechanism we understand well: estrogen supports the brain’s glucose metabolism, its neurotransmitter balance, and its blood flow, and restoring it helps those systems recover. The key is timing and fit. Starting relatively early in the menopause transition, choosing the right route and combination, and giving it a realistic 4–12 weeks all tilt the outcome in your favor.
But you do not need hormones to act. SSRIs/SNRIs, cognitive behavioral therapy, and a committed lifestyle programme are defensible, evidence-backed options that many women use to clear the haze — with or without HT. The single most important step is to stop accepting “it’s just menopause” as the end of the conversation, and to walk into your next appointment with specific symptoms, a timeline, and a clear set of questions.
Your immediate action: write down three concrete examples of how brain fog has affected you this month, and book the appointment with your doctor or a menopause specialist. Bring this guide’s five questions with you.
If you are ready to explore what’s available, browse the MedsBase woman’s health category — and for the hormonal angle beyond estrogen, the TRT & PCT category covers testosterone-related options.
What to read next:
- Considering testosterone for low mood, energy, or libido? Our testosterone therapy for women guide explains the seven essential facts
- Worried about the cardiovascular side of hormone therapy? Read menopause hormone therapy and cardiovascular disease to weigh the risk honestly
Medical Disclaimer
This article is for informational purposes only and does not constitute medical advice. Hormone therapy carries real risks that vary by individual, preparation, dose, and duration of use, and the decision to start or stop treatment must be made with a qualified clinician who knows your full medical history. Never start, change, or stop any hormone therapy or medication based on online information alone.
Reviewed by Sophie Chen, PharmD. Last updated: October 13, 2026.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.