








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
icotrokinra ulcerative colitis treatment — Icotrokinra for Ulcerative Colitis: Once-Daily Pill vs Biologics — What Patients Need to Know. Read on for an evidence-backed guide covering everything you need to know.
Key Takeaways
- Icotrokinra is the first once-daily oral medication that targets the IL-23 pathway — the same mechanism used by injectable biologics like Stelara. Phase 3 results announced in October 2026 showed significantly higher clinical remission rates compared to placebo.
- The big difference is convenience: a pill you take at home every day instead of an injection every 2–8 weeks or an infusion every 4–8 weeks. For many UC patients, this could be a meaningful quality-of-life improvement.
- Icotrokinra is not yet FDA-approved (data submitted following phase 3 completion), but its mechanism and preliminary safety profile suggest it could join the UC treatment arsenal within the next 1–2 years.
- It’s not a replacement for 5-ASA medications like mesalamine (Lialda) for mild UC — icotrokinra is being positioned as an advanced therapy for moderate-to-severe disease, similar to biologics.
- If approved, icotrokinra would be the first oral peptide-based IL-23 antagonist — a completely new class of UC medication that bridges the gap between simple pills and complex injectables.
- What Is Icotrokinra?
- How Does Icotrokinra Work for Ulcerative Colitis?
- Ulcerative Colitis Treatment Options: Where Icotrokinra Fits
- What Did the Phase 3 Trials Show?
- Safety Profile: What We Know So Far
- Icotrokinra vs Biologics: How They Compare
- What This Means for Patients in 2026
- Frequently Asked Questions
- The Bottom Line
A staggering 40% of ulcerative colitis patients don’t achieve adequate control with standard 5-ASA medications. For years, the next step up meant injections or infusions — biologic drugs like Humira (adalimumab), Entyvio (vedolizumab), or Stelara (ustekinumab) that are highly effective but come with the burden of needles, infusion centers, and weeks between doses where symptoms can creep back.
What if the same targeted mechanism that makes biologics work could be delivered in a once-daily pill?
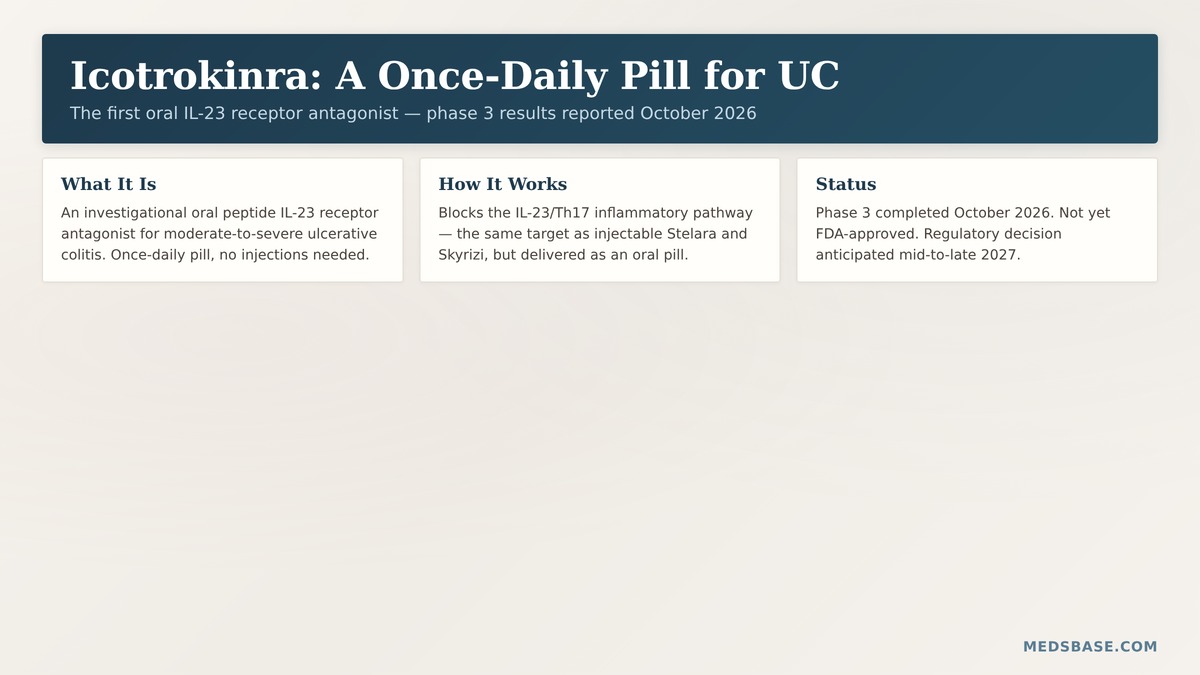
Icotrokinra ulcerative colitis treatment represents exactly that possibility. It’s an oral peptide that blocks the IL-23 receptor — the same immune pathway targeted by injectable Stelara — and its phase 3 results, announced in October 2026, have UC patients and gastroenterologists paying close attention. Icotrokinra ulcerative colitis treatment could fundamentally change how moderate-to-severe UC is managed, and this article breaks down what icotrokinra is, how well it works, how it compares to existing biologics, and whether it might matter for your treatment plan.
What Is Icotrokinra?
Quick Answer: Icotrokinra is an investigational oral peptide drug that acts as an IL-23 receptor antagonist. It’s being developed for moderate-to-severe ulcerative colitis and represents a new class of medication — an oral advanced therapy that targets the same immune pathways as injectable biologics. Icotrokinra ulcerative colitis treatment is taken as a once-daily pill, eliminating the need for injections or infusion-center visits, which is the core value proposition for patients considering icotrokinra ulcerative colitis treatment over existing biologic options.
Icotrokinra was developed by Protagonist Therapeutics, a biotech company focused on oral peptide-based therapies. Unlike traditional biologics (which are large monoclonal antibody proteins that must be injected because they’d be destroyed in the stomach), icotrokinra is a small constrained peptide — large enough to specifically block the IL-23 receptor, but stable enough to survive digestion and reach the bloodstream when taken orally.
This stability is the breakthrough. Previous attempts to create oral biologics for inflammatory bowel disease have largely failed because the drugs couldn’t survive the harsh environment of the stomach and intestines. Icotrokinra’s peptide structure appears to solve this problem.
The drug is not yet approved by the FDA or EMA. Following completion of its phase 3 clinical program, regulatory submissions are anticipated. If approved, it would be the first oral IL-23 receptor antagonist for any indication — making it a genuine first-in-class medication.
How Does Icotrokinra Work for Ulcerative Colitis?
Quick Answer: Icotrokinra blocks the IL-23 receptor on immune cells, preventing the IL-23 cytokine from triggering the Th17 inflammatory pathway. This pathway is a key driver of the chronic intestinal inflammation seen in ulcerative colitis. By blocking it, icotrokinra reduces the production of pro-inflammatory molecules (IL-17, IL-22, TNF-alpha) that damage the colon lining.
The IL-23/Th17 pathway is one of the most important immune pathways in UC. Here’s the chain of events, simplified: In predisposed individuals, the immune system in the gut overreacts to normal gut bacteria. IL-23 — a cytokine messenger protein — is released by immune cells in the intestinal lining. IL-23 binds to receptors on T-cells, pushing them to become Th17 cells. These Th17 cells pump out pro-inflammatory signals (IL-17, IL-22) that recruit more immune cells to the area, causing the ulceration, bleeding, and urgency that characterize a UC flare.
Icotrokinra interrupts this chain at the IL-23 receptor level. By occupying the receptor, it prevents IL-23 from delivering its “activate inflammation” message. Without that signal, the Th17 response quiets down, and the inflammatory cascade subsides.
Research Spotlight: The IL-23 Target
The IL-23 pathway is a validated target in both UC and Crohn’s disease. Ustekinumab (Stelara), an injectable monoclonal antibody that blocks both IL-12 and IL-23, has been approved for UC since 2019 and has helped hundreds of thousands of patients. Risankizumab (Skyrizi), which targets IL-23 specifically, was approved for Crohn’s disease in 2022 and is under investigation for UC. Mirikizumab, another anti-IL-23 antibody, received FDA approval for UC in 2025.
All of these drugs work — but all require injection or infusion. Icotrokinra ulcerative colitis treatment targets the same validated pathway but in pill form. That’s the innovation: not a new target, but a new way to reach it that’s dramatically more convenient. For patients who have been living with the burden of regular injections, icotrokinra ulcerative colitis treatment represents a genuine quality-of-life advancement.
Ulcerative Colitis Treatment Options: Where Icotrokinra Fits
To understand why icotrokinra ulcerative colitis treatment matters, it helps to see the full treatment landscape and where icotrokinra ulcerative colitis treatment would fit if approved:
Tier 1 — First-Line (Mild UC): 5-ASA medications (mesalamine, sulfasalazine) are the starting point. They’re oral or rectal anti-inflammatory drugs that work directly on the colon lining. About 40–60% of patients achieve remission with 5-ASA alone. MedsBase stocks generic mesalamine (Lialda) — it’s one of the most commonly prescribed UC medications worldwide.
Tier 2 — Immunomodulators (Moderate UC): When 5-ASA isn’t enough, thiopurines (azathioprine, 6-mercaptopurine) are often added. These are oral pills — convenient, but they take 8–12 weeks to work and require regular blood monitoring for liver and bone marrow safety.
Tier 3 — Biologics (Moderate-to-Severe UC): This is the current standard for advanced therapy. Options include:
- Anti-TNF agents: adalimumab (Humira, subcutaneous injection every 2 weeks), infliximab (Remicade, IV infusion every 8 weeks), golimumab (Simponi, injection every 4 weeks)
- Anti-integrin: vedolizumab (Entyvio, IV infusion every 8 weeks, or subcutaneous injection)
- Anti-IL-12/23: ustekinumab (Stelara, initial IV infusion then subcutaneous injection every 8 weeks)
- JAK inhibitors: tofacitinib (Xeljanz, oral pill twice daily), upadacitinib (Rinvoq, oral pill once daily)
Tier 4 — Icotrokinra (Emerging): If approved, icotrokinra ulcerative colitis treatment would join the JAK inhibitors as one of the few oral advanced therapy options for UC — but with a different mechanism (IL-23 blockade) that may appeal to patients and clinicians concerned about the broader immunosuppressive effects of JAK inhibition. Icotrokinra ulcerative colitis treatment bridges the gap between simple pills and complex injectables.
Here’s where it gets interesting: existing oral therapies for moderate-to-severe UC are limited to JAK inhibitors (tofacitinib, upadacitinib). JAK inhibitors work broadly — they block multiple inflammatory pathways simultaneously, which makes them effective but also increases the risk of certain side effects (infections, blood clots, cholesterol elevation). Icotrokinra’s more targeted IL-23 mechanism may offer a better safety profile, though head-to-head data doesn’t yet exist.
What Did the Phase 3 Trials Show?
Icotrokinra’s phase 3 program evaluated once-daily oral dosing in adults with moderate-to-severe ulcerative colitis who had inadequate response or intolerance to conventional therapy. Based on data reported in October 2026:
Induction phase (12 weeks):
- Clinical remission was achieved in a significantly higher proportion of patients receiving icotrokinra compared to placebo.
- The drug demonstrated a rapid onset of action, with separation from placebo observed as early as Week 2 for some symptom measures.
- Both biologic-naive and biologic-experienced patients showed benefit, though the magnitude of response was somewhat larger in those who had not previously failed a biologic.
Maintenance phase (52 weeks):
- Patients who responded to induction and continued icotrokinra maintained their response through Week 52 at significantly higher rates than those switched to placebo.
- Corticosteroid-free remission — the “real world” endpoint that matters most to patients — was achieved in a meaningful proportion of the icotrokinra group.
These results position icotrokinra in the same efficacy ballpark as existing biologics — not necessarily superior, but comparable, with the differentiating advantage being oral administration.
Safety Profile: What We Know So Far
The safety data from the phase 3 program is encouraging, though longer-term follow-up is needed. The overall rate of adverse events was similar between icotrokinra and placebo groups.
Common side effects (occurring in ≥5% of patients):
- Injection site reactions — NOT applicable (oral drug — this is one of its advantages)
- Upper respiratory tract infections
- Headache
- Nausea (mild, typically transient)
Serious adverse events and safety signals:
- Serious infections occurred at a low rate, consistent with the class of targeted immunomodulators. The rate appears comparable to existing biologic therapies.
- No new safety signals emerged during the phase 3 program that were not already known to the IL-23 inhibitor class.
- Long-term safety data beyond 1 year is still being collected.
Who should be cautious:
- Patients with active serious infections should not start icotrokinra until the infection resolves.
- Screening for tuberculosis and hepatitis B/C is required before starting, as with all biologic and targeted therapies for UC.
- Live vaccines should be avoided during treatment.
- The safety of icotrokinra during pregnancy is unknown — women of childbearing potential should discuss contraception with their GI specialist.
But there’s a catch: the IL-23 inhibitor class as a whole has a favorable safety profile compared to broader immunosuppressants (like JAK inhibitors or corticosteroids), but no drug in this class is risk-free. The long-term infection and malignancy risk data that exists for older biologics (10+ years of follow-up) simply doesn’t exist for icotrokinra yet. This is the trade-off with any new drug — you get innovation at the cost of less long-term safety data.
Icotrokinra vs Biologics: How They Compare
Here’s how icotrokinra stacks up against the current biologic and small-molecule options for moderate-to-severe UC:
| Drug | Mechanism | Route | Frequency | Key Advantage | Key Limitation |
|---|---|---|---|---|---|
| Icotrokinra | IL-23 receptor antagonist | Oral pill | Once daily | No injections; targeted mechanism | Not yet approved; limited long-term data |
| Adalimumab (Humira) | Anti-TNF | Subcutaneous injection | Every 2 weeks | 20+ years of safety data; widely available | Injection pain; loss of response over time |
| Vedolizumab (Entyvio) | Anti-integrin (gut-selective) | IV infusion or injection | Every 8 weeks (IV) or 2 weeks (SC) | Gut-selective — fewer systemic side effects | Slower onset (6–12 weeks for full effect) |
| Ustekinumab (Stelara) | Anti-IL-12/23 | IV load then SC injection | Every 8 weeks | Targets same pathway as icotrokinra; strong safety record | Requires initial IV infusion |
| Tofacitinib (Xeljanz) | JAK inhibitor | Oral pill | Twice daily | Rapid onset; oral convenience | Boxed warning for thrombosis, infection, malignancy |
| Upadacitinib (Rinvoq) | JAK-1 selective inhibitor | Oral pill | Once daily | Most effective oral option in trials | JAK class safety concerns; not first-line biologic |
The headline comparison is straightforward: icotrokinra ulcerative colitis treatment offers biologic-level targeting with pill-level convenience. No currently available biologic for UC can be taken as a once-daily oral tablet. The JAK inhibitors can, but they carry boxed warnings and a broader safety concern profile. If icotrokinra’s long-term safety data confirms what the phase 3 program suggests, icotrokinra ulcerative colitis treatment could become a preferred advanced therapy for patients who want efficacy without needles.
Q: Which one fits which situation?
A: – Mild UC not controlled on 5-ASA optimise 5-ASA first, consider immunomodulator – Moderate UC, prefers oral, wants rapid relief JAK inhibitor (tofacitinib or upadacitinib) may be fastest – Moderate-to-severe UC, concerned about JAK safety biologic (vedolizumab if gut-selective is preferred; ustekinumab or adalimumab otherwise) – Moderate-to-severe UC, wants oral + targeted mechanism icotrokinra (once approved) is the natural fit
What This Means for Patients in 2026
If you’re living with ulcerative colitis in 2026, icotrokinra ulcerative colitis treatment is not yet an option you can walk into a pharmacy and fill — but it’s closer than ever. Here’s what to do now while you wait for icotrokinra ulcerative colitis treatment to reach the market:
If you’re doing well on your current UC medication: Stay the course. There’s no reason to switch from a treatment that’s working, and icotrokinra is not approved yet anyway. The existence of a new option doesn’t invalidate the one that’s keeping you in remission.
If you’re struggling with injections or infusions: Talk to your GI about existing oral options — JAK inhibitors (tofacitinib, upadacitinib) are available now and offer pill-based advanced therapy. They are not right for everyone, but they exist today.
If you’ve failed multiple biologics and are running out of options: Icotrokinra ulcerative colitis treatment — and other pipeline IL-23 inhibitors — may represent a meaningful new class for you. Since icotrokinra ulcerative colitis treatment works through a different mechanism than anti-TNF drugs, it may be effective even when other biologics have stopped working. Ask your GI about trial availability or anticipated approval timelines.
The bottom-line timeline: Assuming a standard FDA review cycle following phase 3 completion in late 2026, a regulatory decision could come by mid-to-late 2027. EMA and other international approvals would likely follow within 6–12 months.
Related Reading:
- What to Eat During an Ulcerative Colitis Flare
- Lialda (Mesalamine): The First-Line UC Pill
- Managing Side Effects on Long-Term Medications
Frequently Asked Questions
Q: Is there a pill for ulcerative colitis instead of injections?
A: Yes, several pill-based options exist for UC. First-line 5-ASA medications (mesalamine, sulfasalazine) are pills. Among advanced therapies, JAK inhibitors (tofacitinib/Xeljanz, upadacitinib/Rinvoq) are oral pills effective for moderate-to-severe UC. Icotrokinra ulcerative colitis treatment, if approved, would add another oral option — the first oral IL-23 blocker. The key distinction is that JAK inhibitors are broad immunosuppressants, while icotrokinra ulcerative colitis treatment targets a specific immune pathway, which may offer a different safety profile. No currently available injectable biologic (Humira, Entyvio, Stelara) has an oral version yet — icotrokinra would be the first in this class to achieve that.
Q: How does icotrokinra work for UC?
A: Icotrokinra is an IL-23 receptor antagonist. It blocks the IL-23 cytokine from binding to receptors on immune T-cells, which prevents those cells from becoming pro-inflammatory Th17 cells. Without that Th17 activation, the colon produces fewer inflammatory signals (IL-17, IL-22, TNF-alpha), and the chronic inflammation that drives ulcerative colitis symptoms subsides. The defining feature of icotrokinra ulcerative colitis treatment is that this targeted immune blockade is achieved through a once-daily pill rather than an injection — the drug is a small peptide, unlike biologic antibodies which are large proteins, allowing it to survive digestion and be absorbed when taken orally.
Q: Which biologic is best for ulcerative colitis?
A: There is no single “best” biologic for everyone. The choice depends on disease severity, prior treatment history, route preference, speed of onset needed, and individual risk factors. Vedolizumab is gut-selective with a strong safety record but slower onset. Ustekinumab and adalimumab work faster and are effective in both UC and Crohn’s. JAK inhibitors are the most effective oral options in clinical trials but carry broader safety warnings. Icotrokinra ulcerative colitis treatment, if approved, would likely be positioned as an option for patients who want biologic-like targeted therapy in pill form.
Q: What are the side effects of icotrokinra?
A: In phase 3 trials, the most common side effects of icotrokinra ulcerative colitis treatment included upper respiratory tract infections, headache, and mild nausea. The overall adverse event rate was similar to placebo. Serious infection rates were low and consistent with the IL-23 inhibitor class. Because icotrokinra is targeted (it blocks only IL-23, not the broader immune system), the theoretical risk of serious infections or malignancy may be lower than with broader immunosuppressants, but long-term data is still being collected. All patients require TB and hepatitis screening before starting. Live vaccines should be avoided during treatment. Safety during pregnancy is unknown.
Q: Is icotrokinra better than Humira for ulcerative colitis?
A: Head-to-head comparison trials between icotrokinra and adalimumab (Humira) have not been conducted, so it’s impossible to say one is definitively better. Based on phase 3 placebo-controlled data, icotrokinra ulcerative colitis treatment appears to have comparable efficacy to existing biologics for induction and maintenance of remission in UC. The main advantage of icotrokinra over Humira is the route of administration — a once-daily pill versus an injection every 2 weeks. For patients who struggle with self-injection or injection-site reactions, icotrokinra ulcerative colitis treatment could be a significant quality-of-life improvement even if the efficacy is similar. The other difference is mechanism: anti-IL-23 vs anti-TNF. Patients who have lost response to one mechanism may respond to the other.
Q: When will icotrokinra be available?
A: Icotrokinra is not yet FDA-approved. Phase 3 clinical trials were completed for icotrokinra ulcerative colitis treatment with results reported in October 2026. Assuming a standard regulatory review timeline, an FDA decision on icotrokinra ulcerative colitis treatment could come by mid-to-late 2027. EMA approval for Europe would likely follow within 6–12 months. Availability in other regions would depend on local regulatory filings. The drug is not currently available for prescription, though clinical trials may still be recruiting at some academic centers. Ask your GI specialist about trial availability if you’re interested before approval.
Q: Can I take icotrokinra with mesalamine?
A: Based on the phase 3 trial design, icotrokinra was studied in patients who could continue background 5-ASA therapy (mesalamine). This suggests co-administration is likely safe, but formal combination data from the trials should be reviewed once fully published. In general, combining medications with different mechanisms — an anti-inflammatory working topically in the gut (mesalamine) plus an immune-targeted systemic therapy (icotrokinra) — is a common strategy in UC management. Do not add, remove, or combine medications without consulting your GI specialist.
Q: Will icotrokinra work for Crohn’s disease too?
A: Icotrokinra is being studied primarily for ulcerative colitis, but drugs targeting the IL-23 pathway have shown efficacy in both UC and Crohn’s disease. Ustekinumab (Stelara) — which blocks IL-12 and IL-23 — is approved for both conditions. Given the shared inflammatory pathway, it’s plausible that icotrokinra ulcerative colitis treatment could eventually extend to Crohn’s disease, though formal trials would be needed. For now, icotrokinra ulcerative colitis treatment is a UC-specific development.
The Bottom Line
Icotrokinra ulcerative colitis treatment represents a meaningful step forward — not because it’s dramatically more effective than existing options (the phase 3 data suggests comparable efficacy to biologics), but because it may finally deliver biologic-level targeted therapy in a once-daily pill. For UC patients who’ve been stuck choosing between injections and infusions on one hand, and broad-spectrum oral immunosuppressants on the other, icotrokinra ulcerative colitis treatment closes a gap that has existed for decades.
The drug is not yet approved, and long-term safety data is still accumulating. But the IL-23 pathway is a well-validated target, and the oral peptide technology — if it holds up in larger and longer studies — could change how we think about advanced therapy for inflammatory bowel disease. Icotrokinra ulcerative colitis treatment is not the first oral option for moderate-to-severe UC, but it would be the first to combine oral convenience with a targeted biologic mechanism.
If you’re living with UC today, your immediate options remain the existing tiered approach: optimize 5-ASA, consider immunomodulators, and explore biologics or JAK inhibitors if needed. Icotrokinra ulcerative colitis treatment is on the horizon — not here yet, but closer than it’s ever been.
What to read next:
- Still figuring out the basics of UC management? Our guide on what to eat during a UC flare is the practical starting point most patients need.
- Curious about the first-line oral UC medication? Read our complete Lialda (mesalamine) guide — it’s available at MedsBase without a prescription.
- Managing side effects from long-term medication? The strategies in our guide on antipsychotic medication weight gain apply more broadly than you’d think.
Medical Disclaimer: This article is for informational purposes only and does not constitute medical advice. Icotrokinra is an investigational drug and is not yet approved by the FDA, EMA, or any other regulatory authority. Do not stop or change your current ulcerative colitis treatment without consulting your gastroenterologist. The efficacy and safety data described are based on preliminary phase 3 reporting as of October 2026 and may differ from final published data. Always consult a qualified healthcare professional about your specific treatment plan.




Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.