








✓ Medically reviewed by · Last reviewed: May 2026
Pharmacy Researcher · 8 years experience
Pharmacy researcher with 8 years reviewing clinical drug information, generic formulation equivalence, and international pharmaceutical standards. Focuses on patient-facing accuracy in medication education.
rectal cancer immunotherapy — Rectal Cancer Immunotherapy: Dostarlimab (Jemperli) and the New Option to Avoid Chemo, Radiation, and Surgery. Read on for an evidence-backed guide covering everything you need to know.

- On October 19, 2026, the FDA approved Jemperli (dostarlimab-gxly) as a stand-alone rectal cancer immunotherapy for one specific, repair-defective tumour type (dMMR/MSI-H).
- It lets some patients skip chemotherapy, radiation and surgery — treatments that can permanently change bowel, bladder, sexual and fertility function.
- In the pivotal AZUR-1 trial, almost three-quarters of patients had not needed surgery, radiotherapy or chemotherapy after more than two years of follow-up.
- In an earlier Memorial Sloan Kettering study, none of the 50 patients had detectable cancer after treatment; 93% stayed cancer-free for at least 12 months.
- It is not for everyone — only about 3% of locally advanced rectal cancers are dMMR/MSI-H — and it comes with immune-related side effects that can be serious.
- What Is Rectal Cancer Immunotherapy?
- How Does Rectal Cancer Immunotherapy Work?
- Who Is Eligible for Rectal Cancer Immunotherapy?
- Safety Profile & Side Effects
- What Does the Research Say About Rectal Cancer Immunotherapy?
- Rectal Cancer Immunotherapy vs Standard Treatment
- How to Talk to Your Doctor About Rectal Cancer Immunotherapy
- Related Reading
- Frequently Asked Questions
- The Bottom Line
For most people diagnosed with locally advanced rectal cancer, the treatment plan has looked the same for years: chemotherapy and radiation first, then surgery to remove the tumour — surgery that carries a real risk of a permanent colostomy bag and lasting changes to bowel, bladder and sexual function. On October 19, 2026, that changed for a specific group of patients. The FDA approved Jemperli (dostarlimab-gxly), a rectal cancer immunotherapy used on its own, for people whose tumours have a particular genetic signature. By the end of this guide you will understand exactly how this rectal cancer immunotherapy works, who actually qualifies, what the trial numbers really show, the risks you should not overlook, and the right questions to ask your own oncology team.
One detail here is easy to miss but changes everything — and it has to do with a “brake” your immune system uses on purpose. We’ll get to it in a moment.
What Is Rectal Cancer Immunotherapy?
Quick answer: Rectal cancer immunotherapy is a treatment that uses drugs to help your own immune system recognise and destroy rectal cancer cells, instead of attacking the cancer directly with chemotherapy or radiation. The newest approved version is dostarlimab (Jemperli), a PD-1 inhibitor given as an infusion.
Rectal cancer immunotherapy is part of a larger family of treatments called immune checkpoint inhibitors. To understand why this particular approval is a big deal, you need one piece of background: a small subset of rectal cancers carries a mistake in the cellular machinery that normally repairs DNA. When that repair system — called mismatch repair — is broken, the tumour accumulates thousands of small genetic errors. Those errors produce abnormal proteins, and those abnormal proteins can make the tumour unusually “visible” to the immune system. Doctors describe such a tumour as mismatch repair deficient (dMMR) or microsatellite instability-high (MSI-H); the two terms describe the same underlying defect.
It is this specific tumour type, not rectal cancer generally, that has historically responded dramatically to checkpoint-inhibitor immunotherapy. In metastatic colorectal cancer, drugs that block the protein PD-1 have produced striking and durable responses in dMMR/MSI-H tumours, which is why researchers turned to them earlier in the disease, before any surgery. The result is the approval you are reading about today. For broader context on how colorectal and rectal cancers are detected, the NCI provides an overview of colorectal cancer.
How Does Rectal Cancer Immunotherapy Work?

The idea behind rectal cancer immunotherapy is not to poison the tumour, but to take the foot off your immune system’s brakes. Your T-cells — the immune system’s attack cells — are capable of killing cancer, but tumours frequently escape by raising a “do not attack” flag. That flag is a protein called PD-1 (on the immune cell) connecting with its partner PD-L1 (on the tumour cell). When the two bind, the T-cell stands down.
Dostarlimab is a monoclonal antibody that blocks PD-1. By covering the receptor, it prevents the tumour from sending the “stand down” signal, so your T-cells are free to sweep in and destroy the cancer cells. This is the same logic behind the PD-1 immunotherapy class reviewed for dostarlimab, and it only works well in tumours that are already immunogenic — which is exactly why the dMMR/MSI-H signature matters so much. The cellular errors in these tumours generate the very proteins that flag them to the immune system once the brake is lifted.
Here’s where it gets interesting. Standard rectal cancer treatment is aggressive partly because surgery aims to remove the entire tumour and surrounding lymph nodes. But if immunotherapy can achieve what clinicians call a “clinical complete response” — meaning no cancer is detectable on scans, biopsies and physical examination — then the need for radiation and surgery effectively disappears. That is the entire promise of this approval.
Who Is Eligible for Rectal Cancer Immunotherapy?
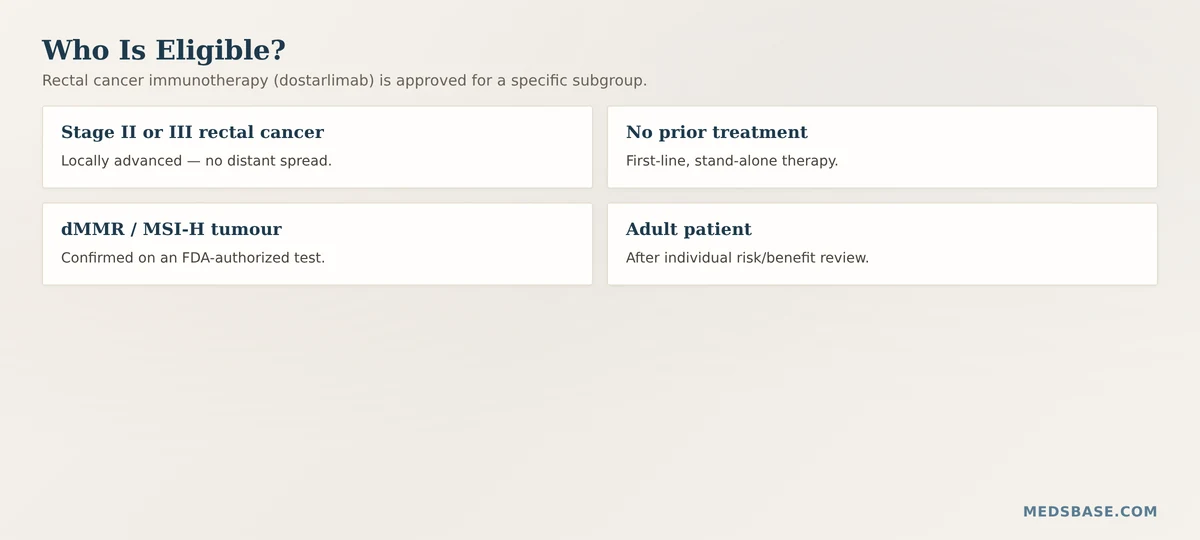
The approval is narrower than most headlines suggest. Four conditions must generally be met:
- The cancer is stage II or stage III locally advanced rectal cancer — it has grown into nearby tissue or reached nearby lymph nodes, but has not spread to distant organs.
- No prior treatment for this cancer — dostarlimab is approved as first-line, stand-alone therapy.
- The tumour is dMMR or MSI-H, confirmed by an FDA-authorized laboratory test.
- The patient is an adult whose doctor agrees the risk/benefit is appropriate after a full assessment.
Because dMMR/MSI-H tumours are relatively rare, only about 3% of locally advanced rectal cancers meet this signature. So while the news is genuinely transformative, the honest framing is that most rectal cancer patients will still follow the standard chemotherapy, radiation and surgery route.
- Who it’s for: adults with newly diagnosed, previously untreated stage II/III rectal cancer whose tumour tests dMMR or MSI-H, and who are open to a treatment that may let them avoid surgery and its permanent effects.
- Who should avoid it (or proceed with caution): people whose tumour is mismatch-repair proficient (the majority), anyone whose cancer has already spread to distant organs, people with active autoimmune disease (immunotherapy can worsen it), and anyone who has had an organ transplant or recent immune-suppressing therapy. A doctor must make this call individually.
Safety Profile & Side Effects
Rectal cancer immunotherapy does not come free of risk. Because it releases the brakes on the entire immune system, it can sometimes cause the immune system to attack healthy organs. These immune-related side effects can be serious and, in rare cases, fatal.
The most common side effects reported in the rectal cancer trials (each in at least 15% of patients) were fatigue, rash, diarrhoea and itching.
| Side Effect | Frequency | Severity | What It Signals |
|---|---|---|---|
| Fatigue | Common (≥15%) | Usually mild | Often manageable; monitor for worsening |
| Rash | Common (≥15%) | Mild–moderate | Immune-related skin reaction |
| Diarrhoea | Common (≥15%) | Can be serious | May signal colitis — tell your team promptly |
| Itching | Common (≥15%) | Mild | Usually alongside rash |
| Immune attack on other organs | Less common | Can be severe/fatal | Lungs, liver, thyroid, kidneys, glands |
The key safety lesson is not to tough it out. Diarrhoea, in particular, can be an early sign of immune-mediated colitis, and catching it early makes it far easier to manage. Your oncology team will monitor you closely during and after the infusions, and they will want to know about any new symptom — even a mild one — as soon as it starts.
What Does the Research Say About Rectal Cancer Immunotherapy?

Two studies drive this approval, and their numbers are worth understanding precisely because the strength of this rectal cancer immunotherapy is unusually dramatic.
The first is the landmark study published in the New England Journal of Medicine from Memorial Sloan Kettering Cancer Center. In that phase 2 trial (NCT04165772), 50 patients with previously untreated dMMR/MSI-H locally advanced rectal cancer received single-agent dostarlimab every three weeks for six months. The result was striking: none of the patients had detectable signs of cancer after treatment, and nearly all — 93% — maintained that cancer-free status for at least 12 months. Of the 27 patients followed for at least three years, only one had their cancer return.
The second is the larger confirmatory AZUR-1 phase 2 study, which enrolled 154 patients. After a median follow-up of more than two years, almost three-quarters of patients had not needed surgery, radiotherapy or chemotherapy.
| Study | Year | Finding | Source |
|---|---|---|---|
| MSKCC phase 2 (NCT04165772) | 2022 | 50 patients; none had detectable cancer; 93% stayed clear ≥12 months | NEJM (PMID 35660797) |
| AZUR-1 (NCT05723562) | 2026 | 154 patients; ~75% avoided surgery/radiation/chemo at >2 years | FDA / ClinicalTrials.gov |
What this means for you: these are unusually strong early results by oncology standards, but the approval is accelerated — meaning the FDA based it on early response measures while requiring longer follow-up to confirm the responses are lasting. The honest summary is that this rectal cancer immunotherapy looks remarkably effective for the right tumour type, but the durability question is still being answered.
Rectal Cancer Immunotherapy vs Standard Treatment

The contrast between the two paths is the real story, so it helps to see them side by side.
| Standard treatment | Rectal cancer immunotherapy (dostarlimab) | |
|---|---|---|
| What it involves | Chemotherapy + radiation, then surgery | Up to 9 IV infusions over ~6 months |
| Main burden | Permanent bowel/bladder/sexual/fertility changes; possible permanent colostomy; surgical risks | Immune-related side effects (fatigue, rash, diarrhoea, organ inflammation) |
| Evidence base in dMMR/MSI-H | Long-established curative approach | ~75% avoided surgery; durability still being confirmed |
The verdict depends entirely on your tumour’s mismatch-repair status. If your tumour is dMMR/MSI-H, the immunotherapy path offers a genuine chance to avoid the most life-altering parts of treatment. If it is mismatch-repair proficient, the standard path remains the right, evidence-backed choice, because immunotherapy is dramatically less effective in those tumours.
How to Talk to Your Doctor About Rectal Cancer Immunotherapy
If you have been newly diagnosed with rectal cancer, walk into the conversation prepared — and if you have not already had MSI/dMMR testing, ask for it up front.
- Ask for MSI/dMMR testing. This single test determines whether immunotherapy is even on the table. It is standard in many centres but worth confirming explicitly.
- Confirm your stage. This approval is for stage II/III without distant spread. Ask exactly where your cancer is and whether it has spread.
- Ask which immunotherapy and why. If eligible, clarify the drugs being discussed and whether they are the same class as dostarlimab.
- Review the immune-related risks. Make sure you understand what symptoms to report immediately and who to call.
- Understand that follow-up is part of the deal. Because this is an accelerated approval, response monitoring and possibly confirmatory follow-up matter.
If you are already managing a chronic condition and want to understand how treatment decisions fit into a wider health picture, you can explore chronic conditions treatment options on MedsBase.
Related Reading
Frequently Asked Questions
Q: What is rectal cancer immunotherapy?
A: Rectal cancer immunotherapy is a treatment that uses your own immune system to fight rectal cancer rather than attacking the tumour with chemotherapy or radiation. The newest version, dostarlimab (Jemperli), is a PD-1 inhibitor that unblocks immune cells so they can destroy the cancer.
Q: How does dostarlimab work?
A: Dostarlimab blocks the PD-1 protein on T-cells. Tumours use PD-1 to send a “do not attack” signal to the immune system; by blocking it, dostarlimab lets T-cells recognise and attack the cancer. It is most effective in dMMR/MSI-H tumours, which carry many abnormal proteins the immune system can already see.
Q: Can rectal cancer immunotherapy cure rectal cancer?
A: The early evidence is striking but not final. In the MSKCC study, none of 50 patients had detectable cancer after treatment and 93% stayed clear for at least 12 months. In the larger AZUR-1 trial, about three-quarters avoided surgery, radiation and chemo. However, the approval is accelerated, and longer follow-up is still needed to confirm lasting benefit.
Q: Who is eligible for dostarlimab?
A: Adults with previously untreated stage II or III locally advanced rectal cancer whose tumour is dMMR or MSI-H (confirmed by an FDA-authorized test) and has not spread to distant organs. Only about 3% of locally advanced rectal cancers meet this signature.
Q: Is rectal cancer immunotherapy safe?
A: It can cause the immune system to attack healthy organs, and these reactions can be severe or even fatal in rare cases. The most common side effects are fatigue, rash, diarrhoea and itching. It is not right for everyone, especially those with active autoimmune disease.
Q: How is dostarlimab given?
A: Dostarlimab is given as an intravenous infusion, every three weeks, for up to nine doses over about six months. There is no surgery, radiation or oral pill involved for this indication.
Q: What is the difference between dMMR and MSI-H?
A: They describe the same underlying problem: a defect in the cell’s system for correcting DNA-copying errors. dMMR (mismatch repair deficient) and MSI-H (microsatellite instability-high) are two ways of measuring and naming that same repair defect.
Q: Does rectal cancer immunotherapy work for all rectal cancer?
A: No. It is dramatically less effective in mismatch-repair-proficient tumours, which make up the large majority of rectal cancers. For most patients, the standard chemotherapy, radiation and surgery sequence remains the evidence-backed approach.
Q: What should I ask my doctor about rectal cancer immunotherapy?
A: Start by asking for MSI/dMMR testing on your tumour. Then confirm your stage, ask whether you qualify, review the immune-related side effects and the monitoring plan, and understand that longer-term follow-up is part of the treatment.
The Bottom Line
Rectal cancer immunotherapy is a genuine turning point — but for a narrow, precisely defined group of patients. For someone with a newly diagnosed dMMR/MSI-H stage II or III rectal cancer, it offers the first realistic chance to avoid chemotherapy, radiation and surgery and their permanent costs to daily life. For everyone else, the standard treatment plan remains correct. Your immediate action, if this resonates, is specific: ask your oncology team for your tumour’s MSI/dMMR status before finalising any treatment plan. Wondering how treatment decisions like this compare to other everyday medical choices? Read our guide to isotretinoin for acne for a different treatment-decision explainer, or see how we break down a head-to-head choice in losartan vs valsartan.

Written by
Sophie ChenPharmaceutical Content Researcher · 8 years experience
Sophie Chen is a pharmaceutical content researcher with 8 years covering generic medication access and clinical pharmacology. She specialises in international regulatory frameworks, bioequivalence standards, and patient-facing education on therapeutic drug classes. She is not a clinician.
Pingback: Isotretinoin for Acne: 7 Proven Facts Before You Start